⚠ Evidence warning: Clinical trials or other evidence do not support the claim that myrrh produces clinically meaningful, coxib-like anti-inflammatory and pain-relieving effects that help osteoarthritis and rheumatoid arthritis, or that myrrh and frankincense combinations work together against joint inflammation (no human trial of myrrh for either disease was found, and the combination synergy data come from a laboratory antimicrobial study). This page keeps it as a report of what people, websites or other media say.
Myrrh Anti-Inflammatory
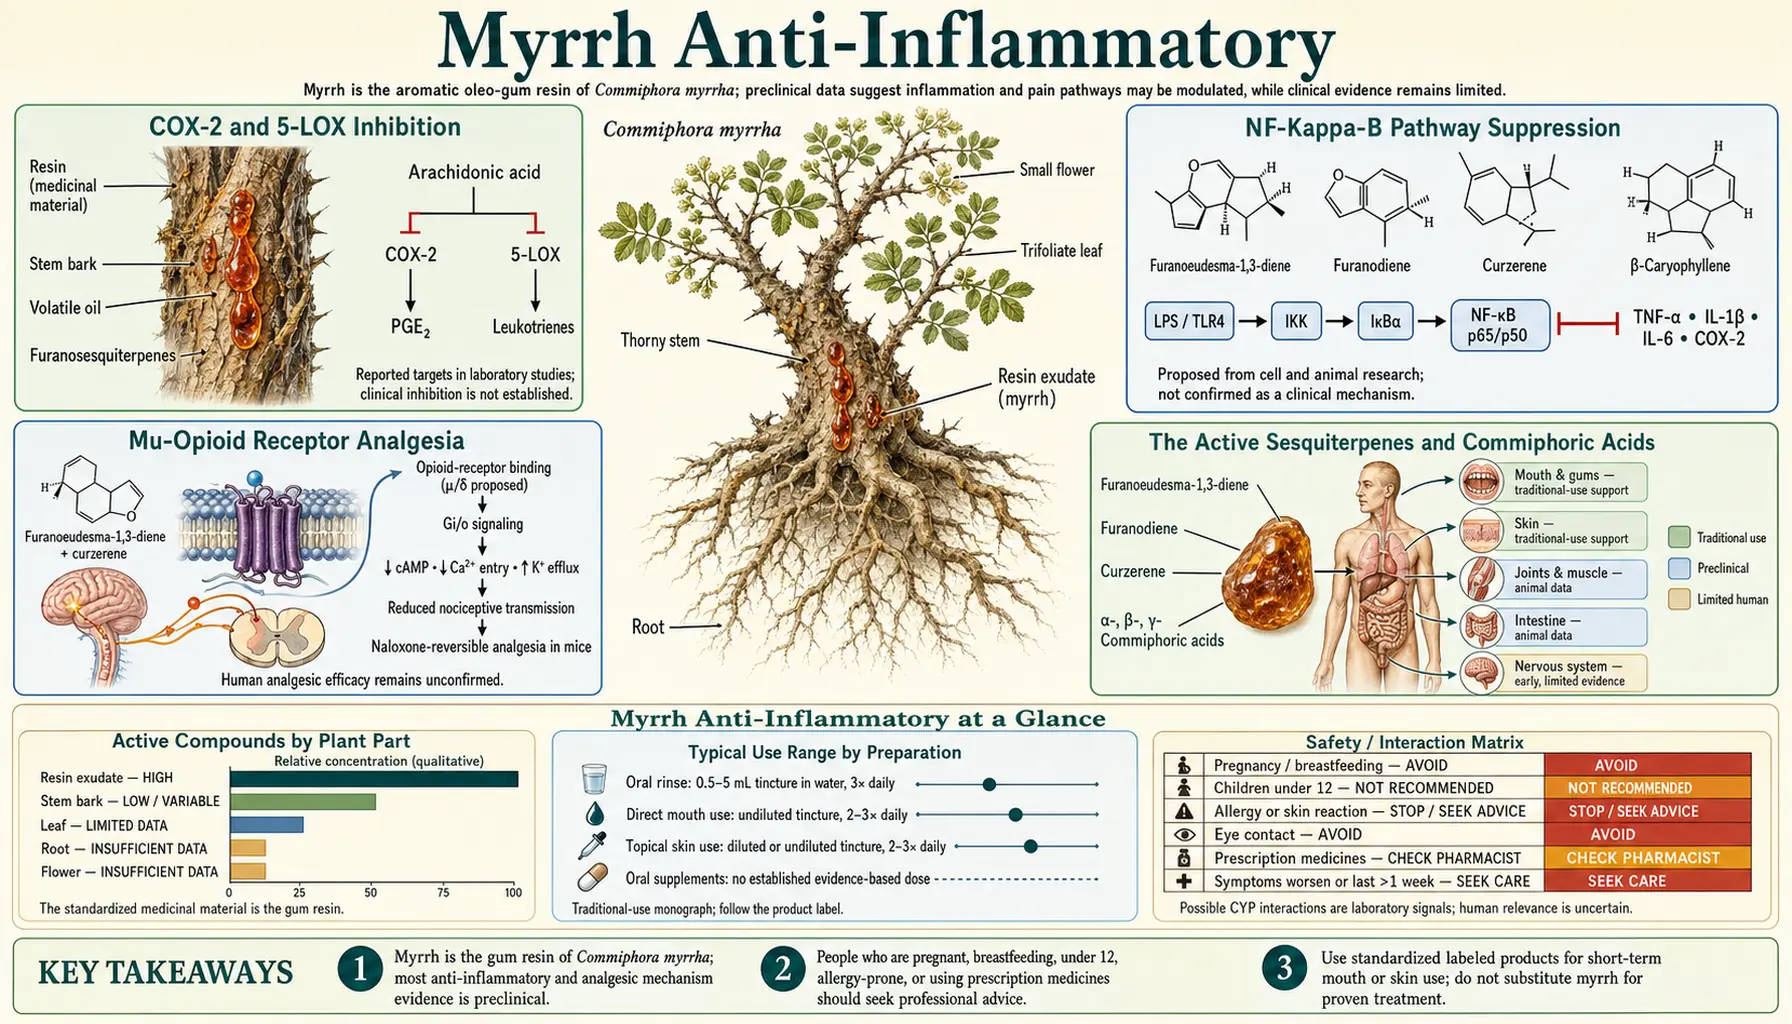
Myrrh is one of two ancient aromatic tree resins (the other being frankincense, Boswellia sacra or Boswellia serrata) that produce clinically meaningful anti-inflammatory effects through parallel but distinct mechanisms. Both resins inhibit the cyclooxygenase (COX) and lipoxygenase (LOX) enzymes responsible for producing pro-inflammatory prostaglandins and leukotrienes, but they do so through different active compound classes — myrrh through sesquiterpenes (curzerene, furanoeudesma-1,3-diene) and commiphoric acids, frankincense through boswellic acids. The two resins have been used together since antiquity in Egyptian, Biblical, Ayurvedic, and traditional Chinese medicine, and modern laboratory studies confirm that the combination produces synergistic anti-inflammatory effects greater than either resin alone. Traditional applications focus on osteoarthritis, rheumatoid arthritis, and other chronic inflammatory conditions. Furanosesquiterpenes also bind directly to mu-opioid receptors, providing complementary analgesia — an effect unusual among common herbs and documented in a landmark 1996 Nature paper by Dolara and colleagues. This page covers the molecular mechanisms, the comparison to Boswellia, the traditional and contemporary inflammatory-disease applications, and the practical use of myrrh as an anti-inflammatory adjunct.
Table of Contents
- Cyclooxygenase-2 and 5-LOX Inhibition
- NF-Kappa-B Pathway Suppression
- Mu-Opioid Receptor Analgesia
- The Active Sesquiterpenes and Commiphoric Acids
- Osteoarthritis — Traditional and Modern Use
- Rheumatoid Arthritis — Traditional Use and Mechanism
- Myrrh vs Boswellia — Two Resins, Two Mechanisms
- Combined Myrrh + Frankincense Synergy
- Other Inflammatory Applications
- Dosing and Forms for Anti-Inflammatory Use
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Cyclooxygenase-2 and 5-LOX Inhibition
Two enzymatic pathways dominate the production of inflammatory lipid mediators in mammalian cells: the cyclooxygenase (COX) pathway and the lipoxygenase (LOX) pathway. Both start from arachidonic acid, a 20-carbon polyunsaturated fatty acid released from membrane phospholipids by phospholipase A2 during inflammation, tissue damage, or other activating stimuli.
The COX pathway converts arachidonic acid into prostaglandin H2 (PGH2), which is then further metabolized by tissue-specific synthases into the various prostaglandins (PGE2, PGD2, PGI2, etc.) and thromboxanes that mediate pain, swelling, fever, and platelet aggregation. COX exists in two principal isoforms: cyclooxygenase-1 (COX-1) is constitutively expressed and produces "housekeeping" prostaglandins that maintain gastric mucosal integrity, renal blood flow, and platelet function; cyclooxygenase-2 (COX-2) is inducible by inflammatory stimuli and produces the prostaglandins responsible for inflammatory pain, swelling, and fever. Most nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, aspirin) inhibit both cyclooxygenase-1 and cyclooxygenase-2 to varying degrees, while the "coxibs" (celecoxib, etoricoxib) selectively inhibit cyclooxygenase-2 to spare cyclooxygenase-1's gastric and renal functions.
Myrrh sesquiterpenes inhibit cyclooxygenase-2 with apparent selectivity over cyclooxygenase-1, producing an anti-inflammatory effect mechanistically analogous to the coxib class of drugs but at lower potency. The inhibition is dose-dependent and reversible. Curzerene, furanoeudesma-1,3-diene, and lindestrene have all shown cyclooxygenase-2 inhibitory activity in cell-free enzyme assays and in cellular inflammation models. The proposed clinical significance is a coxib-like prostaglandin reduction that lowers inflammatory pain and swelling. Whether myrrh carries less stomach-ulcer risk than long-term nonsteroidal anti-inflammatory drug (NSAID) use has not been studied in people; no human study of myrrh and stomach ulcers was found.
The animal evidence is mixed. In a 2011 mouse study (Su 2011), an 85% ethanol extract of Commiphora myrrha reduced paw swelling caused by a formalin injection, and its petroleum-ether fraction (100 mg/kg) worked more strongly and lowered the level of the inflammatory messenger prostaglandin E2 (PGE2) in the swollen paw. The ethanol extract and the petroleum-ether fraction also reduced writhing caused by an acetic-acid injection, a chemical pain test. But none of the extracts raised the pain threshold on the hot-plate test, a heat pain test. These are mouse results; the study did not measure cyclooxygenase-2 itself, and there are no human data on myrrh and cyclooxygenase-2.
The LOX pathway diverts arachidonic acid into leukotrienes — potent inflammatory mediators particularly important in asthma, allergic inflammation, and chronic inflammatory bowel disease. 5-lipoxygenase (5-LOX) is the rate-limiting enzyme in leukotriene production, and 5-LOX inhibition is how the asthma drug zileuton works; the related drugs montelukast and zafirlukast work differently, blocking the leukotriene receptor (the cysteinyl leukotriene 1 receptor) instead (García-Marcos 2003). Myrrh sesquiterpenes and commiphoric acids inhibit 5-LOX in addition to cyclooxygenase-2, producing a dual-pathway suppression of lipid inflammatory mediators that is broader than the effect of any single-pathway pharmaceutical. This dual COX/LOX inhibition resembles the proposed mechanism of Boswellia's boswellic acids and helps explain why both resins have been used historically for joint and respiratory inflammatory conditions.
NF-Kappa-B Pathway Suppression
Beyond the lipid mediator pathways, chronic inflammation is driven by transcriptional regulation of inflammatory gene expression. The master transcription factor in inflammatory gene expression is NF-kappa-B (nuclear factor kappa-light-chain-enhancer of activated B cells), a heterodimeric protein complex that, when activated, translocates from the cytoplasm into the nucleus and binds to specific DNA response elements upstream of hundreds of inflammatory genes. NF-kappa-B target genes include the cytokines (tumor necrosis factor-alpha, interleukin-1-beta, interleukin-6, IL-8), chemokines, adhesion molecules, cyclooxygenase-2 itself, inducible nitric oxide synthase (iNOS), matrix metalloproteinases, and many others.
In the resting state, NF-kappa-B is held in the cytoplasm by its inhibitor I-kappa-B. Inflammatory stimuli (tumor necrosis factor-alpha, interleukin-1 (IL-1), oxidative stress, pathogen-associated molecular patterns) activate the I-kappa-B kinase (IKK) complex, which phosphorylates I-kappa-B and targets it for ubiquitination and proteasomal degradation. Once freed from I-kappa-B, NF-kappa-B translocates to the nucleus and turns on the inflammatory gene program. Chronic activation of NF-kappa-B is implicated in essentially every chronic inflammatory disease, from rheumatoid arthritis and inflammatory bowel disease to atherosclerosis, type 2 diabetes, and many cancers.
Myrrh sesquiterpenes have been shown to suppress NF-kappa-B activation through multiple mechanisms: inhibition of I-kappa-B phosphorylation by IKK, stabilization of I-kappa-B against proteasomal degradation, and direct interference with NF-kappa-B DNA binding. The result is suppressed transcription of the entire NF-kappa-B-dependent inflammatory gene program, including tumor necrosis factor-alpha, interleukin-1-beta, interleukin-6 (IL-6), cyclooxygenase-2 (further amplifying the direct cyclooxygenase-2 enzymatic inhibition described above), and iNOS.
This NF-kappa-B suppression mechanism is shared with several other plant-derived anti-inflammatory compounds, including curcumin from turmeric, resveratrol from grapes, and the boswellic acids from frankincense. The shared mechanism explains why these compounds are often discussed together in the broader natural-medicine literature on chronic inflammation, and why combination preparations (myrrh + frankincense + turmeric + ginger, for example) appear in many traditional and contemporary anti-inflammatory formulations.
Mu-Opioid Receptor Analgesia
An unusual and clinically meaningful feature of myrrh's pharmacology is direct mu-opioid receptor agonism by specific furanosesquiterpene compounds. This mechanism was definitively established in a landmark 1996 paper in Nature by Dolara and colleagues, who isolated furanoeudesma-1,3-diene and curzerene from Commiphora molmol resin and demonstrated that these compounds produced dose-dependent analgesia in mouse hot-plate and tail-flick assays. Critically, the analgesia was reversed by naloxone, a selective opioid receptor antagonist — establishing that the compounds were acting through the opioid receptor system rather than through an unrelated analgesic mechanism.
The first test in people was a small 2017 pilot study (Germano 2017). It gave 95 female and 89 male volunteers with headache, fever-related pain, joint pain, muscle aches, lower back pain or menstrual cramps one capsule a day of a Commiphora myrrha extract standardised for its furanodiene-type compounds (200 mg or 400 mg, carrying 8 mg or 16 mg of these compounds) or a placebo capsule for 20 days. The authors reported pain relief in men at 400 mg a day for almost all the pain types, and in women relief of lower back pain and fever-related pain at 200 mg a day. It is a pilot study, not a full trial, and the abstract does not describe how volunteers were assigned to groups or whether anyone was blinded.
The clinical implication is that myrrh produces both anti-inflammatory effects (through COX, LOX, and NF-kappa-B inhibition) and direct analgesic effects (through mu-opioid receptor agonism). The combination is mechanistically attractive for inflammatory pain conditions: rather than addressing only the inflammation (as an isolated COX inhibitor would) or only the pain (as an isolated opioid would), myrrh addresses both simultaneously.
The opioid agonist activity of myrrh is comparatively weak — the binding affinity of furanoeudesma-1,3-diene at the mu-opioid receptor is several orders of magnitude lower than that of morphine or fentanyl — but at the high local concentrations achievable in topical mucosal application (myrrh tincture applied to an aphthous ulcer, for example), the analgesia is clinically perceptible within minutes of application. In systemic use (oral tincture, capsules), the opioid contribution is more modest but still measurable.
The opioid mechanism explains why myrrh has been used for pain management across virtually every traditional medical system since antiquity. Egyptian physicians used it for wound pain. Greek and Roman physicians used it for joint pain, dental pain, and surgical wound pain. Chinese traditional medicine uses it for chronic pain syndromes and traumatic injury. Ayurvedic medicine uses it for rheumatic pain and abdominal cramping. The traditional uses converge on pain because the underlying mechanism is shared across all of them: weak mu-opioid receptor agonism combined with anti-inflammatory action.
An important safety consideration: while myrrh's opioid activity is weak, it is potentially additive with conventional opioid medications and with other central nervous system (CNS) depressants. The concern is additive central nervous system depression — deeper drowsiness — when myrrh is combined with prescribed opioid pain medications, alcohol, benzodiazepines, or sedating antihistamines.
The Active Sesquiterpenes and Commiphoric Acids
The active compounds responsible for myrrh's anti-inflammatory effects belong to two principal chemical classes: sesquiterpenes (volatile 15-carbon terpenoids in the essential oil fraction) and commiphoric acids (resinous acids unique to the Commiphora genus).
Sesquiterpenes account for the majority of the volatile fraction of myrrh and include over 200 identified individual compounds. The principal anti-inflammatory sesquiterpenes:
- Curzerene — 15-30% of myrrh essential oil; inhibits cyclooxygenase-2 and 5-LOX; suppresses NF-kappa-B
- Furanoeudesma-1,3-diene — 5-20% of myrrh oil; acts on opioid receptors (Dolara 1996); anti-inflammatory and analgesic
- Lindestrene — 5-15% of myrrh oil; antibacterial and anti-inflammatory
- Beta-elemene and delta-elemene — immunomodulatory effects; investigated for anticancer activity in addition to anti-inflammatory action
- Furanodiene — mu-opioid receptor activity; potent NF-kappa-B suppression
- Furanodienone — anti-inflammatory and antibacterial; structurally distinctive furanosesquiterpene
- Methoxyfuranoguaia-9-ene-8-one — together with furanodiene-6-one, showed antibacterial and antifungal activity and local-anaesthetic (sodium-channel blocking) activity in laboratory tests (Dolara 2000)
- Beta-eudesmol and alpha-copaene — broad-spectrum anti-inflammatory and antimicrobial effects
Commiphoric acids are a group of resinous acids specific to Commiphora species, including alpha-commiphoric acid, beta-commiphoric acid, and commiphorinic acid. They contribute to the anti-inflammatory effect through cyclooxygenase-2 inhibition, NF-kappa-B suppression, and direct binding to inflammatory cell surface receptors. The commiphoric acids are concentrated in the resin fraction rather than the volatile oil fraction, which is why myrrh tincture (which extracts the resin) and powdered myrrh resin retain anti-inflammatory activity even when much of the volatile oil has evaporated.
The compositional variability between myrrh samples is substantial. Commiphora myrrha, Commiphora molmol, and several other Commiphora species are all sold commercially as "myrrh," and the volatile compound profile differs significantly between species and even between geographic populations of the same species. Somali and Ethiopian myrrh from the Horn of Africa is generally considered the highest-quality medicinal product, with Yemeni and Arabian sources also valued. Quality control of commercial myrrh products is challenging, and reproducibility of clinical effects requires either standardized extracts (such as a standardized Egyptian myrrh preparation) or carefully sourced raw resin from established suppliers.
Osteoarthritis — Traditional and Modern Use
Osteoarthritis (OA) is the most common form of joint disease, affecting about 595 million people worldwide in 2020, 7.6% of the world's population (Global Burden of Disease Study 2021). It is characterized by progressive degradation of articular cartilage, subchondral bone changes, synovial inflammation, and joint pain that worsens with activity and improves with rest. Conventional pharmaceutical management relies on nonsteroidal anti-inflammatory drugs (NSAIDs) and acetaminophen for symptomatic relief, with corticosteroid injections, hyaluronic acid injections, and ultimately joint replacement surgery for advanced disease. The chronic nonsteroidal anti-inflammatory drug use that osteoarthritis often requires carries significant cumulative risk: gastric ulceration, renal injury, cardiovascular events.
Both myrrh and Boswellia (frankincense) have a long traditional use in joint pain and stiffness across Egyptian, Greco-Roman, Ayurvedic, traditional Chinese, and Middle Eastern medical traditions. The traditional preparations typically involve oral tinctures, capsules of powdered resin, or topical liniments applied directly to affected joints. The combination of myrrh and frankincense is particularly traditional in Egyptian and Ayurvedic practice and is considered to produce greater effect than either resin used alone (see the synergy section below).
Modern clinical research on myrrh specifically for osteoarthritis is limited, but the much larger body of research on Boswellia (boswellic acids) for OA establishes the proof of principle that resin-derived COX/LOX/NF-kappa-B-inhibitory compounds produce clinically meaningful improvements in OA pain and function. Several randomized controlled trials of standardized boswellia extracts have shown statistically significant improvements in WOMAC pain and function scores in knee OA compared to placebo. The mechanistically parallel activity of myrrh suggests similar clinical benefit, and the synergy data support the use of myrrh + frankincense combination preparations for OA management.
Practical considerations: for patients with knee, hip, or hand osteoarthritis interested in herbal anti-inflammatory adjuncts, a typical regimen combines internal use (300-600 mg powdered myrrh resin two to three times daily, or equivalent tincture dosing) with topical application of a myrrh-containing liniment to affected joints twice daily. Continuous use for 8-12 weeks is generally required to establish clinical benefit. The combination with boswellia, curcumin (from turmeric), and ginger is common in commercial herbal anti-inflammatory products and produces additive or synergistic effects in laboratory models. For more on conventional and complementary OA management, see our Osteoarthritis page.
Rheumatoid Arthritis — Traditional Use and Mechanism
Rheumatoid arthritis (RA) is a chronic autoimmune disease characterized by symmetric polyarthritis, particularly affecting the small joints of the hands and feet, with associated systemic inflammation that can affect the lungs, cardiovascular system, and other organs. Unlike osteoarthritis (which is fundamentally a degenerative process), rheumatoid arthritis is driven by autoimmune attack on synovial tissue, with elevated levels of inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, interleukin-1-beta) driving cartilage destruction, bone erosion, and ultimately joint deformity.
Modern rheumatoid arthritis management has been revolutionized by the disease-modifying anti-rheumatic drugs (DMARDs), particularly the biologic agents that target specific inflammatory cytokines (anti-TNF agents: infliximab, etanercept, adalimumab; anti-IL-6: tocilizumab; anti-IL-1: anakinra; JAK inhibitors: tofacitinib, baricitinib). These therapies have transformed the prognosis of rheumatoid arthritis from progressive joint destruction to often complete clinical remission. The conventional first-line approach is methotrexate, often combined with a biologic agent in patients with inadequate response.
Traditional myrrh use in rheumatoid arthritis-like conditions long predated the modern understanding of autoimmunity. Greco-Roman physicians used myrrh for "joint flux" and "arthritic pain"; Ayurvedic medicine uses myrrh-containing formulations for "Vata-Kapha joint disorders"; traditional Chinese medicine uses mo yao for "blood-stasis joint pain." The traditional applications are consistent with the modern understanding of myrrh's mechanism: cyclooxygenase-2 and 5-LOX inhibition reduce the lipid inflammatory mediators in synovial fluid; NF-kappa-B suppression reduces transcription of inflammatory cytokines and adhesion molecules; mu-opioid receptor agonism provides direct pain relief.
The clinical role of myrrh in modern rheumatoid arthritis management is necessarily adjunctive. The biologic and conventional DMARD therapies produce vastly larger effect sizes on joint inflammation and disease progression than any herbal preparation, and rheumatology care for active rheumatoid arthritis is built on these drugs. Within this framework, practitioners describe myrrh as a possible supplementary anti-inflammatory and analgesic agent in patients with residual symptoms on optimized conventional therapy, or as one component of an integrative approach in patients with milder disease who are hesitant to start aggressive pharmacotherapy. The drug interactions of most concern are with methotrexate (which has hepatic clearance that can be affected by herbal liver-active compounds) and with the blood thinner warfarin (a published case report describes myrrh weakening warfarin's effect; see Cautions).
For more on the autoimmune-disease context, see our Rheumatoid Arthritis page.
Myrrh vs Boswellia — Two Resins, Two Mechanisms
Myrrh and Boswellia (frankincense) are the two most clinically important aromatic tree resins in traditional medicine. They share many superficial features — both are oleo-gum-resins harvested by incising bark, both come from arid regions of Africa and Arabia, both have been used together for thousands of years, both produce anti-inflammatory effects through COX/LOX/NF-kappa-B inhibition — but they differ in important chemical and clinical respects.
Active compound classes: Frankincense's anti-inflammatory activity is driven primarily by boswellic acids, particularly acetyl-11-keto-beta-boswellic acid (AKBA), which is a potent and relatively selective 5-LOX inhibitor. Myrrh's anti-inflammatory activity is driven primarily by furanosesquiterpenes (curzerene, furanoeudesma-1,3-diene, lindestrene) and commiphoric acids, which inhibit both cyclooxygenase-2 and 5-LOX with more balanced activity. The boswellic acid mechanism is more "narrow and deep" (potent and specific 5-LOX inhibition); the myrrh mechanism is "broader and shallower" (moderate inhibition of multiple inflammatory pathways).
Bioavailability: Boswellic acids have notoriously poor oral bioavailability, which has driven the development of enhanced-absorption standardized boswellia extracts. Myrrh sesquiterpenes have somewhat better oral bioavailability due to their lipophilicity and lower molecular weight, but they are also subject to extensive first-pass hepatic metabolism. Both resins are more reliably bioavailable when delivered through mucosal routes (sublingual tincture, buccal application) or topical application to affected sites.
Analgesic activity: Myrrh has direct mu-opioid receptor agonist activity through its furanosesquiterpenes (Dolara 1996), producing meaningful direct analgesic effects independent of the anti-inflammatory mechanism. Boswellia does not have significant opioid receptor activity; its analgesic effects are entirely indirect, mediated by reduction of inflammatory pain. For pain-dominant inflammatory conditions, myrrh may produce more rapid subjective pain relief.
Clinical evidence base: Boswellia has a substantially larger modern clinical trial literature, particularly in osteoarthritis (multiple positive randomized controlled trials (RCTs) of standardized boswellia extracts), inflammatory bowel disease (smaller but supportive trials of boswellia for ulcerative colitis and Crohn's disease), and asthma (early-phase trials showing reduced bronchial hyperreactivity). Myrrh's modern clinical evidence base is concentrated in oral health (gingivitis trials), wound healing (limited human data), and antiparasitic use (a myrrh-based antiparasitic product). For chronic inflammatory disease specifically, the boswellia evidence is stronger.
Side effect profile: Both resins are generally well-tolerated. Boswellia's main side effects are mild gastrointestinal upset and rare hypersensitivity reactions. Myrrh's side effects are similar (gastrointestinal upset, contact dermatitis) but additionally include the traditionally described uterine-stimulant activity (pregnancy is listed as a contraindication) and a reported interaction with warfarin (a case report describes myrrh weakening warfarin's effect). These two points are the main safety differences drawn between the resins; apart from them, the two resins are described as roughly comparable in safety.
The practical implication for clinicians and patients: myrrh and boswellia are not interchangeable, and the choice between them (or the decision to combine them) depends on the specific clinical situation. For osteoarthritis without significant pain, boswellia alone is supported by stronger evidence. For osteoarthritis with prominent pain, combining myrrh + boswellia leverages myrrh's direct analgesic effect. For inflammatory bowel disease, boswellia has more direct evidence and a more favorable safety profile in the gastrointestinal (GI) tract. For oral mucosal inflammation, myrrh has the regulatory endorsement (German Commission E, European Medicines Agency, EMA) and stronger clinical evidence. For wound healing, both resins have historical use, with myrrh's evidence base modestly larger.
Combined Myrrh + Frankincense Synergy
The traditional combination of myrrh and frankincense was not merely ceremonial but reflected empirical observation of superior therapeutic outcomes. The combination appears in Egyptian medical papyri, in the Biblical record (the gifts of the Magi, the holy anointing oil of Exodus 30), in Ayurvedic and Unani classical texts, and in the Chinese pharmacopoeia (ru xiang + mo yao as a classic combination for blood-stasis pain). Modern laboratory studies have evaluated this traditional combination using checkerboard antimicrobial assays and fractional inhibitory concentration (FIC) index calculations.
The de Rapper 2012 study published in Letters in Applied Microbiology tested three frankincense essential oils (Boswellia rivae, Boswellia neglecta, Boswellia papyrifera) and two myrrh essential oils (Commiphora guidotti and Commiphora myrrha) from Ethiopia, alone and in combination, against a panel of microbes that included bacteria and the yeast Cryptococcus neoformans. Cryptococcus neoformans and Pseudomonas aeruginosa were often the most susceptible. In combination the oils showed synergistic, additive and non-interactive effects, with no antagonism; most interactions were synergistic or additive, with strong synergy between B. papyrifera and C. myrrha, which was also the most favourable pairing when different ratios were tested against Bacillus cereus. This was a laboratory (test-tube) study of the volatile essential oils; it did not test a mechanism for the synergy.
For anti-inflammatory applications, similar synergy is observed. Myrrh's cyclooxygenase-2 inhibition complements frankincense's 5-LOX inhibition to produce dual-pathway suppression of inflammatory lipid mediators more complete than either resin alone. Both resins suppress NF-kappa-B, but they do so through different upstream targets in the IKK/I-kappa-B pathway, producing more profound transcriptional suppression in combination than separately. The combined preparation also addresses both pain (through myrrh's mu-opioid activity) and inflammation (through both resins' enzyme inhibition) in a single formulation.
Practical formulations for combined use:
- Traditional Egyptian-style oral capsule — equal parts powdered myrrh and frankincense resin, 300-500 mg of combined resin two to three times daily
- Topical anti-inflammatory liniment — myrrh tincture and frankincense essential oil mixed in a carrier oil (jojoba or coconut), applied to affected joints twice daily
- Commercial combination products — many herbal joint-support supplements include both myrrh and boswellia, often combined with turmeric, ginger, and other anti-inflammatory herbs
Other Inflammatory Applications
Beyond the joint inflammatory conditions, myrrh has been applied traditionally and investigated experimentally for several other inflammatory states:
- Inflammatory bowel disease (Crohn's, ulcerative colitis) — the NF-kappa-B and cytokine-suppressing effects of myrrh are mechanistically relevant to inflammatory bowel disease (IBD) pathogenesis. Traditional use of myrrh for "chronic dysentery" likely overlapped with what would now be diagnosed as inflammatory bowel disease. In a 12-month double-blind, double-dummy trial of 96 people with ulcerative colitis in remission (Langhorst 2013), a preparation of myrrh, chamomile flower extract and coffee charcoal was compared with the standard drug mesalazine: 25 of 47 people (53%) relapsed on the herbal preparation and 22 of 49 (45%) on mesalazine, a difference that was not statistically significant (P = 0.540), and the disease activity scores did not differ significantly. The herbal preparation was well tolerated; the authors called this first evidence that needs further study. A 2024 systematic review of German medical guidelines (Utz 2024) states that this myrrh, chamomile and coffee charcoal combination can be used as a complementary treatment for keeping ulcerative colitis in remission.
- Asthma and chronic respiratory inflammation — 5-LOX inhibition reduces leukotriene-driven bronchoconstriction. Traditional steam inhalation of myrrh for "consumption" and respiratory complaints reflects this mechanism. Not a substitute for inhaled corticosteroids or bronchodilators in established asthma.
- Dysmenorrhea (menstrual cramping) — uterine smooth muscle contraction in dysmenorrhea is driven primarily by PGF2-alpha. Cyclooxygenase-2 inhibition reduces this prostaglandin and provides relief. However, myrrh's uterine-stimulant activity makes it a complex choice for menstrual symptoms — it may worsen rather than improve symptoms in some women, and its use in this context requires individualized assessment.
- Chronic sinusitis and rhinitis — traditional use of myrrh steam inhalation for chronic sinus inflammation. The volatile sesquiterpenes reach the nasal and sinus mucosa and produce local anti-inflammatory effects.
- Skin inflammatory conditions — eczema, psoriasis, contact dermatitis: topical application of diluted myrrh preparations has traditional use. Modern evidence is limited but supportive of mild-to-moderate efficacy in localized inflammatory skin lesions.
- Post-surgical inflammation — in dental and oral surgery, where myrrh has the strongest regulatory support, it can be used to reduce post-operative gingival inflammation and discomfort.
Dosing and Forms for Anti-Inflammatory Use
For chronic inflammatory conditions, internal use of myrrh is typically required to produce systemic anti-inflammatory effects. Topical use addresses local inflammation but does not meaningfully treat systemic disease.
Tincture (1:5 in 90% ethanol):
- 1-2 mL (20-40 drops) diluted in water, 2-3 times daily
- Taken with food to reduce gastrointestinal irritation
- Duration: 4-12 weeks for chronic inflammatory conditions, with periodic discontinuation if extended use is contemplated
Powdered resin in capsules:
- 300-600 mg two to three times daily with meals
- Standardized preparations give a more consistent content
- A standardized Egyptian myrrh-based antiparasitic product: 600 mg twice daily is the figure given for its parasitic use, sometimes carried over to other uses (no source for this figure was found, and it was not tested for inflammation)
Topical liniment for joint pain:
- Myrrh essential oil diluted to 5% in carrier oil (jojoba, coconut)
- Sometimes combined with frankincense essential oil at equal concentration
- Applied to affected joints twice daily with gentle massage
Combined myrrh + boswellia capsule (commercial):
- Many commercial products provide both resins in a single capsule, often with curcumin, ginger, and other complementary anti-inflammatory herbs
- Dosing is product-specific
Traditional practice limits continuous internal use to about 4-6 weeks and takes periodic breaks for long-term use (a week off every 4-6 weeks of use, or alternating with other anti-inflammatory herbs). The interactions with prescription medicines are listed under Cautions below: warfarin (a case report of a weakened effect), diabetes medicines, thyroid hormone, nonsteroidal anti-inflammatory drugs, opioids and other sedating drugs, and methotrexate (see the rheumatoid arthritis section).
Cautions
- Pregnancy — myrrh is traditionally regarded as a uterine stimulant and pregnancy is listed as a contraindication; there is no safety data for internal or topical use in pregnancy.
- Anticoagulant therapy — myrrh is said to inhibit platelets and add to the effect of warfarin, heparin, aspirin, clopidogrel, and direct oral anticoagulants, but no study of this was found. The one published report of myrrh with warfarin, a case report, describes the opposite: myrrh (Commiphora molmol) weakened warfarin's blood-thinning effect (Al Faraj 2005). For people on warfarin, the international normalized ratio (INR, the blood test used to track warfarin) can therefore shift in either direction when myrrh is started or stopped.
- Surgical procedures — practitioners describe stopping myrrh at least two weeks before scheduled surgery because of its reported effects on blood clotting.
- Diabetes medications — myrrh's hypoglycemic effect can potentiate insulin, metformin, sulfonylureas, and other diabetes drugs. In people with diabetes this can push blood glucose lower than usual, so diabetes-medicine doses set before myrrh was started can become too strong.
- Thyroid hormone interactions — some evidence suggests myrrh may suppress thyroid hormone production. This matters most for people with hypothyroidism on thyroid hormone replacement who use myrrh long-term.
- Concurrent nonsteroidal anti-inflammatory drug use — chronic high-dose nonsteroidal anti-inflammatory drugs carry a known risk of stomach ulcers (see the osteoarthritis section); whether myrrh adds to that risk has not been studied in people. Stomach-protecting drugs (a proton pump inhibitor or an H2 blocker) are commonly given alongside long-term nonsteroidal anti-inflammatory drug use.
- Concurrent opioid use — myrrh's weak mu-opioid activity is additive with prescribed opioid pain medications, which can deepen drowsiness in people on chronic opioid therapy.
- Hepatic and renal disease — significant chronic high-dose internal myrrh use may affect hepatic and renal function. This matters most for people with existing liver or kidney disease; there is no safety data for internal myrrh use in them.
- Gastrointestinal upset — nausea, diarrhea, and abdominal cramping can occur with internal use, particularly at higher doses or on an empty stomach. Traditional practice takes it with food and starts at a lower dose.
Key Research Papers
- Dolara P, Luceri C, Ghelardini C, Monserrat C, Aiolli S, Luceri F, Lodovici M, Menichetti S, Romanelli MN (1996). Analgesic effects of myrrh. Nature 379(6560):29. — PubMed PMID: 8538737
- Dolara P, Corte B, Ghelardini C, Pugliese AM, Cerbai E, Menichetti S, Lo Nostro A (2000). Local anaesthetic, antibacterial and antifungal properties of sesquiterpenes from myrrh. Planta Medica 66(4):356-8. — PubMed PMID: 10865454
- Germano A, Occhipinti A, Barbero F, Maffei ME (2017). A Pilot Study on Bioactive Constituents and Analgesic Effects of MyrLiq®, a Commiphora myrrha Extract with a High Furanodiene Content. BioMed Research International 2017:3804356. — PubMed PMID: 28626756
- Su S et al. (2011). Anti-inflammatory and analgesic activity of different extracts of Commiphora myrrha. Journal of Ethnopharmacology. — PubMed PMID: 21167270
- de Rapper S, Van Vuuren SF, Kamatou GP, Viljoen AM, Dagne E (2012). The additive and synergistic antimicrobial effects of select frankincense and myrrh oils — a combination from the pharaonic pharmacopoeia. Letters in Applied Microbiology 54(4):352-8. — PubMed PMID: 22288378
- Tipton DA et al. (2003). In vitro cytotoxic and anti-inflammatory effects of myrrh oil on human gingival fibroblasts and epithelial cells. Toxicology In Vitro. — PubMed PMID: 12781209
- Hanus LO et al. (2005). Myrrh — commiphora chemistry. Biomedical Papers. — PubMed PMID: 16170385
- Shen T et al. (2012). The genus Commiphora: traditional uses, phytochemistry and pharmacology. Journal of Ethnopharmacology. — PubMed PMID: 22626923
- Rahman MM et al. (2008). Antibacterial terpenes from the oleo-resin of Commiphora molmol. Phytotherapy Research. — PubMed PMID: 18570217
- Nomicos EY (2007). Myrrh: medical marvel or myth of the Magi? Holistic Nursing Practice 21(6):308-23. — PubMed PMID: 17978635
- Haffor AS (2010). Effect of myrrh on leukocyte levels before and during healing from gastric ulcer or skin injury. Journal of Immunotoxicology. — PubMed PMID: 19995243
- Ammon HPT (2006). Boswellic acids in chronic inflammatory diseases. Planta Medica. (Comparison reference for boswellia mechanism) — PubMed PMID: 17024588
- Al-Harbi MM et al. (1994). Anticarcinogenic effect of Commiphora molmol. Chemotherapy. — PubMed PMID: 7956458
- Tonkal AM, Morsy TA (2008). An update review on Commiphora molmol and related species. Journal of the Egyptian Society of Parasitology 38(3):763-96. — PubMed PMID: 19209761
- Al Faraj S (2005). Antagonism of the anticoagulant effect of warfarin caused by the use of Commiphora molmol as a herbal medication: a case report. Annals of Tropical Medicine and Parasitology 99(2):219-20. — PubMed PMID: 15814041
- Langhorst J, Varnhagen I, Schneider SB, Albrecht U, Rueffer A, Stange R, Michalsen A, Dobos GJ (2013). Randomised clinical trial: a herbal preparation of myrrh, chamomile and coffee charcoal compared with mesalazine in maintaining remission in ulcerative colitis — a double-blind, double-dummy study. Alimentary Pharmacology & Therapeutics 38(5):490-500. — PubMed PMID: 23826890
- Utz S, Bittel M, Langhorst J (2024). Phytotherapeutic recommendations in medical guidelines for the treatment of gastroenterological diseases — a systematic review [in German]. Zeitschrift für Gastroenterologie 62(7):1060-1073. — PubMed PMID: 38604221
- GBD 2021 Osteoarthritis Collaborators (2023). Global, regional, and national burden of osteoarthritis, 1990-2020 and projections to 2050: a systematic analysis for the Global Burden of Disease Study 2021. The Lancet Rheumatology 5(9):e508-e522. — PubMed PMID: 37675071
- García-Marcos L, Schuster A, Pérez-Yarza EG (2003). Benefit-risk assessment of antileukotrienes in the management of asthma. Drug Safety 26(7):483-518. — PubMed PMID: 12735786