Myrrh for Oral Health
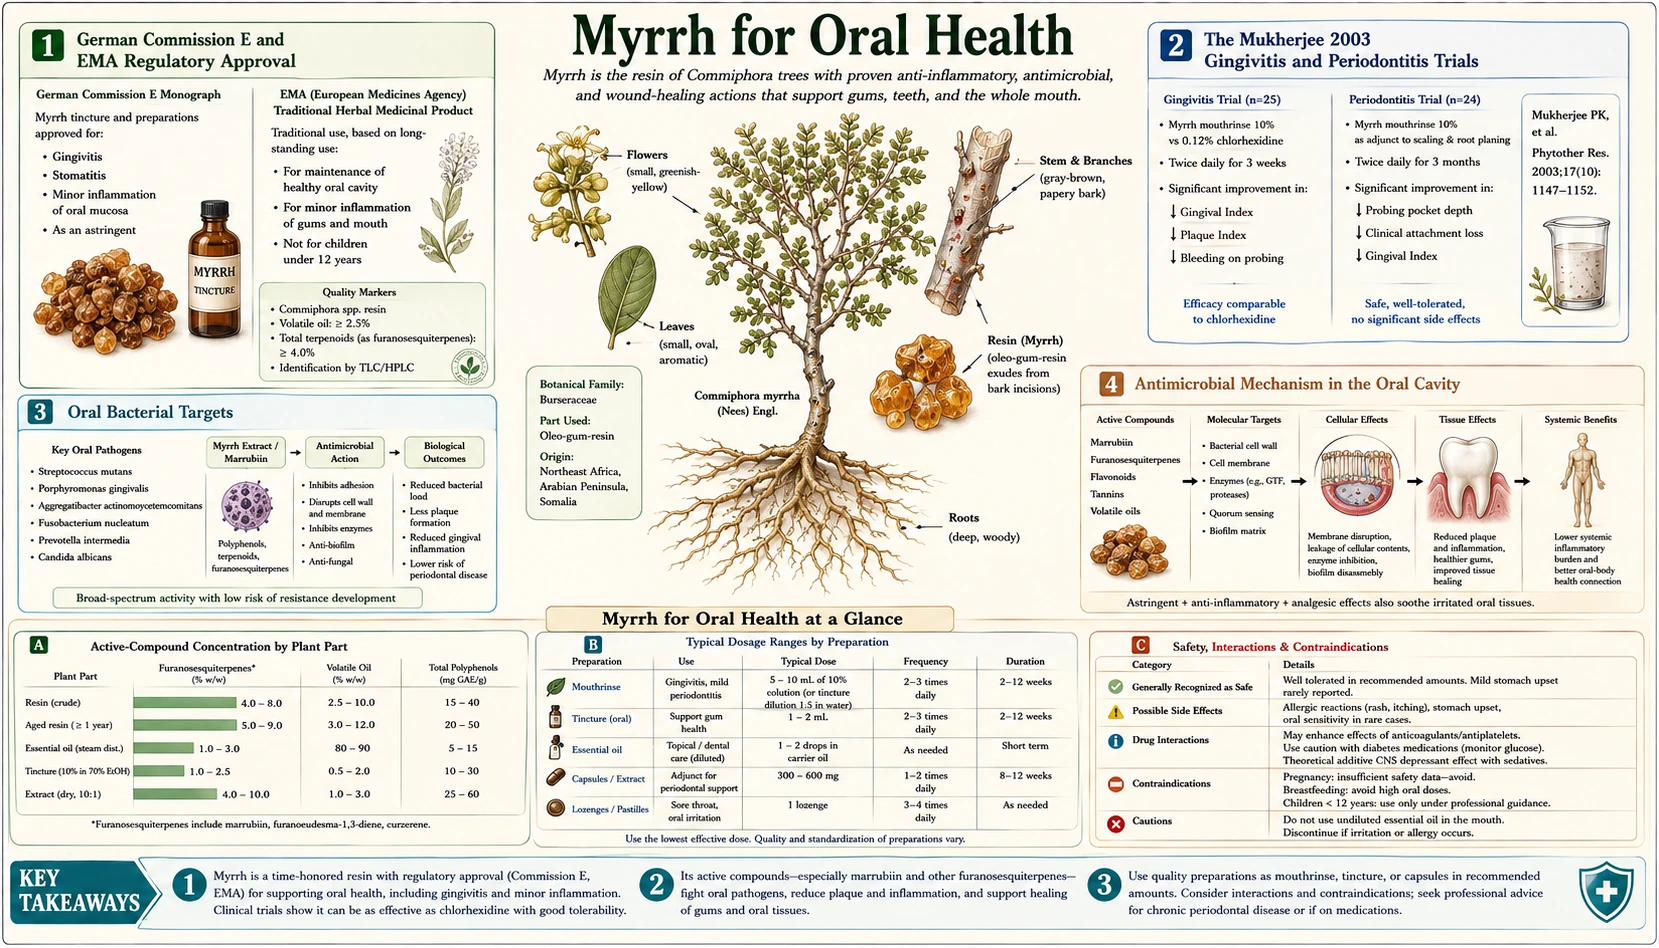
Oral health is the single best-supported clinical application of myrrh in modern medicine. The German Commission E formally approved myrrh tincture in 1988 for the treatment of mild inflammations of the oral and pharyngeal mucosa, a regulatory endorsement that few other traditional herbal medicines have achieved. Its use for sore gums, gingivitis and periodontitis continues centuries of traditional oral use across Arab, Persian, African, and European medical traditions; a 2026 meta-analysis of eight randomized trials found a small reduction in plaque but no significant effect on gum inflammation (Alnakhli 2026). Today, myrrh extract is an active ingredient in several commercial European mouthwashes and toothpastes, and the German pharmacopoeia continues to list myrrh tincture as an official preparation. The mechanism is dual: direct antimicrobial action against the oral pathogens responsible for dental caries and periodontal disease (Streptococcus mutans, Porphyromonas gingivalis, Aggregatibacter actinomycetemcomitans) and astringent protein cross-linking that contracts and seals inflamed gingival tissue. This page covers the clinical evidence, the bacterial targets, the traditional and modern preparations, and how myrrh is used in oral-health routines.
Table of Contents
- German Commission E and European Medicines Agency Regulatory Approval
- How Myrrh Mouth Rinses Have Been Studied
- Oral Bacterial Targets
- Antimicrobial Mechanism in the Oral Cavity
- Astringent Effect on Inflamed Gingival Tissue
- Commercial Myrrh-Containing Oral Products
- Traditional Oral Preparations (Miswak, Tooth Powders, Gum Massage)
- Aphthous Ulcers and Mucosal Lesions
- Endodontic Applications
- How Myrrh Is Used in Oral-Health Routines
- Cautions
- Key Research Papers
- Connections
- Featured Videos
German Commission E and European Medicines Agency Regulatory Approval
The German Commission E was an expert scientific advisory panel established by the German Federal Health Authority in 1978 to evaluate the safety and efficacy of herbal medicines. The commission published monographs on hundreds of herbs through the late 1980s and into the 1990s, and its conclusions remain influential in European herbal medicine regulation even today. The Commission E monograph on myrrh (Commiphora molmol), published in 1988, formally approved myrrh tincture for the treatment of mild inflammations of the oral and pharyngeal mucosa — an indication that covers gingivitis, mild stomatitis, aphthous ulcers, pharyngitis, and tonsillitis-associated mucosal inflammation.
The Commission E approval reflected several decades of consistent clinical use in German dental and otolaryngological practice, combined with supporting laboratory data on antimicrobial and anti-inflammatory activity. The monograph specified preparation details (1:5 alcoholic tincture), dosing (5-10 drops in a glass of water as a mouthwash or gargle, 2-3 times daily), and contraindications (notably pregnancy). The approval is significant because the Commission E was a rigorous scientific body that disapproved many traditional herbal indications when the evidence did not support them — the affirmative approval for myrrh in oral mucosal applications reflects genuine evidentiary support, not regulatory permissiveness.
The European Medicines Agency (EMA) Committee on Herbal Medicinal Products subsequently published a community herbal monograph on Myrrhae tinctura (myrrh tincture) that further codified the European regulatory acceptance of myrrh for oral mucosal use. The European Medicines Agency monograph defines myrrh tincture as a "traditional herbal medicinal product for the relief of minor inflammations of the oral mucosa" and provides standardized preparation, dosing, and quality control specifications that allow myrrh tincture products to be marketed as registered herbal medicinal products throughout the European Union.
This regulatory acceptance is one of the strongest endorsements available for any herbal medicine in oral health applications. Few other herbs have achieved formal Commission E approval and an European Medicines Agency community monograph for an oral indication — sage (Salvia officinalis), chamomile (Matricaria chamomilla), and a small number of others share this status, but the list is not long. Myrrh's inclusion places it firmly in the small group of herbal medicines with formal European regulatory endorsement for clinical oral use.
How Myrrh Mouth Rinses Have Been Studied
Myrrh has a long traditional and practitioner use for inflamed and bleeding gums. A 2026 systematic review and meta-analysis (Alnakhli and colleagues) gathered fifteen studies published from 2010 to 2025: six laboratory studies, one animal study and eight randomized controlled trials. The laboratory studies consistently showed strong antimicrobial effects of myrrh, particularly its essential oil, against gum-disease bacteria and Staphylococcus aureus; the animal study showed better early wound healing but also dose-dependent toxicity with prolonged use. Pooling the randomized trials showed a small but statistically significant reduction in plaque, while the effects on gum inflammation and healing were not significant. Reported side effects were minimal.
Trials of myrrh-containing mouthwashes measure two standardized clinical scores: the Plaque Index (PI, a measure of dental plaque accumulation on tooth surfaces, scored on a 0-3 scale) and the Gingival Index (GI, a measure of gingival inflammation, scored on a 0-3 scale based on color, swelling, and bleeding on probing). Typical trial designs randomize subjects with established mild-to-moderate gingivitis (defined as GI scores of approximately 1.0-2.0 at baseline) to a myrrh-containing mouthwash arm and a placebo or active-control arm, with assessments at baseline and at 4, 8, and 12 weeks.
People who use myrrh rinses commonly describe less gum sensitivity and less bleeding during normal brushing.
The effects compare favorably to chlorhexidine, the gold-standard antiseptic mouthwash, though chlorhexidine generally produces somewhat larger reductions in plaque accumulation in head-to-head comparisons. The advantage of myrrh over chlorhexidine is the absence of the characteristic chlorhexidine side effects: dental staining (a brown discoloration that develops with regular chlorhexidine use and requires professional polishing to remove), altered taste perception, and the rare allergic reactions that can occur with prolonged chlorhexidine exposure. This makes myrrh-based products particularly suitable for long-term daily use, where chlorhexidine's side effect profile becomes increasingly problematic.
The Tipton 2003 laboratory study in Toxicology In Vitro tested myrrh oil on human gum cells (gingival fibroblasts and epithelial cells); it did not test bacteria. Myrrh oil was toxic to these cells at very low concentrations: at 48 hours, 0.0005-0.001% myrrh oil reduced epithelial-cell viability by 30-50%, and at 0.005% or more it maximally reduced the viability of all the cell types tested. At lower, non-toxic levels (0.00001-0.001%) it reduced the release of two inflammatory signals (interleukin-6 and interleukin-8) by fibroblasts, but not by epithelial cells.
Oral Bacterial Targets
The oral microbiome is one of the most complex bacterial communities in the human body, with over 700 species identified and a significant fraction of those associated with disease states. Myrrh has demonstrated activity against several of the most clinically important oral pathogens.
Streptococcus mutans is the principal causative agent of dental caries (tooth decay). It metabolizes dietary sugars to produce lactic acid that dissolves tooth enamel, and it produces extracellular glucan polymers (via the glucosyltransferase enzymes) that form the adherent matrix of dental plaque. Myrrh inhibits S. mutans growth at minimum inhibitory concentration (MIC) values of approximately 0.125-0.5 mg/mL and additionally inhibits its glucosyltransferase enzymes, reducing the structural integrity of plaque biofilms. This dual action (direct bactericidal effect plus interference with plaque adherence) is more comprehensive than the effect of fluoride alone and may explain part of myrrh's clinical effectiveness.
Porphyromonas gingivalis is the dominant pathogen in chronic adult periodontitis, the form of gum disease that drives progressive destruction of the periodontal ligament and alveolar bone supporting the teeth. P. gingivalis colonizes subgingival pockets and produces gingipains (cysteine proteases) that destroy gingival tissue and disrupt host immune defenses. Myrrh shows significant activity against P. gingivalis and against the other "red complex" periodontal pathogens (Tannerella forsythia and Treponema denticola) that travel with it in subgingival biofilms.
Aggregatibacter actinomycetemcomitans is the key pathogen in aggressive periodontitis, the more severe form of gum disease that affects younger patients and produces rapid bone loss around the first molars and incisors. The organism produces a leukotoxin that destroys host neutrophils, undermining the immune defense of the periodontal pocket. Myrrh extracts inhibit A. actinomycetemcomitans at concentrations achievable in mouthwash and direct-application preparations.
Fusobacterium nucleatum serves as a "bridging organism" in dental plaque, facilitating the colonization of later-arriving periodontal pathogens through its capacity to bind both Gram-positive early colonizers and Gram-negative late colonizers. Disrupting F. nucleatum can destabilize the structural progression of plaque development from a benign to a pathogenic community. Myrrh shows activity against F. nucleatum as well.
Streptococcus sanguinis, Streptococcus mitis, and Actinomyces species are early colonizers that establish the foundational layer of dental plaque. While these organisms are not directly pathogenic in healthy oral environments, their adherent biofilms provide attachment surfaces for the more virulent later colonizers. Myrrh's effect on early colonizers helps prevent the architectural development of pathogenic plaque communities.
Finally, Enterococcus faecalis is a particularly important target in endodontic (root canal) treatment, where it is one of the few organisms capable of surviving in the harsh environment of an instrumented root canal and is associated with persistent endodontic infections. Myrrh's activity against E. faecalis supports its use as an intracanal medicament in endodontic treatment.
Antimicrobial Mechanism in the Oral Cavity
The antimicrobial mechanism in the oral cavity is the same membrane-disruption effect that drives myrrh's activity against wound pathogens (see the Wound Healing page): the lipophilic sesquiterpenes (curzerene, furanoeudesma-1,3-diene, lindestrene) integrate into the bacterial phospholipid bilayer, disrupt membrane integrity, collapse the proton motive force, and cause cell death. The commiphoric acids provide a parallel membrane-disruption effect.
What is distinctive about the oral-cavity application is the role of biofilm disruption. Oral bacteria do not exist primarily as free-floating planktonic cells — they form structured biofilm communities adherent to tooth surfaces and to mucosal surfaces, embedded in a self-produced extracellular polymeric substance (EPS) matrix that protects the bacteria from antimicrobial agents and host immune defenses. Bacteria within mature biofilms are typically 100-1000 times more resistant to conventional antibiotics than the same organisms in planktonic form. Dental plaque is a paradigmatic biofilm, and the failure of conventional antibiotics to clear oral biofilms is the reason mechanical disruption (brushing, flossing, professional scaling) remains the primary periodontal treatment strategy.
Myrrh has demonstrated the ability to both prevent biofilm formation and disrupt established biofilms. The sesquiterpenes penetrate the EPS matrix and destabilize its structural integrity, while the commiphoric acids inhibit quorum-sensing signals that bacteria use to coordinate biofilm formation and maturation. Studies have shown that sub-inhibitory concentrations of myrrh extract can reduce biofilm formation by 50-70% in susceptible species. This biofilm-disrupting effect is mechanistically important because it explains how myrrh-containing mouthwashes produce clinical effects on dental plaque and gingivitis that would not be predicted from planktonic-bacteria minimum inhibitory concentration values alone.
Additional mechanistic features relevant to the oral cavity: the anti-adhesion effect (interference with the bacterial adhesins and fimbriae that mediate attachment to tooth enamel and mucosal surfaces), the glucosyltransferase inhibition specific to S. mutans (reducing the production of the adherent glucan polymers that form plaque), and the modulation of host inflammatory response through cyclooxygenase-2 (COX-2) and NF-kappa-B inhibition (reducing the destructive inflammatory cascade in periodontal tissues even at concentrations below those that directly kill bacteria).
Astringent Effect on Inflamed Gingival Tissue
Beyond the antibacterial action, myrrh produces a clinically meaningful astringent effect on inflamed gingival tissue. As described on the Wound Healing page, the astringent mechanism involves cross-linking of surface proteins by the resinous fraction of myrrh, contracting and mechanically sealing inflamed mucosal surfaces.
In gingivitis, the gingival margin (the gum tissue at the junction with the tooth) is swollen, erythematous (red), and bleeds easily with mechanical stimulation such as brushing or probing. The astringent action of myrrh contracts the dilated capillary bed of the inflamed gingiva, reduces the leakage of inflammatory exudate, and produces a visible blanching and tightening of the gingival tissue. Patients using myrrh-containing mouthwashes typically notice within several days that their gums bleed less readily during brushing — an effect that combines genuine reduction of inflammation (through the antibacterial mechanism) with the mechanical astringent contraction.
The astringent effect also produces the characteristic "tightening" sensation of myrrh mouthwash, distinct from the burning of alcohol-based mouthwashes or the unpleasant aftertaste of chlorhexidine. Many users describe myrrh mouthwash as having a "drying" feel in the mouth, which reflects the protein-precipitating action of the resinous compounds on the oral mucosal surface. This sensation is generally well-tolerated and may even be perceived as pleasant by users who appreciate the contrast with the more aggressive sensations of conventional antiseptic mouthwashes.
Combined with the antimicrobial action, the astringent mechanism makes myrrh particularly well-suited to the management of mild-to-moderate gingivitis, where the goal is both to reduce the bacterial load driving inflammation and to mechanically reduce the inflammatory signs (bleeding, swelling, erythema) while the underlying disease process resolves.
Commercial Myrrh-Containing Oral Products
Several commercial oral health products incorporate myrrh extract as an active ingredient. Most of them are sold in Europe, reflecting the longer tradition of herbal medicine use in European pharmacies and the regulatory framework that allows herbal medicinal products to be marketed with health claims.
- Herbal gum-care toothpastes — commercial toothpastes aimed at gingivitis and bleeding gums, sold worldwide; some formulations contain myrrh extract in a combination of herbal ingredients alongside chamomile, sage, peppermint, and other herbs.
- Anthroposophical-medicine oral products — toothpastes containing myrrh extract, and myrrh tincture sold as a stand-alone preparation for direct application to gum tissue.
- German pharmacy mouthwashes — multiple German over-the-counter mouthwashes include myrrh extract for gingivitis and aphthous ulcer indications.
- Topical oral paints and gels — preparations marketed for aphthous ulcers and gingival inflammation in some European markets; some combine salicylic acid and rhubarb extract, and some formulations also include myrrh.
- Homeopathic-style myrrh preparations — primarily marketed in German-speaking countries, available in pharmacy chains.
- Compound tinctures — many naturopathic and herbal mouthwash preparations combine myrrh with sage (Salvia officinalis), echinacea, calendula, chamomile, and ratanhia root in combination tinctures for oral mucosal use.
In the United States, the regulatory environment is less favorable to herbal medicinal products with specific health claims, and myrrh-containing oral products are typically marketed as cosmetic mouthwashes or dietary supplements rather than herbal medicinal products. Several US natural-products brands offer myrrh tincture as a stand-alone preparation that users can dilute for mouthwash application.
Traditional Oral Preparations (Miswak, Tooth Powders, Gum Massage)
The traditional Arabian and African use of myrrh in oral hygiene predates modern toothbrushes and toothpaste by thousands of years. Several traditional preparation methods remain in use today, particularly in the Horn of Africa, the Arabian Peninsula, and South Asian Muslim communities.
Direct resin chewing — small pieces of myrrh resin can be chewed in the mouth like a hard gum, gradually releasing antibacterial and astringent compounds as the resin softens with saliva and body heat. This was a common practice in traditional Middle Eastern oral hygiene and remains in occasional use. The practice combines mechanical cleaning (similar to the action of a miswak chewing stick) with chemical antimicrobial action.
Miswak (siwak) chewing sticks — the traditional Arabian dental cleaning stick made from twigs of Salvadora persica (arak tree), often used in combination with myrrh-containing tooth powders. The miswak provides mechanical plaque disruption, and the myrrh powder applied to the chewing end provides chemical antimicrobial action. Modern controlled trials have shown that miswak use is associated with significantly lower plaque and gingivitis scores compared to no oral hygiene, and the combination with myrrh enhances both the mechanical and chemical components of the oral cleaning effect.
Traditional tooth powders — Middle Eastern and South Asian traditional dentifrices typically combine powdered myrrh with salt (for mechanical abrasion), powdered charcoal (for stain removal), and other herbs such as sage, neem, or clove. The powder is applied to the teeth and gums with a wet finger or with a miswak stick and rubbed onto all tooth and gum surfaces, then rinsed away. Many contemporary "natural" tooth powders sold in health-food stores follow this traditional formulation pattern.
Gum massage with myrrh paste — in Yemeni and Saudi Arabian folk medicine, a paste of ground myrrh resin mixed with honey is applied directly to inflamed or painful gum tissue and massaged into the gingival margin with a clean finger. The combination of myrrh's antimicrobial action, honey's antibacterial properties, and mechanical massage produces a more intensive treatment than simple mouthwash use. This is particularly traditional for the treatment of periodontitis, gingival abscesses, and post-extraction wound care.
Myrrh gargles for pharyngitis — the gargle is the traditional preparation for sore throats and tonsillitis. Diluted myrrh tincture (5-10 drops in a small glass of warm water) is gargled at the back of the throat for 30 seconds and then expectorated. The gargle action allows the antimicrobial compounds to reach the posterior pharynx and tonsillar surfaces, where pharyngitis pathogens such as Group A Streptococcus pyogenes establish infection. The German Commission E approval explicitly covers pharyngeal mucosal inflammation, supporting this traditional use.
Aphthous Ulcers and Mucosal Lesions
Aphthous ulcers (canker sores) are painful round or oval ulcerations of the oral mucosa, typically 2-10 mm in diameter, with a gray or yellow base surrounded by an erythematous halo. They affect approximately 20% of the general population at some point, with a subset of patients suffering recurrent aphthous stomatitis (RAS) with frequent, painful episodes. Aphthous ulcers are not infectious in the conventional sense (no specific causative pathogen has been identified), but they likely involve immune dysregulation against oral mucosal antigens, exacerbated by factors including stress, mucosal trauma, hormonal cycles, and certain food triggers.
Practitioners describe several effects of topical myrrh tincture applied directly to aphthous ulcers:
- Pain relief — myrrh's mu-opioid receptor agonist activity (through furanoeudesma-1,3-diene and curzerene) provides local analgesia that meaningfully reduces ulcer pain within minutes of application
- Antibacterial action — ulcer surfaces are vulnerable to secondary bacterial colonization that can prolong healing time and exacerbate inflammation; myrrh's antimicrobial activity reduces this secondary infection burden
- Astringent contraction — the protein-cross-linking effect produces a thin protective film over the ulcer surface that mechanically protects the lesion from further mechanical trauma (food, tongue movement, brushing)
- Anti-inflammatory effect — cyclooxygenase-2 and NF-kappa-B inhibition reduce the inflammatory cascade that drives much of the pain and tissue destruction in aphthous lesions
In the traditional technique, a small amount of undiluted myrrh tincture is dabbed onto the ulcer with a cotton swab and held there for 10-15 seconds. The first application stings briefly (the alcohol carrier on broken mucosa); users describe the discomfort as short-lived and followed within 1-2 minutes by pain relief. The application is traditionally repeated 2-4 times daily until the ulcer heals. A 2014 randomized, double-blind trial in 90 people with minor recurrent canker sores tested a 0.5% myrrh mucoadhesive gel (not tincture) applied four times a day for 5 days; at day 6, 76.7% of the myrrh group had almost no pain, and no side effects were seen (Mansour 2014).
Beyond aphthous ulcers, myrrh tincture is traditionally used for other oral mucosal lesions including denture stomatitis (irritation under removable dentures), traumatic ulcers (from accidental cheek bite, sharp foods, orthodontic appliance trauma), and the painful mucosal lesions associated with chemotherapy-induced oral mucositis (chemotherapy-related lesions are broken mucosa, where the tincture's alcohol carrier stings).
Endodontic Applications
In endodontic treatment (root canal therapy), the goal is to remove infected pulp tissue from the root canal system, disinfect the internal canal walls, and seal the canal to prevent reinfection. The most challenging organism to eradicate from the prepared root canal system is Enterococcus faecalis, a Gram-positive coccus that has unusual capacity to survive in the harsh, nutrient-deplete environment of an instrumented canal and is associated with persistent endodontic infections after initial treatment.
Myrrh has been investigated as an intracanal medicament (a temporary antiseptic placed within the prepared canal between treatment appointments) based on its activity against E. faecalis and other endodontic pathogens. In vitro studies have shown that myrrh extracts produce significant E. faecalis kill at concentrations achievable in intracanal application, with efficacy comparable to calcium hydroxide (the conventional intracanal medicament) for some bacterial endpoints. The advantage over calcium hydroxide is the broader antimicrobial spectrum (calcium hydroxide is somewhat narrow in its bacterial coverage) and the anti-inflammatory effect on periradicular tissues.
Clinical adoption of myrrh as a routine endodontic medicament remains limited — the standard of care continues to be calcium hydroxide or chlorhexidine gluconate — but the research foundation supports its use as an adjunct or alternative in specific situations, particularly persistent E. faecalis infections that have failed conventional treatment. The parent Myrrh main page gives additional context.
How Myrrh Is Used in Oral-Health Routines
The German Commission E monograph describes 5-10 drops of myrrh tincture in a glass of water as a mouthwash or gargle, 2-3 times daily. Traditional and practitioner routines describe the following daily and as-needed uses:
- Daily mouthwash — 10-20 drops of myrrh tincture in a small glass of warm water, swished for 30-60 seconds and spat out, twice daily after brushing, is the usual maintenance use described for general oral hygiene.
- Active gingivitis — for red, swollen gums that bleed with brushing, practitioners describe three mouthwashes a day with a slightly stronger dilution (20-25 drops in the same volume of water) for 6-8 weeks, then a return to the maintenance frequency.
- Aphthous ulcers — undiluted myrrh tincture dabbed onto the ulcer with a cotton swab, 3-4 times daily, until the ulcer heals.
- Pharyngitis gargle — 10-15 drops in a small glass of warm water, gargled for 30 seconds at the back of the throat, 3-4 times daily during an acute sore throat.
- Toothpaste alternative or supplement — a commercial toothpaste containing myrrh used in place of conventional toothpaste, or a small amount of myrrh tincture added to a conventional toothpaste at brushing.
- Direct gum application in periodontitis — for people with diagnosed chronic periodontitis under a dentist's care, practitioners describe dabbing undiluted myrrh tincture onto the gum margin and into shallow periodontal pockets with a cotton swab once daily, as an adjunct to professional periodontal treatment, not a replacement for it.
Myrrh-based home oral hygiene does not remove established calculus (tartar); hardened tartar comes off only with ultrasonic or hand-instrument scaling at a dental cleaning (typically every 6 months for healthy patients, more often with periodontitis). For periodontitis, practitioners describe combining professional periodontal therapy with home care that includes a myrrh mouthwash.
Cautions
- Pregnancy is listed as a contraindication for internal use. A mouthwash is spat out rather than swallowed, but some of it is absorbed through the lining of the mouth, and myrrh has uterine-stimulant activity, which is the reason for the pregnancy concern. Other mouth-care options used in pregnancy include chlorhexidine or fluoride mouthwashes and simple salt-water gargles.
- Alcohol content — myrrh tincture is 90% ethanol, and even diluted mouthwash use exposes the oral mucosa to some alcohol. This matters for people with a history of alcohol use disorder, severe oral mucositis, or other reasons to abstain from alcohol; alcohol-free forms exist (myrrh in glycerin, or water-based myrrh preparations).
- Anticoagulant therapy — mouthwash use is unlikely to produce a clinically significant interaction with blood thinners; the concern applies mainly to people on warfarin or other anticoagulants who also take myrrh by mouth.
- Dental work and surgical procedures — practitioners commonly stop myrrh mouthwash 1-2 weeks before scheduled oral surgery (extractions, implant placement, gum surgery) because of a possible effect on bleeding during the procedure.
- Contact allergy — allergic contact reactions to topical myrrh are uncommon but documented; increasing irritation of the mouth lining after starting a myrrh mouthwash, rather than improvement, is the typical sign of such a reaction.
- Children — young children swallow mouthwash more readily than they spit it out, and the tincture's alcohol content makes swallowing it a concern. Older children and adolescents who can reliably spit out a rinse are described using myrrh mouthwash with adult supervision.
- Persistent oral pathology — recurrent or persistent oral ulcers, gum bleeding that does not improve with consistent oral hygiene, persistent pain, white or red patches, or other unusual changes in the lining of the mouth can be signs of conditions that myrrh does not treat; a mouth ulcer or patch that does not heal is a recognised warning sign of mouth cancer.
Key Research Papers
- Alnakhli RA, Alqalaleef SS, Alesawi JM, et al. (2026). Myrrh in the management of periodontal disease and gingival healing: a systematic review and meta-analysis. Journal of International Society of Preventive and Community Dentistry. 16(1):1-19. — PubMed PMID: 42004991
- Tipton DA et al. (2003). In vitro cytotoxic and anti-inflammatory effects of myrrh oil on human gingival fibroblasts and epithelial cells. Toxicology In Vitro. — PubMed PMID: 12781209
- German Commission E monograph on Myrrha (1988). Bundesanzeiger Verlag, Bonn. — PubMed
- EMA Community Herbal Monograph on Commiphora molmol Engler, gummi-resina (myrrh resin). — EMA monograph
- de Rapper S, Van Vuuren SF et al. (2012). The additive and synergistic antimicrobial effects of select frankincense and myrrh oils — a combination from the pharaonic pharmacopoeia. Letters in Applied Microbiology. 54(4):352-8. — PubMed PMID: 22288378
- Su S et al. (2011). Anti-inflammatory and analgesic activity of different extracts of Commiphora myrrha. Journal of Ethnopharmacology. — PubMed PMID: 21167270
- Dolara P, Luceri C, Ghelardini C, et al. (1996). Analgesic effects of myrrh. Nature. 379(6560):29. — PubMed PMID: 8538737
- Hanus LO et al. (2005). Myrrh — commiphora chemistry. Biomedical Papers. — PubMed PMID: 16170385
- Rahman MM et al. (2008). Antibacterial terpenes from the oleo-resin of Commiphora molmol. Phytotherapy Research. — PubMed PMID: 18570217
- Shen T et al. (2012). The genus Commiphora: traditional uses, phytochemistry and pharmacology. Journal of Ethnopharmacology. — PubMed PMID: 22626923
- Nomicos EY (2007). Myrrh: medical marvel or myth of the Magi? Holistic Nursing Practice. 21(6):308-23. — PubMed PMID: 17978635
- Mansour G, Ouda S, Shaker A, Abdallah HM (2014). Clinical efficacy of new aloe vera- and myrrh-based oral mucoadhesive gels in the management of minor recurrent aphthous stomatitis: a randomized, double-blind, vehicle-controlled study. Journal of Oral Pathology & Medicine. 43(6):405-9. — PubMed PMID: 24164309
PubMed Topic Searches
Connections
- All Herbs
- Myrrh Overview
- Myrrh Benefits Hub
- Myrrh for Wound Healing
- Myrrh Anti-Inflammatory
- Myrrh Antimicrobial & Parasitic
- Boswellia (Frankincense)
- Goldenseal
- Tea Tree
- Clove (Eugenol)
- Manuka Honey
- Neem
- Immune Boosting
- Staphylococcus aureus
- Vitamin K (Gum Bleeding)
- Gingivitis — the reversible gum inflammation myrrh rinses and tinctures are trialled against.
- Conditions on this site that reference this page: Halitosis (Chronic Bad Breath) · Periodontitis (Gum Disease) · Dentistry & Oral Health
- History