⚠ Evidence warning: Clinical trials or other evidence do not support the claims that goldenseal or berberine improves low stomach acid, prevents traveler's diarrhea, treats C. difficile, heals leaky gut and helps Crohn's disease or microscopic colitis. This page keeps it as a report of what people, websites or other media say.
Goldenseal for Digestive & Gut Health
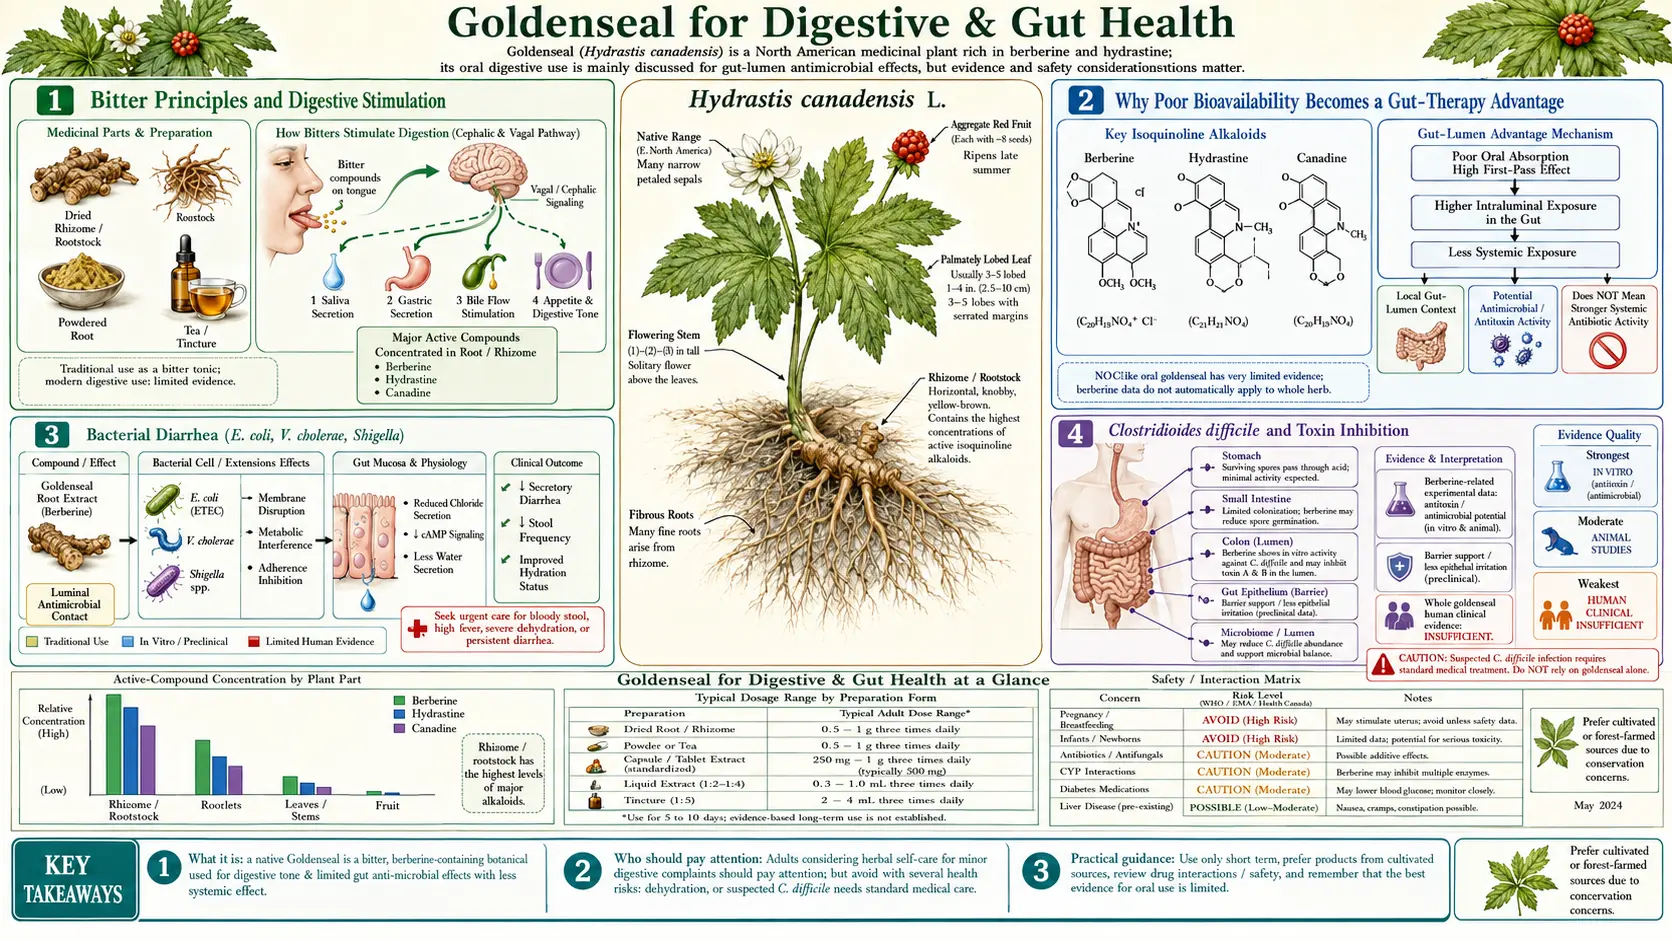
Goldenseal's digestive applications are one of its most discussed and most paradoxically practical uses. Berberine's notoriously poor systemic oral bioavailability (0.36% in a 2010 rat study) is described by practitioners as an advantage in the gut: in that study about half of an oral dose ran intact through the gastrointestinal tract, where it can contact intestinal bacteria, and the other half was disposed of by the small intestine. This is why goldenseal (and other berberine-rich plants) are proposed for in-gut antimicrobial action against bacterial diarrhea, C. difficile, H. pylori, and small intestinal bacterial overgrowth (SIBO). Layered on top of the antimicrobial action are three complementary digestive effects: bitter-principle vagal stimulation of saliva/gastric acid/bile, mucous-membrane astringency from hydrastine, and direct inhibition of bacterial enterotoxin-driven intestinal fluid secretion. This deep-dive walks through each digestive application, the clinical evidence (including the 2014 Johns Hopkins chart review of small intestinal bacterial overgrowth), the comparison to cheaper berberine sources, and the practical considerations for using goldenseal as part of a gut-restoration protocol.
Table of Contents
- Bitter Principles and Digestive Stimulation
- Why Poor Bioavailability Becomes a Gut-Therapy Advantage
- Bacterial Diarrhea (E. coli, V. cholerae, Shigella)
- Clostridioides difficile and Toxin Inhibition
- Small Intestinal Bacterial Overgrowth and the Johns Hopkins Chart Review
- Helicobacter pylori and Peptic Ulcer Adjunct
- Direct Inhibition of Enterotoxin-Driven Chloride Secretion
- Inflammatory Bowel Disease Adjunct Pilot Data
- Intestinal Barrier and Microbiome Effects
- Comparison to Barberry, Oregon Grape, and Pure Berberine HCl
- Doses Practitioners Describe for Gut Applications
- Cautions and Drug Interactions
- Berberine and Colorectal Polyps
- Key Research Papers
- Connections
- Featured Videos
Bitter Principles and Digestive Stimulation
Goldenseal is one of the most powerful bitter herbs in the Western pharmacopeia. The bitter taste is generated almost entirely by the isoquinoline alkaloids, and the digestive-stimulating effects of bitters are mediated by a coordinated cascade beginning in the mouth and extending through the entire upper gastrointestinal tract.
When bitter compounds contact the bitter taste receptors (T2Rs) on the tongue, they trigger a vagal nerve reflex that increases:
- Salivary secretion — preparing the mouth and pharynx for swallowing, beginning starch digestion via salivary amylase
- Gastric acid (HCl) secretion — mediated by parietal cells, lowering gastric pH for optimal pepsin activity and protein digestion
- Pepsinogen secretion — the precursor that gastric acid activates into the protein-cleaving enzyme pepsin
- Bile flow (cholagogue effect) — gallbladder contraction releasing bile into the duodenum for fat emulsification
- Pancreatic enzyme secretion — amylase, lipase, and protease release into the duodenum
- Intestinal motility — promoting forward peristalsis and reducing stagnation
The classical herbalist's description of goldenseal as a "bitter tonic" maps directly onto this cascade. For individuals with hypochlorhydria (low stomach acid), poor fat digestion (sluggish bile flow, bloating after fatty meals), or generally poor appetite, herbalists describe taking a small amount of bitter goldenseal tincture (10-20 drops in water) 15-30 minutes before meals and report better digestion. They describe the same effect across bitter herbs (gentian, dandelion root, artichoke leaf, wormwood), and the bitter-principle idea is widely used in integrative gastroenterology.
Herbalists also describe much cheaper and more sustainable bitter herbs for the same purpose. Goldenseal's use as a "digestive bitter" is not unique — gentian root or dandelion root tincture are used for the same vagal-reflex digestive stimulation without any conservation cost.
Why Poor Bioavailability Becomes a Gut-Therapy Advantage
In a 2010 rat study, berberine's absolute oral bioavailability was 0.36%, which the authors called extremely low; no absolute figure from people was read for this page. In pharmaceutical drug development, this would normally be considered a fatal flaw. Practitioners treat it as an advantage for gut applications.
Not all of the unabsorbed dose stays in the gut. In the same rats, about half of an oral dose ran intact through the gastrointestinal tract, where it can meet gut bacteria, and the other half was disposed of by the small intestine. No measurement of berberine concentrations inside the human intestine was found. Laboratory work reports minimum inhibitory concentrations (MICs), the lowest dose that stops bacterial growth, for individual gut organisms; those are quoted in the sections below.
This is why the uses most often proposed for berberine and goldenseal are in-gut antimicrobial effects:
- Bacterial diarrhea treatment (high luminal berberine kills enteric pathogens)
- small intestinal bacterial overgrowth (SIBO) eradication
- H. pylori adjunct therapy (luminal berberine reaches the gastric mucosa)
- C. difficile infection (luminal berberine reaches colonic C. difficile and inhibits toxin production)
- Traveler's diarrhea prophylaxis
The contrast with systemic antibiotic-style applications is striking. For a systemic infection (e.g. pneumonia, sepsis, methicillin-resistant Staphylococcus aureus (MRSA) bacteremia), oral berberine simply cannot reach therapeutic systemic concentrations — the in vitro MICs against methicillin-resistant Staphylococcus aureus are unreachable through oral dosing alone. Topical or intravenous administration would be required, neither of which is standard for berberine.
The upshot is that the uses proposed for goldenseal are concentrated in the gastrointestinal tract. This is also true for the sustainable berberine alternatives — Oregon grape root, barberry, Chinese goldthread, and purified berberine HCl all share the same poor systemic bioavailability.
Bacterial Diarrhea (E. coli, V. cholerae, Shigella)
The most extensively studied digestive application of berberine is the treatment of acute infectious diarrhea. The landmark clinical trial is Rabbani and colleagues' 1987 study published in the Journal of Infectious Diseases, in which 165 adults with diarrhea caused by enterotoxigenic E. coli (ETEC) or Vibrio cholerae were randomized to berberine sulphate (400 mg single dose) or placebo. Results:
- For ETEC diarrhea: mean stool volumes were significantly lower than in controls during three consecutive 8-hour periods, and at 24 hours 42% of treated patients had stopped having diarrhea against 20% of controls
- For cholera: stool volume in the second 8-hour period was 2.22 liters on 400 mg against 2.79 liters in controls. A 1200 mg dose plus tetracycline gave no significant reduction against tetracycline alone, and the authors called the activity against cholera “slight and not additive with tetracycline”
- Safety: no side effects of berberine were noted
A 2020 meta-analysis of 38 randomized trials with 3948 participants, 27 of them trials in children, found that berberine, alone or combined with other treatment, generally improved cure rates and shortened diarrhea compared with control groups, with no deaths or serious adverse events reported. It rated the evidence as moderate to low or very low, and 22 of the 27 trials in children gave berberine as an enema. Some integrative travel-medicine protocols describe prophylactic berberine for travelers to areas with high traveler's-diarrhea incidence; no human trial of that use was found.
The proposed mechanism is dual: direct bactericidal/bacteriostatic effect on the enteric pathogens, plus inhibition of the bacterial-enterotoxin-driven intestinal fluid secretion that produces the diarrhea (discussed in detail below).
For acute infectious diarrhea, practitioners usually favor purified berberine HCl over goldenseal, on cost and sustainability grounds. A regimen they describe is 500 mg of berberine HCl every 6 hours for the duration of acute symptoms (typically 2-5 days), tapering as symptoms resolve.
Clostridioides difficile and Toxin Inhibition
Clostridioides difficile (formerly Clostridium difficile) infection is one of the leading causes of hospital-acquired diarrhea and a major contributor to antibiotic-associated colitis. The clinical syndrome ranges from mild diarrhea to fulminant pseudomembranous colitis with toxic megacolon. The disease-causing agents are two large clostridial toxins: toxin A (enterotoxin) and toxin B (cytotoxin), which together produce the mucosal inflammation, epithelial necrosis, and fluid secretion that characterize the colitis.
Berberine's relevance to C. difficile infection extends beyond direct antibacterial activity (minimum inhibitory concentration (MIC) 16-64 micrograms per milliliter against clinical isolates). A 2025 laboratory study found that berberine and baicalein, at sub-inhibitory concentrations, damaged the bacterial cell and suppressed toxin production. No human study of this effect was found.
The clinical relevance is concentrated in two contexts:
- Recurrent C. difficile infection — approximately 20% of patients treated for primary C. difficile infection develop a recurrence within 8 weeks, and risk of further recurrence rises with each episode. In a 2015 mouse study, berberine with vancomycin prevented relapse and improved survival, and a 2025 study in a mouse model of recurrent infection reported less severe disease and better survival. No human study was found.
- Adjunct during active C. difficile treatment — some integrative practitioners add berberine to standard vancomycin protocols to provide additional toxin reduction during the period when host inflammation and mucosal damage are at peak severity.
For these uses, the evidence so far comes from the laboratory and from mice. The summaries of the 2017 update by the Infectious Diseases Society of America and the Society for Healthcare Epidemiology of America, and of the 2021 American College of Gastroenterology guideline, do not mention berberine — the use remains within the integrative-medicine adjunct category rather than standard-of-care. Practitioners describe berberine only as an add-on to the antibiotics used for this infection, not a replacement.
Small Intestinal Bacterial Overgrowth and the Johns Hopkins Chart Review
Small intestinal bacterial overgrowth (SIBO) is a condition in which excessive bacterial colonization of the small bowel produces bloating, abdominal pain, diarrhea or constipation, malabsorption, and a constellation of nutritional deficiencies. Small intestinal bacterial overgrowth is increasingly recognized as a common contributor to irritable bowel syndrome, unexplained chronic gastrointestinal (GI) symptoms, and post-infectious diarrhea.
The standard-of-care small intestinal bacterial overgrowth treatment is the non-absorbed antibiotic rifaximin (550 mg three times daily for 14 days), often combined with neomycin for methane-predominant subtypes. Rifaximin is highly effective but expensive (approximately $1500-2000 per 14-day course in the United States without insurance), often not covered by insurance for small intestinal bacterial overgrowth indication, and frequently requires repeated courses for small intestinal bacterial overgrowth that recurs.
The best-known study comparing herbal antimicrobial therapy to rifaximin for small intestinal bacterial overgrowth was published in 2014 by Chedid and colleagues at Johns Hopkins, in Global Advances in Health and Medicine. It was, in the authors’ words, “a retrospective chart review and not a prospective, randomized controlled trial”: patients positive on lactulose breath testing were offered either rifaximin 1200 mg daily or herbal therapy for 4 weeks, not assigned at random. Of 165 who were treated, 104 had a repeat breath test and were analysed (67 rifaximin, 37 herbal). Results:
- Rifaximin response rate: 23 of 67, 34% (negative follow-up breath test)
- Herbal antimicrobial response rate: 17 of 37, 46% (negative follow-up breath test). The difference was not statistically significant (P=.24)
- Herbal antimicrobial response in rifaximin non-responders: 8 of 14, 57% (those who had failed rifaximin first); triple antibiotics in the same group gave 6 of 10, 60%
- Safety: the rifaximin group had 1 anaphylaxis, 2 hives, 2 diarrhea and 1 C. difficile case; the herbal group had 1 diarrhea case (P=.22)
The herbal products were multi-herb commercial mixtures. Their berberine sources were Chinese goldthread (Coptis root), Indian barberry (Berberis aristata) and berberine sulfate, alongside other antimicrobials including oregano oil and red thyme oil. Goldenseal does not appear anywhere in the paper, and because the products were mixtures, the result cannot be credited to berberine alone.
The authors concluded that herbal therapies “are at least as effective as rifaximin” on the breath test and called for prospective studies to validate this. The Chedid paper has been cited extensively in integrative gastroenterology literature and is now part of naturopathic small intestinal bacterial overgrowth protocols. Herbal antimicrobial protocols for small intestinal bacterial overgrowth as practitioners describe them use berberine HCl at 500 mg three times daily as the core, often combined with oregano oil and other supporting antimicrobials, for 4-8 weeks.
For small intestinal bacterial overgrowth specifically, practitioners again favor the more sustainable berberine sources. Modern integrative gastroenterologists more typically use purified berberine HCl or Oregon grape extract on cost and sustainability grounds.
Helicobacter pylori and Peptic Ulcer Adjunct
Helicobacter pylori is the bacterium responsible for the majority of peptic ulcers and a recognized risk factor for gastric adenocarcinoma. The 2024 American College of Gastroenterology guideline makes bismuth quadruple therapy for 14 days the preferred first treatment when antibiotic susceptibility is unknown, says clarithromycin or levofloxacin salvage regimens “should only be used if antibiotic susceptibility is confirmed,” and addresses the need for a test after treatment to confirm cure in every patient. Older "triple therapy" (proton pump inhibitor + amoxicillin + clarithromycin) is what most berberine studies were added to; its eradication rates have declined to approximately 70-75% in many regions due to growing antibiotic resistance.
Berberine has been studied as an adjunct to standard H. pylori eradication regimens. A 2026 narrative review covers its laboratory effects on adhesion, motility, urease activity, efflux pumps and biofilm. The activities described include:
- Direct antibacterial activity against H. pylori at minimum inhibitory concentration 25-100 micrograms per milliliter
- Inhibition of H. pylori urease, the enzyme that H. pylori uses to neutralize gastric acid in its immediate microenvironment by generating ammonia from urea. Without urease, H. pylori cannot survive in the gastric lumen.
- Inhibition of H. pylori motility at sub-inhibitory concentrations, reducing the bacterium's ability to colonize new mucosal sites
- Effects on antibiotic sensitivity — in a laboratory study published in the World Journal of Gastroenterology, berberine lowered the minimum inhibitory concentrations of amoxicillin and tetracycline in some multidrug-resistant strains but “did not significantly change” those of clarithromycin
In people, a 2018 meta-analysis of randomized trials found that adding berberine to triple therapy improved eradication (risk ratio 1.18 on breath testing and 1.23 on biopsy) and lowered side effects overall, especially nausea and diarrhea; its authors called for better-designed trials. The evidence is suggestive rather than definitive, and the guideline summary does not mention berberine. Practitioners use it as an add-on in people with prior eradication failure or in regions with high antibiotic resistance.
Add-on dosing practitioners describe: berberine HCl 500 mg three times daily, combined with triple therapy for 14 days. Purified berberine HCl is used here rather than goldenseal on sustainability grounds.
Direct Inhibition of Enterotoxin-Driven Chloride Secretion
One of berberine's most elegant mechanisms in infectious diarrhea is a direct effect on the intestinal epithelium independent of its antibacterial activity. Many of the most clinically significant diarrhea-causing organisms — Vibrio cholerae, enterotoxigenic E. coli, certain Shigella species — produce enterotoxins that activate cAMP-dependent signaling in intestinal epithelial cells, opening apical chloride channels (CFTR) and producing massive secretion of Cl− (and water following osmotically) into the gut lumen. This is the molecular mechanism of cholera and ETEC diarrhea: the secretory volume can reach 1 liter per hour in severe cholera.
Berberine has been shown to reduce cAMP-activated chloride secretion in intestinal epithelial cells, but not by blocking the chloride channel itself. In human colon cells in Ussing chambers, it lowered that secretion in a dose-dependent way, with half the effect at about 80 micromolar; it “did not affect” the apical chloride conductance and instead stopped a basolateral potassium channel (KCNQ1) that keeps chloride secretion going. In perfused rat small intestine, berberine in the gut reversed cholera toxin-induced secretion within 60-80 minutes. Earlier reports extend this to ETEC heat-labile toxin. This effect is independent of berberine's antibacterial activity — it would reduce diarrheal fluid loss even in a treated infection where the bacteria have been killed but the secreted toxins continue to drive epithelial fluid loss.
The clinical implications:
- Berberine's effect on ETEC diarrhea is more rapid than would be expected from antibacterial action alone — stool volume fell within the first 8-hour periods rather than over the days bacteria take to die off
- The dual mechanism (direct antibacterial + chloride secretion inhibition) is the proposed reason berberine reduces stool volume; in the Rabbani trial the effect on cholera was slight
- The chloride secretion inhibition is proposed as an adjunct to oral rehydration therapy in low-resource settings where access to antibiotics is limited
Constipation is a real side effect of long-term berberine use in adults without diarrhea: it was the most common adverse event in a large polyp trial (1% against under 0.5% on placebo). The chloride-secretion effect is a proposed explanation, not a proven one, because in rat intestine berberine “did not significantly alter normal ileal water and electrolyte transport.”
Inflammatory Bowel Disease Adjunct Pilot Data
The application of berberine and goldenseal to Crohn's disease and ulcerative colitis is an area of active research. The theoretical case rests on mechanism: berberine has documented anti-inflammatory effects (NF-kB pathway inhibition, reduction of tumor necrosis factor-alpha and interleukin-6 (IL-6)), intestinal barrier-restorative effects (upregulation of tight junction proteins claudin and occludin), and potential immune-modulating effects (Th17/Treg balance modulation).
What is reported for berberine in inflammatory bowel disease (IBD):
- Ulcerative colitis in remission — practitioners report using berberine to help hold remission; no published randomized trial of this use was found.
- Crohn's disease — practitioners report similar use, particularly for postoperative recurrence prevention. Definitive randomized data are lacking.
- Microscopic colitis — reports of benefit, with the proposed mechanism being a combination of direct anti-inflammatory effect and barrier restoration
For inflammatory bowel disease specifically, practitioners describe berberine as an adjunct to (not a replacement for) standard immunosuppressive or biologic therapy. The cytochrome P450 drug interactions are particularly relevant in inflammatory bowel disease where patients may be on biologics, immunosuppressants, or anti-inflammatory drugs metabolized through the affected enzymes.
Intestinal Barrier and Microbiome Effects
Beyond direct antimicrobial and anti-inflammatory effects, berberine has documented effects on the intestinal barrier and on overall gut microbiota composition that may be relevant for conditions involving "leaky gut" / increased intestinal permeability.
Tight junction protein expression: Berberine increases the expression of intestinal tight junction proteins including claudin-1, claudin-5, occludin, and zonula occludens-1 (ZO-1). These proteins form the molecular seal between adjacent intestinal epithelial cells and are the primary determinant of intestinal barrier permeability. Berberine's tight-junction-restorative effect has been documented in animal models of inflammatory bowel disease, diet-induced obesity, and chronic alcohol exposure.
Microbiota modulation: Berberine produces relatively consistent and well-characterized shifts in gut microbiota composition. In multiple animal and human studies, berberine increases the relative abundance of Akkermansia muciniphila (associated with metabolic health and intestinal barrier integrity), Bacteroides species (generally beneficial), and reduces the abundance of Clostridium species and some Firmicutes. The net effect on overall microbial diversity is variable across studies, but the general direction is toward what is sometimes called a "leaner" microbiota profile.
Implications for "leaky gut" syndromes: Conditions that are increasingly characterized by increased intestinal permeability — including irritable bowel syndrome (IBS), autoimmune diseases, food sensitivities, and chronic fatigue syndrome — may benefit from berberine's combined barrier-restorative and microbiota-modulating effects. The clinical evidence in these conditions is preliminary but mechanistically plausible.
The practical caveat is that berberine's broad antimicrobial action will also kill commensal bacteria, not just pathogens. Extended berberine use (more than 3-4 weeks continuously) without microbiota-restorative support (a high-fiber diet, fermented foods, and possibly a brief course of probiotics) may produce dysbiosis. Practitioners use cycling protocols (2-4 weeks on, 1-2 weeks off) to try to lessen this risk.
Comparison to Barberry, Oregon Grape, and Pure Berberine HCl
For gut applications specifically, the case for using goldenseal over its more sustainable alternatives is exceptionally weak. Here is the side-by-side comparison:
- Goldenseal (Hydrastis canadensis): Berberine 2.5-6% + hydrastine + canadine. Conservation status: CITES Appendix II, United Plant Savers "At-Risk." Cost: $40-80 per ounce of root powder.
- Oregon grape root (Mahonia aquifolium): Berberine 2-3% + berbamine + oxyacanthine + other supporting alkaloids. Conservation status: abundant, not threatened. Cost: $10-20 per ounce of root powder.
- Barberry (Berberis vulgaris): Berberine 1.5-3% + berbamine + palmatine + jatrorrhizine. Conservation status: abundant; the European barberry is also widespread as an invasive species in parts of North America. Cost: $10-20 per ounce.
- Chinese goldthread (Coptis chinensis): Berberine 5-8% (the highest natural concentration) + palmatine + coptisine. Conservation status: cultivated extensively in China; the wild Chinese populations are themselves under pressure but commercial supply is from cultivation. Cost: variable.
- Purified berberine HCl (capsules): Berberine 99%+ purity, typically 500 mg per capsule. Conservation status: synthesized or extracted from cultivated Chinese goldthread / barberry. Cost: $0.10-0.30 per 500 mg dose, $10-30 per bottle of 60-120 capsules. The most economical and most precisely dosed option.
For nearly all gut applications — small intestinal bacterial overgrowth eradication, bacterial diarrhea, H. pylori adjunct, traveler's diarrhea prophylaxis, blood sugar management, inflammatory bowel disease adjunct — practitioners most often describe purified berberine HCl. It is the most reliably dosed, the cheapest per effective dose, and free of the sustainability concerns that attach to goldenseal.
The narrow case for using goldenseal whole-root over berberine HCl in gut applications would be a clinical context where the hydrastine-mediated mucous-membrane astringency adds meaningful value (severe mucousy diarrhea with significant epithelial inflammation, perhaps). For most clinical scenarios, this is a marginal advantage that does not justify the conservation cost.
Doses Practitioners Describe for Gut Applications
These regimens are what practitioners describe, not doses taken from a trial. The trial doses on this page were 400 mg once for ETEC diarrhea and 0.3 g twice daily in the polyp trial.
For purified berberine HCl (the form practitioners most often describe for gut uses):
- Small intestinal bacterial overgrowth: 500 mg three times daily with meals, for 4-8 weeks. Often combined with oregano oil (200 mg three times daily) and other supporting antimicrobials in herbal small intestinal bacterial overgrowth protocols.
- Acute bacterial diarrhea: 500 mg every 6 hours for the duration of acute symptoms (2-5 days), tapering as resolution occurs.
- Traveler's diarrhea prophylaxis: 500 mg twice daily, starting 1-2 days before travel through 1-2 days after return.
- H. pylori adjunct: 500 mg three times daily, combined with triple therapy for 14 days.
- C. difficile adjunct: 500 mg three times daily, alongside standard vancomycin or fidaxomicin therapy, with some practitioners continuing 2-4 weeks after it in the hope of reducing recurrence.
- Inflammatory bowel disease adjunct: 300-500 mg three times daily, ongoing, alongside standard immunomodulating therapy (with the cautions about drug interactions noted below).
- Blood sugar / metabolic indications: 500 mg two to three times daily with meals.
For goldenseal (when chosen for a specific clinical reason that warrants the alkaloid profile):
- Tincture (1:5, 60% ethanol): 2-4 mL three times daily before meals. For digestive bitter effect, 10-20 drops in water 15-30 minutes before meals.
- Standardized extract (5% berberine): 250-500 mg three times daily with meals.
- Root powder: 500-1000 mg three times daily.
- Duration: 7-21 days for acute use, with practitioner supervision for anything longer.
- Cycling: 2-3 weeks on, 1-2 weeks off, for any extended use, to preserve microbiota diversity and prevent mucous membrane over-drying.
Practitioners describe taking berberine-containing supplements with food to slow absorption and maximize gut exposure. They also say food items that significantly raise gastric pH can reduce berberine ionization and alter both its gut and whole-body handling.
Cautions and Drug Interactions
- Pregnancy and breastfeeding — strictly contraindicated. Berberine stimulates uterine contractions, crosses the placenta, and displaces bilirubin from albumin (kernicterus risk in the neonate).
- CYP450 drug interactions — berberine is a potent inhibitor of CYP3A4, CYP2D6, and CYP2C9. Major interactions with: warfarin, statins, calcium channel blockers, cyclosporine, tacrolimus, selective serotonin reuptake inhibitors (SSRIs)/serotonin-norepinephrine reuptake inhibitors (SNRIs), several antiretrovirals, and many other drugs.
- Metformin — in adults with type 2 diabetes on metformin, goldenseal lowered metformin exposure by about 20% at low metformin doses, 14% at moderate doses and 0% at high doses. Overall the interaction was not clinically meaningful, and HbA1c fell on average from 6.8% to 6.5%.
- Liver tumors in rodents — in 2-year US National Toxicology Program studies, goldenseal root powder increased liver tumors in rats and mice. Researchers suspect berberine's effect on topoisomerase, an enzyme that manages DNA, and said further studies are needed to apply this to people.
- P-glycoprotein inhibition — berberine inhibits the P-gp drug efflux transporter, increasing absorption of P-gp substrates including digoxin, several chemotherapeutic agents, and some immunosuppressants.
- Hypoglycemia — berberine significantly lowers blood glucose. Patients on insulin, sulfonylureas, or other hypoglycemic medications may experience additive hypoglycemia (low blood sugar) when berberine is added to a diabetic regimen.
- Gut microbiota disruption with long-term use — berberine kills commensals as well as pathogens. Practitioners use cycling protocols (2-4 weeks on, 1-2 weeks off) with probiotic and prebiotic support to try to lessen dysbiosis risk.
- Constipation — the most common side effect in the polyp trial below (1%). The chloride secretion inhibition that benefits diarrheal disease is the proposed reason.
- Neonates and young infants — berberine displaces bilirubin from albumin, so the kernicterus risk (brain damage from bilirubin) noted above applies directly to newborns.
- Sustainability ethics — see the Sustainability deep dive. For gut applications, practitioners concerned with conservation use purified berberine HCl or Oregon grape instead of goldenseal.
Berberine and Colorectal Polyps
The largest gut trial of berberine concerns polyps rather than infection, and it used purified berberine, not goldenseal. In a double-blind trial in Chinese adults whose precancerous bowel polyps (colorectal adenomas) had been removed, 553 were assigned to berberine 0.3 g twice daily and 555 to placebo, and 429 and 462 were analysed. Adenomas came back in 36% on berberine against 47% on placebo. Constipation was the most common side effect (1% against under 0.5%), and no serious adverse events were reported.
A follow-up study traced patients for up to 6 years after treatment stopped; 648 had a colonoscopy in that time. Adenomas came back in 34.7% of the berberine group against 52.1% of the placebo group. This follow-up was a retrospective cohort study, a weaker design than the original trial.
Key Research Papers
- Rabbani GH, Butler T, Knight J, Sanyal SC, Alam K (1987). Randomized controlled trial of berberine sulfate therapy for diarrhea due to enterotoxigenic Escherichia coli and Vibrio cholerae. Journal of Infectious Diseases 155(5):979-84. — PubMed PMID: 3549923
- Chedid V, Dhalla S, Clarke JO, Roland BC, Dunbar KB, Koh J, Justino E, Tomakin E, Mullin GE (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine 3(3):16-24. — PubMed PMID: 24891990
- Yang X, Zheng D, Yong J, Li Y, Sun Y, Zhao F, Tang D, Xie Y, Bi D (2025). Baicalein and Berberine Inhibit the Growth and Virulence of Clostridioides difficile. Pathogens 14(7):662. — PubMed PMID: 40732709
- Lv Z, Peng G, Liu W, Xu H, Su J (2015). Berberine blocks the relapse of Clostridium difficile infection in C57BL/6 mice after standard vancomycin treatment. Antimicrobial Agents and Chemotherapy 59(7):3726-35. — PubMed PMID: 25824219
- Wang L, Xu T, Wu S, Zhao C, Huang H (2025). The efficacy and underlying mechanisms of berberine in the treatment of recurrent Clostridioides difficile infection. International Journal of Antimicrobial Agents 65(5):107468. — PubMed PMID: 39986400
- McDonald LC, Gerding DN, Johnson S, Bakken JS, Carroll KC, Coffin SE, et al. (2018). Clinical Practice Guidelines for Clostridium difficile Infection in Adults and Children: 2017 Update by the Infectious Diseases Society of America (IDSA) and Society for Healthcare Epidemiology of America (SHEA). Clinical Infectious Diseases 66(7):987-994. — PubMed PMID: 29562266
- Kelly CR, Fischer M, Allegretti JR, LaPlante K, Stewart DB, Limketkai BN, Stollman NH (2021). ACG Clinical Guidelines: Prevention, Diagnosis, and Treatment of Clostridioides difficile Infections. American Journal of Gastroenterology 116(6):1124-1147. — PubMed PMID: 34003176
- Huang YQ, Huang GR, Wu MH, Tang HY, Huang ZS, Zhou XH, et al. (2015). Inhibitory effects of emodin, baicalin, schizandrin and berberine on hefA gene: treatment of Helicobacter pylori-induced multidrug resistance. World Journal of Gastroenterology 21(14):4225-31. — PubMed PMID: 25892872
- Viscardi S, Duda-Madej A, Krzyżek P (2026). Berberine and Berberine-Derived Compounds as Promising Weapons Against Helicobacter pylori: A Narrative Review. Pharmaceuticals 19(8):1279. — PubMed PMID: 42653775
- Jiang X, Jiang C, Huang C, Chen G, Jiang K, Huang B, Liu F (2018). Berberine Combined with Triple Therapy versus Triple Therapy for Helicobacter pylori Eradication: A Meta-Analysis of Randomized Controlled Trials. Evidence-Based Complementary and Alternative Medicine 2018:8716910. — PubMed PMID: 30410559
- Chey WD, Howden CW, Moss SF, Morgan DR, Greer KB, Grover S, Shah SC (2024). ACG Clinical Guideline: Treatment of Helicobacter pylori Infection. American Journal of Gastroenterology 119(9):1730-1753. — PubMed PMID: 39626064
- Swabb EA, Tai YH, Jordan L (1981). Reversal of cholera toxin-induced secretion in rat ileum by luminal berberine. American Journal of Physiology 241(3):G248-52. — PubMed PMID: 7282933
- Alzamora R, O'Mahony F, Ko WH, Yip TW, Carter D, Irnaten M, Harvey BJ (2011). Berberine Reduces cAMP-Induced Chloride Secretion in T84 Human Colonic Carcinoma Cells through Inhibition of Basolateral KCNQ1 Channels. Frontiers in Physiology 2:33. — PubMed PMID: 21747769
- Liu YT, Hao HP, Xie HG, Lai L, Wang Q, Liu CX, Wang GJ (2010). Extensive intestinal first-pass elimination and predominant hepatic distribution of berberine explain its low plasma levels in rats. Drug Metabolism and Disposition 38(10):1779-84. — PubMed PMID: 20634337
- Yu M, Jin X, Liang C, Bu F, Pan D, He Q, et al. (2020). Berberine for diarrhea in children and adults: a systematic review and meta-analysis. Therapeutic Advances in Gastroenterology 13:1756284820961299. — PubMed PMID: 33149763
- Xu J, Lao Y, Zhang W, Chen L, Zhang H, Liu H, et al. (2025). Berberine alleviates metabolic dysfunction-associated steatohepatitis by enhancing the abundance of Akkermansia muciniphila. Journal of Nutritional Biochemistry 146:110069. A mouse study. — PubMed PMID: 40816629
- Habtemariam S (2020). Berberine pharmacology and the gut microbiota: A hidden therapeutic link. Pharmacological Research 155:104722. — PubMed PMID: 32105754
- Chen YX, Gao QY, Zou TH, Wang BM, Liu SD, Sheng JQ, et al. (2020). Berberine versus placebo for the prevention of recurrence of colorectal adenoma: a multicentre, double-blinded, randomised controlled study. Lancet Gastroenterology & Hepatology 5(3):267-275. — PubMed PMID: 31926918
- Tan YJ, Zou TH, Yu K, Sheng JQ, Jin P, Zhang MJ, et al. (2025). Berberine for preventing colorectal adenoma recurrence and neoplasm occurrence: 6-Year follow-up of a randomized clinical trial. Cell Reports Medicine 6(9):102293. — PubMed PMID: 40795846
- Dunnick JK, Singh B, Nyska A, Peckham J, Kissling GE, Sanders JM (2011). Investigating the potential for toxicity from long-term use of the herbal products, goldenseal and milk thistle. Toxicologic Pathology 39(2):398-409. — PubMed PMID: 21300790
- Chen S, Wan L, Couch L, Lin H, Li Y, Dobrovolsky VN, Mei N, Guo L (2013). Mechanism study of goldenseal-associated DNA damage. Toxicology Letters 221(1):64-72. — PubMed PMID: 23747414
- Nguyen JT, Arian CM, Tanna RS, Cherel MG, Layton ME, White JR, Thummel KE, Paine MF (2025). The Pharmacokinetic Interaction Between Metformin and the Natural Product Goldenseal Is Metformin Dose-Dependent: A Three-Arm Crossover Study in Adults With Type 2 Diabetes. Clinical and Translational Science 18(2):e70120. — PubMed PMID: 39943692
PubMed Topic Searches
- PubMed: Berberine + SIBO
- PubMed: Berberine + infectious diarrhea
- PubMed: Berberine + H. pylori
- PubMed: Berberine + IBD
- PubMed: Berberine + gut microbiota
- PubMed: Berberine and heat-labile enterotoxin (LT) signaling
- PubMed: Berberine and intestinal tight junction protein expression
- PubMed: Bitter principles, T2R bitter receptors, and gastric/biliary secretion
- PubMed: Berberine vs metformin for type 2 diabetes (meta-analysis)
Connections
- All Herbs
- Goldenseal Overview
- Goldenseal Benefits Hub
- Goldenseal Antimicrobial Action
- Goldenseal for Eye Health
- Sustainability & Cautions
- Berberine (Pure Supplement)
- Barberry (Sustainable Alternative)
- Berberine Remedy
- Small Intestinal Bacterial Overgrowth
- Herbal Antimicrobials for Small Intestinal Bacterial Overgrowth
- Irritable Bowel Syndrome
- Crohn's Disease
- Clostridium Difficile
- Escherichia Coli
- Helicobacter Pylori
- Gut Healing
- Oregano
- Garlic
- Immune Boosting
- History