⚠ Evidence warning: Clinical trials or other evidence do not support the claim that berberine eye drops cure acute bacterial conjunctivitis as well as chloramphenicol drops; no such trial was found, and the indexed berberine eye-drop trials are in trachoma. This page keeps it as a report of what people, websites or other media say.
Goldenseal for Eye Health
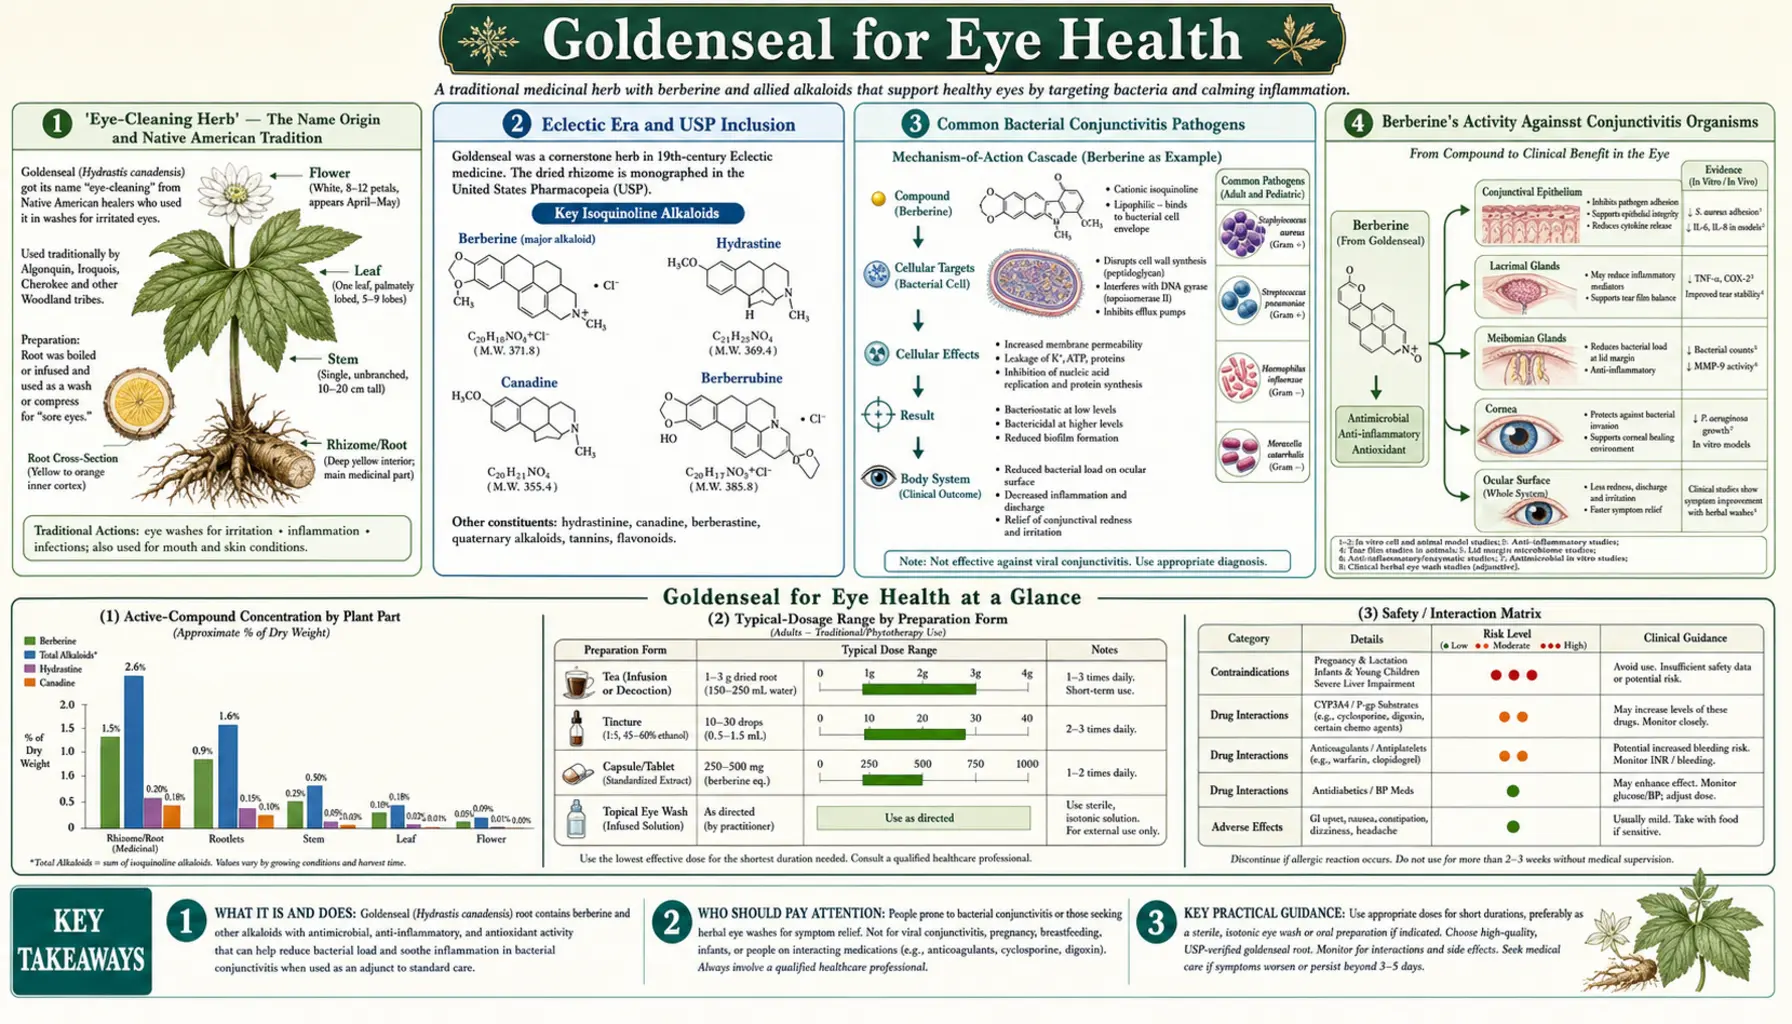
Goldenseal's use as a conjunctivitis eyewash — the application that gave the plant its older common names "eye balm," "eye root," and "eye-cleaning herb" — is one of the oldest documented Native American medicinal uses of Hydrastis canadensis. Cherokee and Iroquois healers prepared goldenseal root decoctions as a wash for conjunctivitis, blepharitis, sore eyes, and inflamed eyelids; the practice was adopted by 19th-century Eclectic physicians and goldenseal eyewashes remained in the United States Pharmacopeia until the mid-20th century. Modern pharmacology has confirmed berberine's broad-spectrum activity against common conjunctivitis pathogens (Staphylococcus aureus, Streptococcus pneumoniae, Haemophilus influenzae, Pseudomonas aeruginosa) and Indian clinical trials of the 1980s and 1990s tested berberine eye drops in trachoma. It is also claimed that berberine drops cure acute bacterial conjunctivitis as well as chloramphenicol drops; no trial testing this was found in PubMed. Critical safety caveats apply: home-prepared goldenseal eyewashes carry a genuine contamination risk that can produce endophthalmitis (catastrophic intraocular infection), infant eyes are a special risk (berberine pushes bilirubin off its carrier protein, raising the risk of kernicterus, bilirubin brain damage, in newborns), and modern pharmaceutical antibiotic drops are now the standard of care for acute infectious conjunctivitis. This deep-dive walks through the history, the science, and the safety facts that apply to goldenseal in ophthalmic applications.
Table of Contents
- "Eye-Cleaning Herb" — The Name Origin and Native American Tradition
- Eclectic Era and USP Inclusion
- Common Bacterial Conjunctivitis Pathogens
- Berberine's Activity Against Conjunctivitis Organisms
- The Berberine vs Chloramphenicol Claim
- Trachoma and Ocular Chlamydia trachomatis
- Blepharitis, Sty, and Eyelid Margin Infections
- Anti-Inflammatory Effects in Conjunctival Tissue
- Critical Safety Caveats — Why "Home Eyewash" Is Risky
- Why Infant Eyes Are a Special Risk
- Where Antibiotic Drops Are the Standard of Care
- What Reduces Contamination Risk in an Eyewash
- Key Research Papers
- Connections
- Featured Videos
"Eye-Cleaning Herb" — The Name Origin and Native American Tradition
Among the dozen or so common names attached to Hydrastis canadensis in 18th and 19th-century North American ethnobotanical literature, several — "eye balm," "eye root," and "eye-cleaning herb" — refer specifically to the plant's most prominent traditional use. Long before European contact, the Cherokee, Iroquois, Mohawk, Onondaga, and several other woodland tribes used goldenseal root preparations as a wash for inflamed, infected, and otherwise sore eyes.
The traditional preparation was a decoction: small pieces of dried or fresh goldenseal rhizome simmered in clean water for 15-20 minutes, strained, cooled to body temperature, and applied to the affected eye(s) with a clean cloth or used directly as a wash. The bright yellow color of the decoction is from the berberine, which at the concentrations used was visibly tinting the wash water.
The indications for which goldenseal eyewashes were used spanned what modern ophthalmology would classify as:
- Bacterial conjunctivitis — "pink eye," with redness, mucopurulent discharge, eyelid sticking
- Blepharitis — inflammation of the eyelid margins, often associated with Staphylococcus overgrowth
- Hordeolum (stye) — acute infection of an eyelash follicle or eyelid gland
- Sore or irritated eyes from smoke, dust, wind exposure, prolonged crying, or general overuse
- Snowblindness — ultraviolet-induced corneal damage from snow glare, encountered by hunters and travelers
- Probable trachoma cases — chronic ocular Chlamydia trachomatis infection, historically a major cause of blindness in many populations
European settlers documented the practice extensively in the late 18th and early 19th centuries. Goldenseal eyewashes appear in early American household medical manuals and in the materia medica writings of figures including Constantine Rafinesque (Medical Flora of the United States, 1828) and John King (King's American Dispensatory, 1854).
Eclectic Era and USP Inclusion
The Eclectic physicians — a school of American botanical medicine centered at the Eclectic Medical Institute in Cincinnati from approximately 1830 to 1939 — elevated goldenseal to one of their most frequently prescribed remedies. The Eclectic monographs on goldenseal, particularly Felter and Lloyd's comprehensive entry in the 1898 King's American Dispensatory, describe in detail the ophthalmic uses:
- "In aural and ophthalmological practice this drug is a favorite local application." Hydrastis "is valuable in all conjunctival inflammations, particularly so in the catarrhal forms."
- For the colorless hydrastis preparation of the time, the Dispensatory gives "about 1 part in 10 or 20 of pure water in conjunctival diseases"; for berberine sulphate, four grains dissolved in 1 fluid ounce of hot water formed, when cold, an eyewash (collyrium) for purulent and phlyctenular conjunctivitis. The authors note that the yellow root infusions and berberine salts stained, which is why the colorless preparation had largely replaced them.
- For chronic conjunctivitis (likely including trachoma cases), longer courses of dilute application were standard.
- Combined with other Eclectic ophthalmic herbs — particularly eyebright (Euphrasia officinalis) and bayberry root bark — in compound formulations.
The United States Pharmacopeia (USP), the official drug compendium of American medicine, listed Hydrastis canadensis as an official drug from 1830 through 1955 (with brief intermittent gaps). Although the USP listing did not officially endorse the ophthalmic use, the inclusion of goldenseal as a recognized medicinal plant meant that physicians and pharmacists across the country had access to standardized preparations that they routinely used for the indications — including the eye washes — passed down from Eclectic-era clinical practice.
The decline of goldenseal in the official pharmacopeia paralleled the decline of botanical medicine more broadly in the early to mid 20th century, driven by the rise of antibiotics (which made bacterial conjunctivitis dramatically easier to treat with topical antibiotic drops), the standardization-oriented medical reform of the Flexner era, and the increasing pressure on wild goldenseal populations from overharvesting.
Common Bacterial Conjunctivitis Pathogens
Bacterial conjunctivitis is the most common cause of acute "pink eye" in adults and the second most common (after viral) in children. The pathogen distribution varies by age group and clinical setting, but the dominant bacterial organisms are remarkably consistent:
- Staphylococcus aureus — the leading cause of bacterial conjunctivitis in adults, often associated with concomitant blepharitis. Causes a mucopurulent discharge with eyelid crusting. Increasingly includes methicillin-resistant strains (methicillin-resistant Staphylococcus aureus, MRSA).
- Streptococcus pneumoniae — a leading cause in children, often associated with concurrent upper respiratory tract infection. Can produce severe conjunctival inflammation.
- Haemophilus influenzae (non-typeable) — very common in children, particularly in the context of otitis media or upper respiratory infection. Often produces conjunctivitis-otitis syndrome.
- Moraxella catarrhalis — less common but a recognized pathogen, particularly in older adults with chronic conditions.
- Pseudomonas aeruginosa — uncommon in healthy individuals but a significant pathogen in contact lens wearers and immunocompromised patients. Can rapidly produce corneal ulceration and threaten vision.
- Chlamydia trachomatis — the cause of chronic conjunctivitis ("inclusion conjunctivitis") in sexually active adults and of trachoma (chronic follicular conjunctivitis leading to blindness) in low-resource settings.
- Neisseria gonorrhoeae — a rare but emergency-level pathogen producing hyperacute conjunctivitis with copious purulent discharge. Untreated can rapidly perforate the cornea.
The 90%+ of community-acquired bacterial conjunctivitis falls into the first four categories (Staph aureus, Strep pneumoniae, H. influenzae, Moraxella). Berberine has documented in vitro activity against all four.
Berberine's Activity Against Conjunctivitis Organisms
In vitro studies have demonstrated berberine activity across the spectrum of common conjunctivitis pathogens:
- Staphylococcus aureus: minimum inhibitory concentration (MIC) 32-128 micrograms per milliliter for general strains, reduced to 8-16 micrograms per milliliter when combined with goldenseal's native efflux-pump inhibitors. Activity against both methicillin-susceptible and methicillin-resistant Staphylococcus aureus strains.
- Streptococcus pneumoniae: minimum inhibitory concentration 16-64 micrograms per milliliter; activity against both penicillin-susceptible and penicillin-resistant strains.
- Haemophilus influenzae: minimum inhibitory concentration 32-128 micrograms per milliliter for typeable and non-typeable strains.
- Moraxella catarrhalis: minimum inhibitory concentration 16-64 micrograms per milliliter.
- Pseudomonas aeruginosa: minimum inhibitory concentration 128-512 micrograms per milliliter; activity is weaker than against Gram-positives but still clinically meaningful at topical application concentrations.
- Chlamydia trachomatis: 12.5-50 micrograms per milliliter reduces chlamydial infectivity by 80-99% in cell culture.
- Neisseria gonorrhoeae: minimum inhibitory concentration 32-128 micrograms per milliliter against clinical isolates. Suspected gonococcal conjunctivitis is a sight-threatening emergency that hospitals treat with immediate pharmaceutical therapy and ophthalmology evaluation, not with berberine.
Topical application of berberine to the conjunctival sac — whether via goldenseal decoction wash or via berberine sulphate drops — can readily achieve local concentrations well above these minimum inhibitory concentrations. The 0.2% berberine solution used in a 1992 Indian trachoma trial (described below) delivers approximately 2000 micrograms per milliliter at the application site, an order of magnitude above the minimum inhibitory concentration for the relevant pathogens.
The Berberine vs Chloramphenicol Claim
It has been claimed that a randomized trial by Mohan and colleagues in India compared berberine sulphate 0.2% eye drops with chloramphenicol 0.5% eye drops in acute bacterial conjunctivitis and found similar cure rates. No such trial was found in PubMed: a search for berberine with chloramphenicol and conjunctivitis or eye drops returns nothing, and the indexed berberine trial by Mohan and colleagues (Indian Journal of Ophthalmology, 1982) is a trachoma trial, described in the next section. The trial design, dosing schedule, cure rates and side-effect figures given with this claim have no traceable source.
The berberine used in the Indian trachoma trials was a measured berberine solution (0.2% in the 1992 trial), not home-prepared goldenseal decoction, and results with it do not carry over to home eyewashes, whose contamination risk is described below.
Trachoma and Ocular Chlamydia trachomatis
Trachoma is a chronic conjunctivitis caused by ocular serovars of Chlamydia trachomatis. Untreated, trachoma produces follicular inflammation that progresses over years to scarring of the conjunctiva, in-turning of the eyelashes (entropion and trichiasis), corneal scarring, and ultimately blindness. The World Health Organization estimates that trachoma still causes blindness in approximately 1.9 million people globally, almost entirely in low-resource settings in Africa, the Middle East, and parts of Asia.
Berberine has been studied for trachoma since the 1960s. Indian research groups tested berberine eye drops for trachoma in the 1980s and 1990s (Mohan 1982; Babbar 1982; Khosla 1992). In the 1992 Delhi trial, in 32 microbiologically confirmed cases, berberine 0.2% drops did better than sulfacetamide 20% (the alternative low-cost option at the time) both in the clinical course of trachoma and in lowering blood antibody levels against Chlamydia trachomatis; no placebo comparison is reported. The World Health Organization (WHO) trachoma elimination strategy now relies primarily on a single oral dose of azithromycin (effective, easy to administer in mass treatment campaigns), but berberine drops remain in use in some settings as a low-cost alternative or adjunct.
The WHO approach is the SAFE package: surgery for in-turned eyelashes, antibiotic mass treatment against the infection, facial cleanliness, and environmental improvement to limit spread. A 2025 review in The Lancet reports that, as of December 2024, 21 countries had eliminated trachoma as a public-health problem with it, and WHO targets global elimination by 2030; persistent and returning active trachoma in some populations could still threaten that target (Habtamu 2025). Ethiopia carries over half of the world's remaining trachoma burden. There, the 2021–2024 Stronger SAFE trial in rural Oromia (68 community clusters) tested a second yearly azithromycin dose, fly control and an intensive face-washing programme: after 3 years, eye chlamydia infection in children aged 1–9 was 2.2% with the enhanced package and 2.7% with the standard package, no real difference. Azithromycin caused only 13 mild, short-lived side effects (mostly nausea, diarrhoea and headache) and no serious ones (Last 2026).
For an individual patient with suspected ocular chlamydial infection (e.g. inclusion conjunctivitis in a sexually active adult), the standard treatment is oral azithromycin or doxycycline, not topical therapy of any kind. Where systemic antichlamydial therapy is available, topical berberine is not used as the primary treatment for ocular chlamydial infection.
Blepharitis, Sty, and Eyelid Margin Infections
Blepharitis — chronic inflammation of the eyelid margins — is one of the most common ophthalmic conditions, often associated with overgrowth of Staphylococcus species at the eyelid base and dysfunction of the meibomian glands that secrete the lipid layer of the tear film. Symptoms include eyelid burning, itching, redness, crusting, foreign-body sensation, and chronic mild conjunctival irritation.
Standard management involves daily eyelid hygiene (warm compresses, eyelid scrubs with dilute baby shampoo or commercial preparations) and, in severe cases, topical or oral antibiotics. Goldenseal eyelid washes have a long traditional history for this indication and may offer modest benefit, particularly for staphylococcal blepharitis where berberine's anti-staphylococcal activity is most relevant. The astringent effect of hydrastine on the inflamed lid margins is also potentially beneficial.
For an acute hordeolum (sty) — a focal infection of an eyelash follicle or eyelid gland presenting as a painful red bump on the eyelid margin — warm compress therapy alone is typically sufficient. Topical antibiotic drops or ointments may be added if there is associated conjunctivitis. Goldenseal compresses or washes are sometimes used as a botanical alternative; the evidence is largely traditional rather than clinical-trial based.
For both blepharitis and hordeolum, the same safety caveats discussed below apply — the contamination risk is lowest with properly prepared, sterilized goldenseal preparations, and pharmaceutical alternatives are now the standard of care.
Anti-Inflammatory Effects in Conjunctival Tissue
Beyond direct antimicrobial action, berberine has documented anti-inflammatory effects in conjunctival tissue that may contribute to its overall ophthalmic benefit:
- Suppression of interleukin-1 beta (IL-1β) in conjunctival epithelial cells — reducing the cytokine cascade that drives the redness, swelling, and symptom severity of bacterial and inflammatory conjunctivitis
- Suppression of tumor necrosis factor alpha (TNF-α) — another inflammatory cytokine that contributes to ocular surface inflammation
- Reduction in nuclear factor kappa B (NF-kB) nuclear translocation in conjunctival cells — the upstream signaling node that drives much of the inflammatory cytokine production
- Antioxidant effects — berberine scavenges reactive oxygen species and induces endogenous antioxidant enzymes (superoxide dismutase, catalase) in ocular tissues
The combined effect is that berberine treatment of conjunctivitis can produce symptom relief that exceeds what would be expected from antibacterial activity alone — some of the apparent therapeutic effect is the dampening of the host inflammatory response rather than direct pathogen killing.
Modern interest in berberine for ocular surface inflammation has extended beyond infectious conjunctivitis to include dry eye disease, allergic conjunctivitis, and some forms of chronic ocular surface inflammation, with preliminary in vitro and animal-model data suggesting potential benefit. Clinical translation in these non-infectious applications is still incomplete.
Critical Safety Caveats — Why "Home Eyewash" Is Risky
Home-prepared herbal eyewashes carry a genuine and well-documented risk of contamination-related ocular infection.
The conjunctival sac is one of the most infection-vulnerable mucous membranes in the body. A bacterially or fungally contaminated preparation, when applied directly to the eye, can produce a range of complications from minor irritation to endophthalmitis (catastrophic intraocular infection that can blind the eye within hours to days). Case reports of vision-threatening complications from home-prepared herbal eye preparations — including chamomile teas, eyebright infusions, and goldenseal washes — are scattered through the ophthalmology literature.
The specific risks of home-prepared goldenseal eyewashes include:
- Bacterial contamination during preparation — municipal tap water is not sterile, and the simmering process is insufficient to sterilize a final preparation that will sit in a container at room temperature
- Storage contamination — a goldenseal decoction held at room temperature for more than a few hours will support significant bacterial growth, including potentially pathogenic Pseudomonas, Serratia, and other Gram-negative organisms
- Particulate contamination — inadequately filtered decoctions can contain plant particulates that can lodge under the eyelid or scratch the cornea
- Inappropriate dilution or pH — an overly concentrated preparation can cause direct chemical irritation; an inappropriate pH (eye preparations are made near-neutral, approximately 7.0-7.4) can damage the corneal epithelium
- Inadequate sterility for application — eye droppers, cloths, or cups used to apply the eyewash may themselves be contaminated
The result is that even an experienced herbalist preparing a "fresh decoction" carries a non-zero risk of an infection-related ocular complication. The risk is small in absolute terms, but the consequences when it does occur (potential permanent vision loss) make the risk-benefit calculation challenging when modern pharmaceutical alternatives are available and inexpensive.
Sunlight and berberine on the eye. Laboratory work at the US National Institute of Environmental Health Sciences found that human lens cells were severely damaged when exposed to berberine together with ultraviolet-A light; retinal cells were also damaged under visible light, but only at about ten times higher berberine concentrations. The authors estimate that goldenseal infusions contain about 1 mM berberine, and tinctures more than ten times that. These are cell-culture findings, with no human eye study; the authors conclude that goldenseal or berberine eyewashes call for caution when the eyes are exposed to bright sunlight, while oral preparations are not likely to cause this eye damage (Chignell 2007).
Why Infant Eyes Are a Special Risk
HIGHEST-RISK GROUP: newborns, premature babies and infants. Goldenseal in any form applied to their eyes carries a risk of bilirubin brain damage (kernicterus).
Berberine, the primary alkaloid in goldenseal, displaces bilirubin from its binding site on serum albumin. In adults this is clinically inconsequential, but in newborns — whose hepatic glucuronidation system is not yet fully mature and who can have high circulating bilirubin levels — the displaced bilirubin can cross the blood-brain barrier and deposit in the basal ganglia, producing kernicterus (bilirubin-induced encephalopathy). Kernicterus is irreversible, can produce permanent neurological damage including cerebral palsy, hearing loss, intellectual disability, and seizure disorder, and can be fatal.
The displacement has been measured. In a laboratory study, berberine was about ten times stronger than phenylbutazone (a known potent bilirubin displacer) at pushing bilirubin off albumin, and a week of daily berberine injections in adult rats lowered bilirubin binding and kept both free and total bilirubin raised. The study was prompted by reports that huanglian (Coptis chinensis), a berberine-rich Chinese herb, posed some kernicterus risk for jaundiced newborn Chinese infants; the author concluded that berberine-rich herbs are "best avoided in jaundiced neonates and pregnant women" (Chan 1993).
Even small amounts of berberine absorbed through the conjunctival mucosa can produce clinically meaningful systemic exposure in a small infant. This is not a theoretical concern — documented case reports exist of neonatal jaundice complications attributed to herbal preparations containing berberine.
The caution covers goldenseal eyewashes, drops, and compresses for any child under 2 years of age. Berberine transfers via breast milk, which raises the same concern for oral goldenseal taken by breastfeeding mothers in the immediate postpartum period. Conjunctivitis or eye discharge in a newborn is a sign pediatricians treat promptly; modern pharmaceutical therapy for it is safe and effective.
Where Antibiotic Drops Are the Standard of Care
Pharmaceutical antibiotic eye drops are now the standard of care for acute bacterial conjunctivitis and the usual first choice in most clinical situations. Available pharmaceutical options include:
- Erythromycin ophthalmic ointment — the standard first-line choice for uncomplicated bacterial conjunctivitis. Inexpensive, well-tolerated, very low resistance profile, safe for use in children of any age.
- Trimethoprim/polymyxin B drops — broad-spectrum alternative, also low cost.
- Fluoroquinolone drops (moxifloxacin, ofloxacin, ciprofloxacin) — reserved for contact lens wearers (where Pseudomonas coverage is critical), severe cases, or treatment failures of first-line agents.
- Azithromycin drops — useful for trachoma and inclusion conjunctivitis from Chlamydia trachomatis; less commonly used for general bacterial conjunctivitis.
- Chloramphenicol drops — widely used outside the United States for routine bacterial conjunctivitis; restricted in the US due to historical concerns about systemic absorption and rare aplastic anemia.
Situations in which clinical practice treats pharmaceutical drops as essential and goldenseal is not used:
- Any conjunctivitis in a child under 2 years
- Suspected gonococcal conjunctivitis (hyperacute purulent presentation, treated as an emergency)
- Contact lens wearer with conjunctivitis (risk of Pseudomonas)
- Conjunctivitis with associated vision loss, severe pain, photophobia, or corneal involvement (signs eye hospitals treat as urgent)
- Immunocompromised patients
- Post-operative ocular surgery patients
- Any conjunctivitis that has not responded to 5-7 days of conservative therapy
The narrow case usually made for a goldenseal preparation is a mild self-limited bacterial conjunctivitis in an adult without high-risk features, in a setting where pharmaceutical drops are unavailable or where the patient has specific reasons (allergy to the conventional alternatives, philosophical preference) to seek a botanical option, and where the preparation can be obtained or made under properly sterile conditions.
What Reduces Contamination Risk in an Eyewash
The measures below are the ones described as substantially reducing (but not eliminating) the risk of contamination-related ocular complications from a goldenseal eyewash:
- Commercial sterile berberine drops — pharmaceutically prepared berberine sulphate eye drops (where available) are vastly safer than any home preparation.
- Sterile, distilled, or pharmaceutical-grade saline water for the decoction; tap water is not sterile.
- Certified-clean cultivated goldenseal from a supplier with documented chain of custody. Wild-crafted goldenseal carries additional microbial contamination risk in addition to the sustainability concerns.
- A clean vessel, with the decoction simmered for 15-20 minutes at full boil to maximize microbial reduction.
- Filtering through a sterile filter to remove particulates (a coffee filter is inadequate; sterile gauze or a 0.22-micron syringe filter removes more).
- Physiologic pH where possible (a small amount of sterile sodium bicarbonate to reach pH 7.0-7.4).
- Immediate use, with any unused portion discarded — a fresh preparation each application, never stored and reused.
- Sterile disposable applicators (sterile gauze, single-use eye droppers).
- Warning signs — worsening symptoms, vision changes, eye pain, or no improvement in 48-72 hours are the points at which home treatment is stopped and the eye is examined by an eye specialist.
- Excluded situations — infants, sight-threatening presentations, contact lens wearers, and any uncertainty about the diagnosis.
Even with rigorous adherence to these measures, home-prepared eyewashes carry more contamination risk than commercial pharmaceutical drops. Prescription antibiotic drops are the standard treatment for acute bacterial conjunctivitis.
Key Research Papers
- Mohan M, Pant CR, Angra SK, Mahajan VM (1982). Berberine in trachoma. (A clinical trial). Indian Journal of Ophthalmology 30(2):69-75. — PubMed PMID: 6754599
- Babbar OP, Chhatwal VK, Ray IB, Mehra MK (1982). Effect of berberine chloride eye drops on clinically positive trachoma patients. Indian Journal of Medical Research 76 Suppl:83-8. — PubMed PMID: 7185757
- Khosla PK, Neeraj VI, Gupta SK, Satpathy G (1992). Berberine, a potential drug for trachoma. Revue Internationale du Trachome et de Pathologie Oculaire Tropicale et Subtropicale et de Santé Publique 69:147-65. — PubMed PMID: 1344968
- Berberine in vitro activity against ocular pathogens (S. aureus, S. pneumoniae, H. influenzae) — PubMed
- Berberine activity against Chlamydia trachomatis in cell culture — PubMed
- Berberine and conjunctival epithelial IL-1beta / TNF-alpha suppression — PubMed
- Berberine activity against Pseudomonas aeruginosa ocular infection — PubMed
- Berberine corneal epithelial wound healing — PubMed
- Chan E (1993). Displacement of bilirubin from albumin by berberine. Biology of the Neonate 63(4):201-8. — PubMed PMID: 8513024
- Chignell CF, Sik RH, Watson MA, Wielgus AR (2007). Photochemistry and photocytotoxicity of alkaloids from Goldenseal (Hydrastis canadensis L.) 3: effect on human lens and retinal pigment epithelial cells. Photochemistry and Photobiology 83(4):938-43. — PubMed PMID: 17645667
- Endophthalmitis case reports from contaminated herbal eyewashes — PubMed
- Bacterial conjunctivitis epidemiology and pathogen distribution — PubMed
- Acute bacterial conjunctivitis treatment guidelines (American Academy of Ophthalmology) — PubMed
- Habtamu E, Harding-Esch EM, Greenland K, et al. (2025). Trachoma. Lancet 405(10492):1865-1878. — PubMed PMID: 40412861
- Last A, Shafi Abdurahman O, Greenland K, et al. (2026). Double-dose azithromycin mass drug administration, facial cleanliness, and fly control measures for trachoma control in Oromia, Ethiopia (Stronger SAFE): a cluster-randomised controlled trial. Lancet Infectious Diseases 26(7):680-691. — PubMed PMID: 41895312