Metformin, Berberine, and Glucagon-Like Peptide-1 Agonists for Insulin Resistance
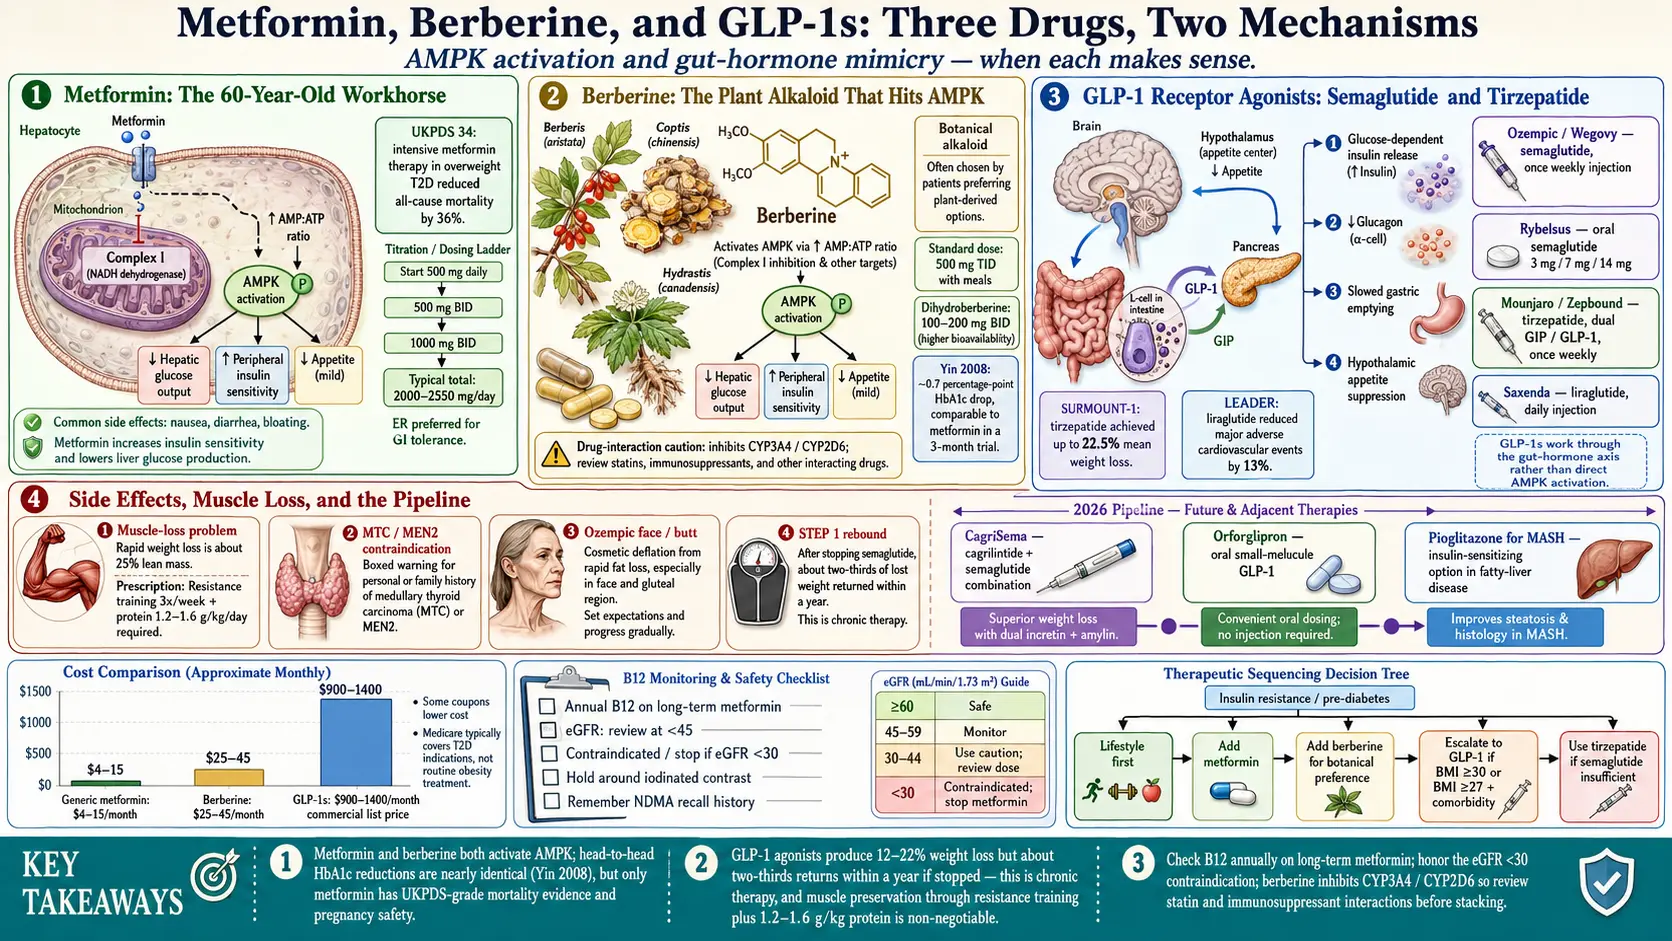
Table of Contents
- Why These Three Drug Classes Matter
- Metformin — The 60-Year-Old Workhorse
- Metformin Dosing, Forms, and Gastrointestinal Tolerance
- Metformin Risks: Vitamin B12, Lactic Acidosis, N-Nitrosodimethylamine
- Metformin Off-Label: Polycystic Ovary Syndrome, Prediabetes, Longevity
- Berberine — The "Natural-Medicine Metformin"
- When Berberine Is NOT Equivalent
- Glucagon-Like Peptide-1 Receptor Agonists — Semaglutide and Friends
- Tirzepatide — The Dual Glucose-Dependent Insulinotropic Polypeptide and Glucagon-Like Peptide-1 Agonist
- Glucagon-Like Peptide-1 Side Effects and the Muscle-Loss Problem
- Cost, Coverage, and Compounded Semaglutide
- The Pipeline: Cagrilintide, Orforglipron, Pioglitazone
- How the Drugs Are Commonly Sequenced
- Monitoring on Therapy
- Key Research Papers
- Connections
- Featured Videos
Why These Three Drug Classes Matter
Insulin resistance does not always yield to diet and exercise alone. For many patients — especially those with a strong genetic push, polycystic ovary syndrome (PCOS), or decades of accumulated metabolic damage — pharmacology is part of the answer. Three drug classes dominate the conversation in 2026: metformin (cheap, old, remarkably safe), berberine (the plant alkaloid that hits the same molecular switch), and the glucagon-like peptide-1 (GLP-1) receptor agonists (GLP-1s) (semaglutide, tirzepatide, and their relatives) that have rewritten what is possible for weight-driven metabolic disease.
None of these replaces the dietary strategy or the muscle-building work discussed in the sibling articles — they multiply their effect. This page covers what each drug does, how it is dosed, what it costs, its side effects, and how the drugs are commonly sequenced.
Metformin — The 60-Year-Old Workhorse
Metformin is a biguanide derived from the French lilac (Galega officinalis), in clinical use since 1957 in Europe and since 1994 in the United States. It remains the first-line drug for type 2 diabetes in essentially every international guideline, and it is the most-prescribed medication for insulin resistance short of full diabetes.
Its primary target is AMP-activated protein kinase (AMPK), the cellular "low-energy" switch. Metformin inhibits Complex I of the mitochondrial electron transport chain, which raises the AMP:ATP ratio and activates AMP-activated protein kinase. Once AMP-activated protein kinase is on, three useful things happen:
- Hepatic glucose production drops. The liver stops dumping glucose into the bloodstream overnight and between meals. This is the largest single effect — fasting blood sugar falls by 20–30% in most responders.
- Peripheral insulin sensitivity improves. Muscle and fat cells take up glucose more readily in response to the same amount of insulin.
- Appetite and weight modestly decrease. Metformin is weight-neutral to mildly weight-reducing (typically 2–5 lb over 6–12 months), unlike sulfonylureas and insulin, which drive weight up.
The landmark evidence is UKPDS 34, the 1998 arm of the UK Prospective Diabetes Study in overweight type 2 diabetics. Metformin reduced all-cause mortality by 36% and diabetes-related death by 42% versus conventional therapy. The trial followed 753 overweight people with newly diagnosed type 2 diabetes for a median of 10.7 years; median hemoglobin A1c (HbA1c) was 7.4% on metformin versus 8.0% with conventional, mainly diet-only, treatment, and the risk of any diabetes-related complication was 32% lower. One part of the study was not reassuring: in a supplementary trial of 537 people already on maximum sulphonylurea therapy, adding metformin early was linked to a 96% higher risk of diabetes-related death. A wider analysis of 4,416 patients did not find that increase with the sulphonylurea-plus-metformin combination.
A mortality benefit has since also been seen with another tablet: in the EMPA-REG OUTCOME trial (7,020 people with type 2 diabetes at high cardiovascular risk, median 3.1 years), the sodium-glucose cotransporter 2 (SGLT2) inhibitor empagliflozin, added to standard care, lowered death from any cause from 8.3% to 5.7% compared with placebo (a 32% relative reduction).
Metformin Dosing, Forms, and Gastrointestinal Tolerance
Problems with metformin most often come from starting at too high a dose. The drug's reputation for causing diarrhea and nausea is earned, but almost entirely avoidable with a slow titration.
- Start: 500 mg once daily with dinner (the largest meal).
- Week 2: 500 mg twice daily (breakfast and dinner).
- Week 3–4: 1000 mg twice daily.
- Maximum: 2550 mg/day (immediate-release) or 2000 mg/day (extended-release).
Metformin is taken with food — mid-meal, not before. Taking it on an empty stomach roughly triples the rate of gastrointestinal (GI) side effects.
Extended-release (ER) metformin is meaningfully better-tolerated than the immediate-release tablet. The drug is released over 8–10 hours rather than peaking in 2–3, which reduces the intestinal-lumen concentration that drives diarrhea. People who could not tolerate the immediate-release tablet often do better on the extended-release form. A once-daily dose of extended-release metformin 1500–2000 mg with dinner is equally effective for most patients.
Generic metformin is one of the cheapest drugs in American pharmacy: $4–15 per month without insurance at discount, warehouse-club and chain pharmacies, and low-cost online pharmacies list it at similar prices.
Metformin Risks: Vitamin B12, Lactic Acidosis, N-Nitrosodimethylamine
Metformin is among the safest prescription drugs in routine use, but three issues deserve explicit mention because patients are rarely warned about them.
Vitamin B12 depletion. Long-term metformin use (generally beyond 4–5 years, sometimes sooner) interferes with calcium-dependent B12 absorption in the terminal ileum. Estimates suggest 10–30% of long-term users develop measurable deficiency, which presents as fatigue, peripheral neuropathy (tingling feet, which is easily mistaken for diabetic neuropathy), anemia, and cognitive fog. Practitioners commonly check serum B12 yearly after the first year of use. When the level is low (some practitioners use about 400 pg/mL as the cut-off), B12 is commonly replaced with methylcobalamin 1000 mcg/day under the tongue or, for established deficiency, with intramuscular injections.
Lactic acidosis. A rare but serious complication in which lactate accumulates to dangerous levels. Risk is essentially zero at normal kidney function but rises sharply below an estimated glomerular filtration rate (eGFR) of 30 mL/min/1.73 m². Current U.S. Food and Drug Administration (FDA) guidance:
- Estimated glomerular filtration rate ≥ 45: no dose change.
- Estimated glomerular filtration rate 30–44: starting is not recommended; for people already taking it, dose reduction is considered (generally ≤ 1000 mg/day).
- Estimated glomerular filtration rate < 30: stop metformin.
- Hold before iodinated intravenous (IV) contrast (computed tomography (CT) scans with contrast, cardiac catheterization) in anyone with estimated glomerular filtration rate < 60 or at risk of acute kidney injury — stop on the day of the procedure and resume 48 hours later if kidney function is stable.
- Hold during acute illness with dehydration, sepsis, or severe gastrointestinal illness.
N-nitrosodimethylamine (NDMA) impurity recalls. In 2020, the U.S. Food and Drug Administration recalled several extended-release metformin lots after finding NDMA, a probable human carcinogen, above acceptable limits. The recalls prompted real worry. Manufacturing controls tightened substantially, and metformin lots released since late 2021 have been consistently clean. Lot numbers can be checked against the U.S. Food and Drug Administration's recall database.
Metformin Off-Label: Polycystic Ovary Syndrome, Prediabetes, Longevity
Metformin's U.S. Food and Drug Administration label is type 2 diabetes. Its real-world use is broader:
- Polycystic ovary syndrome. The strongest off-label use. Metformin improves ovulation, restores menstrual regularity, reduces androgen levels, and modestly improves acne and hirsutism. Standard dosing is 1500–2000 mg/day. Often combined with inositol and a low-carbohydrate approach. See the polycystic ovary syndrome and insulin resistance article and the main polycystic ovary syndrome page for the full protocol.
- Prediabetes. The Diabetes Prevention Program showed metformin reduced progression to type 2 diabetes by 31%, though lifestyle change performed nearly twice as well (58%). Often considered for people with body mass index (BMI) ≥ 30, HbA1c ≥ 6.0%, or prior gestational diabetes.
- Weight maintenance. Modest, real, and mostly useful for preventing regain rather than driving loss.
- Longevity research. The TAME trial (Targeting Aging with Metformin), championed by Nir Barzilai, aims to test whether metformin delays age-related disease clusters in non-diabetic older adults. Mechanistic rationale is strong (AMP-activated protein kinase activation, mechanistic target of rapamycin (mTOR) inhibition, mitochondrial effects). Definitive human evidence is still pending. Taking metformin specifically for longevity remains unproven.
Berberine — The "Natural-Medicine Metformin"
Berberine is a bright-yellow isoquinoline alkaloid extracted from Berberis (barberry), Coptis chinensis (goldthread), and Hydrastis canadensis (goldenseal). It has a two-thousand-year history in Chinese and Ayurvedic medicine for diarrhea, dysentery, and what we would now call metabolic sluggishness.
Its headline mechanism is remarkable: berberine activates the same AMP-activated protein kinase pathway as metformin. Yin and colleagues published the first head-to-head human trial in 2008 (Metabolism), a small pilot study of 36 adults with newly diagnosed type 2 diabetes. Berberine 500 mg three times daily lowered HbA1c from 9.5% to 7.5% over three months, a blood-sugar effect the authors described as similar to metformin at the same dose in the same trial; fasting glucose and triglycerides also fell. In a second part of the study, 48 adults with poorly controlled diabetes added berberine for three months: HbA1c fell from 8.1% to 7.3%, fasting insulin fell 28.1% and the insulin-resistance index (homeostatic model assessment of insulin resistance, HOMA-IR) fell 44.7%. Twenty people (34.5%) had passing stomach and bowel side effects.
Practical dosing:
- 500 mg three times daily with meals. Total 1500 mg/day.
- Split dosing is the usual practice — berberine has a short half-life and poor oral bioavailability (~5%), so once-daily dosing is reported to work poorly.
- Gastrointestinal tolerance is often better than metformin, though some users get loose stools or cramping in the first 1–2 weeks. It is usually taken with food.
- Antimicrobial bonus. Berberine is a well-established botanical antimicrobial effective against many gram-negative gut bacteria. It is a mainstay of herbal small intestinal bacterial overgrowth (SIBO) protocols — see the herbal antimicrobials deep dive for context.
Drug interactions matter. Berberine is a moderate inhibitor of cytochrome P450 3A4 (CYP3A4) and cytochrome P450 2D6 (CYP2D6), which means it can raise blood levels of many prescription drugs — including statins (simvastatin, atorvastatin), cyclosporine, tacrolimus, many calcium-channel blockers, certain antidepressants, and some chemotherapeutics. The interaction matters most for the immunosuppressants cyclosporine and tacrolimus, whose blood levels have to stay within a narrow range. With statins, muscle aches are the sign of raised statin levels, and a lower statin dose is sometimes used.
Quality sourcing. Supplements are unregulated and berberine capsules vary; some products carry independent third-party testing of identity and potency. Expect $25–45 per month at standard dosing.
Dihydroberberine is a reduced form with substantially higher bioavailability — roughly 5× which allows lower doses (100–200 mg twice daily) with less gastrointestinal burden. It is more expensive and has a smaller evidence base, and is used by people who cannot tolerate the full three-times-daily schedule.
When Berberine Is NOT Equivalent
Berberine gets marketed as "nature's semaglutide" and "metformin in a capsule." It is neither of those things at the margin. The research points to these limits:
- Severe or long-standing type 2 diabetes. Patients with HbA1c above ~8.5%, or with insulin deficiency, are treated with prescription drugs; berberine is at most an add-on in that setting.
- Pregnancy and breastfeeding. The research raises a concern here: berberine crosses the placenta and has been linked to kernicterus (displacement of bilirubin in newborns). Metformin, by contrast, is well-studied and generally safe in pregnancy at physician discretion.
- Children. Use in children has been limited to specialist supervision.
- Polypharmacy. For people on three or more prescription drugs metabolized by cytochrome P450 3A4, the interaction risk rises with each added drug.
Berberine has been used for mild insulin resistance, prediabetes and polycystic ovary syndrome, and by people who prefer a botanical approach. For people who have crossed into type 2 diabetes or who have significant cardiovascular risk, metformin has the stronger evidence base.
Glucagon-Like Peptide-1 Receptor Agonists — Semaglutide and Friends
Glucagon-like peptide-1 is a gut hormone released after meals. It stimulates insulin release in a glucose-dependent way (meaning it works only when blood sugar is high, which is why glucagon-like peptide-1 drugs rarely cause hypoglycemia on their own), suppresses glucagon, slows gastric emptying, and reduces appetite through the hypothalamus. The class of drugs that mimic glucagon-like peptide-1 has transformed obesity and diabetes care since 2005.
The current agents, roughly in order of clinical weight:
- Semaglutide. Given as a weekly injection (one product labelled for type 2 diabetes, another for obesity) or as a daily tablet (3, 7, or 14 mg for type 2 diabetes; a separate daily semaglutide tablet is now labelled for weight management). Typical hemoglobin A1c reduction 1.5–1.8%, typical weight loss 12–15% of body weight over a year at full dose.
- Liraglutide. Given as a daily injection (one product labelled for type 2 diabetes, another for obesity). Older, shorter-acting, less weight loss than semaglutide, but covered by some insurance plans that balk at the weekly agents. The LEADER trial (Marso et al., New England Journal of Medicine 2016) showed liraglutide reduced major adverse cardiovascular events by 13% in people with type 2 diabetes at high cardiovascular risk — the first clear heart-protective evidence for the class.
- Dulaglutide. Weekly injectable. Efficacy between liraglutide and semaglutide. Easier pen.
- Exenatide. The original glucagon-like peptide-1, now largely supplanted.
For insulin resistance specifically (pre-diabetes, metabolic syndrome without a formal type 2 diabetes diagnosis), glucagon-like peptide-1 use is off-label and cash-pay. Insurance covers them for type 2 diabetes, or for obesity for people who meet body mass index criteria (body mass index ≥ 30, or ≥ 27 with a comorbidity like hypertension).
Tirzepatide — The Dual Glucose-Dependent Insulinotropic Polypeptide and Glucagon-Like Peptide-1 Agonist
Tirzepatide (one product labelled for type 2 diabetes, another for obesity) adds a second hormone receptor — glucose-dependent insulinotropic polypeptide (GIP) — to the glucagon-like peptide-1 activity. The dual mechanism produces the largest weight reductions any diabetes/obesity drug has achieved.
The SURPASS trials (type 2 diabetes) showed hemoglobin A1c reductions of 2.0–2.5 percentage points and weight loss of 11–15% at the 15 mg dose — consistently superior to semaglutide head-to-head. The SURMOUNT-1 trial (Jastreboff et al., New England Journal of Medicine 2022) in non-diabetic obesity showed a mean weight reduction of 20.9% at 15 mg over 72 weeks (15.0% at 5 mg, 19.5% at 10 mg, 3.1% on placebo) — closer to bariatric surgery than to any prior drug.
Dosing starts at 2.5 mg weekly for four weeks, titrating monthly through 5, 7.5, 10, 12.5, and 15 mg. Most patients plateau at 10–15 mg.
Glucagon-Like Peptide-1 Side Effects and the Muscle-Loss Problem
The class has real downsides that get glossed over in marketing.
- Nausea, vomiting, diarrhea, constipation. Common, dose-dependent, worst during titration. Slow titration is reported as the single biggest predictor of tolerability; people describe smaller meals, less fatty meals, extra fluids, and less alcohol as helping.
- Pancreatitis. Rare but real. Persistent severe upper-abdominal pain is the warning sign, and the labels direct stopping the drug if pancreatitis is suspected.
- Gallbladder disease. Rapid weight loss increases gallstone risk regardless of mechanism; glucagon-like peptide-1 receptor agonists appear to add a small independent risk.
- Thyroid C-cell tumors. Observed in rodents. The human risk is uncertain, but the drugs are contraindicated in personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia syndrome type 2 (MEN 2).
- Hollowed face and buttocks (popularly named after a semaglutide brand). Rapid fat loss, especially in older patients, unmasks underlying tissue thinning — the face and buttocks look hollowed. This is cosmetic, not dangerous, but it is real.
- Muscle loss. The most underappreciated issue. Weight loss from any source is roughly 25% lean mass unless defended. At the glucagon-like peptide-1 rate of loss, an untrained patient can shed 10–15 lb of muscle in a year — catastrophic for long-term metabolic health, because muscle is the body's largest insulin-sensitive tissue. Resistance training 3× per week and protein intake of 1.2–1.6 g/kg body weight are the measures most often described for protecting muscle on a glucagon-like peptide-1. See the exercise and muscle article.
- Rebound weight regain. The STEP 1 trial extension showed that stopping semaglutide returned two-thirds of lost weight within a year. In its 327 participants, those on semaglutide had lost 17.3% of their body weight by week 68; one year after stopping they had regained 11.6 percentage points, ending 5.6% below their starting weight, and most heart and metabolic improvements drifted back toward baseline. The trial authors concluded that ongoing treatment is required to keep the improvements.
Cost, Coverage, and Compounded Semaglutide
Commercial list prices in early 2026 run $900–1,400 per month for semaglutide and tirzepatide. With commercial insurance and a manufacturer savings coupon, eligible patients can pay as little as $25/month for type 2 diabetes; coverage for the obesity indications (semaglutide, tirzepatide) is patchier but improving.
Medicare Part D covers glucagon-like peptide-1 receptor agonists for a type 2 diabetes indication — use for weight loss alone is statutorily excluded unless Congress changes the law. Semaglutide injection is now also labelled for uses other than weight loss: reducing major cardiovascular events in adults with established heart disease and obesity or overweight, and treating metabolic dysfunction-associated steatohepatitis (MASH) with moderate to advanced liver fibrosis (stages F2–F3). Medicaid coverage varies widely by state.
Compounded semaglutide. During the 2022–2025 shortage, the U.S. Food and Drug Administration allowed 503A and 503B compounding pharmacies to produce semaglutide for cash-pay patients at $150–350/month. The U.S. Food and Drug Administration declared the tirzepatide shortage resolved on 2 October 2024 (re-confirmed 19 December 2024) and the semaglutide shortage resolved on 21 February 2025, and with that the legal basis for large-scale compounding of copies evaporated. The agency's wind-down periods ended for state-licensed 503A pharmacies on 5 March 2025 (tirzepatide) and 24 April 2025 (semaglutide), and for 503B outsourcing facilities on 19 March 2025 and 22 May 2025. Some compounders continue to operate in gray areas, often by adding small amounts of B12 or amino acids and calling the product "non-FDA-approved." Quality varies, the drug may not be pure semaglutide, and the legal standing is shaky: the U.S. Food and Drug Administration has stated that a compounded product combining semaglutide with another ingredient such as vitamin B12 can still count as an essential copy of an approved drug.
The Pipeline: Cagrilintide, Orforglipron, Pioglitazone
- CagriSema — a fixed combination of cagrilintide (an amylin analog) plus semaglutide. In the phase 3 REDEFINE 1 trial (3,417 adults without diabetes, 68 weeks), the combination gave an average weight loss of 20.4% versus 3.0% on placebo; stomach and bowel side effects (nausea, vomiting, diarrhea, constipation or abdominal pain) affected 79.6% versus 39.9% on placebo and were mainly passing and mild to moderate. Likely U.S. Food and Drug Administration filing in late 2026.
- Orforglipron — an oral small-molecule glucagon-like peptide-1 agonist. Unlike oral semaglutide (a peptide taken with an absorption enhancer and rigid dosing rules), orforglipron is a true small molecule taken as a normal once-daily pill with food or without. The U.S. Food and Drug Administration approved it on 1 April 2026 for long-term weight management in adults with obesity, or with overweight and at least one weight-related condition. In the 72-week phase 3 ATTAIN-1 trial of 3,127 adults with obesity but no diabetes, average weight loss was 7.5%, 8.4% and 11.2% at 6, 12 and 36 mg versus 2.1% on placebo; 5.3–10.3% stopped because of side effects (2.7% on placebo), mostly mild-to-moderate stomach and bowel effects. A higher figure of up to 14.7% came from a smaller 36-week phase 2 trial. In early type 2 diabetes (ACHIEVE-1, 559 adults, 40 weeks), orforglipron lowered HbA1c by 1.24–1.48 points versus 0.41 on placebo and body weight by 4.5–7.6% versus 1.7%, with no episodes of severe low blood sugar.
- Pioglitazone. An older thiazolidinedione that remains a genuinely powerful insulin sensitizer by activating peroxisome proliferator-activated receptor gamma (PPAR-γ). U.S. Food and Drug Administration-approved for type 2 diabetes; its use in MASH is off-label. Downsides are why it is rarely first-line: weight gain, fluid retention, increased heart failure risk, decreased bone density, and a disputed bladder cancer signal. It is used as a second- or third-line agent in patients with severe insulin resistance and fatty liver.
How the Drugs Are Commonly Sequenced
A commonly described sequence:
- Lifestyle first. Diet, resistance training, sleep, and stress reduction produce real HOMA-IR and HbA1c improvements. A common approach gives this 3–6 months before adding a drug unless numbers are severe.
- Metformin as the usual first drug. For people crossing into prediabetes or type 2 diabetes, or with polycystic ovary syndrome, metformin is cheap, well-studied, and has mortality evidence going back to 1998. Slow titration is common, and the extended-release form is an option when the immediate-release tablet causes stomach and bowel problems.
- Berberine is used as an alternative for mild cases, by patients who prefer not to take prescriptions, or alongside small intestinal bacterial overgrowth. It is not a replacement for metformin in established diabetes.
- A glucagon-like peptide-1 drug is added or swapped in when weight is the dominant driver, when metformin is insufficient, or when the patient is metformin-intolerant. Semaglutide is the most used; tirzepatide is generally chosen when the weight-loss goal is > 15% or when semaglutide plateaus.
- Pioglitazone is used as a specialist's add-on for severe insulin resistance with fatty liver, with heart failure and bone risks weighed.
With any drug combination, the diet, resistance training, and sleep work continues to matter. The drugs add to it rather than replace it.
Monitoring on Therapy
- Hemoglobin A1c every 3 months until stable, then every 6 months.
- Homeostatic model assessment of insulin resistance (fasting glucose and fasting insulin) every 6–12 months to track insulin resistance directly. See the lab testing article.
- Fasting lipid panel yearly (triglycerides fall meaningfully on metformin and glucagon-like peptide-1 receptor agonists).
- Comprehensive metabolic panel with estimated glomerular filtration rate yearly — more often if starting metformin or changing dose.
- Vitamin B12 yearly on metformin after year one.
- Weight, waist circumference, body composition. Dual-energy X-ray absorptiometry (DEXA) or bioimpedance every 6–12 months on a glucagon-like peptide-1 to catch muscle loss early.
- Blood pressure and resting heart rate at every visit (glucagon-like peptide-1 receptor agonists raise heart rate by 2–4 bpm on average).
- Amylase/lipase only if symptoms suggest pancreatitis — routine screening is not part of standard practice.
Key Research Papers
- UK Prospective Diabetes Study (UKPDS) Group. Effect of intensive blood-glucose control with metformin on complications in overweight patients with type 2 diabetes (UKPDS 34). Lancet. 1998. — doi:10.1016/S0140-6736(98)07037-8
- Yin J, Xing H, Ye J. Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism. 2008. — doi:10.1016/j.metabol.2008.01.013
- Marso SP, et al. Liraglutide and cardiovascular outcomes in type 2 diabetes (LEADER). N Engl J Med. 2016. — doi:10.1056/NEJMoa1603827
- Jastreboff AM, et al. Tirzepatide once weekly for the treatment of obesity (SURMOUNT-1). N Engl J Med. 2022. — doi:10.1056/NEJMoa2206038
- Zinman B, Wanner C, Lachin JM, et al. Empagliflozin, cardiovascular outcomes, and mortality in type 2 diabetes. N Engl J Med. 2015;373(22):2117-2128. — PubMed PMID: 26378978
- Wilding JPH, Batterham RL, Davies M, et al. Weight regain and cardiometabolic effects after withdrawal of semaglutide: the STEP 1 trial extension. Diabetes Obes Metab. 2022;24(8):1553-1564. — PubMed PMID: 35441470
- Wharton S, Blevins T, Connery L, et al. Daily oral GLP-1 receptor agonist orforglipron for adults with obesity. N Engl J Med. 2023;389(10):877-888. — PubMed PMID: 37351564
- Garvey WT, Blüher M, Osorto Contreras CK, et al. Coadministered cagrilintide and semaglutide in adults with overweight or obesity. N Engl J Med. 2025;393(7):635-647. — PubMed PMID: 40544433
- Rosenstock J, Hsia S, Nevarez Ruiz L, et al. Orforglipron, an oral small-molecule GLP-1 receptor agonist, in early type 2 diabetes. N Engl J Med. 2025;393(11):1065-1076. — PubMed PMID: 40544435
- Wharton S, Aronne LJ, Stefanski A, et al. Orforglipron, an oral small-molecule GLP-1 receptor agonist for obesity treatment. N Engl J Med. 2025;393(18):1796-1806. — PubMed PMID: 40960239
PubMed Topic Searches
Current peer-reviewed work on these agents and insulin resistance:
- PubMed: Metformin, AMPK, and insulin resistance
- PubMed: Metformin and vitamin B12 deficiency
- PubMed: Metformin in polycystic ovary syndrome
- PubMed: Berberine for type 2 diabetes and HbA1c
- PubMed: Berberine and AMPK mechanism
- PubMed: Semaglutide and weight loss (STEP trials)
- PubMed: Tirzepatide SURPASS and SURMOUNT trials
- PubMed: GLP-1 agonists and muscle loss
- PubMed: Pioglitazone, insulin sensitivity, and MASH
- PubMed: Orforglipron and oral GLP-1 agonists
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Polycystic Ovary Syndrome
- Reversal Protocol: Diet and Fasting
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Insulin Resistance and Polycystic Ovary Syndrome
- Exercise and Muscle Insulin Sensitivity
- Insulin Resistance
- Diabetes
- Obesity
- Berberine
- Small Intestinal Bacterial Overgrowth
- CGM for Non-Diabetics
- Glucagon-Like Peptide-1 Receptor Agonists
- Metabolic Syndrome
- Estimated Glomerular Filtration Rate
- Vitamin B12
- Hypertension
- Herbal Antimicrobials
- Non-Alcoholic Fatty Liver Disease Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Metformin — the full drug page: mechanism, side effects, longevity research.