⚠ Evidence warning: Clinical trials or other evidence do not support the claims that andrographis works best in the first 48-72 hours of a cold or flu and that its tolerability is excellent with side-effect rates similar to placebo. This page keeps it as a report of what people, websites or other media say.
Andrographis for Cold and Flu
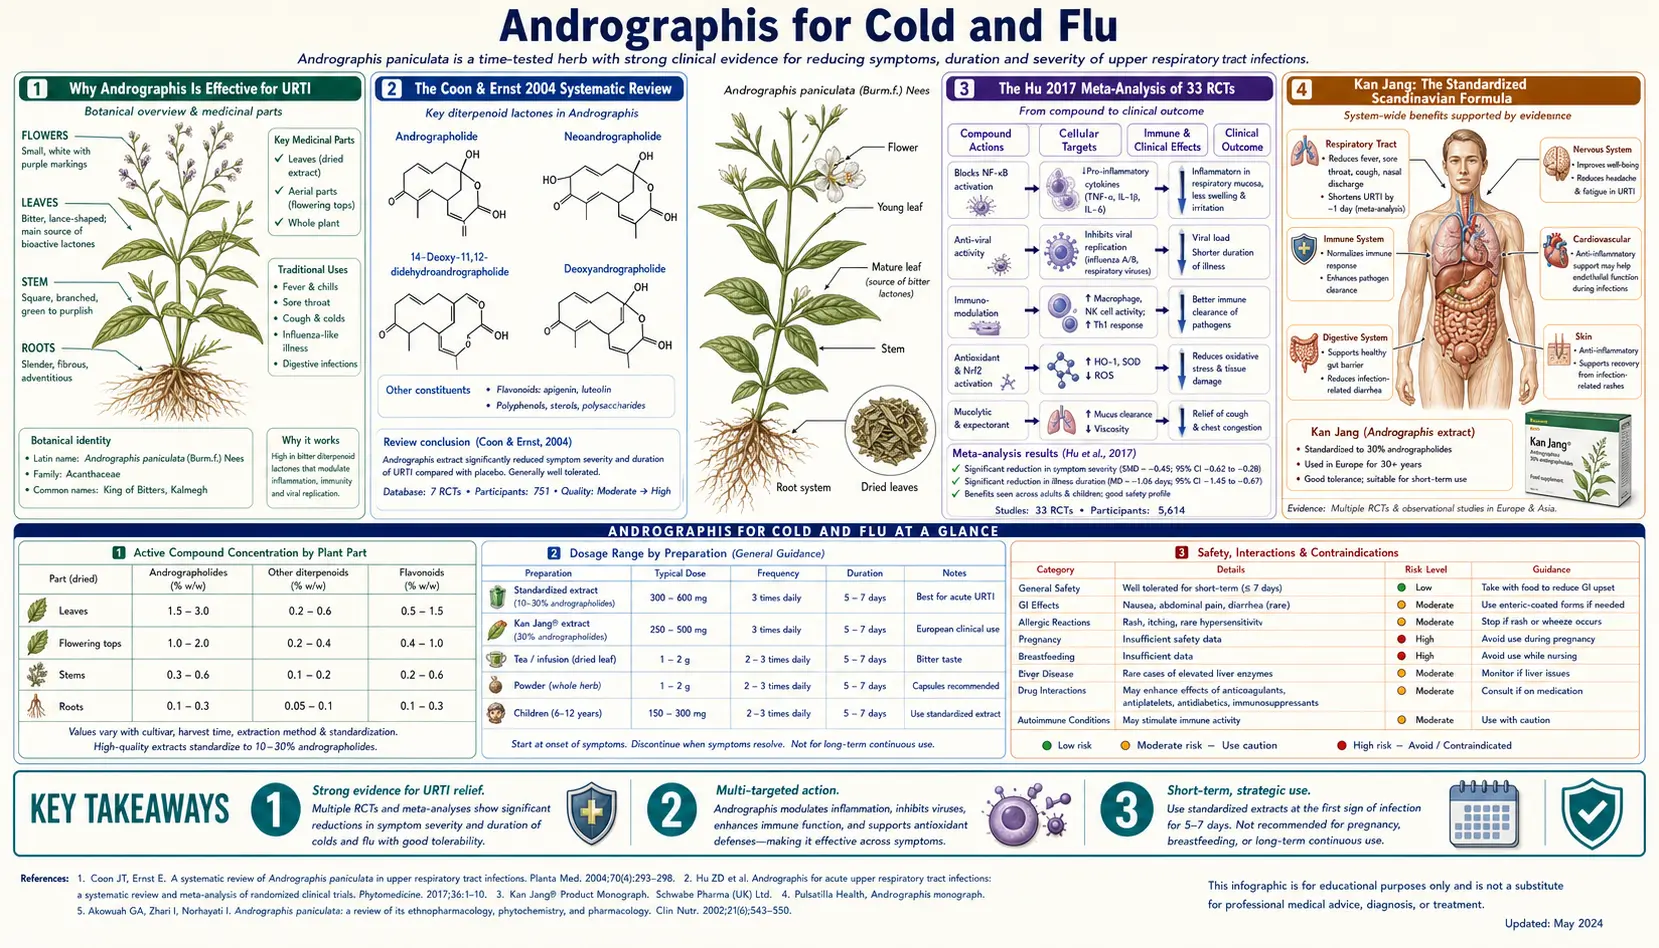
Acute upper respiratory tract infection (URTI) is the single best-documented clinical use of Andrographis paniculata. The 2004 systematic review by Thompson Coon and Ernst assessed seven double-blind controlled trials and found the herb superior to placebo for relieving the symptoms of uncomplicated URTI. Hu and colleagues' 2017 systematic review extended the work to 33 randomized controlled trials and 7,175 patients, finding improvement in cough and sore throat compared with placebo and in overall symptoms, while rating the quality of the trials as overall poor. A standardized andrographis–eleuthero combination developed in Sweden (Andrographis paniculata + Eleutherococcus senticosus, standardized to andrographolide plus deoxyandrographolide) is the most-studied commercial Andrographis preparation worldwide, with the largest body of pediatric and adult URTI trial data. This deep-dive walks through the clinical evidence, the formulation choices that matter, the molecular mechanism behind the antiviral and symptom-reducing effects, and the doses used for adults at the first sign of a cold or flu.
Table of Contents
- Why Andrographis Is Effective for URTI
- The Coon & Ernst 2004 Systematic Review
- The Hu 2017 Meta-Analysis of 33 Randomized Controlled Trials
- The Andrographis–Eleuthero Combination: A Standardized Scandinavian Formula
- Andrographolide: The Diterpene Behind the Effect
- Influenza-Specific Evidence
- Effects on Specific Symptoms (Sore Throat, Cough, Headache, Fatigue)
- Doses and Timing Used in Trials and Practice
- An Adult URTI Regimen Described by Practitioners
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
Why Andrographis Is Effective for URTI
Most "cold and flu" herbs are either antimicrobial (oregano oil, garlic, olive leaf) or pure immune stimulants (echinacea, astragalus). Andrographis is unusual in operating across at least four mechanistically distinct pathways that all converge on reduced symptoms and faster resolution of viral upper respiratory tract infection:
- Direct antiviral binding — andrographolide and its deoxy congeners have been shown to bind influenza hemagglutinin, respiratory syncytial virus (RSV) F protein, dengue envelope protein, and human immunodeficiency virus (HIV) gp120 in vitro, interfering with viral attachment and fusion. Andrographolide also inhibits influenza neuraminidase (the same molecular target as oseltamivir), reducing release of new viral particles from infected cells.
- Cytokine modulation — URTI symptoms (fever, malaise, body ache, headache) are driven more by host cytokine response than by the virus itself. By covalently inhibiting NF-kB p50, andrographolide blunts the over-exuberant tumor necrosis factor-alpha, interleukin-1-beta, and interleukin-6 (IL-6) surge that produces the cardinal "flu-like" symptoms while preserving enough cytokine signaling for actual viral clearance.
- Natural killer (NK) and macrophage activation — the same molecule that suppresses cytokine over-production also increases natural killer cell cytotoxicity and macrophage phagocytic capacity, improving the clearance arm of the response.
- Mucosal epithelial protection — andrographolide reduces lipopolysaccharide-induced and virus-induced lung injury in animal models, partly through Nrf2-driven antioxidant defenses in respiratory epithelium.
The result is a single botanical that simultaneously interferes with viral replication, calms the symptom-producing cytokine surge, and activates clearance — an unusual combination that helps explain why it consistently beats placebo in randomized trials of uncomplicated URTI.
The Coon & Ernst 2004 Systematic Review
The watershed publication that brought Andrographis into mainstream evidence-based discussion of cold remedies was the 2004 systematic review by Jo Thompson Coon and Edzard Ernst (Peninsula Medical School, UK), published in Planta Medica. The authors searched six databases and asked manufacturers and drug-safety reporting schemes for data, then assessed seven double-blind, controlled trials with 896 participants of Andrographis paniculata (either as a single-herb preparation or as the andrographis–eleuthero combination) for symptomatic uncomplicated upper respiratory tract infection in adults and adolescents.
Quality assessment was unusually rigorous for a herbal-medicine review: every included trial scored at least 3 out of 5 for methodological quality on the Jadad scale. The trials included used standardized andrographolide-quantified extracts, blinded outcome assessment, intention-to-treat analysis where applicable, and clinically meaningful endpoints (total symptom score, duration of illness, days of sick leave, individual symptom scores for cough, sore throat, nasal congestion, headache, fatigue, ear pain).
Conclusions from the pooled analysis:
- Andrographis produced significantly greater symptom relief than placebo on the primary composite symptom-score outcome (typically a 0-100 visual-analog scale across cardinal URTI symptoms)
- The effect was largest in the first 48-72 hours, the window when symptoms are typically worst
- The effect was robust across multiple commercial Andrographis preparations (single-herb preparations and the andrographis–eleuthero combination)
- Tolerability was excellent with adverse-effect rates similar to placebo (the most common reported adverse effect was the well-known unpleasant bitter taste at high doses, plus occasional headache and gastrointestinal upset)
- There was preliminary evidence of a preventive effect
- Adverse events (AEs) were “generally mild and infrequent”, and there were few spontaneous reports of adverse events to safety-reporting schemes (the bitter taste at high doses, occasional headache and gastrointestinal upset are the side effects usually described)
Ernst was at the time the most rigorous and famously skeptical scientific reviewer of complementary medicine in the English-speaking world, having repeatedly published negative reviews of homeopathy, healing touch, chiropractic for non-back-pain conditions, and dozens of other modalities. The review's positive conclusion on Andrographis (in the authors' words, it “may be a safe and efficacious treatment for the relief of symptoms of uncomplicated upper respiratory tract infection; more research is warranted”) gave the herb unusual evidentiary credibility in mainstream pharmacology and integrative medicine practice.
The Hu 2017 Meta-Analysis of 33 Randomized Controlled Trials
Hu and colleagues (primary care researchers at the University of Southampton, UK, working with Beijing University of Chinese Medicine and a Paris institute) published a comprehensive update in PLOS ONE in 2017 (with a correction notice in 2018). Their systematic review, searching English and Chinese databases up to March 2016, identified 33 randomized controlled trials and 7,175 patients, with the trial pool now extending across Europe, India, Thailand, Russia, China, and South Korea. Findings:
- Most trials tested commercial Andrographis paniculata products (alone or in herbal mixtures), but few reported manufacturing or quality-control details
- Cough improved compared with placebo in 596 people (standardised mean difference, SMD, −0.39; 95% confidence interval −0.67 to −0.10). An SMD expresses the difference between groups in standard-deviation units
- Sore throat improved compared with placebo in 314 people (SMD −1.13; 95% confidence interval −1.37 to −0.89), a larger effect
- Overall symptoms improved significantly with Andrographis (alone or added to usual care) compared with placebo, usual care, and other herbal therapies
- Compared with usual care, Andrographis (alone or added to usual care) shortened the duration of cough, sore throat, and sick leave or time to recovery
- No major adverse events were reported; minor ones were mainly gastrointestinal (GI)
- The authors judged the methodological quality of the included trials to be “overall poor”
- Trial heterogeneity was substantial, reflecting variation in extract preparation, andrographolide standardization, and outcome measures — a caveat applied to all herbal-medicine meta-analyses
The authors concluded that Andrographis paniculata “appears beneficial and safe” for relieving acute respiratory tract infection symptoms and shortening the time to recovery, but that the findings “should be interpreted cautiously owing to poor study quality and heterogeneity”, and that well-designed trials of its effectiveness and its potential to reduce antibiotic use are needed.
The Hu 2017 review remains the single largest pooled assessment of Andrographis for cold and flu — with its authors' own warning about the poor quality of the trials — and the 2017 publication date matters because it captures another decade of trials that had accumulated since Coon & Ernst — including several Chinese-language trials that had previously been excluded from English-language reviews.
The Andrographis–Eleuthero Combination: A Standardized Scandinavian Formula
The most-studied andrographis product is a fixed-combination product made by a Swedish manufacturer, combining standardized Andrographis paniculata extract with standardized Eleutherococcus senticosus (formerly Siberian ginseng) root extract. The product was developed in the 1970s by Swedish researchers seeking a non-pharmaceutical option for the winter URTI burden in Scandinavia. Standardization parameters:
- Andrographis component: standardized to 4% total andrographolides, including andrographolide and deoxyandrographolide as marker compounds quantified by HPLC
- Eleutherococcus component: standardized to total eleutherosides B and E content
- Typical tablet content: 85 mg Andrographis extract + 9.7 mg Eleutherococcus extract per tablet
- Dose described for the product: 4 tablets three times daily during acute URTI (i.e., 12 tablets per day = ~1,000 mg Andrographis extract per day = ~40 mg total andrographolides per day)
The rationale for combining Andrographis with Eleutherococcus was both pharmacological (Eleutherococcus is a classical adaptogen used to reduce stress-related immune suppression) and pharmacokinetic (Eleutherococcus saponins appear to modestly improve Andrographis bioavailability in animal studies). The trials of this combination and of its standardized andrographis extract by Caceres, Melchior, and colleagues in the 1990s-2000s consistently showed shortened illness duration and reduced symptom severity compared with placebo, including in pediatric and elderly populations.
The combination is sold outside the US under several distributor names, and a comparable andrographis–eleuthero combination is sold in the US. Single-herb andrographis products are sold standardized to 4-10% andrographolide content; at equal andrographolide doses they are described as comparable to the combination's andrographis component.
Andrographolide: The Diterpene Behind the Effect
Andrographolide is a labdane-type diterpene lactone (molecular formula C20H30O5, molecular weight 350.4) characterized by an alpha,beta-unsaturated gamma-butyrolactone — a "Michael acceptor" functional group that allows the molecule to form covalent bonds with cysteine sulfhydryls on key regulatory proteins. The labdane skeleton is shared with several other bioactive diterpenes (forskolin, ginkgolides, salvinorin A), but the lactone substitution pattern of andrographolide is distinctive.
The molecule was first isolated and characterized in 1911 by Gorter, but its full structural elucidation and pharmacological mapping came in the 1950s-70s through work by Chakravarti, Cava, and others. The biosynthesis proceeds from geranylgeranyl pyrophosphate through standard terpenoid cyclization, with the final lactone oxidation occurring in the chloroplast.
The three principal congeners in Andrographis leaves (in addition to andrographolide itself, which is the dominant species at ~1-4% dry weight):
- 14-Deoxyandrographolide — the second most abundant diterpenoid in Andrographis leaves. Approximately 30-40% the potency of andrographolide on NF-kB inhibition but a longer plasma half-life, contributing meaningfully to the clinical effect of total-andrographolide-standardized extracts.
- Neoandrographolide — a glycoside form with weaker direct molecular potency but better water solubility, contributing to oral bioavailability and gut microbiome conversion back to active aglycones.
- 14-Deoxy-11,12-didehydroandrographolide — a minor congener with potent in-vitro antiviral activity, particularly against herpes simplex virus and human immunodeficiency virus.
Standardized extracts that report only "andrographolide content" capture roughly two-thirds of the total bioactive material. Better-quality extracts standardize to "total andrographolides" (a sum-of-congeners measurement), which correlates more closely with clinical effect. Some product labels report both the total andrographolide content and the specific andrographolide content.
Influenza-Specific Evidence
While many of the URTI trials enrolled patients with seasonal "common cold" of mixed viral etiology, several trials specifically targeted influenza A and B. Animal-model studies have established that andrographolide inhibits influenza A H1N1 and H3N2 replication in cell culture and reduces lung injury and mortality in mouse models of severe influenza pneumonia. The molecular mechanism is dual:
- Neuraminidase inhibition — andrographolide binds the active site of influenza neuraminidase, blocking cleavage of sialic acid residues that normally release newly assembled virions from the host cell surface. This is the same molecular mechanism exploited by oseltamivir and zanamivir, although andrographolide is approximately 10-100 fold less potent on a molar basis than the pharmaceutical neuraminidase inhibitors.
- Cytokine storm suppression — severe influenza mortality is driven less by viral burden per se than by an overwhelming cytokine response ("cytokine storm") that produces ARDS-like lung injury. Andrographolide's suppression of tumor necrosis factor-alpha, interleukin-1-beta, interleukin-6, and ICAM-1 production substantially attenuates this lung injury in animal models. In one mouse study (Cai and colleagues, 2016), the congener 14-deoxy-11,12-didehydroandrographolide reduced deaths, weight loss and lung virus levels after lethal H5N1 or H1N1 influenza challenge and lowered inflammatory cytokines in the lungs and blood.
A 2003 Russian study in Volgograd (Kulichenko and colleagues) compared the andrographis–eleuthero combination with amantadine (a now-obsolete influenza drug) in diagnosed influenza, in a pilot of 540 patients (71 on the combination) and a second phase of 66 patients. Sick leave was shorter and post-influenza complications were less frequent with the combination, which was well tolerated. Several Thai trials in pediatric influenza found Andrographis modestly accelerated fever defervescence and reduced total illness duration.
It is important to be clear about scope: Andrographis is not a replacement for influenza vaccination in high-risk patients, and it is not a substitute for oseltamivir in severe or hospitalized influenza in patients at risk of complications. For uncomplicated influenza in otherwise healthy adults, practitioners use Andrographis as a symptomatic option with probable mild antiviral activity; in the one trial against paracetamol (acetaminophen), in sore throat, the high dose matched paracetamol at day 3.
Two 2023 trials tested Andrographis in COVID-19, with opposite results. In Georgia, 140 people with mild COVID-19 took the andrographis–eleuthero combination (90 mg of andrographolides a day) or placebo, with paracetamol, for 14 days: fewer cases turned severe on the combination (5.36% vs 17.86% on placebo), and recovery was faster. In Thailand, 146 patients with mild to moderate COVID-19 who were already taking the antiviral favipiravir received 180 mg a day of andrographis extract or placebo: the extract added no clinical or virological benefit, although one inflammation marker (interleukin-1 beta) was lower.
See our Influenza page for the broader context including vaccine recommendations, oseltamivir use, and supportive care.
Effects on Specific Symptoms (Sore Throat, Cough, Headache, Fatigue)
Across the pooled trial data, Andrographis produces the largest measured effect on three URTI symptoms in particular:
- Sore throat (pharyngitis) — the largest effect, with Thamlikitkul's 1991 Thai trial in adults with pharyngotonsillitis showing pain reduction comparable to paracetamol at the high-dose arm (6 g Andrographis dried herb per day, much higher than typical Western extract doses). In that trial of 152 adults, the 6 g dose and paracetamol both relieved fever and sore throat better than 3 g a day at day 3, but by day 7 the groups no longer differed; mild, self-limiting side effects occurred in about 20% of each group. Mechanism is presumed to be combined NF-kB-driven cytokine reduction at the pharyngeal mucosa plus possible local antibacterial activity against Streptococcus pyogenes.
- Cough — improved in the Hu 2017 meta-analysis (SMD −0.39 against placebo in 596 people), attributable to reduction in airway inflammation and possibly direct effects on cough-receptor sensitivity in the upper airway.
- Fatigue / malaise — the "flu feeling" of profound tiredness, body ache, and listlessness that often persists for days into convalescence. This is the symptom most directly driven by interleukin-1-beta and tumor necrosis factor-alpha, and is the symptom most reproducibly improved by NF-kB-inhibiting agents.
A 2023 phase III trial in India gave 300 adults with a common cold 200 or 400 mg a day of a standardized andrographis leaf extract, or placebo, for 7 days. Both doses lowered scores on the Wisconsin Upper Respiratory Symptom Survey compared with placebo on day 3, but not on days 5 and 7.
Less reproducibly improved symptoms include:
- Nasal congestion / rhinorrhea — modest improvement in some trials, no effect in others. Andrographis is not a decongestant in the pseudoephedrine sense, and a substantial reduction in nasal stuffiness on its own is not reported.
- Fever — mixed evidence; some trials show modest antipyretic effect, others none. Andrographis does not appear to be a robust antipyretic at typical doses.
- Ear pain (associated otitis media) — insufficient data for confident conclusions.
Doses and Timing Used in Trials and Practice
Practitioners describe Andrographis as working best when started at the very first symptomatic prodrome — the initial scratchy throat, mild headache, low-grade malaise, or vague body ache that precedes the full-blown URTI by 12-36 hours. In their experience, starting Andrographis on day 3 of a fully established illness produces less benefit, although there is no evidence that it does any harm at that point.
Doses described for adults with acute URTI:
- Standardized extract (4-10% total andrographolides): 400-600 mg three to four times daily, for a total daily dose of approximately 1,200-2,400 mg extract. This delivers roughly 60-120 mg total andrographolides per day, which is consistent with the doses used in positive clinical trials.
- Andrographis–eleuthero combination tablets: 4 tablets three times daily for the first 3 days, then 4 tablets twice daily for the remainder of the acute illness, typically 5-7 days total.
- Mono-Andrographis dried-herb capsules (non-standardized): 1,500-3,000 mg per day. Less precise because andrographolide content of the raw herb is variable.
- Tincture (1:5 in 40% alcohol): 2-5 mL three times daily.
Duration: 5-7 days, or 2-3 days past resolution of the major symptoms. Continuous prophylactic dosing for prevention of URTI has been studied in a couple of small trials, with mixed results — most clinicians use Andrographis acutely rather than chronically.
Taking with food modestly improves tolerability (the bitter taste is much less noticeable in capsule form, but some people experience mild gastric upset on an empty stomach). Splitting the dose across three or four daily intakes maintains a more even plasma andrographolide concentration than a single large bolus.
An Adult URTI Regimen Described by Practitioners
Integrative and herbal practitioners describe a regimen like the following for adults at the very first symptoms of a viral URTI. It is a practice description that combines separately studied agents, not a protocol tested as a whole in a trial:
- Day 1 (prodrome / first 12 hours) — Andrographis 600 mg standardized extract (4-10% andrographolides) four times daily. Zinc lozenges every 2-3 hours during waking hours (zinc acetate or zinc gluconate, 13-23 mg elemental zinc per lozenge). Vitamin C 1,000 mg every 4-6 hours. More rest, fluids and sleep.
- Days 2-4 — Andrographis continued at 600 mg three to four times daily, with zinc and vitamin C. Elderberry syrup (1 tablespoon three times daily) added when cough or congestion is prominent. Rest continued.
- Days 5-7 — Andrographis tapered to 600 mg twice daily as symptoms resolve; zinc and vitamin C continued until completely well; normal activity resumed gradually.
- Warning signs that need medical care — fever >102.5°F for more than 48 hours, shortness of breath, productive cough with purulent sputum lasting more than 7 days, sinus pain with facial swelling or vision changes, neck stiffness with high fever, severe headache, dehydration, age >65 with comorbidity. These are signs of possible bacterial superinfection, sinusitis, pneumonia, or other complications, which doctors treat as needing evaluation and which fall outside what the regimen above covers.
This regimen pairs Andrographis with the two other URTI agents that practitioners regard as having the strongest evidence (zinc lozenges and vitamin C) and elderberry as an optional addition for those with prominent cough or congestion. See our Vitamin C, Zinc, and Elderberry pages for the supporting evidence on each component.
Cautions and Contraindications
- Pregnancy — absolute contraindication. Andrographis has documented uterine-stimulant activity in animal models and is listed as contraindicated in pregnancy by the European Medicines Agency HMPC monograph, the Australia TGA, and traditional Ayurvedic and Thai pharmacopeias. These sources give no safe dose in pregnancy, and the warning is also applied to people attempting to conceive.
- Lactation — there is insufficient safety data on use while breastfeeding.
- Pediatric use — pediatric use covers children over 4 at age-adjusted doses (typically andrographis–eleuthero combination products specifically dosed for children). There is no safety data for infants and toddlers under 4.
- Anticoagulant interaction — Andrographis may modestly potentiate warfarin and other anticoagulants, which matters most for people on anticoagulation; practitioners describe stopping it 7 days before elective surgery.
- Hypotensive interaction — Andrographis modestly reduces blood pressure and may potentiate antihypertensive medications, so long-term use alongside them can lower blood pressure (BP) further.
- Immunosuppressant interaction — theoretically opposed to immunosuppressant action (e.g., post-transplant patients on tacrolimus, cyclosporine, mycophenolate); this theoretical concern applies to that population.
- Diabetes medications — andrographolide has mild glucose-lowering activity that may potentiate sulfonylureas or insulin, pushing blood glucose lower in people with diabetes who take them.
- Bitter taste and gastric upset — the most common nuisance side effects. People report fewer problems when it is taken with food, in capsules rather than tinctures, and divided across three or four daily intakes.
- Allergic reaction — rare but documented allergic skin rash and urticaria (hives), the usual signs of this reaction.
- Overall side-effect rates — a 2021 safety meta-analysis of 10 randomized trials and 3 intensive monitoring studies of Andrographis taken by mouth found serious adverse events very rare (0.02 per 1,000 patients in the trials) but non-serious ones very common (about 103 per 1,000 patients in the trials and 34 per 1,000 in the monitoring studies), mostly digestive and skin reactions.
- Headache — uncommon (5-10% in some trials), usually mild and transient.
- Australia TGA 2015 taste-disturbance warning — the Australian regulator issued a post-marketing warning about a small number of reports of altered or reduced taste sensation persisting for weeks to months after Andrographis use. The mechanism is unclear and the reports are uncommon, but the regulator now requires this warning on Australian Andrographis product labels.
Key Research Papers
- Coon JT, Ernst E (2004). Andrographis paniculata in the treatment of upper respiratory tract infections: a systematic review of safety and efficacy. Planta Medica 70(4):293-298. — PubMed PMID: 15095142
- Hu XY, Wu RH, Logue M, et al. (2017). Andrographis paniculata (Chuan Xin Lian) for symptomatic relief of acute respiratory tract infections in adults and children: a systematic review and meta-analysis. PLOS ONE 12(8):e0181780 (erratum 2018). — PubMed PMID: 28783743
- Caceres DD, Hancke JL, Burgos RA, Wikman GK (1999). Use of visual analogue scale measurements (VAS) to assess the effectiveness of standardized Andrographis paniculata extract SHA-10 in reducing the symptoms of common cold. Phytomedicine. — PubMed PMID: 10589439
- Melchior J, Spasov AA, Ostrovskij OV, et al. (2000). Double-blind, placebo-controlled pilot and phase III study of activity of standardized Andrographis paniculata Herba Nees extract fixed combination (Kan jang) in the treatment of uncomplicated upper-respiratory tract infection. Phytomedicine. — PubMed PMID: 11081985
- Thamlikitkul V, Dechatiwongse T, Theerapong S, et al. (1991). Efficacy of Andrographis paniculata, Nees for pharyngotonsillitis in adults. Journal of the Medical Association of Thailand. — PubMed PMID: 1797953
- Saxena RC, Singh R, Kumar P, et al. (2010). A randomized double blind placebo controlled clinical evaluation of extract of Andrographis paniculata (KalmCold) in patients with uncomplicated upper respiratory tract infection. Phytomedicine. — PubMed PMID: 20092985
- Cai W, Chen S, Li Y, Zhang A, Zhou H, Chen H, Jin M (2016). 14-Deoxy-11,12-didehydroandrographolide attenuates excessive inflammatory responses and protects mice lethally challenged with highly pathogenic A(H5N1) influenza viruses. Antiviral Research 133:95-105. — PubMed PMID: 27476045
- Xia YF, Ye BQ, Li YD, et al. (2004). Andrographolide attenuates inflammation by inhibition of NF-kappa B activation through covalent modification of reduced cysteine 62 of p50. Journal of Immunology. — PubMed PMID: 15356172
- Chen JX, Xue HJ, Ye WC, et al. (2009). Activity of andrographolide and its derivatives against influenza virus in vivo and in vitro. Biological & Pharmaceutical Bulletin. — PubMed PMID: 19652378
- Kulichenko LL, Kireyeva LV, Malyshkina EN, Wikman G (2003). A randomized, controlled study of Kan Jang versus amantadine in the treatment of influenza in Volgograd. Journal of Herbal Pharmacotherapy. — PubMed PMID: 15277072
- European Medicines Agency Committee on Herbal Medicinal Products (2014). Assessment report on Andrographis paniculata Nees, folium. — PubMed
- Worakunphanich W, Thavorncharoensap M, Youngkong S, Thadanipon K, Thakkinstian A (2021). Safety of Andrographis paniculata: a systematic review and meta-analysis. Pharmacoepidemiology and Drug Safety 30(6):727-739. — PubMed PMID: 33372366
- Raj JP, Maurya MR, Nair N, Marfatia H, Hadaye R, Gogtay NJ (2023). Efficacy and safety of AP-Bio (KalmCold) in participants with uncomplicated upper respiratory tract viral infection (common cold) – a phase III, double-blind, parallel group, randomized placebo-controlled trial. Complementary Therapies in Medicine 73:102934. — PubMed PMID: 36842634
- Ratiani L, Pachkoria E, Mamageishvili N, Shengelia R, Hovhannisyan A, Panossian A (2023). Efficacy of Kan Jang in patients with mild COVID-19: a randomized, quadruple-blind, placebo-controlled trial. Pharmaceuticals (Basel) 16(9):1196. — PubMed PMID: 37765004
- Siripongboonsitti T, Ungtrakul T, Tawinprai K, Auewarakul C, Chartisathian W, Jansala T, Julsawad R, Soonklang K, Mahanonda N, Mahidol C (2023). Efficacy of Andrographis paniculata extract treatment in mild to moderate COVID-19 patients being treated with favipiravir: a double-blind, randomized, placebo-controlled study (APFaVi trial). Phytomedicine 119:155018. — PubMed PMID: 37625206
- Jayakumar T, Hsieh CY, Lee JJ, Sheu JR (2013). Experimental and clinical pharmacology of Andrographis paniculata and its major bioactive phytoconstituent andrographolide. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 23634174