⚠ Evidence warning: Clinical trials or other evidence do not support the claim that Andrographis restores natural killer cell function, reduces how often recurrent sinus, herpes and Epstein-Barr infections come back, and improves psoriasis, ankylosing spondylitis and other autoimmune diseases. This page keeps it as a report of what people, websites or other media say.
Andrographis for Immune Modulation
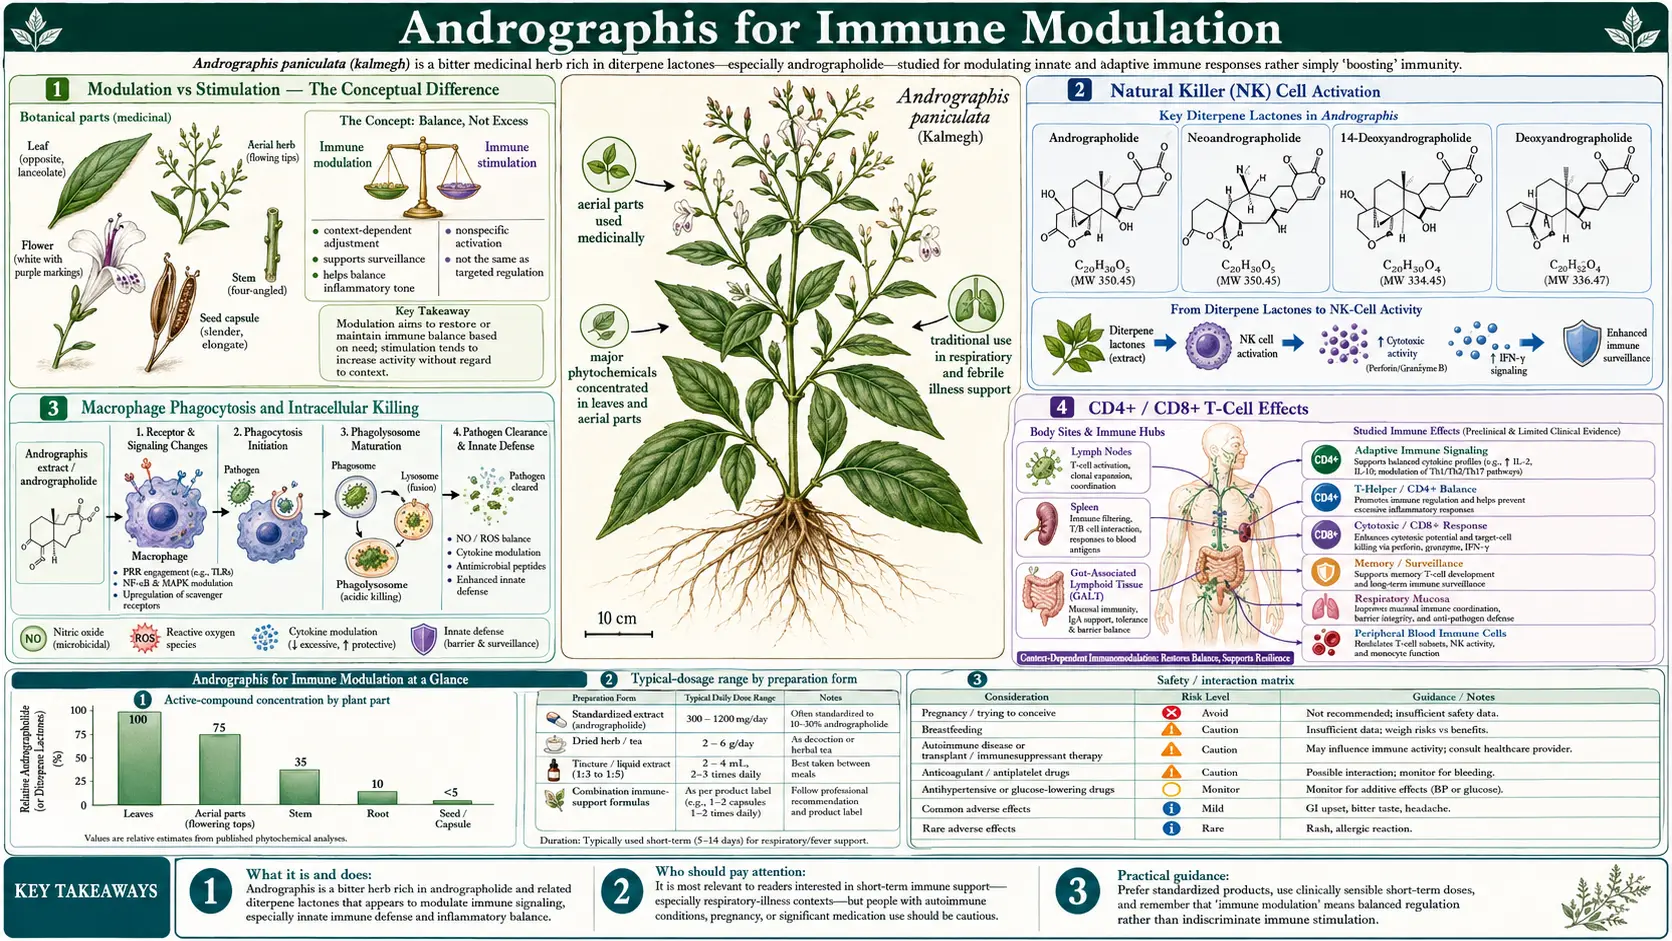
Andrographis is often grouped with classical "immune-stimulant" herbs like echinacea, astragalus, and elderberry, but the molecular reality is more interesting. Andrographolide simultaneously enhances the innate clearance arm of the immune response — activating natural killer (NK) cell cytotoxicity, increasing macrophage phagocytosis, and stimulating dendritic cell antigen presentation — while damping the adaptive cytokine surge that drives autoimmune over-activation. Its main test in a human immune-driven disease is ulcerative colitis. In a 2011 trial against mesalazine, clinical remission and response were seen in 21% and 76% of patients taking an Andrographis paniculata extract and in 16% and 82% of patients taking mesalazine, with no significant difference between the two groups (Tang 2011). In a 2013 placebo-controlled trial, only the 1,800 mg daily dose did better than placebo for clinical response (Sandborn 2013), and a 2024 meta-analysis found Andrographis no better than placebo for clinical response or remission (Iyengar 2024). This deep-dive walks through the molecular targets that underlie immunomodulation rather than immune stimulation, the cell-by-cell evidence from in-vitro and animal work, the ulcerative colitis trials in detail, and the practical applications for patients with autoimmune disease, recurrent infection, or both.
Table of Contents
- Modulation vs Stimulation — The Conceptual Difference
- Natural Killer (NK) Cell Activation
- Macrophage Phagocytosis and Intracellular Killing
- CD4+ / CD8+ T-Cell Effects
- Th1 / Th2 / Th17 Cytokine Balance
- The 2013 Ulcerative Colitis Placebo-Controlled Trial
- The 2011 Ulcerative Colitis Trial Against Mesalazine
- Other Autoimmune Applications
- Recurrent Infection and Adult Immune Restoration
- Cautions (Including Transplant and Immunosuppressant Interactions)
- Key Research Papers
- Connections
- Featured Videos
Modulation vs Stimulation — The Conceptual Difference
The popular framing of herbs as "immune boosters" obscures an important distinction. Crude immune stimulants (echinacea polysaccharides, some mushroom beta-glucans, bacterial cell-wall preparations) upregulate the entire inflammatory cascade non-selectively — useful when you need a sluggish immune system to mount any response at all, but actively counter-productive in autoimmune and chronic inflammatory disease where the problem is too much immune activation, not too little.
An immune modulator, by contrast, selectively pushes specific arms of the response while damping others. Andrographolide is the canonical example of this in the herbal pharmacopeia. It:
- Increases natural killer cell cytotoxicity and macrophage phagocytic activity (the innate clearance arm)
- Increases dendritic cell antigen presentation and maturation (the bridge between innate and adaptive immunity)
- Increases CD4+/CD8+ ratio toward more physiologic values in lymphopenic patients
- Inhibits nuclear factor kappa B (NF-kB)-driven excess tumor necrosis factor-alpha, interleukin-1-beta, interleukin-6 (IL-6) (the inflammatory cytokine surge that drives autoimmunity and tissue damage)
- Modulates the Th1/Th2/Th17 differentiation balance, pushing toward Th1 cytotoxicity in viral infection and toward regulatory T-cell (Treg) tolerance in autoimmune contexts
The combination is unusual. The closest pharmaceutical analog is probably abatacept (CTLA-4-Ig) — a designed biologic that selectively damps T-cell activation in rheumatoid arthritis without globally suppressing infection-fighting capacity. Andrographolide produces a more nuanced version of the same effect through a small natural-product molecule.
The clinical implication is that Andrographis is not contraindicated in autoimmune disease the way crude immune stimulants like echinacea sometimes are. In the 2013 placebo-controlled ulcerative colitis trial discussed below (Sandborn 2013), adverse events developed in 60 and 53% of patients on the 1,200 mg and 1,800 mg daily doses and in 60% of those on placebo.
Natural Killer (NK) Cell Activation
Natural killer cells are large granular lymphocytes that constitute the front line of innate cellular immunity. Unlike T cells, they do not require antigen-specific receptor priming — they recognize and lyse "missing-self" cells (cells that have downregulated their normal MHC-I expression as part of malignant transformation or viral infection) using germline-encoded activating receptors (NKG2D, NKp30, NKp46) balanced against inhibitory receptors (KIR family, NKG2A).
Natural killer cells matter clinically because they are the principal early defense against intracellular viral infection (herpes family, hepatitis, influenza) and the principal early defense against newly transformed tumor cells. Patients with natural killer cell deficiency syndromes have severe, often fatal, recurrent herpes virus infections and elevated cancer risk — powerful evidence of the day-to-day importance of natural killer function.
Andrographolide has been shown in multiple cell-culture and animal-model studies to:
- Increase natural killer cell direct cytotoxic activity against K562 erythroleukemia cells (the standard natural killer cytotoxicity assay) by 30-80% at clinically achievable concentrations
- Increase natural killer cell perforin and granzyme content (the cytolytic granule machinery)
- Upregulate NKG2D activating receptor expression
- Increase interferon-gamma production by activated natural killer cells
- Enhance antibody-dependent cellular cytotoxicity (ADCC) when combined with target-specific immunoglobulin G (IgG)
These natural killer findings come from cell-culture and animal studies; no human trial measuring natural killer function after Andrographis was found. The one trial in human immunodeficiency virus-positive patients (Calabrese 2000) measured CD4 counts and viral load, not natural killer cells. The laboratory findings are proposed as a candidate explanation for some of the observed protective effect against viral upper respiratory tract infection (URTI) — not just direct antiviral binding to the virus, but enhanced cellular clearance of infected cells.
Macrophage Phagocytosis and Intracellular Killing
Macrophages are the long-lived tissue-resident phagocytes that constitute the second front line of innate immunity (after the more nimble but shorter-lived neutrophil). Pulmonary alveolar macrophages, Kupffer cells in the liver, microglia in the brain, and osteoclasts in bone are all specialized macrophage populations performing site-specific defense and tissue-housekeeping functions. Macrophage function depends on two related capacities: phagocytosis (engulfment of particles, dying cells, and microbes) and intracellular killing (reactive oxygen species production via reduced nicotinamide adenine dinucleotide phosphate (NADPH) oxidase, nitric oxide production via inducible nitric oxide synthase (iNOS), lysosomal acidification and proteolysis).
Andrographolide effects on macrophages are dose- and context-dependent:
- Resting macrophages — modest stimulation of basal phagocytic activity, increased toll-like receptor (TLR) expression, increased baseline reactive-oxygen-species production
- Activated macrophages (responding to a real pathogen challenge) — enhanced phagocytic uptake of bacteria, enhanced intracellular killing of internalized pathogens, increased macrophage-derived antimicrobial peptide production
- Hyperactivated macrophages (the "M1 storm" that drives sepsis and cytokine storm) — suppression of excess tumor necrosis factor-alpha and interleukin-6 release, conversion toward a more controlled phenotype that retains phagocytosis without driving organ injury
This dose-and-context-dependent profile is the essence of immunomodulation rather than immunostimulation. The herb increases macrophage clearance function when challenged but does not provoke a futile inflammatory storm when there is no pathogen to engage.
CD4+ / CD8+ T-Cell Effects
The ratio of CD4+ helper T cells to CD8+ cytotoxic T cells in peripheral blood is one of the most useful crude measures of cellular immunity. A normal CD4/CD8 ratio is roughly 1.5-2.5. Ratios below 1.0 (CD4 lymphopenia) indicate compromised cellular immunity, classically seen in advanced human immunodeficiency virus (HIV), chemotherapy, post-organ-transplant, malnutrition, and chronic stress. Ratios above 4.0 (CD8 lymphopenia) can indicate autoimmune disease, chronic viral infection, or immunosenescence.
The one human immunodeficiency virus (HIV) trial found is a 2000 phase I dose-escalating trial of andrographolide in 13 HIV-positive patients and five HIV-uninfected healthy volunteers (Calabrese 2000). No subjects used antiretroviral medications during the trial. The mean CD4 count of the HIV-positive patients rose from a baseline of 405 cells/mm3 to 501 cells/mm3 (p = 0.002) after 10 mg/kg andrographolide, while there were no statistically significant changes in plasma HIV-1 RNA (viral load). No CD4/CD8 ratio result is reported. The trial was interrupted at 6 weeks due to adverse events, including an anaphylactic reaction (a severe allergic reaction) in one patient; all adverse events had resolved by the end of observation. The effects were small relative to combination antiretroviral therapy (which can fully reconstitute CD4 counts), and the trial did not test Andrographis as a replacement for that therapy.
In immunocompetent adults with no underlying lymphocyte abnormality, Andrographis does not appreciably change baseline CD4/CD8 ratios. This is again characteristic of true immunomodulation — the herb pushes the system toward normal where there is abnormality but does not perturb a healthy steady-state.
Th1 / Th2 / Th17 Cytokine Balance
Beyond simple CD4 quantitation, the functional subtype of CD4+ T cells matters enormously. Naive CD4+ T cells encountering antigen differentiate down one of several distinct paths based on local cytokine milieu:
- Th1 (driven by IL-12, IFN-gamma) — cellular immunity, intracellular pathogen defense, antitumor activity
- Th2 (driven by IL-4, IL-13) — humoral immunity, parasite defense, allergic reaction
- Th17 (driven by IL-23, TGF-beta, interleukin-6) — mucosal defense against extracellular bacteria and fungi, autoimmune driver when chronic and unbalanced
- Treg (driven by TGF-beta, IL-2 in absence of interleukin-6) — immune tolerance, regulation, prevention of autoimmunity
Andrographolide tilts the differentiation balance in context-specific ways. In viral infection (where Th1 is the desired phenotype for intracellular pathogen clearance), andrographolide enhances Th1 differentiation. In allergic and parasitic contexts where excess Th2 drives pathology, andrographolide modestly suppresses Th2 cytokines. In autoimmune contexts where Th17 drives tissue damage (rheumatoid arthritis, psoriasis, multiple sclerosis, inflammatory bowel disease), andrographolide preferentially suppresses Th17 differentiation while supporting Treg expansion. The molecular mechanism involves inhibition of signal transducer and activator of transcription 3 (STAT3) phosphorylation (a key Th17 transcription factor) and of NF-kB-driven interleukin-6 production (a key Th17-polarizing cytokine).
This Th17-suppressing, Treg-supporting profile is the molecular underpinning of Andrographis efficacy in autoimmune disease and is shared with several pharmaceutical agents for the same indications — including the IL-17 antagonists secukinumab and ixekizumab (approved for psoriasis, ankylosing spondylitis, psoriatic arthritis), the IL-23 antagonists guselkumab and risankizumab, and the JAK inhibitors tofacitinib and upadacitinib. Andrographolide is a small natural-product molecule reaching similar therapeutic territory by a different route.
The 2013 Ulcerative Colitis Placebo-Controlled Trial
The largest placebo-controlled test of Andrographis in a human immune-driven disease is the 2013 randomized, double-blind, placebo-controlled trial by Sandborn and colleagues of an Andrographis paniculata extract in adults with mild-to-moderate ulcerative colitis (Sandborn 2013). The trial enrolled 224 adults at 52 centers in 5 countries (United States, Canada, Germany, Romania, and Ukraine), randomizing them to:
- Andrographis paniculata extract 1,200 mg daily for 8 weeks, OR
- Andrographis paniculata extract 1,800 mg daily for 8 weeks, OR
- Placebo for 8 weeks
The primary outcome was clinical response (reduction in modified Mayo Clinic disease activity score) at week 8. Secondary outcomes included clinical remission (Mayo score ≤2 with no individual subscore >1), and mucosal healing on colonoscopy or flexible sigmoidoscopy.
Results:
- Clinical response at week 8: 45% in the 1,200 mg arm and 60% in the 1,800 mg arm versus 40% on placebo (P=0.5924 for 1,200 mg vs. placebo and P=0.0183 for 1,800 mg vs. placebo) — only the 1,800 mg dose was statistically significant
- Clinical remission at week 8: 34% in the 1,200 mg arm and 38% in the 1,800 mg arm versus 25% on placebo (P=0.2582 and P=0.1011) — neither dose was statistically significant
- Mucosal healing at week 8: 50.0% on 1,800 mg (P=0.0404) and 37.8% on 1,200 mg (P=0.5821) versus 33.3% on placebo; for the two doses combined, 43.9% versus 33.3% (P=0.1309, not significant)
- Adverse events developed in 60% and 53% of patients in the 1,200 mg and 1,800 mg groups and in 60% of the placebo group
- The authors reported a dose response: the rate of mucosal healing for the 1,800 mg dose was significantly greater than placebo, whereas the 1,200 mg dose was not
A 2024 systematic review and meta-analysis of 28 randomized controlled trials covering 18 herbs for active ulcerative colitis pooled the Andrographis paniculata trials (Iyengar 2024). Compared with placebo, Andrographis did not give a significantly higher rate of clinical response (relative risk, RR 0.95, 95% CI 0.71-1.26) or clinical remission (RR 1.31, 95% CI 0.86-2.01).
It is worth noting that the trial extract is an andrographolide-enriched extract more concentrated than typical over-the-counter Andrographis products. Its 1,200 mg daily dose corresponds to a much higher andrographolide intake than would be achieved with the same milligram dose of standard 4-10%-standardized extract. The trials tested this one extract; how retail products, including those labelled 10% or higher total andrographolides, compare with it has not been tested.
The 2011 Ulcerative Colitis Trial Against Mesalazine
The same Andrographis paniculata extract was also compared head to head with mesalazine (Tang 2011). In a randomised, double-blind, multicentre, 8-week study, 120 patients with mild-to-moderately active ulcerative colitis at five centres in China took the extract at 1200 mg/day or slow-release mesalazine (mesalamine) granules at 4500 mg/day. Clinical remission and response were seen in 21% and 76% of patients on the extract and in 16% and 82% of patients on mesalazine. By colonoscopy, remission and response were seen in 28% and 74% of the extract group and 24% and 71% of the mesalazine group. There was no significant difference between the two treatment groups. The trial had no placebo group.
Other Autoimmune Applications
Beyond the well-documented ulcerative colitis application, Andrographis has been investigated in several other autoimmune-spectrum diseases with varying levels of evidence:
- Rheumatoid arthritis — the Burgos 2009 rheumatoid arthritis (RA) trial gave 60 patients with active RA tablets of an Andrographis paniculata extract (30% total andrographolides) three times a day for 14 weeks, or placebo. Joint pain, the main outcome, fell more in the Andrographis group than on placebo at the end of treatment, but the difference was not statistically significant. Tender and swollen joint counts and health questionnaire scores (HAQ and SF36) improved significantly within the Andrographis group (a before-and-after change in that group, not a difference from placebo), together with a reduction of rheumatoid factor, IgA and C4. See the Anti-Inflammatory page for further detail.
- Psoriasis — small open-label trials and case series report topical or oral Andrographis improving plaque psoriasis severity. The Th17 suppression mechanism is mechanistically aligned with the IL-17 antagonist therapeutic strategy now standard for moderate-to-severe psoriasis.
- Multiple sclerosis — animal-model evidence (experimental autoimmune encephalomyelitis, EAE) shows andrographolide attenuating disease severity. Human trials are sparse and small; the evidence for use in multiple sclerosis (MS) is thin.
- Ankylosing spondylitis — isolated case reports and one small trial suggesting symptom improvement. The evidence is thin.
- Crohn's disease — smaller trial database than ulcerative colitis. Mechanism is analogous and benefit is plausible, but high-quality randomized controlled trial (RCT) evidence is lacking.
- Lupus — animal-model evidence suggesting attenuation. No quality human trials, and no safety data in people with lupus.
For autoimmune disease applications generally, practitioners describe Andrographis as an adjunct to (not a replacement for) conventional disease-modifying therapy: a role in day-to-day inflammation control, while the conventional disease-modifying antirheumatic drugs (DMARDs) handle long-term prevention of disease progression.
Recurrent Infection and Adult Immune Restoration
The other side of the immunomodulation coin is patients with recurrent infection that does not respond well to crude immune stimulants. This includes adults with:
- Recurrent sinopulmonary infection (typically 4-8 URTI per year, often with secondary bacterial superinfection)
- Recurrent herpes simplex (oral or genital) reactivation
- Recurrent herpes zoster (shingles)
- Recurrent Epstein-Barr virus reactivation with chronic fatigue picture
- Post-viral fatigue syndrome / long-COVID-like syndromes (caution: no high-quality data here)
For these patients, practitioners describe a course of Andrographis (typically 600-1,200 mg standardized extract daily for 6-12 weeks) as restoring natural killer function, modestly reducing infection frequency, and improving subjective energy and stamina. No human trial testing these outcomes was found; the proposed mechanism (natural killer and macrophage clearance enhancement combined with downregulation of chronic inflammatory cytokines) comes from laboratory and animal work.
For patients with frank lymphocyte deficiencies or chronic viral infection requiring antiviral therapy, Andrographis is supportive rather than primary — the underlying condition needs separate management.
Cautions (Including Transplant and Immunosuppressant Interactions)
- Pregnancy — absolute contraindication. Uterine-stimulant activity, abortifacient potential in animal studies, listed as contraindicated by every major regulatory body. Reiterated on every Andrographis page.
- Solid organ transplant recipients on immunosuppression — a theoretical concern: its immune-restoring activity may oppose the deliberate immunosuppression required to prevent graft rejection. Includes patients on tacrolimus, cyclosporine, mycophenolate, sirolimus, prednisone for transplant maintenance. No interaction study in transplant recipients was found.
- Autoimmune patients on biologic anti-TNF therapy (infliximab, adalimumab, etanercept, golimumab, certolizumab) — theoretical concern about additive immunosuppression. The mechanistic profile is somewhat complementary rather than redundant, but the combination has not been adequately studied.
- Autoimmune patients on conventional DMARDs (methotrexate, sulfasalazine, hydroxychloroquine, leflunomide) — Andrographis is described as mechanistically complementary. The ulcerative colitis and rheumatoid arthritis trial reports cited on this page give no safety data for combining it with these drugs.
- Hematologic malignancy or active cancer therapy — complex. Andrographolide has documented anticancer activity in cell-culture and animal models but pharmacokinetic interactions with chemotherapy drugs are largely unstudied, including during active chemotherapy.
- Anticoagulant interaction — the one warfarin study found was in rats (Hovhannisyan 2006): a fixed combination of Andrographis paniculata and Eleutherococcus senticosus extracts, at a daily andrographolide dose some 17-fold higher than that recommended for humans, did not produce significant effects on the pharmacokinetics of warfarin, and practically no effect on its pharmacodynamics. No human interaction data was found.
- Pediatric autoimmune disease — safety in pediatric autoimmune populations not well established.
- Allergic reactions — Thailand's national drug-safety database (February 2001 to December 2012) held 106 case reports that named an Andrographis product as the only suspected cause and described a hypersensitivity (allergic) reaction. Thirteen were critical: anaphylactic shock (n = 5), anaphylactic reaction (n = 4) and angioedema (n = 4). Symptoms began 5 minutes to 1 day after use, at doses of 352 mg to 1,750 mg (Suwankesawong 2014).
- Injected andrographolide medicines — a 2022 systematic review of 262 clinical studies (Shang 2022) found that of 9490 participants using andrographolide derivative injections, 383 (4.04%) reported adverse drug reactions, mainly gastrointestinal (stomach and gut), skin and anaphylaxis; fifty-five patients experienced life-threatening anaphylactic shock and three patients died. Nine herbal preparations of Andrographis paniculata, tested in 10 studies, caused mainly mild to moderate gastrointestinal and skin reactions.
- Bitter taste and gastric upset — standard tolerability issues, manageable with capsule form, food, and divided dosing.
Key Research Papers
- Burgos RA, Hancke JL, Bertoglio JC, et al. (2009). Efficacy of an Andrographis paniculata composition for the relief of rheumatoid arthritis symptoms: a prospective randomized placebo-controlled trial. Clinical Rheumatology. — PubMed PMID: 19408036
- Sandborn WJ, Targan SR, Byers VS, et al. (2013). Andrographis paniculata extract (HMPL-004) for active ulcerative colitis. American Journal of Gastroenterology. — PubMed PMID: 23044768
- Tang T, Targan SR, Li ZS, et al. (2011). Randomised clinical trial: herbal extract HMPL-004 in active ulcerative colitis — a double-blind comparison with sustained-release mesalazine. Alimentary Pharmacology & Therapeutics. — PubMed PMID: 21114791
- Iruretagoyena MI, Tobar JA, Gonzalez PA, et al. (2005). Andrographolide interferes with T cell activation and reduces experimental autoimmune encephalomyelitis in the mouse. Journal of Pharmacology and Experimental Therapeutics. — PubMed PMID: 15331658
- Kumar RA, Sridevi K, Kumar NV, et al. (2004). Anticancer and immunostimulatory compounds from Andrographis paniculata. Journal of Ethnopharmacology. — PubMed PMID: 15138014
- Sheeja K, Kuttan G (2007). Activation of cytotoxic T lymphocyte responses and attenuation of tumor growth in vivo by Andrographis paniculata extract and andrographolide. Immunopharmacology and Immunotoxicology. — PubMed PMID: 17464769
- Wang T, Liu B, Zhang W, et al. (2004). Andrographolide reduces inflammation-mediated dopaminergic neurodegeneration in mesencephalic neuron-glia cultures by inhibiting microglial activation. Journal of Pharmacology and Experimental Therapeutics. — PubMed PMID: 14718612
- Carretta MD, Alarcon P, Jara E, et al. (2009). Andrographolide reduces IL-2 production in T-cells by interfering with NFAT and MAPK activation. European Journal of Pharmacology. — PubMed PMID: 19038244
- Hidalgo MA, Hancke JL, Bertoglio JC, Burgos RA (2013). Andrographolide a new potential drug for the long term treatment of rheumatoid arthritis disease. Innovative Rheumatology. — PubMed
- Calabrese C, Berman SH, Babish JG, et al. (2000). A phase I trial of andrographolide in HIV positive patients and normal volunteers. Phytotherapy Research. — PubMed PMID: 10925397
- Kumar S, Singh B, Bajpai V (2021). Andrographis paniculata (Burm. f.) Nees: traditional uses, phytochemistry, pharmacological properties and quality control / quality assurance. Journal of Ethnopharmacology. — PubMed PMID: 33831465
- Mussard E, Cesaro A, Lespessailles E, et al. (2019). Andrographolide, a natural antioxidant: an update. Antioxidants. — PubMed PMID: 31756965
- Iyengar P, Godoy-Brewer G, Maniyar I, et al. (2024). Herbal Medicines for the Treatment of Active Ulcerative Colitis: A Systematic Review and Meta-Analysis. Nutrients. — PubMed PMID: 38612967
- Hovhannisyan AS, Abrahamyan H, Gabrielyan ES, Panossian AG (2006). The effect of Kan Jang extract on the pharmacokinetics and pharmacodynamics of warfarin in rats. Phytomedicine. — PubMed PMID: 16635739
- Suwankesawong W, Saokaew S, Permsuwan U, Chaiyakunapruk N (2014). Characterization of hypersensitivity reactions reported among Andrographis paniculata users in Thailand using Health Product Vigilance Center (HPVC) database. BMC Complementary and Alternative Medicine. — PubMed PMID: 25539642
- Shang YX, Shen C, Stub T, et al. (2022). Adverse Effects of Andrographolide Derivative Medications Compared to the Safe use of Herbal Preparations of Andrographis paniculata: Results of a Systematic Review and Meta-Analysis of Clinical Studies. Frontiers in Pharmacology. — PubMed PMID: 35153776