Aloe Vera for Skin and Wound Healing
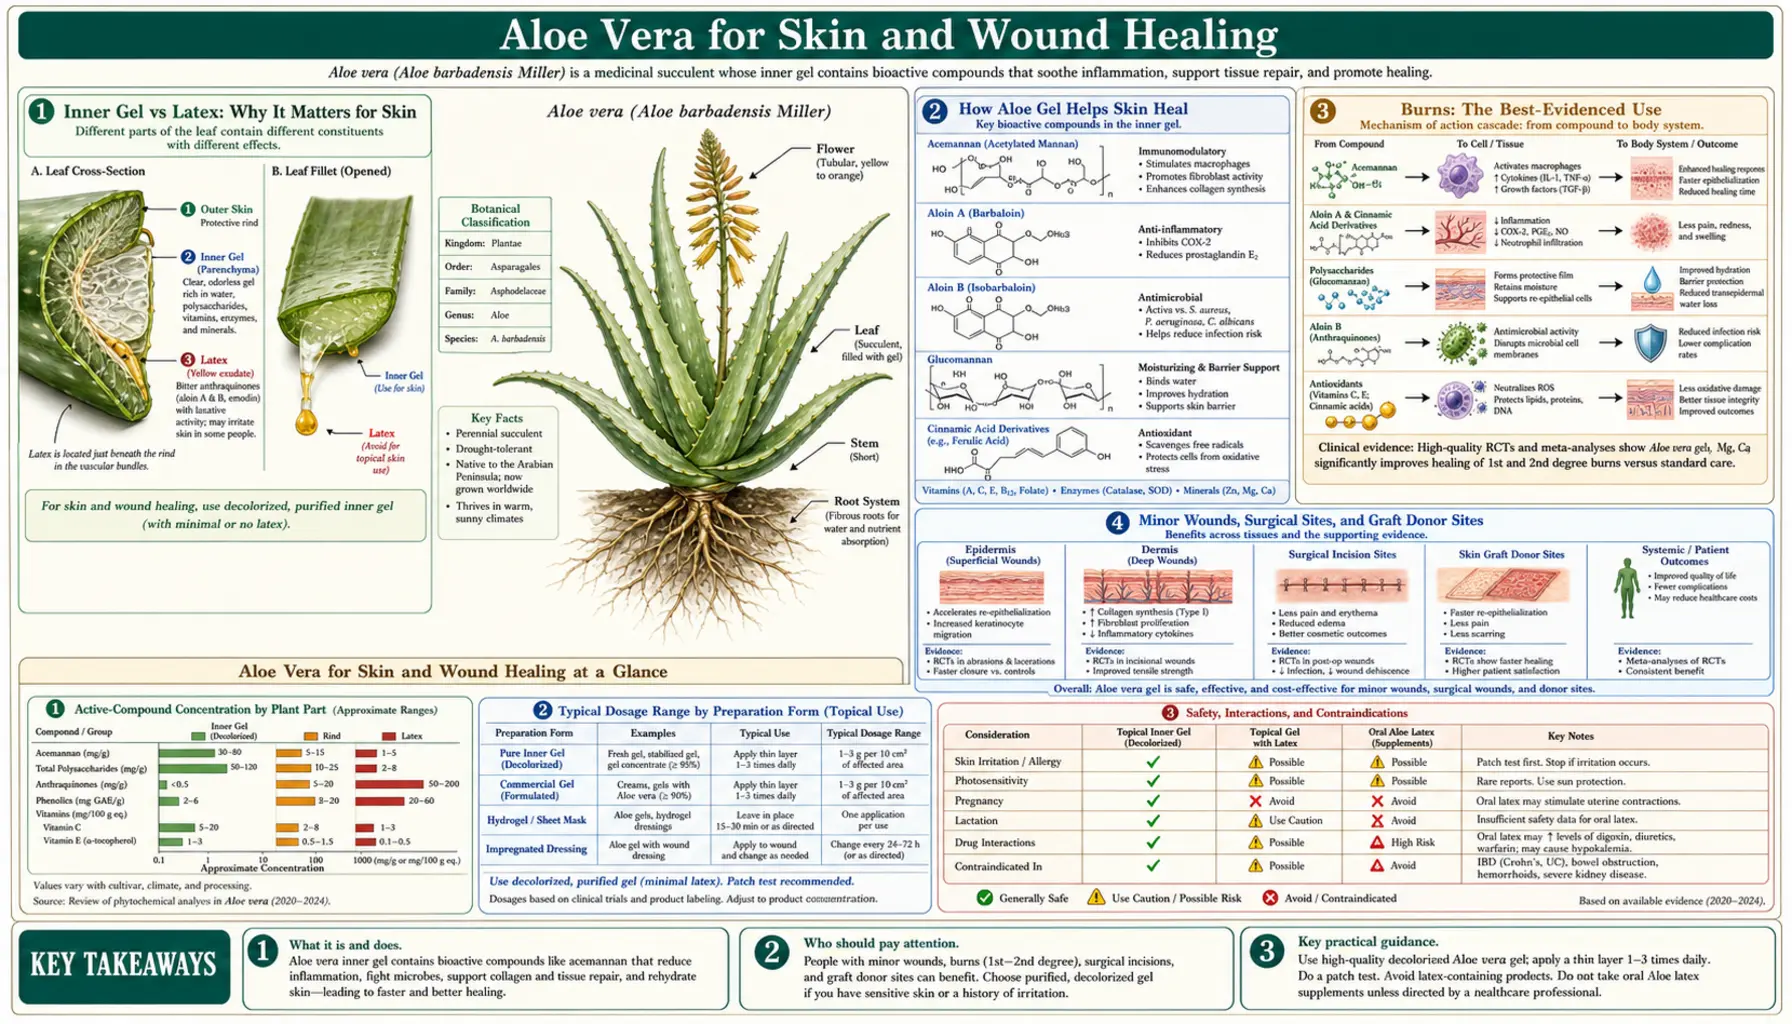
Topical aloe gel is the single best-evidenced use of the plant. For centuries the clear inner-leaf gel has been smeared on burns, cuts, and irritated skin, and modern trials give that tradition real — if modest — support: several meta-analyses of small randomized studies report that aloe shortens the healing time of superficial and partial-thickness burns compared with some standard dressings. The gel works through simple, well-understood physiology (a moist wound environment plus polysaccharides that nudge skin cells to divide) rather than anything miraculous. This page walks through what the evidence supports, what it does not, and how to use aloe on skin safely.
Table of Contents
- Inner Gel vs Latex: Why It Matters for Skin
- How Aloe Gel Helps Skin Heal
- Burns: The Best-Evidenced Use
- Minor Wounds, Surgical Sites, and Graft Donor Sites
- Psoriasis and Seborrheic Dermatitis
- Radiation Dermatitis (An Honest Look)
- Pressure Ulcers (Bedsores)
- Sunburn, Frostbite, Herpes, Acne, Dry Skin
- How to Choose and Use Aloe on Skin
- Cautions and Allergy
- Key Research Papers
- Connections
- Featured Videos
Inner Gel vs Latex: Why It Matters for Skin
For skin, the part used is the clear inner-leaf gel — the slippery, nearly odorless material in the center of the leaf. The bitter yellow latex that seeps from just under the green rind is a different material: it is an anthraquinone-rich stimulant laxative meant for the gut, and on the skin it offers no wound-healing advantage while adding the risk of irritation. When a fresh leaf is filleted at home, the usual practice is to let the cut leaf drain the yellow sap for a few minutes and to rinse the gel before applying it. Commercial products intended for skin are made from the inner gel, but cheaper "whole-leaf" preparations can carry latex residue, which purified or decolorized products have removed.
How Aloe Gel Helps Skin Heal
Aloe's skin effects come from several overlapping mechanisms, none of them mystical:
- Moist wound healing. Because the gel is about 99% water held in a polysaccharide matrix, it keeps a superficial wound bed moist and covered. Decades of wound science show that keratinocytes re-surface a moist wound faster than a dry, scabbed one — much of aloe's benefit on minor burns and abrasions is this straightforward occlusive-hydration effect.
- Acemannan and fibroblast stimulation. The signature polysaccharide acemannan (an acetylated mannan) has been shown in cell and animal studies to activate macrophages, stimulate fibroblast proliferation, and increase collagen synthesis and growth-factor expression (including keratinocyte growth factor and vascular endothelial growth factor).
- Anti-inflammatory activity. Aloe compounds inhibit cyclooxygenase and reduce prostaglandin E2 and thromboxane, dampening the redness, swelling, and pain of minor skin injury.
- Mild antimicrobial and cooling effects. Aloe has modest in-vitro activity against some bacteria and fungi, and the cool, evaporating gel provides genuine symptomatic relief from the sting of sunburn even where it does not measurably speed healing.
An important caveat: much of the fibroblast and growth-factor evidence comes from laboratory and animal models. The human clinical benefit is real for minor burns but is smaller and less certain than the mechanistic enthusiasm sometimes implies.
Burns: The Best-Evidenced Use
Burns are where aloe's evidence is strongest. An influential 2007 systematic review by Maenthaisong and colleagues pooled four controlled trials and estimated that aloe shortened the healing time of first- and second-degree burns by roughly nine days compared with control dressings. More recent analyses — including a 2024 meta-analysis of nine randomized trials in the Journal of Burn Care & Research (healing about 3.8 days faster than with other topical agents) and a 2022 analysis comparing aloe with silver sulfadiazine that pooled eight studies, mostly cohort studies and including animal studies — have broadly agreed that aloe is associated with faster healing of superficial and partial-thickness burns, and is at least comparable to silver sulfadiazine, a standard topical burn agent.
The honest qualifiers matter. These trials are small, use different aloe preparations, and carry a high risk of bias (blinding is hard when one dressing is obviously aloe). The benefit applies to superficial and superficial partial-thickness burns — the kind that are painful and red but not deep. Aloe is not a treatment for deep partial-thickness or full-thickness burns, large burns, chemical or electrical burns, or any burn involving the face, hands, feet, genitals, or a major joint. Those need professional medical care. For a small kitchen or sun burn, the home approach consistent with this evidence is cool running water first, then a layer of pure aloe gel.
Minor Wounds, Surgical Sites, and Graft Donor Sites
For everyday cuts and scrapes, aloe provides the same moist-healing and soothing benefits as for minor burns. For chronic wounds (pressure ulcers, venous leg ulcers, diabetic foot ulcers), the evidence is weaker: a 2012 Cochrane review by Dat and colleagues concluded there was insufficient evidence to determine whether aloe improves healing of acute or chronic wounds, largely because the available trials were few and poor quality.
One well-designed 2018 randomized controlled trial found that aloe gel accelerated healing of split-thickness skin-graft donor sites compared with conventional dressing. Interestingly, the picture is not uniformly positive: a frequently cited study of surgical wounds healing by primary intention after caesarean section and laparotomy actually found delayed healing with aloe, a reminder that a moist, occlusive gel is not always appropriate for a clean, sutured surgical incision. On this evidence, aloe's use is on superficial open wounds rather than closed surgical wounds.
Psoriasis and Seborrheic Dermatitis
Aloe has been studied as a topical for plaque psoriasis with genuinely mixed results. A small 1996 placebo-controlled trial by Syed and colleagues reported that an aloe hydrophilic cream cleared plaques in a large majority of patients, a striking result that generated enthusiasm. A 2010 randomized trial by Choonhakarn and colleagues compared aloe vera cream with 0.1% triamcinolone acetonide, a topical corticosteroid, in 80 people with mild to moderate plaque psoriasis for 8 weeks: the psoriasis severity score (PASI) fell by 7.7 points with aloe and 6.6 with triamcinolone, a small difference in favor of aloe, and quality of life improved similarly in both groups. The trials are small and limited to mild to moderate disease. It has also been used for seborrheic dermatitis with limited supporting data. For the underlying condition, see our Psoriasis page.
Radiation Dermatitis (An Honest Look)
Aloe is one of the most commonly tried remedies for the skin reaction that develops during radiotherapy. A 2022 systematic review and cumulative analysis of 14 randomized trials (1,572 participants) found that people who used aloe preventively had a significantly lower risk of radiation-induced dermatitis than those who did not (relative risk 0.76), with larger reductions for grade 2 and grade 3 reactions. The trials differed a great deal from one another, and the authors called for larger multicenter trials to confirm the finding. A self-controlled clinical trial also reported some benefit. Radiation-oncology teams give their own skin-care guidance to patients during radiotherapy.
Pressure Ulcers (Bedsores)
A small 2018 triple-blind randomized trial in orthopedic patients reported that applying aloe gel to pressure points reduced the incidence of pressure ulcers, and a few other single-center trials have compared aloe with olive oil or standard care for prevention. The signal is encouraging but the trials are small and not independently replicated at scale, so the evidence places aloe as a possible adjunct to — not a replacement for — proven pressure-ulcer prevention (repositioning, pressure-redistributing surfaces, skin care, nutrition).
Sunburn, Frostbite, Herpes, Acne, Dry Skin
- Sunburn. Aloe's cooling, anti-inflammatory gel provides real symptomatic relief. Evidence that it speeds recovery of the sunburn itself is weak, but comfort is a legitimate goal.
- Frostbite. Topical aloe has been used in frostbite protocols as an anti-prostaglandin agent to limit tissue loss; evidence is limited and it is only ever an adjunct to rewarming and medical care.
- Genital and cold-sore herpes. Small trials of aloe cream for genital herpes lesions reported faster healing, but the data are old and thin.
- Acne. Aloe has mild antibacterial and anti-inflammatory effects and is sometimes combined with tretinoin; on its own it is a weak acne treatment. See our Acne page.
- Dry skin and eczema. As a light, water-based moisturizer aloe can soothe dry or itchy skin, though heavier emollients are usually better for eczema. See our Eczema page.
How to Choose and Use Aloe on Skin
- A clean gel. Fresh inner-leaf gel from a filleted leaf, or a commercial gel with a high aloe percentage and minimal additives. On wounds, products with added alcohol, fragrance, or color can sting and irritate.
- Preparing the skin. A burn is usually cooled under running water for several minutes first, and a wound gently cleaned. The gel is typically applied as a thin layer two to three times a day.
- Patch test. A patch test means dabbing a small amount on the inner forearm and waiting 24 hours before wider use; it matters most for people with plant allergies.
- The limits. Aloe is not sole care for deep, large, infected, or full-thickness burns, or for closed surgical incisions. A wound that is spreading, weeping pus, or not improving is a sign of infection or poor healing that needs medical treatment.
Cautions and Allergy
- Allergic contact dermatitis. Aloe belongs to the same broad plant grouping (Liliaceae / Asphodelaceae) as garlic, onion, and tulip; people sensitive to these can react to aloe with redness, itching, or rash; irritation after applying it is a sign of such a reaction.
- Surgical wounds. As noted, aloe may delay healing of clean sutured incisions; the evidence for benefit is on open superficial wounds, not closed ones.
- Gel, not latex. Skin products are made from inner-leaf gel; the yellow latex adds irritation risk without benefit.
- No substitute for medical care. Serious burns and non-healing wounds need professional evaluation.
Key Research Papers
- Maenthaisong R, Chaiyakunapruk N, Niruntraporn S, Kongkaew C (2007). The efficacy of aloe vera used for burn wound healing: a systematic review. Burns — PubMed PMID: 17499928
- Huang YN, Chen KC, Wang JH, Lin YK (2024). Effects of Aloe vera on burn injuries: a systematic review and meta-analysis of randomized controlled trials. J Burn Care Res — PubMed PMID: 38605441
- Sharma S, Alfonso AR, Gordon AJ, et al. (2022). Second-degree burns and aloe vera: a meta-analysis and systematic review. Adv Skin Wound Care — PubMed PMID: 36264753
- Levin NJ, Erben Y, et al. (2022). A systematic review and meta-analysis comparing burn healing outcomes between silver sulfadiazine and aloe vera. Cureus — PubMed PMID: 36337821
- Dat AD, Poon F, Pham KB, Doust J (2012). Aloe vera for treating acute and chronic wounds. Cochrane Database Syst Rev — PubMed PMID: 22336851
- Burusapat C, Supawan M, et al. (2018). Topical aloe vera gel for accelerated wound healing of split-thickness skin graft donor sites: a double-blind, randomized, controlled trial and systematic review. Plast Reconstr Surg — PubMed PMID: 29649056
- Syed TA, Ahmad SA, Holt AH, et al. (1996). Management of psoriasis with Aloe vera extract in a hydrophilic cream: a placebo-controlled, double-blind study. Trop Med Int Health — PubMed PMID: 8765459
- Choonhakarn C, Busaracome P, Sripanidkulchai B, Sarakarn P (2010). A prospective, randomized clinical trial comparing topical aloe vera with 0.1% triamcinolone acetonide in mild to moderate plaque psoriasis. J Eur Acad Dermatol Venereol — PubMed PMID: 19686327
- Vogler BK, Ernst E (1999). Aloe vera: a systematic review of its clinical effectiveness. Br J Gen Pract — PubMed PMID: 10885091
- Wang T, Liao J, Zheng L, Zhou Y, Jin Q, Wu Y (2022). Aloe vera for prevention of radiation-induced dermatitis: a systematic review and cumulative analysis of randomized controlled trials. Front Pharmacol — PubMed PMID: 36249738
- Hekmatpou D, Mehrabi F, Rahzani K, Aminiyan A (2018). The effect of aloe vera gel on prevention of pressure ulcers in patients hospitalized in the orthopedic wards: a randomized triple-blind clinical trial. BMC Complement Altern Med — PubMed PMID: 30268162
- Xing W, Guo W, et al. (2015). Acemannan accelerates cell proliferation and skin wound healing through AKT/mTOR signaling pathway. J Dermatol Sci — PubMed PMID: 26049685
- Jettanacheawchankit S, Sasithanasate S, et al. (2009). Acemannan stimulates gingival fibroblast proliferation; expressions of keratinocyte growth factor-1, vascular endothelial growth factor, and type I collagen; and wound healing. J Pharmacol Sci — PubMed PMID: 19372635