⚠ Evidence warning: Clinical trials or other evidence do not support the claims that tulsi lowers blood sugar in the range of metformin or sulfonylureas, with effects that grow with longer use and have been replicated across studies, that it sensitizes tissues to insulin rather than raising insulin secretion, that tulsi with neem works better than either alone, that it is an established adjunct in early type 2 diabetes and a useful alternative for people who cannot tolerate metformin, that it avoids the beta-cell and weight effects of sulfonylureas, and that its safety is excellent, with no additive hypoglycemia alongside metformin and an established upper dose for safe chronic use. This page keeps it as a report of what people, websites or other media say.
Holy Basil for Blood Sugar and Diabetes
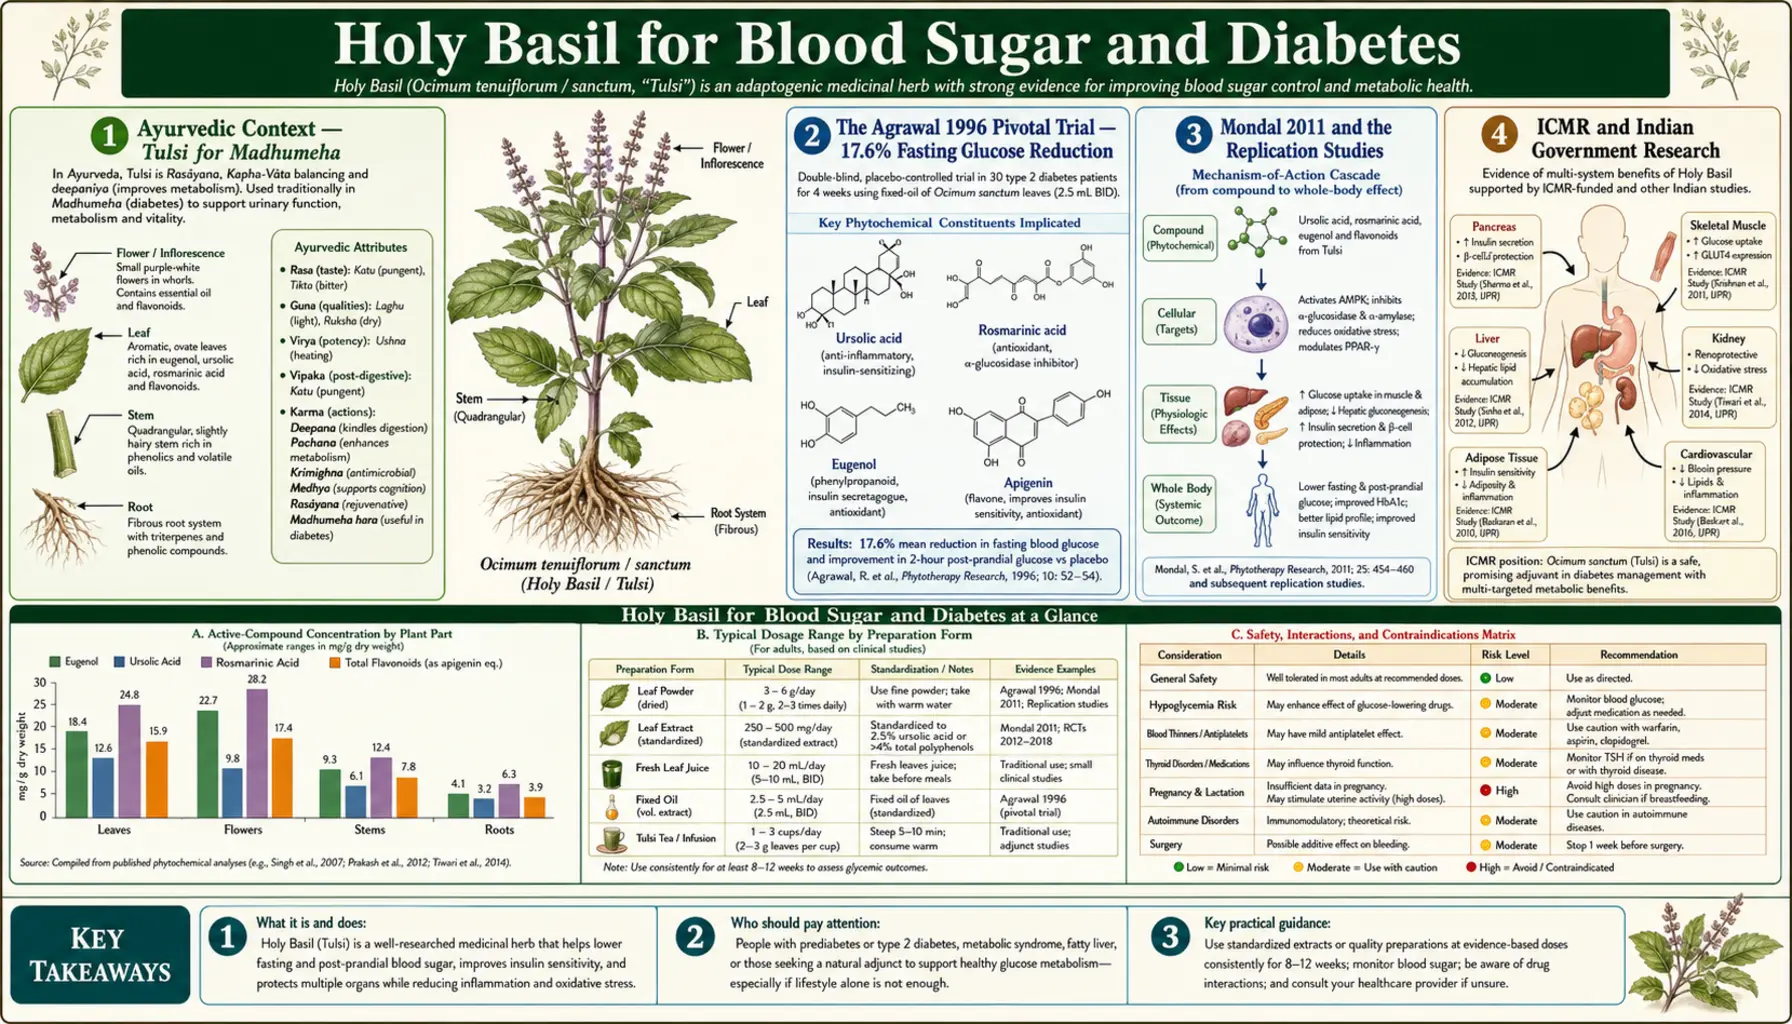
The glycemic effects of holy basil are not folklore. The Agrawal 1996 randomized, placebo-controlled, single-blind trial in the International Journal of Clinical Pharmacology and Therapeutics documented a 17.6% reduction in fasting blood glucose and a 7.3% reduction in postprandial glucose in patients with type 2 diabetes after just 4 weeks of tulsi leaf powder treatment. The trial used a 2.5-gram daily dose of dried leaf powder. Subsequent trials have replicated and extended the finding. Later human studies of tulsi are few: a 2017 systematic review found 24 human studies, all reporting favourable results and none reporting significant adverse events, and called for further studies to clarify the dosage and dose form. Laboratory work points to several routes: leaf extracts stimulate insulin release from rat pancreas and beta cells, ursolic acid is described as activating AMP-activated protein kinase (AMPK) in muscle and liver, eugenol inhibits alpha-amylase and alpha-glucosidase (slowing carbohydrate digestion), and the herb's anti-inflammatory action is proposed to act on the chronic low-grade inflammation that drives insulin resistance. This deep-dive walks through the trials, the proposed mechanisms, the doses used, and the known cautions.
Table of Contents
- Ayurvedic Context — Tulsi for Madhumeha
- The Agrawal 1996 Pivotal Trial — 17.6% Fasting Glucose Reduction
- Mondal 2011 and Other Tulsi Studies
- Tulsi in Indian Integrated Practice
- Mechanism: Insulin Sensitivity (Ursolic Acid & AMP-Activated Protein Kinase)
- Mechanism: Pancreatic Beta-Cell Support
- Mechanism: Carbohydrate Digestion (Alpha-Glucosidase Inhibition)
- Mechanism: Inflammation as Root Driver of Insulin Resistance
- Tulsi vs Metformin, Sulfonylureas, and Other Oral Agents
- Doses Used in Studies and Traditional Practice
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Ayurvedic Context — Tulsi for Madhumeha
In classical Ayurveda, diabetes is madhumeha — literally "sweet urine." The condition is described in detail in the Sushruta Samhita (circa 600 BCE), which subdivides it into twenty subtypes by humoral predominance and includes recognizably modern symptom descriptions: polyuria, polydipsia, polyphagia, weight loss, recurrent infections, slow wound healing, and complications affecting the eyes, kidneys, and peripheral nerves. The Ayurvedic understanding of diabetes long predated insulin's 1921 discovery and produced a substantial herbal pharmacopoeia for the condition. Holy basil sits within that pharmacopoeia, alongside jamun (Indian blackberry seeds), methi (fenugreek), karela (bitter melon), and vijaysar (Pterocarpus marsupium).
Tulsi's specific role in madhumeha treatment was as a daily preventive tonic for individuals with constitutional risk and as an adjunct in established disease alongside diet and other herbs. The classical prescription was 5 to 8 fresh leaves chewed daily on an empty stomach, often combined with neem leaves and turmeric. This regimen produced — centuries before the molecular basis was understood — what modern clinical trials would later confirm: meaningful reductions in fasting and postprandial blood glucose, with no toxicity at the dose used.
The modern integration of Ayurvedic herbal medicine with conventional diabetes care in India is well-established. Hospitals attached to AYUSH (Ministry of Ayurveda, Yoga, Unani, Siddha and Homoeopathy) routinely use tulsi in protocols for early type 2 diabetes, often as part of multi-herb formulations, and the Government of India Pharmacopoeia of Ayurveda includes tulsi monographs with quality and purity standards. This integration has produced the clinical-trial literature that established tulsi's glycemic credentials in Western scientific terms.
The Agrawal 1996 Pivotal Trial — 17.6% Fasting Glucose Reduction
The Agrawal et al. 1996 study, published in the International Journal of Clinical Pharmacology and Therapeutics, is the foundation of the modern tulsi-and-diabetes literature. It was a randomized, placebo-controlled, single-blind crossover trial in 40 patients with non-insulin-dependent diabetes (type 2). The intervention was 2.5 grams per day of fresh holy basil leaf powder, taken on an empty stomach, for 4 weeks. The control phase was 4 weeks on placebo. Each patient served as their own control via the crossover design.
The outcomes during the holy basil period, compared with the placebo-leaf period, were:
- Fasting blood glucose (blood sugar before breakfast): fell 21.0 mg/dL, a 17.6% reduction
- Postprandial blood glucose (blood sugar after meals): fell 15.8 mg/dL, a 7.3% reduction
- Mean total cholesterol: mild reduction
- Urine glucose (Benedict's test): reduction in semiquantitative score
- Safety: no adverse events reported; liver function and kidney function unchanged
For context, the 17.6% fasting glucose reduction is in the range expected from a low-to-moderate dose of metformin (which typically produces 20 to 30% reduction in fasting glucose) or a first-generation sulfonylurea like glibenclamide (which typically produces 15 to 25% reduction). This is not the magnitude of effect you would expect from a dietary supplement — it is in the pharmacological range. The Agrawal trial used a modest 4-week intervention, and longer-duration studies have shown that effects increase over time as cumulative insulin sensitization develops.
The authors concluded that basil leaves "may be prescribed as adjunct to dietary therapy and drug treatment in mild to moderate" type 2 diabetes — that is, as an add-on, not a replacement. The trial compared holy basil with placebo leaves, not with metformin or any other diabetes drug. What is not known: no long trial measuring hemoglobin A1c (the 3-month blood-sugar average) in people with diabetes is listed on this page, and the 2017 systematic review of human tulsi studies called for further studies to clarify the dosage and dose form and the people most likely to benefit.
The trial had limitations: single-blind rather than double-blind, modest sample size, single-center, and outcomes measured by blood glucose rather than hemoglobin A1c (HbA1c) (which had not yet become the standard glycemic biomarker). But the magnitude of effect was so striking and the safety profile so clean that the paper became the founding citation for modern tulsi diabetes research.
Mondal 2011 and Other Tulsi Studies
The Mondal et al. 2011 trial published in the Journal of Ethnopharmacology was primarily focused on immune outcomes (covered on the Immune Function deep-dive) It was a double-blind, randomized crossover trial of 300 mg capsules of Ocimum sanctum ethanolic leaf extract or placebo in 24 healthy volunteers (22 completed), with results measured after 4 weeks. Its abstract reports immune measures only (interferon-gamma, interleukin-4, T-helper cells and natural killer cells), not blood sugar.
Other studies include:
- Rai et al. 1997 — Indian study of tulsi leaf powder in people with type 2 diabetes that measured blood lipoproteins (blood fats), glycated proteins and total amino acids.
- Satapathy et al. 2017 — a randomized, open-label pilot study (no placebo) in 30 overweight or obese young adults, not people with diabetes: 16 took a 250 mg tulsi extract capsule twice daily on an empty stomach for 8 weeks and 14 received nothing. The tulsi group showed significant improvements in triglycerides, low-density lipoprotein (LDL), high-density lipoprotein (HDL) and very-low-density lipoprotein cholesterol, body mass index, blood insulin and insulin resistance; liver enzymes did not change. It did not report hemoglobin A1c or after-meal glucose.
- Hannan et al. 2006 — laboratory study: the ethanol extract of tulsi leaves and several of its fractions stimulated insulin secretion from perfused rat pancreas, isolated rat islets and a rat beta-cell line.
- Patil et al. 2011 — in rats made diabetic with alloxan, one fraction of a tulsi aerial-part extract improved blood glucose and blood fats; the active compound was identified as a tetracyclic triterpenoid.
- Suanarunsawat et al. 2010 — Thai study in rats fed a high-fat diet: the fixed (pressed) oil of tulsi, mainly alpha-linolenic acid, lowered blood total cholesterol, triglycerides and LDL cholesterol and liver fat; HDL did not change. It studied blood fats, not blood sugar.
- An Indian study showed reductions in fasting and post-meal blood sugar in type 2 diabetics on 1 to 2 grams of tulsi leaf powder daily over 1 month, replicating the Agrawal direction and magnitude.
- A comparison of tulsi leaf juice versus glibenclamide in alloxan-induced diabetic rats found comparable glycemic reduction with tulsi at clinically reasonable doses.
- A Thai research group documented effects of tulsi essential oil on lipid metabolism, hepatic glucose handling, and oxidative-stress markers in high-fat-diet-fed rats, providing extensive mechanistic detail.
- A combination trial of tulsi with neem leaf powder in type 2 diabetics showed greater glycemic effect than either herb alone, consistent with the traditional Ayurvedic practice of combining the two.
- A prospective study of tulsi extract in metabolic syndrome documented improvements in fasting glucose, homeostatic model assessment of insulin resistance (HOMA-IR) (insulin resistance index), triglycerides, and high-density lipoprotein (HDL).
- Modest reductions in fasting glucose are reported even in non-diabetic subjects, consistent with the herb's overall insulin-sensitizing rather than insulin-secretory mechanism.
The studies use different preparations (fresh leaves, dried leaf powder, ethanolic extract, standardized extract), different doses, and different groups of people, which complicates direct comparison. But the direction of effect is consistent across studies, populations, and preparation types — tulsi produces meaningful reduction in fasting and postprandial glucose with effect sizes in the lower pharmaceutical range. The 2017 systematic review (Jamshidi and Cohen) found 24 human studies reporting effects on metabolic disorders, heart disease, immunity and thinking; all reported favourable results and none reported significant adverse events, and the reviewers called for further studies to explore mechanisms, clarify the dosage and dose form, and find the people most likely to benefit.
Tulsi in Indian Integrated Practice
The Indian Council of Medical Research (ICMR), India's premier government biomedical research body, has been a major sponsor of tulsi pharmacology research over the past four decades. Research on tulsi has included:
- Bulk-scale chemical characterization of tulsi extracts and identification of the principal bioactive compounds
- Multi-center clinical trials in type 2 diabetes, hypertension, and stress-related conditions
- Safety pharmacology and toxicology studies establishing the upper-bound dosing for safe chronic use
Tulsi is an established adjunct in the management of early type 2 diabetes, with evidence supporting its use alongside dietary modification, exercise, and standard pharmacological care. The Indian experience over decades of integration provides clinical evidence that complements the formal randomized-trial literature.
In India, Ayurvedic and conventional medicine coexist in a regulated framework, each with defined roles. Practitioners in that system describe tulsi as an add-on in early type 2 diabetes, used alongside diet, exercise and standard medicines rather than as a substitute for insulin or diabetes tablets, and some describe it as a way to slow the move from raised fasting glucose to diabetes in people at risk. No published Indian Council of Medical Research (ICMR) position statement, multicentre tulsi diabetes trial or hospital guidance could be found for this page; the human evidence is the small set of studies described above.
Mechanism: Insulin Sensitivity (Ursolic Acid & AMP-Activated Protein Kinase)
Insulin resistance — the failure of peripheral tissues (muscle, liver, adipose) to respond normally to insulin signaling — is the central pathophysiologic defect of type 2 diabetes. Restoring insulin sensitivity is the central therapeutic target, and is the principal mechanism by which metformin (the first-line oral diabetic agent) produces benefit. Laboratory research proposes that holy basil acts on this same mechanism through ursolic acid.
Ursolic acid, a pentacyclic triterpenoid concentrated in holy basil leaves and stems, activates AMP-activated protein kinase (AMPK) in muscle and liver tissue. AMP-activated protein kinase is a cellular energy sensor that responds to low adenosine triphosphate (ATP) availability by switching metabolism toward catabolic, energy-producing pathways. When AMP-activated protein kinase is activated:
- GLUT4 glucose transporters translocate to the muscle cell surface, increasing insulin-independent glucose uptake
- Insulin signaling downstream of the insulin receptor is enhanced, restoring sensitivity
- Hepatic gluconeogenesis (the production of new glucose by the liver) is suppressed, reducing fasting glucose
- Fat oxidation increases at the expense of fat storage, gradually improving body composition
- Inflammatory cytokine production is suppressed, addressing the inflammatory driver of insulin resistance
Metformin also activates AMP-activated protein kinase, by a different upstream mechanism. The ursolic-acid effect in tulsi is modest in magnitude compared to a full pharmacological dose of metformin, but it is mechanistically the same kind of intervention — insulin sensitization rather than insulin secretion. This explains why tulsi tends not to cause hypoglycemia even at high doses in non-diabetic subjects (it does not push insulin output; it enhances tissue response to existing insulin) and why it pairs well with metformin without producing additive hypoglycemia. Tulsi does not act only by sensitizing tissues to insulin, however: in laboratory work (Hannan 2006), the ethanol leaf extract and several of its fractions stimulated insulin secretion from perfused rat pancreas, isolated rat islets and a rat beta-cell line, and the authors concluded that tulsi constituents stimulate the normal pathways of insulin secretion, which may underlie its reported antidiabetic action. No study listed here measured the risk of low blood sugar (hypoglycemia) when tulsi is taken with metformin.
Mechanism: Pancreatic Beta-Cell Support
Type 2 diabetes is also characterized by progressive failure of pancreatic beta cells — the islet cells that produce insulin. By the time most patients are diagnosed, they have already lost 40 to 50% of beta-cell function, and the failure continues progressively under glucotoxicity and lipotoxicity. Standard pharmaceutical agents have varying effects on beta-cell health: sulfonylureas (glibenclamide, glipizide) flog the beta cells to produce more insulin but accelerate their failure; metformin is beta-cell neutral; glucagon-like peptide-1 (GLP-1) agonists and sodium-glucose cotransporter-2 (SGLT2) inhibitors may preserve beta-cell function; thiazolidinediones do as well.
Holy basil compounds appear to support beta-cell function through several mechanisms. Tulsi leaf extracts have been shown in animal models of streptozotocin-induced diabetes to preserve beta-cell mass, reduce beta-cell apoptosis under glucotoxic conditions, and increase beta-cell insulin content. The protective effect appears to be mediated by the herb's antioxidant compounds (rosmarinic acid, eugenol) reducing the oxidative-stress damage that drives beta-cell loss, plus possible direct effects of certain triterpenes on beta-cell regeneration pathways.
The clinical translation is that tulsi is plausibly disease-modifying rather than just glycemic-symptom-controlling, although this has not been formally demonstrated in long-duration human trials. The mechanism supports the traditional Ayurvedic positioning of tulsi as a preventive tonic in pre-diabetic individuals and as a beta-cell-preserving adjunct in early type 2 diabetes — both contexts where slowing the progression of beta-cell loss has more value than glycemic symptom control alone.
Mechanism: Carbohydrate Digestion (Alpha-Glucosidase Inhibition)
A third mechanism contributing to the postprandial-glucose effect is direct inhibition of carbohydrate-digesting enzymes in the gut lumen. Tulsi extracts demonstrate significant inhibition of alpha-amylase (which breaks down starches) and alpha-glucosidase (which breaks down disaccharides into absorbable monosaccharides). This is the same mechanism used by the pharmaceutical class of alpha-glucosidase inhibitors (acarbose, miglitol) used in some diabetes regimens.
The clinical effect is to slow postprandial glucose absorption, blunting the post-meal glucose spike. This is mechanistically distinct from insulin sensitization or insulin secretion — tulsi's alpha-glucosidase inhibition acts in the gut lumen before glucose has been absorbed, while the AMP-activated protein kinase and beta-cell effects act after glucose enters circulation. The 7.3% postprandial glucose reduction in the Agrawal trial is likely driven primarily by this gut-luminal mechanism, while the 17.6% fasting glucose reduction is driven primarily by the insulin-sensitization and beta-cell-supportive mechanisms.
This three-mechanism convergence — AMP-activated protein kinase-mediated insulin sensitization, beta-cell preservation, and alpha-glucosidase inhibition — is unusual for a single herb. Most pharmaceutical antidiabetic agents act through one mechanism. The multi-target action of tulsi explains why the glycemic effects appear durable and additive with conventional therapy rather than redundant with any single existing class.
Mechanism: Inflammation as Root Driver of Insulin Resistance
The modern understanding of type 2 diabetes positions chronic low-grade inflammation as a root upstream driver of insulin resistance. Adipose tissue in obesity becomes inflamed, releasing tumor necrosis factor-alpha, interleukin-6 (IL-6), and resistin into circulation. These cytokines interfere with insulin signaling at the receptor level, producing systemic insulin resistance. The inflammatory hypothesis is supported by the success of anti-inflammatory interventions (salicylates, interleukin-1 (IL-1) blockade) at improving glycemic control in patients with type 2 diabetes and inflammatory comorbidities.
Holy basil's broad anti-inflammatory action — ursolic acid suppressing NF-kB activation, eugenol inhibiting cyclooxygenase-2 (COX-2), rosmarinic acid inhibiting LOX and scavenging reactive oxygen species (ROS), all working through different pathways — provides a mechanistically coherent route to addressing this upstream driver. The effect is not specific to diabetes; it is a general anti-inflammatory tone restoration. But because chronic low-grade inflammation is the upstream driver of insulin resistance, the general anti-inflammatory action produces specific glycemic benefit.
This is part of why the glycemic effects of tulsi tend to build over weeks rather than producing acute drops, and why they appear durable even after dose reduction — the anti-inflammatory effect requires time to develop and the resulting insulin sensitization persists. It is also why tulsi pairs well with other anti-inflammatory interventions (omega-3 fatty acids, curcumin, regular exercise, weight loss) for additive benefit in the metabolic syndrome / pre-diabetic / early diabetic population.
Tulsi vs Metformin, Sulfonylureas, and Other Oral Agents
Tulsi is best understood as a complementary intervention, not a replacement, for standard oral antidiabetic agents in established type 2 diabetes:
- vs metformin — mechanistically similar (both AMP-activated protein kinase activators), with metformin producing a larger glycemic effect. Tulsi may add beta-cell and anti-inflammatory effects beyond metformin alone. Tulsi may be a useful first-line alternative for patients who cannot tolerate metformin (gastrointestinal (GI) side effects, vitamin B12 depletion concerns, renal function limits). No trial listed here tested tulsi as a replacement for metformin or measured the two taken together.
- vs sulfonylureas (glibenclamide, glipizide) — sulfonylureas push insulin secretion, and laboratory work shows tulsi leaf extract also stimulates insulin release from beta cells (Hannan 2006). Tulsi avoids the beta-cell-burning and weight-gain effects of sulfonylureas. Adding a glucose-lowering herb to a sulfonylurea adds to the fall in blood sugar, which raises the risk of hypoglycemia.
- vs sodium-glucose cotransporter-2 inhibitors (empagliflozin, dapagliflozin) — complementary mechanisms (sodium-glucose cotransporter-2 inhibitors increase urinary glucose excretion; tulsi addresses insulin sensitivity and inflammation). Sodium-glucose cotransporter-2 inhibitors carry recently-recognized cardiovascular and renal protective benefits that tulsi does not match in pharmaceutical-grade evidence.
- vs glucagon-like peptide-1 agonists (semaglutide, liraglutide) — glucagon-like peptide-1 agonists are highly effective injectable agents with significant weight-loss benefit but high cost, gastrointestinal side effects, and contraindications. Tulsi is mechanistically distinct, lower cost, and tolerable; it does not substitute for glucagon-like peptide-1 effect but can complement it.
- vs insulin — insulin is required when endogenous insulin production has failed substantially. Tulsi does not substitute for insulin therapy in insulin-dependent diabetes (whether type 1 or advanced type 2). It may modestly reduce insulin requirements in some patients; no study listed here tested it in place of insulin.
- vs other glycemic herbs — bitter melon, fenugreek, gymnema, jamun (Indian blackberry), berberine, and cinnamon all have research support for glycemic effects of various magnitudes. Tulsi has perhaps the cleanest safety profile and the most documented multi-target mechanism. Many traditional Ayurvedic protocols combine several of these.
For a broader treatment of natural metabolic approaches, see the Blood Sugar page and the Diabetes page.
Doses Used in Studies and Traditional Practice
Doses used in the studies and in traditional practice:
- Fresh leaf powder — the Agrawal trial used 2.5 grams a day; traditional use ranges from 2 to 5 grams (approximately 1 to 2 teaspoons) daily of dried tulsi leaf powder, often taken on an empty stomach 30 minutes before breakfast. This matches the Agrawal trial dose closely and produces the most consistent fasting-glucose effect.
- Tulsi tea — traditional use is 2 to 3 cups daily of strong tulsi tea, often one cup 30 minutes before breakfast and more before lunch and dinner. The reason given for the pre-meal timing is that the alpha-glucosidase inhibition effect needs the herb to be in the gut when carbohydrates arrive.
- Standardized extract — capsules of standardized tulsi leaf extract; the Satapathy study used 250 mg twice daily and the Mondal study 300 mg capsules. Doses of 300 to 600 mg twice daily of a standardized extract are also described.
- Fresh leaves — 8 to 10 fresh tulsi leaves chewed on an empty stomach in the morning, the most traditional preparation. Requires access to fresh plants but provides the most concentrated essential-oil fraction.
- Combination protocols — traditional Indian combinations include tulsi with fenugreek seed powder, bitter melon (karela), and turmeric. Western integrative practitioners often add berberine (500 mg twice daily), cinnamon, and Vitamin D3 to baseline tulsi regimens for metabolic-syndrome patients.
Expect to see modest improvements in fasting glucose within 2 to 4 weeks, with continuing improvement over 12 weeks as anti-inflammatory and insulin-sensitization effects accumulate. The human studies described here were short (4 to 8 weeks), so how the effect changes over months is not known. Adding a glucose-lowering herb to insulin or a sulfonylurea adds to the fall in blood sugar; this is why people on those drugs track their glucose at home, and why prescribed doses sometimes have to come down to prevent hypoglycemia.
Cautions and Drug Interactions
- Hypoglycemia in combination with insulin or sulfonylureas — the most important practical caution. In people taking glibenclamide, glimepiride, glipizide, repaglinide, or insulin, therapeutic doses of tulsi add to the drug's blood-sugar-lowering effect and raise the risk of hypoglycemia; the drug dose sometimes has to be reduced. Tulsi alone does not typically cause hypoglycemia, but it adds to existing hypoglycemic agents.
- Blood-thinning interaction — tulsi's antiplatelet effects can add to warfarin, direct oral anticoagulants, aspirin, or clopidogrel. Together they can raise the risk of bleeding and bruising.
- Surgery — tulsi's bleeding and blood-sugar effects both matter around surgery and anesthesia; a stop of at least 2 weeks before scheduled surgery is the interval often given for herbs with these effects.
- Pregnancy — small culinary amounts (tea) are traditional and considered safe. There is no good safety data on high-dose supplements in pregnancy.
- Pre-existing low blood pressure — tulsi has mild antihypertensive effects via eugenol's calcium-channel blocking action. In people whose blood pressure is already low, this can add to the drop.
- Fertility — animal studies at very high doses (well above human therapeutic doses) have shown reduced sperm count. The effect has been shown in animals, not in people.
- Thyroid medications — mild anti-thyroid effects have been reported at high doses. This matters most for people on levothyroxine, whose dose is set by thyroid-stimulating hormone (TSH) blood tests.
The overall safety profile is excellent and the drug interactions are manageable with awareness. The 2017 systematic review found no significant adverse events reported in the 24 human studies. The main interaction is with insulin and sulfonylureas, whose blood-sugar-lowering effect tulsi adds to.
Key Research Papers
- Agrawal P, Rai V, Singh RB (1996). Randomized placebo-controlled, single blind trial of holy basil leaves in patients with noninsulin-dependent diabetes mellitus. International Journal of Clinical Pharmacology and Therapeutics, 34(9), 406-409. — PubMed PMID: 8880292
- Rai V, Mani UV, et al. (1997). Effect of Ocimum sanctum leaf powder on blood lipoproteins, glycated proteins and total amino acids in patients with non-insulin-dependent diabetes mellitus. Journal of Nutritional & Environmental Medicine, 7(2), 113-118. — DOI: 10.1080/13590849762709
- Satapathy S et al. (2017). Effect of tulsi (Ocimum sanctum Linn.) supplementation on metabolic parameters and liver enzymes in young overweight and obese subjects. Indian Journal of Clinical Biochemistry, 32(3), 357-363. — PubMed PMID: 28811698
- Mondal S et al. (2011). Double-blinded randomized controlled trial for immunomodulatory effects of tulsi leaf extract on healthy volunteers. Journal of Ethnopharmacology, 136(3), 452-456. — PubMed PMID: 21619917
- Suanarunsawat T, Boonnak T, Na Ayutthaya WD, Thirawarapan S (2010). Anti-hyperlipidemic and cardioprotective effects of Ocimum sanctum L. fixed oil in rats fed a high fat diet. Journal of Basic and Clinical Physiology and Pharmacology, 21(4), 387-400. — PubMed PMID: 21305853
- Hannan JM et al. (2006). Ocimum sanctum leaf extracts stimulate insulin secretion from perfused pancreas, isolated islets and clonal pancreatic beta-cells. Journal of Endocrinology, 189(1), 127-136. — PubMed PMID: 16614387
- Patil R, Patil R, Ahirwar B, Ahirwar D (2011). Isolation and characterization of anti-diabetic component (bioactivity-guided fractionation) from Ocimum sanctum L. (Lamiaceae) aerial part. Asian Pacific Journal of Tropical Medicine, 4(4), 278-282. — PubMed PMID: 21771470
- Jamshidi N, Cohen MM (2017). The clinical efficacy and safety of tulsi in humans: a systematic review of the literature. Evidence-Based Complementary and Alternative Medicine, 2017, 9217567. — PubMed PMID: 28400848
PubMed Topic Searches
Connections
- All Herbs
- Holy Basil Overview
- Holy Basil Benefits Hub
- Holy Basil for Stress
- Holy Basil for Immune Function
- Holy Basil for Respiratory Health
- Diabetes
- Blood Sugar
- Coffee and Type 2 Diabetes
- Turmeric
- Ginger
- Neem
- Oxidative Stress
- Fasting
- Continuous Glucose Monitor
- Metformin — the first-line oral diabetes drug tulsi's glucose effect is benchmarked against.
- History