Spinach Iron Absorption and Oxalates
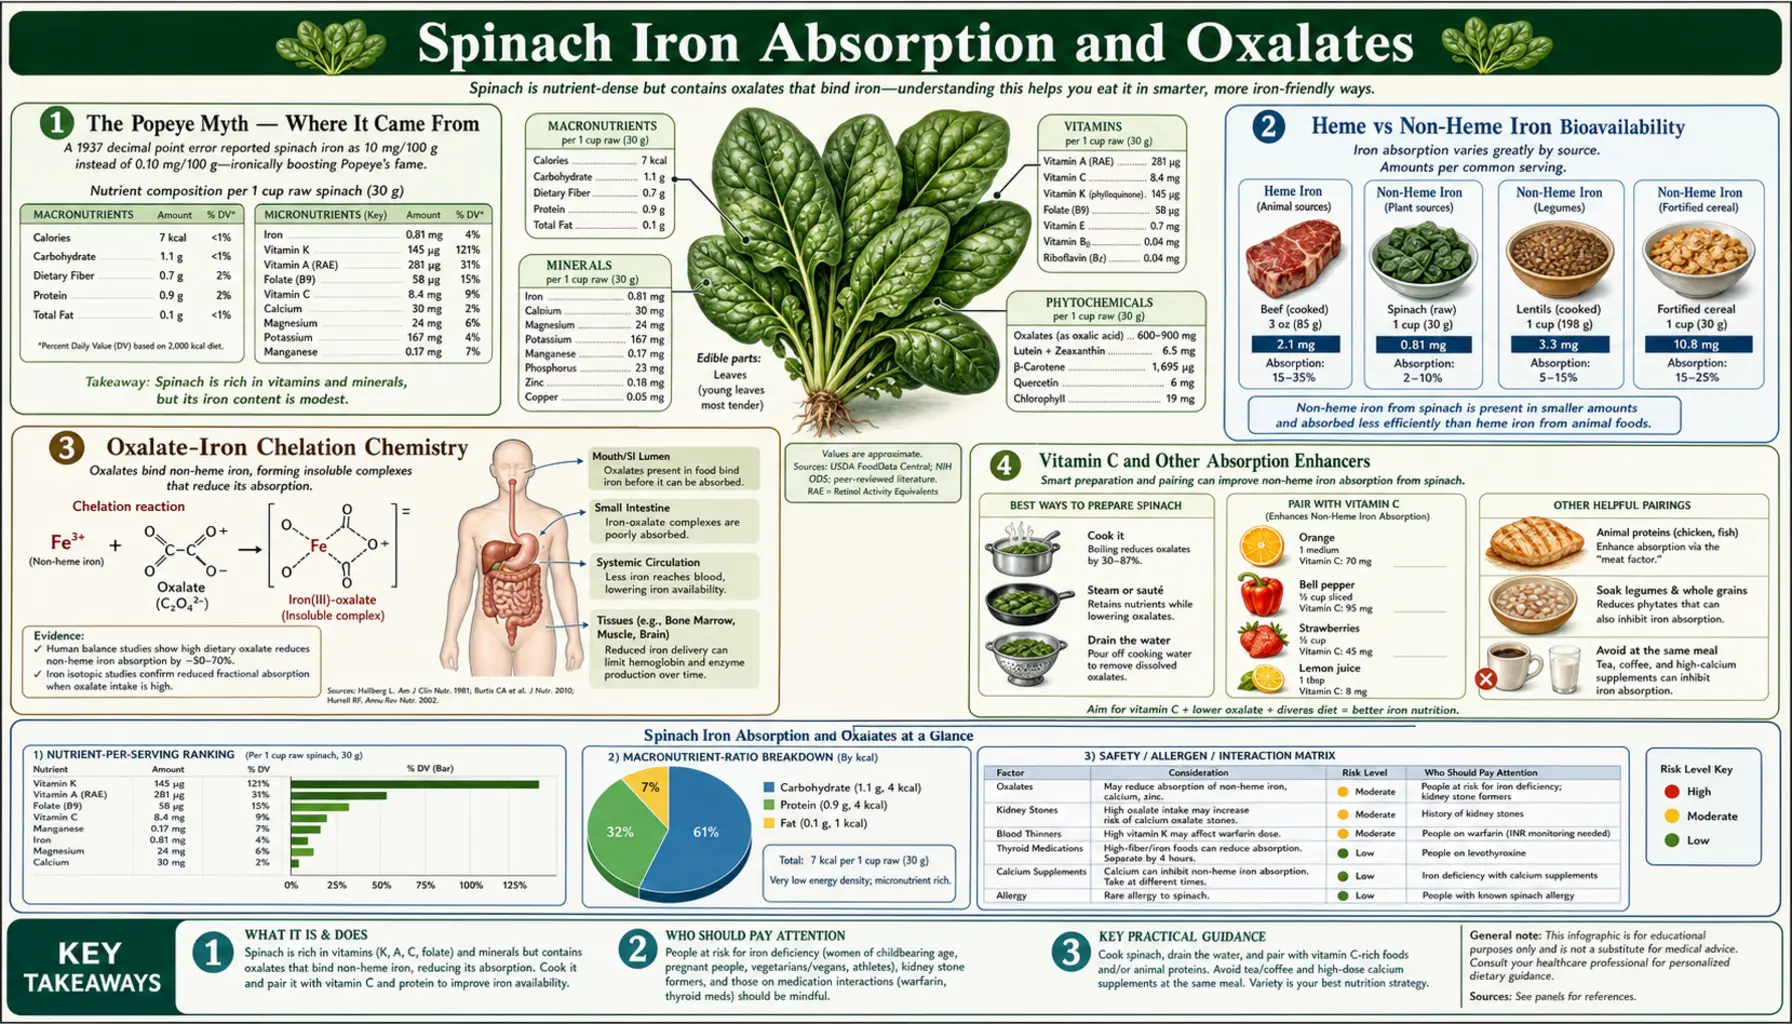
The Popeye image of spinach as iron-rich superfood is one of the most persistent nutrition myths. Spinach does contain non-heme iron at 2.7 mg per 100 g raw (3.6 mg cooked, per USDA) — respectable in absolute terms — but the high oxalate content (750-1,500 mg per 100 g raw) chelates most of that iron into insoluble iron-oxalate complexes that pass through the gut unabsorbed. Real-world bioavailability is approximately 2%, compared to 15-35% for heme iron from red meat and 5-12% for non-heme iron from less-oxalate-rich foods. Vitamin C eaten in the same meal can raise spinach iron absorption by reducing ferric iron to the more absorbable ferrous form, although across a whole diet the effect measured is far smaller than in single test meals. Beyond the iron question, the same oxalate is the substrate for calcium oxalate kidney stones in susceptible individuals — the most common kidney stone type, affecting up to 10% of the population. This page covers the chemistry, the kidney stone risk, the cooking-based oxalate reduction strategies, and the practical implications for both iron-deficient patients and oxalate-sensitive patients.
Table of Contents
- The Popeye Myth — Where It Came From
- Heme vs Non-Heme Iron Bioavailability
- Oxalate-Iron Chelation Chemistry
- Vitamin C and Other Absorption Enhancers
- Kidney Stones — The Oxalate Concern
- Cooking Methods That Reduce Oxalate
- The Calcium-Oxalate Trade-Off
- What to Know If You Have Iron Deficiency
- What to Know If You Are Oxalate-Sensitive
- Key Research Papers
- Connections
- Featured Videos
The Popeye Myth — Where It Came From
The cultural image of spinach as iron-rich superfood dates to the 1929 Popeye cartoon strip, which made spinach the source of the sailor's super-strength. The Popeye character was credited by mid-century nutritionists with single-handedly increasing U.S. spinach consumption by 33% during the 1930s, an early case study in popular media influence on dietary habits.
The persistent (but largely apocryphal) story is that the 1870 Wolff analysis of spinach iron content contained a decimal-point error, reporting 35 mg iron per 100 g instead of the correct 3.5 mg, and that this exaggerated figure persisted in nutrition textbooks until the 1930s, was used by E.C. Segar in creating the Popeye character, and the myth survived even after the error was corrected. Subsequent historical detective work suggests the decimal-error story is itself partially a myth — the 35 mg figure may have referred to dry-weight rather than fresh-weight content (which would have been roughly correct), or to a different chemical analysis entirely.
The substantive truth, regardless of the origin myth, is that spinach iron content per gram is respectable but the iron is poorly absorbed. Per the U.S. Department of Agriculture (USDA) FoodData Central database:
- Spinach, raw — 2.7 mg iron per 100 g
- Spinach, cooked, boiled, drained — 3.6 mg iron per 100 g (concentrated because water is removed)
- Spinach, canned — 2.3 mg iron per 100 g
For comparison:
- Beef liver — 6.5 mg heme iron per 100 g (much higher bioavailability)
- Beef chuck — 2.8 mg heme iron per 100 g
- Oysters — 7.8 mg iron per 100 g
- Lentils — 3.3 mg non-heme iron per 100 g
- Tofu — 2.7 mg non-heme iron per 100 g
- Pumpkin seeds — 8.8 mg non-heme iron per 100 g
The numerical iron content of spinach is in the same range as lentils, tofu, and beef chuck — respectable but not extraordinary. The catch is that the bioavailable fraction (the iron actually absorbed and used) is much lower for spinach than for any of those comparisons because of the oxalate chelation effect described below.
Heme vs Non-Heme Iron Bioavailability
Dietary iron exists in two distinct chemical forms with very different absorption mechanisms:
- Heme iron — iron bound in the heme prosthetic group of hemoglobin and myoglobin, present only in animal flesh. Absorbed intact via the heme carrier protein 1 (HCP1) in the duodenal enterocyte and then released from the porphyrin ring inside the cell by heme oxygenase. Bioavailability is 15-35% depending on iron status, dietary co-factors, and the meat source.
- Non-heme iron — ionic iron (Fe³+ or Fe²+) bound to various dietary ligands. Must be reduced from ferric (Fe³+) to ferrous (Fe²+) by the duodenal cytochrome b reductase (DCYTB) before absorption via the divalent metal transporter 1 (DMT1). Bioavailability ranges from 1-25% depending heavily on dietary co-factors and inhibitors. Found in plant foods, dairy, and fortified grains.
Spinach iron is non-heme iron, and within the non-heme iron category it has one of the lowest bioavailability rates of any common food. The Hallberg and Hulthén 2000 algorithm for predicting dietary iron absorption works from phytate, polyphenols, vitamin C (ascorbic acid), meat, fish and seafood, calcium, egg, soy protein and alcohol; oxalate is not one of its factors, and the paper gives no figure for spinach. Figures of roughly 1-3% absorption are often quoted for spinach, compared to 5-12% for non-heme iron in low-inhibitor foods (cooked lentils, tofu, fortified cereal).
The key implications:
- Spinach is not a reliable treatment for iron deficiency. Patients with iron-deficiency anemia who try to correct it through spinach consumption alone will not see meaningful improvement in ferritin or hemoglobin.
- For iron deficiency, the rank order of dietary effectiveness is: heme iron from red meat > iron supplements > non-heme iron from low-inhibitor foods (lentils, pumpkin seeds, fortified cereal) with vitamin C >> non-heme iron from high-oxalate greens.
- For vegan and vegetarian people at risk of iron deficiency, the more dependable plant sources are low-oxalate, high-bioavailability foods (lentils, pumpkin seeds, fortified products) eaten with vitamin C, rather than greens.
- Spinach can still contribute incidentally to iron intake in a mixed diet but is not a dependable way to correct iron deficiency.
Oxalate-Iron Chelation Chemistry
Oxalate (oxalic acid, C&sub2;H&sub2;O&sub4;) is a small dicarboxylic acid produced by many plants as a defense compound and as a calcium-regulating metabolite. Spinach, beet greens, rhubarb, Swiss chard, almonds, and a few other foods are particularly high in oxalate.
The chemistry of oxalate-mineral interaction is that the two carboxylate groups can chelate divalent metal cations to form insoluble or poorly absorbed complexes. Calcium oxalate (the substance of most kidney stones) is the most familiar example, but oxalate also forms similar complexes with iron (iron oxalate), magnesium, and zinc:
- Calcium oxalate (CaC&sub2;O&sub4;) — the most common chelation product because dietary calcium is typically the highest divalent cation concentration in the gut. Highly insoluble at physiologic pH; precipitates in the gut and passes in stool. This is actually beneficial for kidney stone prevention because it reduces dietary oxalate absorption.
- Iron oxalate (FeC&sub2;O&sub4;) — insoluble at the alkaline pH of the small intestine where non-heme iron is absorbed. Most spinach iron is bound as iron oxalate by the time it reaches the absorptive duodenum, and passes through the gut unabsorbed.
- Magnesium oxalate — somewhat more soluble than calcium oxalate but still reduces magnesium bioavailability from oxalate-rich foods.
A 1988 study by Heaney, Weaver and Recker in 13 healthy adults quantified the practical effect on calcium absorption from spinach. Fractional calcium absorption from milk (low oxalate) averaged 27.6%; from spinach (high oxalate) only 5.1%. Despite spinach's 136 mg calcium per 100 g cooked appearing on nutrition labels, the bioavailable calcium is approximately 7 mg per 100 g — trivial compared to milk or fortified plant milks.
The Heaney and Weaver 1989 AJCN study measured absorption of isotope-labeled calcium oxalate in 18 women: about 10% when taken alone and 14% when taken with milk, against about 36% from milk; even so, the calcium oxalate was absorbed better than the spinach calcium in the authors' earlier study. Taking calcium oxalate together with milk did not lower absorption of the milk's own calcium.
The same logic applies to spinach iron and to a lesser extent spinach magnesium. The presence of iron and calcium on the spinach nutrition label is technically accurate (the minerals are present in the leaf tissue) but functionally misleading for the consumer trying to use spinach for those nutrients.
Vitamin C and Other Absorption Enhancers
The single most effective intervention for boosting non-heme iron absorption from spinach (or any non-heme source) is co-ingestion with vitamin C. Ascorbic acid:
- Reduces ferric (Fe³+) iron to the more absorbable ferrous (Fe²+) form in the duodenum, partially bypassing the DCYTB reductase rate-limiting step.
- Chelates iron in a soluble ascorbate-iron complex that competes with oxalate for binding the iron, increasing the soluble iron fraction reaching the enterocyte brush border.
- Reduces the pH of the gut content, increasing iron solubility (most relevant in the proximal duodenum where pH transition from acidic stomach to alkaline jejunum occurs).
The Cook and Reddy 2001 AJCN study measured the effect across a complete diet rather than a single meal: in 12 people eating a freely chosen, then a low-vitamin-C, then a high-vitamin-C diet for 5 days each, mean non-heme iron absorption did not differ significantly between the three periods, despite daily vitamin C intakes ranging from 51 to 247 mg. The authors concluded that vitamin C's helping effect on iron absorption from a complete diet is far less pronounced than in single test meals given to fasting volunteers, where vitamin C has a pronounced enhancing effect.
Practical spinach pairings for iron absorption:
- Spinach + lemon juice — one tablespoon lemon juice contains ~7 mg vitamin C; squeezed over a spinach salad or sauteed spinach.
- Spinach + tomatoes — ~14 mg vitamin C per medium tomato; spinach in marinara sauce or a Greek salad with tomato.
- Spinach + bell peppers — 80-150 mg vitamin C per cup; a spinach stir-fry with bell peppers.
- Spinach + orange juice — 124 mg vitamin C per cup; spinach smoothie with orange.
- Spinach + strawberries — 85 mg vitamin C per cup; spinach-strawberry salad.
- Spinach + beef — the "meat factor" enhances non-heme iron absorption even without vitamin C; spinach as a side to a meat dish, or spinach mixed into ground beef preparations.
Inhibitors that lower iron absorption from the same meal: coffee, tea, red wine (tannins), high-calcium dairy (which can compete with iron for absorption), bran cereal (phytate). The Hurrell 1999 study found that black tea served with a bread meal reduced non-heme iron absorption by 79-94%.
Kidney Stones — The Oxalate Concern
Calcium oxalate stones account for approximately 70-80% of all kidney stones — the most common kidney stone type, affecting roughly 10% of the U.S. adult population at some point in life. The recurrence rate after a first stone is approximately 50% within 10 years.
Dietary oxalate is one of several contributors to urinary oxalate excretion, which in turn is a primary determinant of calcium oxalate stone risk. Other contributors include:
- Endogenous oxalate production — the liver produces oxalate as a metabolite of glycine, glyoxylate, hydroxyproline, and vitamin C metabolism. Endogenous production is typically the larger contributor to urine oxalate than dietary intake in most people.
- Dietary oxalate absorption — typically 5-15% of dietary oxalate is absorbed; the rest is bound in the gut by calcium and excreted in stool.
- Calcium intake (paradoxical) — LOW dietary calcium increases urinary oxalate by reducing the gut binding of dietary oxalate. The Curhan 1997 Annals of Internal Medicine Nurses' Health Study famously showed that higher dietary calcium intake REDUCED kidney stone risk — opposite to the old recommendation to restrict calcium in stone formers.
- Hyperabsorption — some individuals (about 20% of recurrent calcium oxalate stone formers) have enhanced intestinal oxalate absorption, possibly related to Oxalobacter formigenes gut microbiota depletion (this bacterium degrades dietary oxalate in the colon).
- Inflammatory bowel disease and Roux-en-Y bypass — both increase oxalate absorption and produce "enteric hyperoxaluria" with markedly elevated stone risk.
The practical picture for spinach eaters in the general population: the Taylor and Curhan 2007 study described below, which followed large cohorts for new kidney stones, linked frequent spinach eating (eight or more servings a month) to a modestly higher stone risk in men and older women, and the risk from dietary oxalate appeared higher in men who ate less calcium. For individuals with a history of calcium oxalate stones, the standard urology recommendation is to limit very-high-oxalate foods (spinach, rhubarb, beet greens, almonds, peanuts, dark chocolate) and to maintain adequate dietary calcium intake (1,000-1,200 mg/day) at the same meals as oxalate-containing foods.
The Taylor and Curhan 2007 study followed 45,985 men, 92,872 older women and 101,824 younger women in three large U.S. cohorts for new kidney stones; spinach supplied more than 40% of their oxalate intake. Compared with eating spinach less than once a month, eating it eight or more times a month carried a relative risk of 1.30 for men and 1.34 for older women; neither oxalate nor spinach was linked to risk in younger women, and the authors concluded that their data do not implicate dietary oxalate as a major risk factor for kidney stones. The Taylor and Curhan 2008 CJASN study of 3,348 people found that those in the highest quarter of dietary oxalate intake excreted only 1.7 mg/day more urinary oxalate than those in the lowest quarter, and that higher calcium intake went with lower urinary oxalate.
Cooking Methods That Reduce Oxalate
The Chai and Liebman 2005 Journal of Agricultural and Food Chemistry study tested boiling and steaming (and, for potatoes, baking) on nine kinds of raw and cooked vegetables. Results across the nine vegetables:
- Raw vegetables (control) — most of the tested raw vegetables held a high proportion of their oxalate in the water-soluble form
- Steaming — 5-53% reduction in soluble oxalate
- Boiling — 30-87% reduction in soluble oxalate; boiling was more effective than steaming
- The cooking water — testing the water used for boiling and steaming recovered approximately 100% of the oxalate lost, so the soluble oxalate dissolves into the cooking water and is poured off with it
- Blanching (brief immersion in boiling water, then drained) — not tested separately in this study; it is the traditional kitchen method described below
The critical distinction is between SOLUBLE oxalate (the absorbable, kidney-stone-relevant fraction) and TOTAL oxalate. Cooking does not destroy the oxalate molecule chemically — it dissolves the soluble fraction into the cooking water. If the cooking water is consumed (as in soup or stew), the total oxalate burden on the consumer is unchanged. Only when the water is discarded does the consumer benefit from the oxalate reduction.
This is why traditional Italian preparations of spinach typically blanch the spinach in boiling water and discard the water before sauteing in olive oil and garlic — the technique is centuries old, predating modern oxalate chemistry, but produces a measurable oxalate reduction.
The boil-and-discard preparation as it is usually described for oxalate-sensitive people:
- A large pot of water is brought to a rolling boil.
- The spinach (or other oxalate-rich greens) boils for 1-3 minutes, until just wilted.
- It is drained in a colander and as much water as possible is pressed out.
- The cooking water, which now holds the dissolved oxalate, is thrown away rather than used for soup or stock.
- The blanched spinach is then sauteed briefly in olive oil with garlic, or used in dishes that don't depend on cooking liquid.
The trade-off, as discussed in our Cooking vs Raw deep-dive, is that this method also leaches out water-soluble vitamins (folate, vitamin C, B vitamins) which are lost with the discarded water. Steaming keeps more folate; boiling and discarding the water removes more oxalate. There is no single perfect method; the right answer depends on which nutrient or risk factor is most relevant to the individual.
The Calcium-Oxalate Trade-Off
One of the more counterintuitive findings in kidney stone research is that adequate dietary calcium REDUCES rather than increases calcium oxalate stone risk. The mechanism is competitive binding in the gut:
- When dietary calcium and dietary oxalate are consumed at the same meal, the calcium binds the oxalate in the gut to form insoluble calcium oxalate, which precipitates and passes in stool.
- The result is reduced absorption of BOTH the calcium AND the oxalate — both end up in the stool rather than the bloodstream and urine.
- Conversely, low-calcium diets allow more dietary oxalate to be absorbed unbound, leading to higher urinary oxalate excretion and higher calcium oxalate stone risk.
The Curhan 1997 Annals of Internal Medicine Nurses' Health Study followed 91,731 women over 12 years and found that the highest quintile of dietary calcium intake had a 35% LOWER risk of incident kidney stones compared to the lowest quintile, after adjustment for other risk factors. An earlier Curhan 1993 NEJM study of 45,619 men had found the same: men in the highest quintile of dietary calcium had a lower risk (relative risk 0.56, and 0.66 after adjustment for other risk factors). The mechanistic explanation came from balance studies showing that low-calcium diets produce higher urinary oxalate even when dietary oxalate is unchanged.
What these findings mean for spinach eaters with a kidney stone history:
- Adequate total dietary calcium (1,000-1,200 mg/day) can come from low-oxalate sources (dairy if tolerated, fortified plant milk, sardines with bones, fortified orange juice).
- Eating high-oxalate foods (spinach, almonds) with calcium at the same meal lets the calcium bind the oxalate in the gut — spinach with feta cheese, spinach lasagna with ricotta, almonds with yogurt.
- Calcium SUPPLEMENTS taken AWAY from meals raise serum and urinary calcium without the protective gut-binding of dietary oxalate. In the Curhan 1997 women's study, women who took calcium supplements had a higher stone risk than women who did not (relative risk 1.20), and 67% of the supplement users took them either apart from meals or with meals probably low in oxalate.
- Adequate hydration (2.5-3 liters fluid daily) is the single most important behavioral intervention for stone prevention, separate from dietary modifications.
What to Know If You Have Iron Deficiency
For people with diagnosed iron-deficiency anemia or low ferritin, spinach is not a dependable fix. The approaches used, in order of typical clinical use:
- Finding and addressing the cause — chronic blood loss (gastrointestinal (GI) bleeding, heavy menstrual periods, frequent blood donation), malabsorption (celiac disease, atrophic gastritis, post-bariatric surgery), inadequate intake (strict vegan diets without iron supplementation), or chronic inflammation. The cause matters more than the supplement.
- Oral iron supplementation — ferrous sulfate 325 mg contains 65 mg elemental iron; one regimen in use is a dose every other day on an empty stomach with vitamin C, based on the 2017 Stoffel hepcidin-cycle research. In those trials in iron-depleted women aged 18-40 given 60 mg iron doses, alternate-day dosing gave higher absorption than dosing on consecutive days over the same number of doses (cumulative fractional absorption 21.8% vs 16.3%; 175.3 mg vs 131.0 mg absorbed) and lower blood hepcidin; the trials reported no grade 3 or 4 adverse events, and the abstract gives no comparison of stomach side effects. Treatment is typically continued for 3-6 months past ferritin normalization to replete iron stores.
- Heme iron foods — red meat (especially beef chuck, beef liver), poultry dark meat, shellfish (oysters, clams, mussels) provide 15-35% bioavailable iron. Beef liver delivers approximately 6.5 mg highly bioavailable iron per 100 g.
- Non-heme iron foods WITH vitamin C — lentils, tofu, pumpkin seeds, fortified breakfast cereal, blackstrap molasses, paired with citrus, bell peppers, tomatoes, or strawberries to enhance absorption.
- Intravenous (IV) iron infusion — for severe deficiency, intolerance to oral iron, or malabsorption (ferric carboxymaltose, iron sucrose, low-molecular-weight iron dextran). Effective in single or 2-3 dose protocols.
Spinach can be a contributing source of dietary iron in a mixed approach but is not a dependable primary strategy. The 2% absorption rate means that achieving the 8-18 mg/day iron Recommended Dietary Allowance (RDA) from spinach alone would require eating multiple pounds per day, which is impractical and would deliver excessive oxalate.
For more on iron-deficiency management, see our Iron Deficiency Anemia page.
What to Know If You Are Oxalate-Sensitive
For patients with a history of calcium oxalate kidney stones (most stone formers), enteric hyperoxaluria (inflammatory bowel disease, fat malabsorption, Roux-en-Y gastric bypass), or known oxalate hyperabsorption:
- Highest-oxalate foods — the foods most often put on the reduce list are spinach, rhubarb, beet greens, Swiss chard, almonds, peanuts, dark chocolate (especially raw cacao), and to a lesser extent tea (especially black tea), sweet potatoes, and instant coffee.
- Boiling and discarding the water for moderate amounts of medium-oxalate foods; this is more effective than steaming for oxalate reduction.
- Adequate calcium at meals (1,000-1,200 mg/day total) binds oxalate in the gut.
- Plenty of fluid — 2.5-3 liters daily keeps urinary oxalate concentration low.
- Vitamin C megadoses — vitamin C is metabolized to oxalate; in the Taylor and Curhan 2008 study, people taking 1,000 mg/day or more of vitamin C excreted 6.8 mg/day more urinary oxalate than people taking less than 90 mg/day. The 75-200 mg/day range usually described for stone formers is far below the multi-gram megadoses popular in some wellness regimens.
- Potassium citrate, used per urology recommendation — alkalinizes the urine and reduces calcium oxalate supersaturation; prescription therapy for recurrent stone formers.
- Low-oxalate spinach substitutes — for the leafy green benefits without the oxalate burden: cooked kale (moderate oxalate, generally tolerated), romaine lettuce (low oxalate), arugula (low oxalate), bok choy (low oxalate), butter lettuce (very low oxalate). These can substitute for spinach in salads and side dishes.
For more on kidney stone management, see our Kidney Stones page.
Key Research Papers
- Hallberg L, Hulthen L (2000). Prediction of dietary iron absorption: an algorithm for calculating absorption and bioavailability of dietary iron. AJCN 71:1147-1160. — PubMed PMID: 10799377
- Cook JD, Reddy MB (2001). Effect of ascorbic acid intake on nonheme-iron absorption from a complete diet. AJCN 73:93-98. — PubMed PMID: 11124756
- Heaney RP, Weaver CM (1989). Oxalate: effect on calcium absorbability. AJCN 50:830-832. — PubMed PMID: 2801588
- Heaney RP, Weaver CM, Recker RR (1988). Calcium absorbability from spinach. AJCN 47:707-709. — PubMed PMID: 3354496
- Chai W, Liebman M (2005). Effect of different cooking methods on vegetable oxalate content. J Agric Food Chem 53:3027-3030. — PubMed PMID: 15826055
- Curhan GC, Willett WC, Speizer FE, Spiegelman D, Stampfer MJ (1997). Comparison of dietary calcium with supplemental calcium and other nutrients as factors affecting the risk for kidney stones in women. Ann Intern Med 126:497-504. — PubMed PMID: 9092314
- Taylor EN, Curhan GC (2007). Oxalate intake and the risk for nephrolithiasis. J Am Soc Nephrol 18:2198-2204. — PubMed PMID: 17538185
- Taylor EN, Curhan GC (2008). Determinants of 24-hour urinary oxalate excretion. CJASN 3:1453-1460. — PubMed PMID: 18650406
- Hurrell RF et al. (1999). Inhibition of non-haem iron absorption in man by polyphenolic-containing beverages. British J Nutrition 81:289-295. — PubMed PMID: 10999016
- Stoffel NU et al. (2017). Iron absorption from oral iron supplements given on consecutive versus alternate days. Lancet Haematology 4:e524-533. — PubMed PMID: 29032957
- Curhan GC, Willett WC, Rimm EB, Stampfer MJ (1993). A prospective study of dietary calcium and other nutrients and the risk of symptomatic kidney stones. NEJM 328:833-838. — PubMed PMID: 8441427
- Holmes RP, Goodman HO, Assimos DG (2001). Contribution of dietary oxalate to urinary oxalate excretion. Kidney International 59:270-276. — PubMed PMID: 11135080
- Borghi L et al. (2002). Comparison of two diets for the prevention of recurrent stones in idiopathic hypercalciuria. NEJM 346:77-84. — PubMed PMID: 11784873
PubMed Topic Searches
Connections
- All Food
- Spinach Main Page
- Spinach Benefits Hub
- Spinach Folate & Pregnancy
- Spinach for Eyes
- Cooking vs Raw
- Iron
- Calcium
- Vitamin C (Iron Enhancer)
- Iron Deficiency Anemia
- Kidney Stones
- Crohn's Disease (Enteric Hyperoxaluria)
- Lentils (Better Plant Iron Source)
- Kale (Lower Oxalate)
- Beef Liver (Heme Iron)
- Eggs
- History
- Nutrients