Tuna: Omega-3 vs Mercury Trade-Off
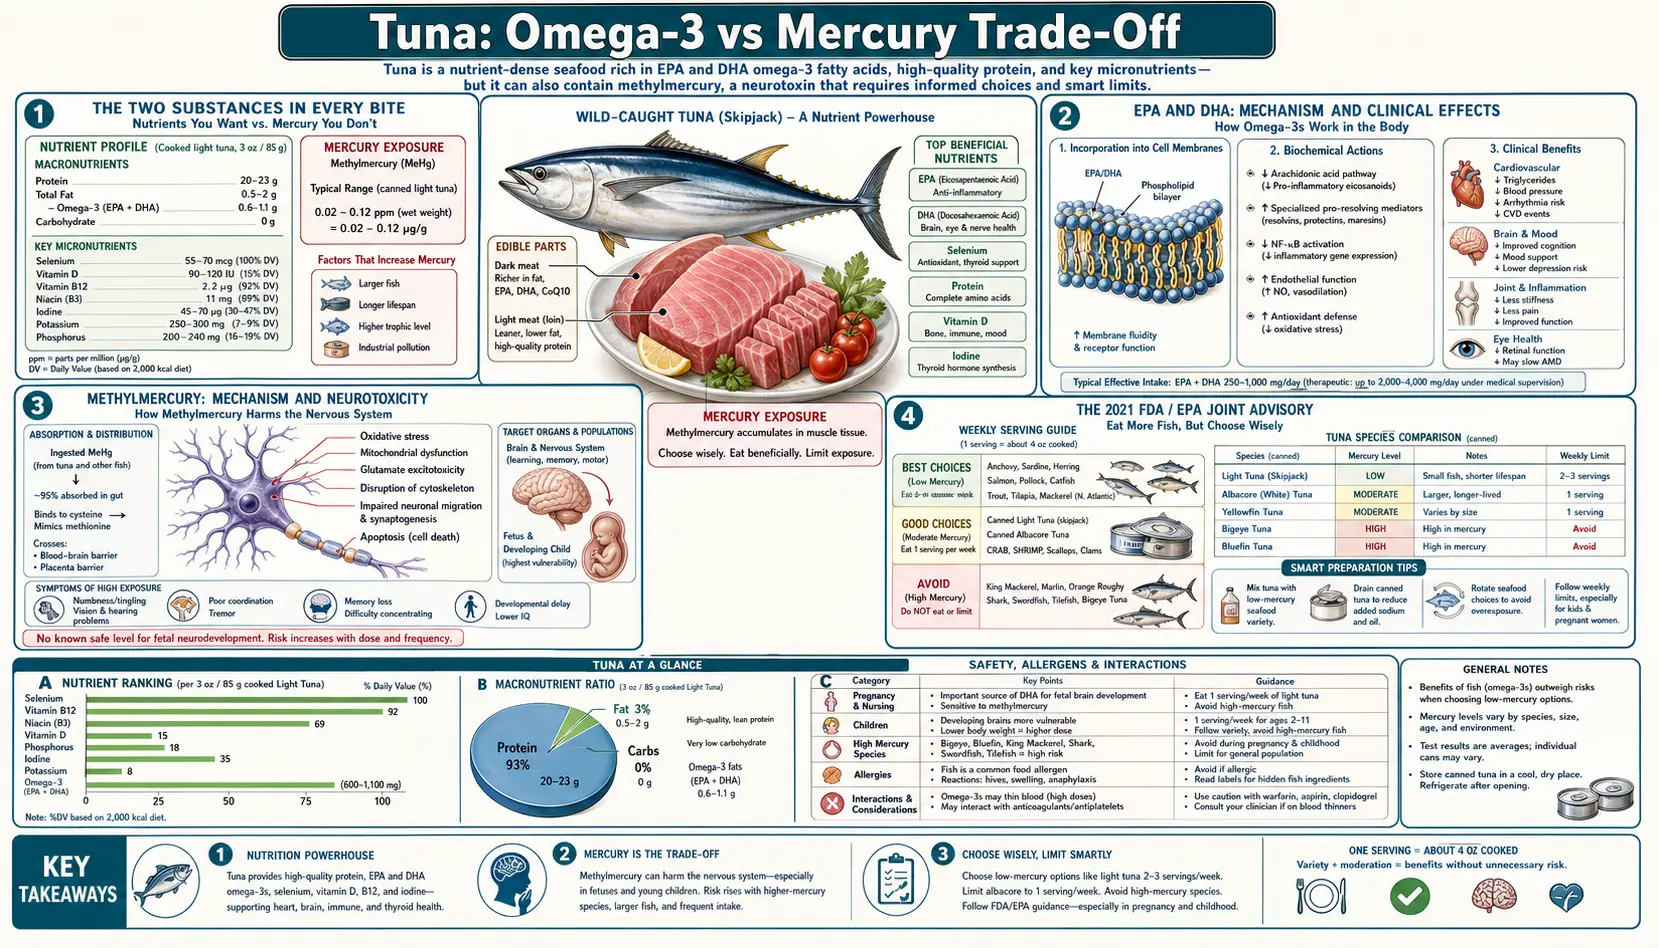
Every can of tuna delivers two things in the same bite: long-chain omega-3 fatty acids (eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA)) that the cardiovascular and central nervous systems require, and methylmercury that the marine food web concentrated from coal-fired power plant emissions. The trade-off is not philosophical — it is quantitative. The 2021 U.S. Food and Drug Administration (FDA) and Environmental Protection Agency (EPA) joint advisory translates the trade-off into weekly serving caps that differ for adults, pregnant women, and children, and that differ by tuna species by a factor of three or more. Two pivotal cohort studies (the Faroe Islands and the Seychelles) drew opposite conclusions about prenatal mercury harm at typical fish-eating exposures; the resolution involves understanding co-exposure to polychlorinated biphenyls (PCBs) in pilot whale meat and the selenium-rich nature of ocean fish. This deep-dive sets out the numbers, the studies, and what the published advice lists for each group.
Table of Contents
- The Two Substances in Every Bite
- Eicosapentaenoic Acid and Docosahexaenoic Acid: Mechanism and Clinical Effects
- Methylmercury: Mechanism and Neurotoxicity
- The 2021 U.S. Food and Drug Administration / U.S. Environmental Protection Agency Joint Advisory
- Faroese vs Seychelles: Two Cohorts, Two Conclusions
- Selenium-Mercury Antagonism
- The Hair Mercury Test as Biomarker
- Practical Heuristics by Population
- Key Research Papers
- Connections
- Featured Videos
The Two Substances in Every Bite
A 3-oz serving of canned light tuna in water contains approximately:
- Omega-3 fatty acids (eicosapentaenoic acid + docosahexaenoic acid): 230-280 mg
- Mercury: U.S. Food and Drug Administration monitoring of canned light tuna (which includes skipjack) found an average of 0.126 ppm (545 samples, 1991-2010)
- Selenium: 60-90 µg (substantially exceeding mercury on a molar basis)
- Protein: 22 g complete protein
The same 3-oz serving of canned white (albacore) tuna contains:
- Omega-3 fatty acids (eicosapentaenoic acid + docosahexaenoic acid): 700-800 mg (~3× light)
- Mercury: U.S. Food and Drug Administration monitoring of canned albacore tuna found an average of 0.350 ppm (451 samples, 1991-2009), against 0.126 ppm for canned light tuna
- Selenium: 60-90 µg (similar to light)
- Protein: 21 g complete protein
The math is not coincidental: a longer-lived larger predatory fish (albacore reaches 6-9 years and 60 lb; skipjack lives ~4-5 years and rarely exceeds 30 lb) accumulates both lipid-soluble omega-3 and methylmercury at roughly proportional rates. The omega-3 advantage of albacore is real, and so is the mercury penalty. The question is which side of the ledger weighs more for the consumer in front of you, and the answer depends on whether that consumer is a pregnant woman, a child under 11, or an adult outside those categories.
For a side-by-side species comparison including yellowfin and bluefin, see Light vs Albacore.
Eicosapentaenoic Acid and Docosahexaenoic Acid: Mechanism and Clinical Effects
Eicosapentaenoic acid (EPA, 20:5n-3) and docosahexaenoic acid (DHA, 22:6n-3) are 20- and 22-carbon polyunsaturated fatty acids with five and six double bonds respectively. They are not strictly "essential" in the chemical sense (the body can theoretically synthesize them from the plant-source precursor alpha-linolenic acid (ALA)), but the conversion is so inefficient in humans — less than 5% of dietary alpha-linolenic acid reaches eicosapentaenoic acid, less than 0.5% reaches docosahexaenoic acid — that practical adequacy depends on direct dietary intake or supplementation.
Eicosapentaenoic acid and docosahexaenoic acid serve at least four distinct biochemical roles:
- Membrane phospholipid composition — docosahexaenoic acid in particular is highly concentrated in retinal photoreceptors and synaptic membranes in the brain. Docosahexaenoic acid is roughly 30-40% of the fatty acids in the gray matter of the prefrontal cortex.
- Eicosanoid substrate competition — eicosapentaenoic acid competes with arachidonic acid (the omega-6 precursor) for cyclooxygenase and lipoxygenase enzymes, producing series-3 prostaglandins and series-5 leukotrienes that are markedly less inflammatory than the series-2 and series-4 derivatives of arachidonic acid.
- Specialized pro-resolving mediators — eicosapentaenoic acid and docosahexaenoic acid are substrates for resolvins, protectins, and maresins — lipid mediators that actively turn off acute inflammation rather than merely failing to start it. This is a distinct mechanism from anti-inflammatory drug action.
- Triglyceride-lowering via peroxisome proliferator-activated receptor alpha (PPAR-alpha) — pharmacologic doses (2-4 g/day) reduce serum triglycerides by 25-30% via PPAR-alpha activation in the liver.
The clinical evidence ladder is well-established: the American Heart Association (AHA) recommends 2 servings of fatty fish per week for primary prevention based on the GISSI-Prevenzione, JELIS, and pooled meta-analyses. The REDUCE-IT trial (Bhatt 2019 NEJM) showed a 25% relative-risk reduction in cardiovascular events with icosapent ethyl (pure eicosapentaenoic acid) 4 g/day in statin-treated patients with elevated triglycerides. For the broader omega-3 story including supplementation strategy, see Omega-3 Fatty Acids.
Methylmercury: Mechanism and Neurotoxicity
Mercury exists in three environmentally relevant forms: elemental (Hg-0), inorganic (Hg-2+ salts), and organic methylmercury (CH3-Hg+). The form that matters for tuna consumption is methylmercury, which is biosynthesized by sulfate-reducing bacteria in sediment from inorganic mercury deposited from atmospheric coal combustion emissions. Once in the marine food web, methylmercury bioaccumulates — each trophic level concentrates it roughly 10-fold over its prey, so a 4-trophic-level predator like tuna ends up with mercury concentrations 10,000× the seawater background.
Methylmercury is highly bioavailable: 95%+ is absorbed from the gut, vs ~10% for inorganic mercury salts. Once absorbed, methylmercury crosses two critical barriers that inorganic mercury does not:
- Blood-brain barrier — methylmercury complexes with the amino acid cysteine to form a structural analog of methionine, which is then transported across the blood-brain barrier by the large-neutral amino acid transporter (LAT1).
- Placenta — methylmercury reaches the fetal circulation at concentrations equal to or greater than maternal blood, and accumulates in the developing fetal brain.
Inside cells, methylmercury binds with extraordinarily high affinity to thiol (-SH) groups, particularly cysteine residues on selenoproteins, on glutathione, and on tubulin. The dominant mechanism of neurotoxicity is currently thought to be inhibition of selenium-dependent antioxidant enzymes (glutathione peroxidase, thioredoxin reductase) in neurons, leading to oxidative stress and disruption of microtubule-dependent neuronal migration during fetal brain development.
Adult exposure at the levels typical of US fish consumers does not produce frank Minamata-disease-like symptoms (those required the much higher industrial methylmercury exposures of Minamata, Japan in the 1950s). The concerns at typical exposure are subtler: subclinical paresthesias, fine-motor coordination decrements measurable on neuropsychological testing, and possibly cardiovascular effects (in a cohort of eastern Finnish men, those in the highest third of hair mercury, 2.0 µg/g or more, had twice the adjusted risk of a heart attack (acute myocardial infarction) and 2.9 times the risk of cardiovascular death; the mercury came mainly from local nonfatty freshwater fish). For more on mercury toxicology generally, see Mercury.
The 2021 U.S. Food and Drug Administration / U.S. Environmental Protection Agency Joint Advisory
The current US guidance is the 2021 joint advisory from the U.S. Food and Drug Administration and Environmental Protection Agency, which organizes commercial fish into three categories:
- "Best Choices" (2-3 servings per week): canned light tuna, salmon, sardines, anchovies, herring, tilapia, cod, catfish, shrimp, scallops, oysters — 36 types of fish and shellfish in all. Mercury concentration generally below 0.15 ppm.
- "Good Choices" (1 serving per week): canned white (albacore) tuna, fresh tuna (yellowfin), halibut, Chilean sea bass, snapper, mahi-mahi, monkfish. Mercury 0.15-0.45 ppm.
- "Choices to Avoid" during pregnancy, lactation, and for children: swordfish, shark, king mackerel, tilefish from the Gulf of Mexico, bigeye tuna, marlin, orange roughy. Mercury >0.45 ppm.
For canned tuna specifically:
- Adults in general: the FDA/EPA chart itself is written for people who might become or are pregnant or breastfeeding and for children aged 1 to 11. For adults in general, the FDA advice page cites the Dietary Guidelines for Americans, which recommend at least 8 ounces of seafood per week on a 2,000-calorie diet.
- Pregnant or breastfeeding: one serving is 4 ounces. The advice lists 2 to 3 servings a week from the "Best Choices" list (canned light tuna is on it), OR 1 serving a week from the "Good Choices" list (canned and fresh/frozen albacore and yellowfin are on it). Bigeye tuna is on the "Choices to Avoid" list; bluefin does not appear on the chart.
- Children 1-3: a serving is about 1 ounce, and the advice lists 2 servings a week from the "Best Choices" list.
- Children 4-7: a serving is about 2 ounces, 2 servings a week from the "Best Choices" list.
- Children 8-10: a serving is about 3 ounces, 2 servings a week from the "Best Choices" list.
- Children aged 11: a serving is about 4 ounces, 2 servings a week from the "Best Choices" list. The childhood advice names only the "Best Choices" list; albacore is on the "Good Choices" list.
The advice states that fish intake during pregnancy is recommended because moderate scientific evidence shows it can help the baby's cognitive development, and that while it is important to limit mercury in the diets of those who are pregnant or breastfeeding and children, many types of fish are both nutritious and lower in mercury. The Hibbeln analysis of the Avon Longitudinal Study of Parents and Children (ALSPAC; 2007, Lancet) followed 11,875 pregnancies. At the time, U.S. advice limited seafood in pregnancy to 340 g (12 oz) a week. Compared with mothers who ate more than 340 g a week, mothers who ate no seafood had 1.48 times the odds of a child in the lowest quarter for verbal IQ. For each outcome measured in the children between 6 months and 8 years of age, the lower the mother's seafood intake in pregnancy, the higher the risk of a poorer result: maternal intake above the then-recommended cap was associated with better child development, not worse.
Faroese vs Seychelles: Two Cohorts, Two Conclusions
The methylmercury-and-fetal-neurodevelopment literature is dominated by two large cohort studies that arrived at opposite conclusions and shaped two decades of regulatory debate.
The Faroe Islands Children's Health Study (Philippe Grandjean and colleagues, University of Southern Denmark, 1986 onward) followed approximately 1,000 Faroese children from birth. The Faroese diet is unusual: in addition to ocean fish, the population consumes pilot whale meat at substantial frequency. Pilot whale is highly contaminated with both methylmercury and persistent organic pollutants (PCBs and chlorinated pesticides). The Faroese cohort found dose-dependent neurodevelopmental decrements at age 7 (language, attention, memory) associated with prenatal mercury exposure measured in maternal hair and cord blood.
The Seychelles Child Development Study (Philip Davidson, Gary Myers and colleagues, University of Rochester, 1989 onward) followed approximately 700 children in the Republic of Seychelles, where ocean fish consumption averages 12 meals per week (vs ~2/week in the US). The Seychellois cohort found no association between prenatal mercury exposure and neurodevelopmental outcomes at multiple time points (24 months, 5.5 years, 9 years, 17 years).
The differences between the two cohorts are now understood as the explanation for the discrepancy:
- Co-exposure differences — Faroese children had substantial co-exposure to PCBs (from pilot whale blubber) that the Seychellois did not. PCBs are independent neurodevelopmental toxicants.
- Mercury exposure pattern — the Faroese had peak mercury exposures coinciding with pilot whale hunts (intermittent high doses); the Seychellois had steady daily fish-meal exposure (lower peaks).
- Nutritional context — the Seychellois cohort was eating ocean fish rich in selenium and omega-3 fatty acids, both of which appear to mitigate mercury neurotoxicity. The pilot whale meat in the Faroese diet does not have the same omega-3 profile.
The current synthesis (National Research Council (NRC) 2000 report, U.S. Environmental Protection Agency 2002, European Food Safety Authority (EFSA) 2012) is that the Faroese results probably represent the worst-case exposure pattern, the Seychellois results represent the typical-fish-diet pattern, and the truth for US consumers eating ocean fish (not pilot whale) is closer to the Seychellois finding. The U.S. Environmental Protection Agency (EPA) reference dose (RfD) of 0.1 µg methylmercury/kg/day is conservatively derived from the Faroese data with a 10× uncertainty factor.
A newer Seychelles group, the Seychelles Child Development Study Nutrition Cohort 2, tested 1,237 children at age 7 on 17 measures covering thinking, attention and movement skills, language, behaviour, school achievement and social communication (Strain 2021). The mother's mercury level in pregnancy, measured in her hair, was not linked to any of the 17 results. The mother's blood levels of omega-3 and omega-6 fats in pregnancy did not change how mercury related to the results.
Selenium-Mercury Antagonism
Selenium and mercury have an extraordinarily high binding affinity for each other — the formation constant for selenium-mercury complexes exceeds that of any other biologically relevant metal-mineral interaction. This has practical implications.
Methylmercury exerts most of its toxicity by binding to and inhibiting selenoenzymes (glutathione peroxidase, thioredoxin reductase, iodothyronine deiodinase). When dietary selenium is abundant, two protective mechanisms operate:
- Selenium intercepts methylmercury directly, forming biologically inert HgSe (mercury selenide) complexes that are sequestered and excreted without disrupting selenoenzyme function.
- Adequate dietary selenium supports replacement synthesis of selenoenzymes faster than methylmercury can inhibit them.
Ocean fish, including tuna, are unusually selenium-rich — the molar selenium content of nearly every ocean fish species exceeds its mercury content, often by a factor of 3-10. This is the basis for the "selenium health benefit value" proposed by Nicholas Ralston and Laura Raymond: an index defined as (Se-Hg)/Se, with positive values indicating net selenium surplus. By this index, skipjack, salmon, sardines, and most ocean fish have strongly positive selenium health benefit values, while tilefish, swordfish, shark, and pilot whale have negative values (mercury exceeds selenium on a molar basis).
The selenium health benefit value framework is not currently used by U.S. Food and Drug Administration in advisories (which are based on total mercury), but it explains why the Seychelles cohort, eating mostly small-to-medium ocean fish, showed no neurodevelopmental harm despite mercury exposures that would have been concerning under a mercury-only framework. For more on selenium itself, see Selenium.
The Hair Mercury Test as Biomarker
For consumers (or clinicians) who want to verify that fish consumption is staying within safe limits, hair mercury testing is the standard biomarker. Hair grows approximately 1 cm/month and incorporates methylmercury into the keratin matrix at roughly 250× the steady-state blood concentration. A 1-cm hair segment closest to the scalp reflects approximately the previous month's exposure; longer segments give a longitudinal record.
Reference values for hair mercury:
- <1 µg/g — typical for low fish consumers in the US
- 1-2 µg/g — moderate fish consumer; well within the safety level derived from the U.S. Environmental Protection Agency reference dose
- 2-5 µg/g — heavy fish consumer; approaching but not exceeding the U.S. Environmental Protection Agency reference-dose-derived safety threshold of approximately 4-5 µg/g in hair
- >5 µg/g — exceeds the hair threshold derived from the U.S. Environmental Protection Agency reference dose; the highest-mercury fish on the FDA/EPA chart include swordfish, shark, tilefish (Gulf of Mexico), bigeye tuna and marlin, and a repeat test after 3-6 months shows whether a change in intake has lowered the level
- >10 µg/g — substantial exceedance; in people with symptoms, care at this level can include clinical evaluation, stopping dietary mercury, and chelation with dimercaptosuccinic acid (DMSA)
For pregnant women, the World Health Organization (WHO) benchmark for fetal effects is approximately 11 µg/g in maternal hair, with a 10× safety factor giving a target of <1 µg/g pre-conception and during pregnancy. Most US women fall below 1 µg/g; women who eat sushi-grade tuna or swordfish more than once a week sometimes exceed it.
Hair mercury testing is available through commercial laboratories for $30-100. Blood mercury is faster-responding (half-life ~50 days) but less stable. Whole-blood mercury >5.8 µg/L is the U.S. Centers for Disease Control and Prevention-defined elevation threshold. For mercury testing options and interpretation, see Lab Tests.
Practical Heuristics by Population
- Average adult, not pregnant: the Dietary Guidelines for Americans, cited on the FDA advice page, recommend at least 8 ounces of seafood a week. A 3-oz serving of canned light tuna carries 230-280 mg of omega-3 and one of albacore 700-800 mg (figures above); the FDA's average mercury levels are 0.126 ppm for canned light tuna and 0.350 ppm for canned albacore.
- Pregnant, breastfeeding or trying to conceive: the FDA/EPA advice lists 2 to 3 four-ounce servings a week from "Best Choices" (canned light tuna is one) OR 1 from "Good Choices" (albacore is one). A hair mercury test, before conception or at 12-16 weeks of pregnancy, is compared against the <1 µg/g target described above.
- Children under 11: the FDA/EPA advice gives a serving of about 1, 2, 3 and 4 ounces at ages 1-3, 4-7, 8-10 and 11, and lists 2 servings a week from the "Best Choices" list, which includes canned light tuna; albacore is on the "Good Choices" list, which the childhood advice does not name. The FDA page also quotes the Dietary Guidelines for Americans: children eating more fish than the FDA/EPA amounts are to be fed only the lowest-mercury "Best Choices" fish, a list that includes salmon, sardines, anchovies and shrimp but not canned light tuna.
- Heavy sushi consumer (yellowfin, bluefin, bigeye 3+ times per week): FDA monitoring found average mercury of 0.354 ppm in fresh/frozen yellowfin and 0.689 ppm in fresh/frozen bigeye. Most heavy sushi eaters fall in the 2-5 µg/g hair range; some exceed 10 µg/g.
- Anyone with autoimmune disease, kidney disease, or unexplained neurological symptoms: a hair mercury test is sometimes part of a broader workup, though mercury is rarely the primary driver.
- Concerned about both mercury and omega-3: canned light tuna (which includes skipjack) is the only tuna on the FDA/EPA "Best Choices" list. Salmon (wild Pacific or farmed Atlantic, both low-mercury, high-omega-3) and sardines are on the same list. Eicosapentaenoic acid/docosahexaenoic acid from a fish oil or algal oil supplement (mercury removed during manufacture) takes the mercury side out of the trade-off for the omega-3 portion of the diet.
For broader cardiovascular and cognitive context, see Cardiology and Neurology.
Key Research Papers
- Mozaffarian D, Rimm EB (2006). Fish intake, contaminants, and human health: evaluating the risks and the benefits. JAMA 296(15):1885-99. — PubMed PMID: 17047219
- Hibbeln JR et al. (2007). Maternal seafood consumption in pregnancy and neurodevelopmental outcomes in childhood (ALSPAC study): an observational cohort study. Lancet 369(9561):578-85. — PubMed PMID: 17307104
- Grandjean P et al. (1997). Cognitive deficit in 7-year-old children with prenatal exposure to methylmercury. Neurotoxicology and Teratology 19(6):417-28. — PubMed PMID: 9392777
- Davidson PW et al. (1998). Effects of prenatal and postnatal methylmercury exposure from fish consumption on neurodevelopment: outcomes at 66 months of age in the Seychelles Child Development Study. JAMA 280(8):701-7. — PubMed PMID: 9728641
- Myers GJ et al. (2003). Prenatal methylmercury exposure from ocean fish consumption in the Seychelles child development study. Lancet 361(9370):1686-92. — PubMed PMID: 12767734
- Ralston NVC, Raymond LJ (2010). Dietary selenium's protective effects against methylmercury toxicity. Toxicology 278(1):112-23. — PubMed PMID: 20561558
- Karimi R, Fitzgerald TP, Fisher NS (2012). A quantitative synthesis of mercury in commercial seafood and implications for exposure in the United States. Environmental Health Perspectives 120(11):1512-9. — PubMed PMID: 22732656
- Mahaffey KR et al. (2011). Balancing the benefits of n-3 polyunsaturated fatty acids and the risks of methylmercury exposure from fish consumption. Nutrition Reviews 69(9):493-508. — PubMed PMID: 21884130
- Strain JJ et al. (2008). Associations of maternal long-chain polyunsaturated fatty acids, methyl mercury, and infant development in the Seychelles Child Development Nutrition Study. Neurotoxicology 29(5):776-82. — PubMed PMID: 18590765
- Choi AL et al. (2009). Methylmercury exposure and adverse cardiovascular effects in Faroese whaling men. Environmental Health Perspectives 117(3):367-72. — PubMed PMID: 19337510
- Salonen JT et al. (1995). Intake of mercury from fish, lipid peroxidation, and the risk of myocardial infarction. Circulation 91(3):645-55. — PubMed PMID: 7828289
- Bhatt DL et al. (2019). Cardiovascular risk reduction with icosapent ethyl for hypertriglyceridemia (REDUCE-IT). NEJM 380(1):11-22. — PubMed PMID: 30415628
- Strain JJ et al. (2021). Associations of prenatal methylmercury exposure and maternal polyunsaturated fatty acid status with neurodevelopmental outcomes at 7 years of age: results from the Seychelles Child Development Study Nutrition Cohort 2. American Journal of Clinical Nutrition 113(2):304-313. — PubMed PMID: 33330939