Complex Regional Pain Syndrome (CRPS)
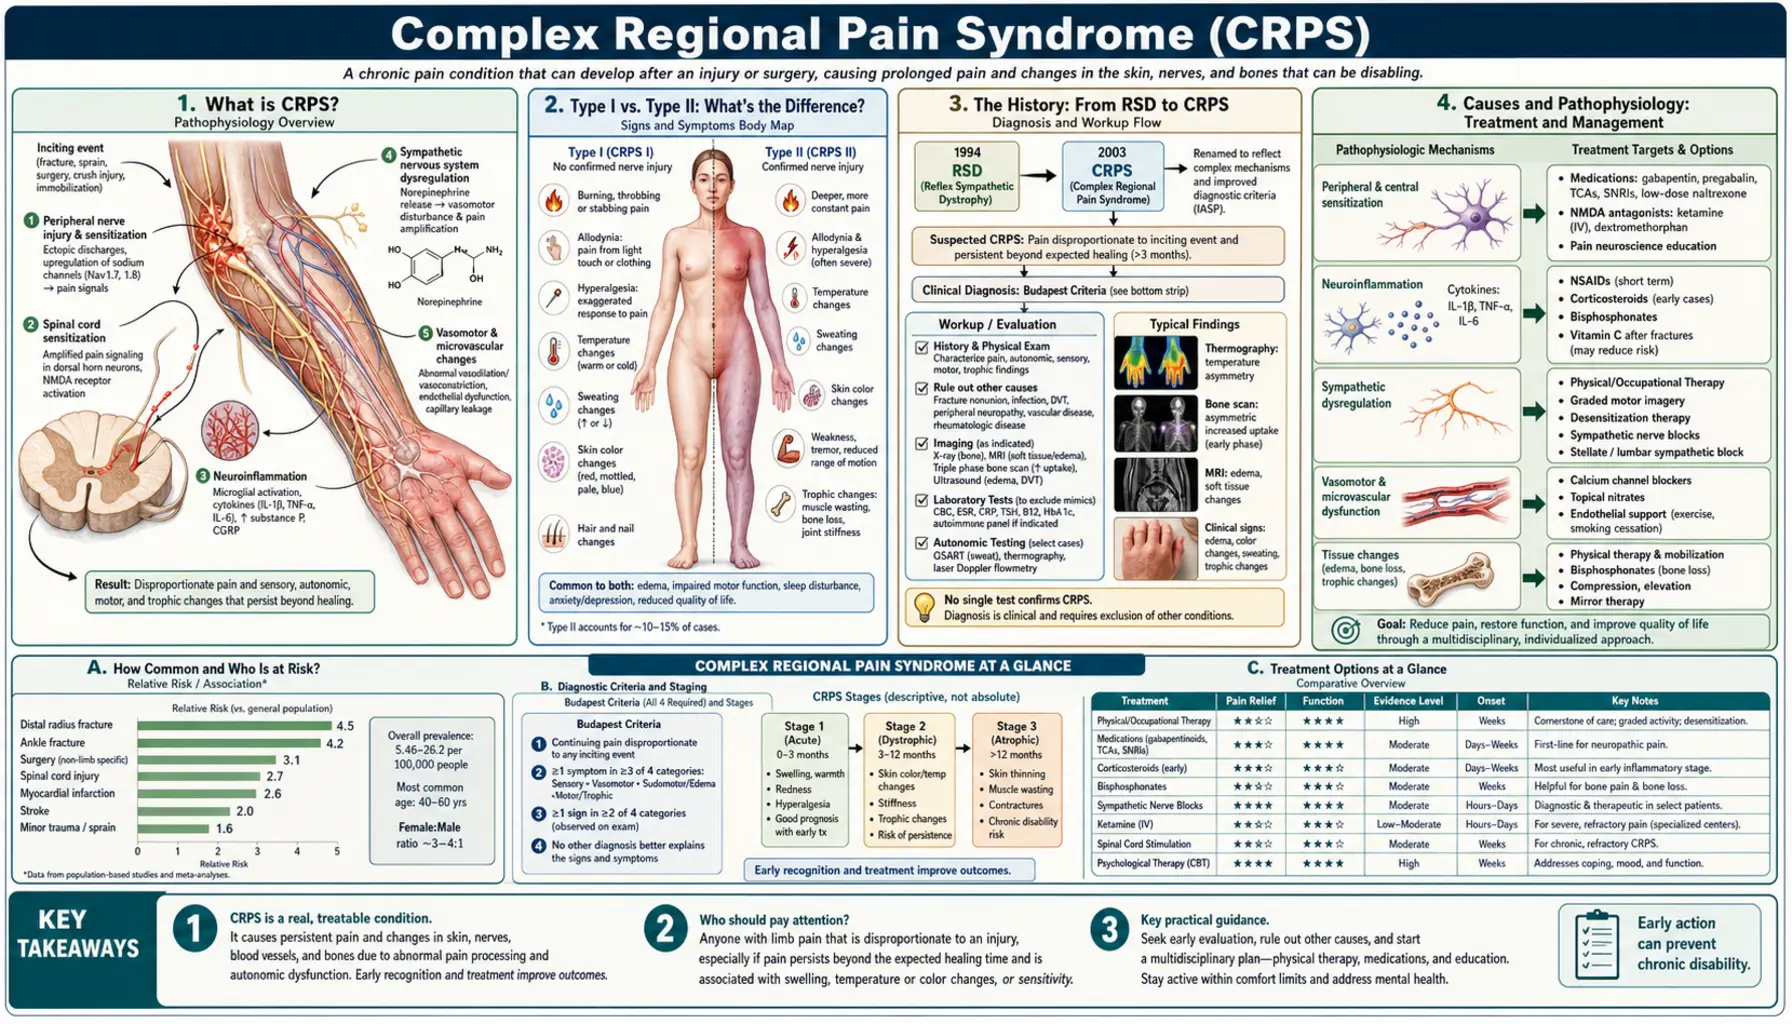
- What CRPS Is
- How Type I and Type II Differ
- The History: From RSD to CRPS
- Causes and Pathophysiology
- Budapest Criteria: How CRPS is Diagnosed
- Stages and Progression
- Conventional Treatment
- Mirror Therapy and Graded Motor Imagery
- Low-Dose Naltrexone
- Natural and Lifestyle Approaches
- Complications
- Key Research Papers
- Connections
What CRPS Is
Complex Regional Pain Syndrome (CRPS) is a chronic pain condition characterized by severe, out-of-proportion pain — usually in a limb (arm, leg, hand, or foot) — along with abnormal changes in skin color, temperature, and texture, and autonomic nervous system dysfunction. Pain is typically burning or aching and disproportionate to any observable tissue injury.
CRPS develops after an initiating event (injury, surgery, or occasionally spontaneously) but then takes on a life of its own, independent of the original injury healing. A population-based study of 600,000 patients' records in the Netherlands (de Mos and colleagues, 2007) found about 26 new cases per 100,000 people each year; women were affected 3.4 times more often than men, and a fracture was the most common trigger (44% of cases). Onset most commonly occurs after a fracture or sprain, particularly of the wrist (Colles' fracture is a classic trigger) or ankle.
How Type I and Type II Differ
CRPS Type I (formerly Reflex Sympathetic Dystrophy, RSD): No confirmed nerve damage. Pain and symptoms arise without identifiable nerve injury — the nervous system has essentially "gone wrong" on its own. This is by far the more common form (~90% of cases). The mechanisms involve peripheral and central sensitization, neuroinflammation, and sympathetic nervous system dysregulation.
CRPS Type II (formerly Causalgia): Occurs after a confirmed, identifiable nerve injury (e.g., from surgery, laceration, or crush injury). The distribution of pain and symptoms follows the injured nerve's territory. Despite having a confirmed nerve cause, treatment approaches overlap significantly with Type I.
In practice, both types cause the same constellation of signs and symptoms and are managed similarly.
The History: From RSD to CRPS
CRPS has been recognized since the American Civil War, when surgeon Silas Weir Mitchell described "causalgia" — burning pain in soldiers after peripheral nerve injuries. The term Reflex Sympathetic Dystrophy (RSD) dominated for decades and implied that an overactive sympathetic nervous system was always responsible.
However, research showed that sympathetically independent pain is common in CRPS, and the "reflex" and "sympathetic" terminology was misleading. In 1994, the International Association for the Study of Pain (IASP) renamed the condition Complex Regional Pain Syndrome. Many patients and advocacy groups still use the terms RSD and CRPS interchangeably.
Causes and Pathophysiology
CRPS develops when the normal healing process goes wrong in multiple systems simultaneously. Key mechanisms:
- Peripheral sensitization: Damaged tissues release inflammatory mediators (substance P, CGRP, bradykinin, nerve growth factor) that lower the pain threshold in local nociceptors — they fire with less stimulation.
- Central sensitization: The spinal cord and brain rewire in response to persistent peripheral input; pain signals are amplified and persist even after peripheral healing.
- Neuroinflammation: Pro-inflammatory cytokines (tumor necrosis factor alpha, interleukin-1 beta, interleukin-6) remain chronically elevated in the affected limb; neuropeptides cause ongoing vasodilation and tissue changes.
- Sympathetic-sensory coupling: Sympathetic nerve fibers grow abnormal sprouts around dorsal root ganglion neurons, creating cross-talk that did not exist before — this is why emotional stress and temperature changes provoke CRPS pain.
- Cortical reorganization: The brain region representing the affected limb in the somatosensory cortex shrinks and reorganizes — which is why mirror therapy and graded motor imagery work.
Budapest Criteria: How CRPS is Diagnosed
There is no blood test or imaging finding that confirms CRPS. Diagnosis is clinical, based on the Budapest Criteria, proposed at a 2003 meeting in Budapest and validated in 2010: in that study they kept almost all of the older IASP criteria's sensitivity (0.99) while greatly improving specificity (0.68, against 0.41). In 2021 an international group published an updated version, the "Valencia consensus-based adaptation" of these criteria. The patient must meet all of the following:
- Continuing pain disproportionate to any inciting event.
- Reports of at least one symptom in 3 of 4 categories: sensory (allodynia/hyperalgesia), vasomotor (temperature/color changes), sudomotor/edema (swelling, sweating), motor/trophic (weakness, tremor, nail/hair/skin changes).
- Displays at least one sign in 2 or more categories at the time of evaluation.
- No other diagnosis better explains the symptoms.
Supportive testing: three-phase bone scan (hot spots in early CRPS); skin temperature asymmetry greater than 1°C; X-ray (patchy osteoporosis in chronic CRPS); MRI (bone marrow edema pattern).
Stages and Progression
The traditional three-stage model (Stage 1: acute — warm, red, painful; Stage 2: dystrophic — cooling, mottled, stiffening; Stage 3: atrophic — cold, pale, wasted muscle) is now considered an oversimplification. CRPS does not progress in a linear, predictable fashion. Many patients plateau or partially recover at any point. Some cases spontaneously remit, especially pediatric cases. Longer duration without treatment predicts worse outcomes.
Conventional Treatment
Care usually combines several approaches:
- Physical and occupational therapy: The cornerstone. Graded exposure, desensitization, edema control, range-of-motion exercises, mirror therapy, and graded motor imagery. Early mobilization is critical.
- Medications: Gabapentin/pregabalin (reduce central sensitization); tricyclic antidepressants (amitriptyline — neuropathic pain and sleep); serotonin-norepinephrine reuptake inhibitors (duloxetine); low-dose naltrexone (LDN — see dedicated section); corticosteroids (short course in acute CRPS only); ketamine infusions (N-methyl-D-aspartate (NMDA) receptor antagonist — used in refractory cases at specialized centers); calcitonin (addresses bone pain and osteoporosis component); bisphosphonates (pamidronate/alendronate; a 2013 placebo-controlled trial of the bisphosphonate neridronate was in early (acute) CRPS type I — see below).
- Interventional procedures: Sympathetic nerve blocks (stellate ganglion for upper extremity, lumbar sympathetic for lower extremity); spinal cord stimulation (SCS) — FDA-approved; in the key randomized trial (Kemler and colleagues, 2000; 36 people given stimulation plus physical therapy, 18 given physical therapy alone), pain fell by an average of 2.4 cm on a 10-cm scale at six months against a 0.2 cm rise with physical therapy alone, but daily function did not improve in a clinically important way; quality of life improved only in the 24 people whose trial stimulation worked and who received an implant, and 6 of those 24 needed further procedures, including removal of the device in 1; intrathecal drug delivery.
- Psychological interventions: cognitive behavioral therapy (CBT), acceptance and commitment therapy (ACT), pain neuroscience education — essential components of comprehensive care.
Neridronate trial: In a 2013 Italian placebo-controlled trial of 82 people with early (acute) CRPS type I of the hand or foot, four intravenous infusions of 100 mg of the bone drug neridronate over 10 days lowered pain by 46.5 mm on a 100-mm scale over the following 20 days, against 22.6 mm with placebo; a year later none of the patients reported symptoms linked to CRPS type I. Neridronate is a bisphosphonate.
Mirror Therapy and Graded Motor Imagery
Two of the most evidence-supported non-invasive treatments for CRPS — both targeting the brain's representation of the affected limb.
Mirror therapy: A box with a mirror placed vertically in the patient's midline. The unaffected limb performs exercises and is reflected in the mirror while the affected limb is hidden. The brain receives visual feedback of a "normal" moving limb in the affected side's position — this retrains motor and sensory cortex representation. Best evidence is for hand/arm CRPS.
Graded Motor Imagery (GMI): A 3-stage program: (1) left/right limb recognition training (using smartphone apps showing photos — reactivates cortical lateralization); (2) imagined movements without actually moving; (3) mirror therapy. GMI addresses cortical reorganization step by step. The evidence comes from small trials: in a 2005 randomized trial of 20 people with CRPS after a wrist fracture, pain and disability fell more when the three steps were done in this order than in other orders; in a 2006 randomized trial of 51 people with CRPS type I or phantom limb pain, pain fell 23.4 mm on a 100-mm scale with graded motor imagery against 10.5 mm with physical therapy and usual care, and gains were kept at 6 months. A 2024 review of 6 randomized trials of graded motor imagery and mirror therapy found they reduced pain and improved function, but noted small sample sizes and mixed designs that limit how far the findings apply.
Low-Dose Naltrexone
Naltrexone is an opioid receptor antagonist approved in standard doses (50 mg/day) for addiction. At low doses (1.5–4.5 mg/day, taken at bedtime), it paradoxically acts as an anti-inflammatory and neuroprotective agent by briefly blocking opioid receptors — causing a rebound increase in endorphin production (the endorphin upregulation hypothesis) — and most importantly by blocking TLR4 receptors on microglia, the brain's immune cells. This reduces microglial activation and neuroinflammation.
Case series, small trials, and patient reports support low dose naltrexone's benefit in CRPS. A protocol commonly described by practitioners starts at 1.5 mg/night, rises to 3 mg after 2 weeks, then to 4.5 mg. These doses are made up by compounding pharmacies (standard 50 mg tablets cannot be split accurately to these doses). Side effects are generally mild (vivid dreams for the first few weeks).
Natural and Lifestyle Approaches
- Vitamin C: Trials of vitamin C taken for about 50 days after a wrist fracture disagree. In a 1999 trial (123 adults), CRPS (then called reflex sympathetic dystrophy) occurred in 7% of wrists on 500 mg/day against 22% on placebo; a larger 2007 trial (416 patients) found CRPS in 1.8% on 500 mg/day and 1.7% on 1,500 mg/day against 10.1% on placebo, while 200 mg/day made no significant difference. A 2014 Scottish trial (336 adults with a broken wrist end of the forearm bone, 500 mg/day) found no difference in the CRPS rate at one year and concluded vitamin C gave no benefit. A 2022 meta-analysis of 8 studies linked vitamin C with a lower CRPS rate after wrist, foot and ankle injuries or surgery (odds ratio 0.33); a 2024 meta-analysis of 8 studies found the pooled effect was not statistically significant and detected publication bias.
- Alpha-lipoic acid (ALA): 600 mg three times daily; reduces oxidative stress in neural tissue; evidence exists in diabetic neuropathy and emerging evidence in CRPS.
- Magnesium: A N-methyl-D-aspartate receptor modulator; reduces central sensitization; intravenous (IV) magnesium is used in some ketamine protocols; oral magnesium glycinate 300–400 mg/day is used by some people as an add-on.
- Swimming or hydrotherapy: Water provides gentle resistance and desensitization without weight-bearing; often the only tolerated exercise in early CRPS.
- Mindfulness-based stress reduction (MBSR): Reduces pain catastrophizing and central sensitization amplification; well-validated in chronic pain generally.
- Anti-inflammatory diet: A Mediterranean-pattern diet with an omega-3 emphasis may reduce neuroinflammation and support recovery.
Complications
Psychological: Depression affects approximately 50% of CRPS patients, along with anxiety and post-traumatic stress disorder (PTSD) — all of which are linked to worse pain. Suicide risk is elevated in severe chronic CRPS.
Physical: Muscle atrophy and contractures from immobility; skin fragility; osteoporosis (especially in the affected limb); and spread to other limbs (approximately 35% of cases with severe CRPS eventually experience spread to additional limbs). In a Dutch series of 185 people with CRPS, 89 had it in more than one limb; spread to a second limb was most often to the opposite limb (49%), then to the limb on the same side (30%), while diagonal spread (14%) was rare and usually followed a new injury. Spread was linked with a younger age at onset and more severe disease.
Social: Disability, job loss, and relationship strain from a condition that is often invisible and disbelieved by others — including medical professionals. CRPS in children and adolescents typically has a better prognosis with aggressive physical therapy and family-centered care.
Key Research Papers
- Harden RN, et al. Validation of proposed diagnostic criteria (the "Budapest Criteria") for complex regional pain syndrome. Pain. 2010. — PubMed PMID: 20493633
- Search PubMed
- Moseley GL. Graded motor imagery for pathologic pain: a randomized controlled trial. Neurology. 2006;67(12):2129-34. — PubMed PMID: 17082465
- Search PubMed
- Kemler MA, Barendse GA, van Kleef M, et al. Spinal cord stimulation in patients with chronic reflex sympathetic dystrophy. N Engl J Med. 2000;343(9):618-24. — PubMed PMID: 10965008
- Zollinger PE, Tuinebreijer WE, Kreis RW, Breederveld RS. Effect of vitamin C on frequency of reflex sympathetic dystrophy in wrist fractures: a randomised trial. Lancet. 1999;354(9195):2025-8. — PubMed PMID: 10636366
- Search PubMed
- de Mos M, de Bruijn AG, Huygen FJ, et al. The incidence of complex regional pain syndrome: a population-based study. Pain. 2007;129(1-2):12-20. — PubMed PMID: 17084977
- Search PubMed
- Search PubMed
- Search PubMed
- Zollinger PE, Tuinebreijer WE, Breederveld RS, Kreis RW. Can vitamin C prevent complex regional pain syndrome in patients with wrist fractures? A randomized, controlled, multicenter dose-response study. J Bone Joint Surg Am. 2007;89(7):1424-31. — PubMed PMID: 17606778
- Ekrol I, Duckworth AD, Ralston SH, Court-Brown CM, McQueen MM. The influence of vitamin C on the outcome of distal radial fractures: a double-blind, randomized controlled trial. J Bone Joint Surg Am. 2014;96(17):1451-9. — PubMed PMID: 25187584
- Seth I, Bulloch G, Seth N, et al. Effect of Perioperative Vitamin C on the Incidence of Complex Regional Pain Syndrome: A Systematic Review and Meta-Analysis. J Foot Ankle Surg. 2022;61(4):748-754. — PubMed PMID: 34961681
- Ranjbar Moghaddam M, Nasiri-Formi E, Merajikhah A. Efficacy of vitamin C supplementation in preventing and treating complex regional pain syndrome type I (CRPS-I) in Orthopedic patients: A systematic review and meta-analysis. Int J Orthop Trauma Nurs. 2024;55:101140. — PubMed PMID: 39447383
- Varenna M, Adami S, Rossini M, et al. Treatment of complex regional pain syndrome type I with neridronate: a randomized, double-blind, placebo-controlled study. Rheumatology (Oxford). 2013;52(3):534-42. — PubMed PMID: 23204550
- Moseley GL. Is successful rehabilitation of complex regional pain syndrome due to sustained attention to the affected limb? A randomised clinical trial. Pain. 2005;114(1-2):54-61. — PubMed PMID: 15733631
- Donati D, Boccolari P, Giorgi F, et al. Breaking the Cycle of Pain: The Role of Graded Motor Imagery and Mirror Therapy in Complex Regional Pain Syndrome. Biomedicines. 2024;12(9):2140. — PubMed PMID: 39335652
- Goebel A, Birklein F, Brunner F, et al. The Valencia consensus-based adaptation of the IASP complex regional pain syndrome diagnostic criteria. Pain. 2021;162(9):2346-2348. — PubMed PMID: 33729210
- van Rijn MA, Marinus J, Putter H, et al. Spreading of complex regional pain syndrome: not a random process. J Neural Transm (Vienna). 2011;118(9):1301-9. — PubMed PMID: 21331457
PubMed Topic Searches
Connections
- Pain & Allergy
- Chronic Pain
- Neuropathic Pain
- Migraine
- Complex Regional Pain Syndrome (CRPS / RSD): the full deep dive — the longer chronic-pain treatment of the same condition, covering the Budapest criteria in detail, bisphosphonates, ketamine infusions, sympathetic blocks, spinal-cord stimulation, and vitamin C prophylaxis after wrist fracture.
- Fibromyalgia
- Depression
- Anxiety
- Vitamin C
- Magnesium