Diabetic Nephropathy
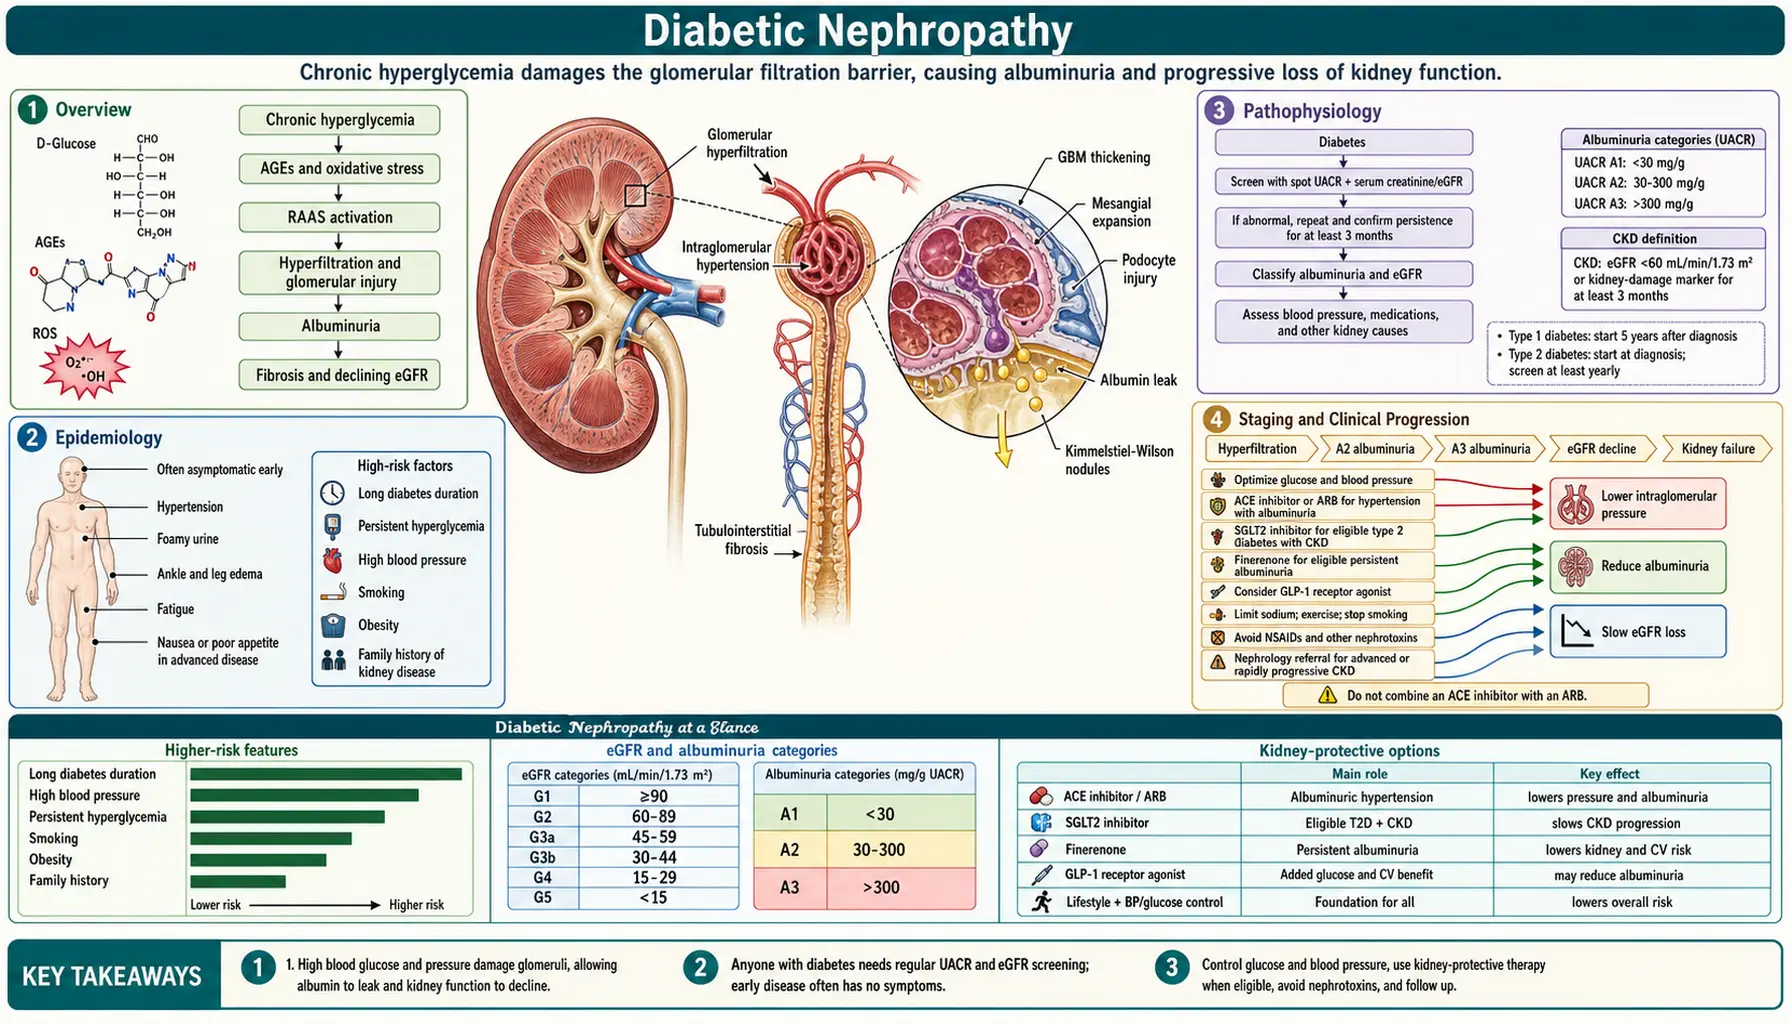
Diabetic nephropathy (DN), also called diabetic kidney disease (DKD), is the most common cause of end-stage renal disease (ESRD) in the United States and worldwide. It affects 30–40% of people with type 1 diabetes and 20–30% with type 2 diabetes over their lifetime. DN results from sustained hyperglycemia activating multiple injurious pathways in the glomerulus, leading to characteristic pathological changes — glomerular hypertrophy, basement membrane thickening, mesangial expansion, and ultimately Kimmelstiel-Wilson nodular glomerulosclerosis. It is defined clinically by progressive albuminuria and declining kidney function in the setting of diabetes, typically without need for kidney biopsy. Modern treatment with renin-angiotensin-aldosterone system (RAAS) blockade, sodium-glucose cotransporter-2 (SGLT2) inhibitors, glucagon-like peptide-1 (GLP-1) agonists, and finerenone has transformed the prognosis.
Table of Contents
- Overview
- Epidemiology
- Pathophysiology
- Staging and Clinical Progression
- Diagnosis
- Glycemic Control and Blood Pressure
- RAAS Blockade Therapy
- Sodium-Glucose Cotransporter-2 Inhibitors and Glucagon-Like Peptide-1 Agonists
- Finerenone and Novel Therapies
- Dietary and Lifestyle Management
- Prognosis and ESRD Prevention
- Key Research Papers
- Featured Videos
Overview
Diabetic nephropathy is the leading cause of ESRD in developed countries — 44% of new ESRD cases in the US arise from diabetes, according to the United States Renal Data System (USRDS) 2022 Annual Report. It represents a microvascular complication of diabetes affecting the glomerular filtration barrier. Both type 1 and type 2 diabetes cause DN through the same fundamental mechanism: sustained hyperglycemia leads to glomerular hypertension, glomerular hypertrophy, and activation of pathological signaling pathways — PKC, mTOR, TGF-β, RAAS, and NF-κB — culminating in progressive glomerulosclerosis, albuminuria, and chronic kidney disease (CKD).
The landmark Diabetes Control and Complications Trial (DCCT, 1993) for type 1 diabetes and the United Kingdom Prospective Diabetes Study (UKPDS, 1998) for type 2 diabetes proved that tight glycemic control prevents or delays DN development. The treatment revolution of the 2020s — sodium-glucose cotransporter-2 inhibitors, finerenone, and glucagon-like peptide-1 receptor agonists — has dramatically reduced progression to ESRD beyond what RAAS blockade alone achieves, fundamentally changing the long-term outlook for patients with diabetic kidney disease.
Epidemiology
DN affects approximately 30–40% of type 1 diabetes patients and 20–30% of type 2 diabetes patients over 20–25 years of disease duration. In the United States, 37 million people live with diabetes; approximately 28% develop albuminuria or reduced glomerular filtration rate (GFR), constituting diabetic kidney disease. DN accounts for 44% of incident ESRD cases, translating to roughly 120,000 new dialysis patients per year attributable to diabetes.
Racial and ethnic disparities are pronounced. Black, Hispanic, Native American, and Pacific Islander populations experience 2–4 times higher ESRD rates compared with White Americans with diabetes. These disparities reflect inequalities in healthcare access, glycemic control, hypertension burden, and genetic susceptibility. Type 2 diabetes drives the overwhelming majority of DN burden worldwide due to its high global prevalence, which now exceeds 500 million people.
Pathophysiology
Hyperglycemia activates multiple parallel injurious pathways that converge on the glomerular filtration barrier:
- Glomerular hemodynamic changes: Hyperglycemia causes afferent arteriolar vasodilation combined with efferent arteriolar vasoconstriction (angiotensin II mediated), producing glomerular hypertension. Mechanical stress on podocytes and mesangium drives glomerular hypertrophy and hyperfiltration — an elevated glomerular filtration rate is characteristic of early DN.
- Advanced glycation end-products (AGEs): Glucose-derived AGEs cross-link proteins in the glomerular basement membrane (GBM), increasing thickness and reducing permeability selectivity. AGE-RAGE signaling drives oxidative stress and NF-κB activation, producing pro-inflammatory cytokines.
- Polyol pathway: Aldose reductase converts excess intracellular glucose to sorbitol, causing osmotic injury and oxidative stress. Sorbitol is subsequently converted to fructose, generating dicarbonyl stress and further AGE production.
- Protein kinase C (PKC) activation: Diacylglycerol (DAG) accumulates under hyperglycemic conditions, activating PKC isoforms. This drives TGF-β overproduction, mesangial matrix expansion, GBM thickening, podocyte apoptosis, and VEGF overproduction causing abnormal glomerular neovascularization.
- TGF-β and fibrosis pathway: TGF-β is the central driver of mesangial expansion and GBM thickening. It promotes podocyte-to-mesenchymal transition, with connective tissue growth factor (CTGF) acting as a downstream effector of progressive glomerulosclerosis.
- RAAS activation: Local intra-renal RAAS activation occurs independently of systemic RAAS status. Angiotensin II drives glomerular hypertension, TGF-β production, and inflammation. Aldosterone drives podocyte injury, interstitial fibrosis, and tubulointerstitial inflammation.
- Oxidative stress: Reactive oxygen species generated by AGE-RAGE signaling, mitochondrial dysfunction, and nicotinamide adenine dinucleotide (NAD)(P)H oxidase activation cause endothelial dysfunction and podocyte injury, amplifying all other pathological processes.
- Inflammation: Macrophage infiltration, NF-κB activation, and elevated interleukin-6 (IL-6) and tumor necrosis factor alpha (TNF-α) levels drive tubulointerstitial inflammation and progressive fibrosis independent of glomerular injury.
- Podocyte loss: Podocytes are post-mitotic cells incapable of regeneration. Their progressive loss leads to focal segmental sclerosis. Low podocyte density on biopsy predicts rate of glomerular filtration rate decline and progression to ESRD.
- Kimmelstiel-Wilson (KW) nodules: Pathognomonic on kidney biopsy — hyaline material deposits in a nodular pattern in the periphery of the glomerulus (mesangial nodules of laminated matrix). Present in approximately 30% of DN biopsies; highly specific but not sensitive for DN.
Staging and Clinical Progression
DN follows a characteristic clinical trajectory described by Mogensen's 5 stages, modified for modern clinical use:
- Stage 1 — Hyperfiltration: estimated glomerular filtration rate (eGFR) elevated above 120–130 mL/min; glomerular hypertrophy; normal albumin excretion. This stage is present at or near diabetes onset and is partially reversible with strict glucose control.
- Stage 2 — Silent phase: Normal albuminuria (urine albumin-to-creatinine ratio, ACR, <30 mg/g); early structural changes including GBM thickening and mesangial expansion visible on biopsy; estimated glomerular filtration rate normal or elevated. This phase may last 10–15 years with no clinical manifestations.
- Stage 3 — Microalbuminuria (Incipient nephropathy): ACR 30–300 mg/g. Estimated glomerular filtration rate still normal; blood pressure begins to rise; this is the critical therapeutic window — RAAS blockade initiated at this stage halts progression to macroalbuminuria in 30–40% of patients and reverses albuminuria to normal in approximately 20%.
- Stage 4 — Macroalbuminuria (Overt nephropathy): ACR >300 mg/g (>300 mg/day); estimated glomerular filtration rate declining at an average of 10–15 mL/min/year without treatment; hypertension is prominent; edema develops; cardiovascular risk is markedly elevated. In type 1 diabetes mellitus (DM), diabetic retinopathy is present in virtually all patients at this stage — its absence raises doubt about the DN diagnosis.
- Stage 5 — ESRD: estimated glomerular filtration rate <15 mL/min/1.73 m²; dialysis or transplantation required. Most patients reach ESRD within 5–10 years of onset of macroalbuminuria without modern multimodal therapy.
Screening recommendations: Standard screening is an annual urine ACR and serum creatinine/estimated glomerular filtration rate test for everyone with diabetes. For type 2 DM, screening begins at diagnosis. For type 1 DM, screening begins 5 years after diagnosis. An abnormal ACR is confirmed on 2 of 3 measurements obtained 3 months apart, with urinary tract infection excluded as a confounding cause.
Diagnosis
DN is usually diagnosed clinically without kidney biopsy when the presentation is classic. Clinical diagnostic criteria include: diabetes of greater than 5–10 years duration, albuminuria (ACR >30 mg/g confirmed on 2 of 3 tests 3 months apart, excluding urinary tract infection (UTI)), presence of diabetic retinopathy, and no hematuria or other features suggesting an alternative diagnosis.
Kidney biopsy is indicated when atypical features are present: active urine sediment with red blood cell casts suggesting glomerulonephritis, sudden-onset proteinuria, unusually rapid glomerular filtration rate decline, absence of retinopathy in type 1 DM with presumed DN, or clinical suspicion of a concurrent primary glomerular disease.
Laboratory workup:
- Hemoglobin A1c (HbA1c) and fasting glucose — assess glycemic control
- Urine albumin-to-creatinine ratio (ACR) — preferred over 24-hour urine for screening; spot ACR is well-validated
- Serum creatinine and estimated glomerular filtration rate (CKD-EPI equation) — stage chronic kidney disease severity
- Electrolytes — monitor potassium, especially with RAAS blockade and estimated glomerular filtration rate <45
- Complete blood count (CBC), lipid panel — cardiovascular risk assessment
- Urine microscopy — exclude active sediment suggesting alternative glomerular disease
Pathology on biopsy: Glomerular hypertrophy, GBM thickening, diffuse mesangial expansion (early stages), Kimmelstiel-Wilson nodules (late; pathognomonic), hyalinosis of both afferent and efferent arterioles (hyaline arteriolosclerosis — efferent involvement is specific to DN, distinguishing it from hypertensive nephrosclerosis), progressive glomerulosclerosis, and tubulointerstitial fibrosis in advanced disease.
Glycemic Control and Blood Pressure
Glycemic control is foundational in DN prevention and management. The target hemoglobin A1c is <7.0% for most patients (American Diabetes Association (ADA) 2024 guidelines). In type 1 DM, the DCCT trial (1,441 patients, mean 6.5 years) found that intensive glucose control reduced the occurrence of microalbuminuria by 39% and of albuminuria by 54%. In type 2 DM, the UKPDS (3,867 newly diagnosed patients, 10 years) found that intensive control reduced microvascular endpoints, including the need for retinal laser treatment, by 25%. For elderly patients prone to frequent hypoglycemia, less aggressive targets of hemoglobin A1c 7.5–8.0% are commonly used. Hypoglycemia itself is associated with worse cardiovascular and renal outcomes; in the DCCT, intensive therapy brought a two- to threefold increase in severe hypoglycemia.
Blood pressure control targets <130/80 mmHg for patients with diabetes and chronic kidney disease (endorsed by ADA, Kidney Disease: Improving Global Outcomes (KDIGO), and American College of Cardiology/American Heart Association (ACC/AHA) 2024 guidelines). This target reduces glomerular filtration rate decline rate and cardiovascular event risk. Systolic blood pressure control is more important than diastolic for renal protection. Under these guidelines, blood-pressure treatment starts when pressure exceeds this threshold, with RAAS-based regimens as the preferred backbone.
RAAS Blockade Therapy
Angiotensin-converting enzyme inhibitors (captopril, lisinopril, enalapril) and angiotensin receptor blockers (losartan, irbesartan, olmesartan) are the cornerstone of DN therapy for all patients with ACR >30 mg/g, with or without hypertension. Their renoprotective effects operate through two mechanisms: reducing intraglomerular pressure by dilating the efferent arteriole, and reducing proteinuria by 30–40% through a direct antiproteinuric effect independent of blood pressure reduction.
- The IDNT trial (Lewis 2001, NEJM): in 1,715 hypertensive patients with nephropathy due to type 2 diabetes, irbesartan 300 mg/day lowered the risk of doubling of serum creatinine by 33% versus placebo and by 37% versus amlodipine, and lowered the primary composite (doubling of serum creatinine, ESRD, or death from any cause) by 20% versus placebo and 23% versus amlodipine; the protection was not explained by blood-pressure differences.
- The RENAAL trial (Brenner 2001, NEJM): losartan 100 mg/day reduced ESRD risk by 28% versus placebo in type 2 DN over 3.4 years.
- The MICRO-HOPE substudy (2000): in 3,577 people with diabetes aged 55 or older at high cardiovascular risk, ramipril 10 mg/day lowered the risk of overt nephropathy by 24% and the combined outcome of heart attack, stroke, or cardiovascular death by 25%.
Dual RAAS blockade (combining angiotensin-converting enzyme inhibitor (ACEi) with angiotensin receptor blocker (ARB)) brought harm without benefit: the VA-NEPHRON-D trial showed increased acute kidney injury (AKI) and hyperkalemia without additional renal benefit from the combination. Hyperkalemia is the most common complication of RAAS blockade in DN patients; the risk is greatest when estimated glomerular filtration rate falls below 45 mL/min, which is why serum potassium is checked closely. Potassium binders such as patiromer or sodium zirconium cyclosilicate can enable continuation of RAAS blockade in patients who develop hyperkalemia.
Sodium-Glucose Cotransporter-2 Inhibitors and Glucagon-Like Peptide-1 Agonists
Sodium-glucose cotransporter-2 inhibitors (dapagliflozin, empagliflozin, canagliflozin) represent a landmark advance in DN treatment, recommended by KDIGO 2022 for all patients with type 2 DM and chronic kidney disease with estimated glomerular filtration rate ≥20 mL/min, regardless of glycemic control status.
Their renoprotective mechanism involves blockade of sodium-glucose cotransporter 2 in the proximal tubule, causing glucosuria. This reduces tubuloglomerular feedback, lowering afferent arteriolar tone and intraglomerular pressure — directly counteracting the glomerular hemodynamic abnormality central to DN. Additional benefits include weight loss, blood pressure reduction, and anti-inflammatory and anti-fibrotic effects.
- CREDENCE trial (Perkovic 2019, NEJM): canagliflozin 100 mg daily in 4,401 patients with type 2 DM, albuminuric chronic kidney disease (ACR >300–5,000 mg/g) and estimated glomerular filtration rate 30 to <90 reduced the composite of end-stage kidney disease, doubling of the serum creatinine level, or death from renal or cardiovascular causes by 30% (hazard ratio 0.70); end-stage kidney disease alone was 32% lower. The trial was stopped early after a planned interim analysis.
- DAPA-CKD trial (Heerspink 2020, NEJM): dapagliflozin in chronic kidney disease patients with estimated glomerular filtration rate 25–75 and ACR 200–5,000 mg/g — including both diabetic and non-diabetic chronic kidney disease — reduced the primary composite — sustained glomerular filtration rate decline ≥50%, ESRD, or death from renal or cardiovascular causes — by 39% (hazard ratio 0.61); the kidney-specific composite, counting death from renal causes only, was 44% lower (hazard ratio 0.56). Dapagliflozin is now approved for non-diabetic chronic kidney disease based on this result.
- EMPA-KIDNEY trial (2023, NEJM): empagliflozin across a broad chronic kidney disease population reduced kidney disease progression or cardiovascular death by 28%.
Glucagon-like peptide-1 receptor agonists (semaglutide, liraglutide, dulaglutide) provide both cardiovascular and emerging kidney protection in diabetic patients:
- LEADER trial (kidney results: Mann 2017, NEJM; main trial: Marso 2016, NEJM): in 9,340 patients followed a median 3.84 years, liraglutide reduced the composite renal outcome — new persistent macroalbuminuria, doubling of creatinine, ESRD, or renal death — by 22% versus placebo (hazard ratio 0.78), a result driven primarily by fewer cases of new persistent macroalbuminuria.
- SUSTAIN-6 trial (Marso 2016, NEJM): in 3,297 patients with type 2 diabetes, rates of new or worsening nephropathy were lower with weekly semaglutide than with placebo, but retinopathy complications (bleeding into the eye, blindness, or conditions needing eye injections or laser treatment) were significantly more common (hazard ratio 1.76, 95% confidence interval 1.11 to 2.78).
- FLOW trial (Perkovic 2024, NEJM): semaglutide 1 mg subcutaneously weekly in 3,533 patients with type 2 DM and chronic kidney disease (eGFR 50–75 with ACR >300 to <5,000 mg/g, or eGFR 25 to <50 with ACR >100 to <5,000 mg/g) reduced the composite of kidney failure, at least 50% estimated glomerular filtration rate decline, or death from kidney-related or cardiovascular causes by 24% (hazard ratio 0.76). Death from any cause was 20% lower, and kidney function fell more slowly, by 1.16 mL/min/1.73 m² per year. This was the first trial establishing direct kidney protection by a glucagon-like peptide-1 receptor agonist.
The mechanism of glucagon-like peptide-1 renoprotection involves reduced glomerular hyperfiltration, anti-inflammatory effects, weight loss reducing glomerular hypertension, and possible direct glucagon-like peptide-1 receptor signaling on podocytes.
Finerenone and Novel Therapies
Finerenone is a non-steroidal, selective mineralocorticoid receptor antagonist (MRA) approved by the U.S. Food and Drug Administration (FDA) in 2021 for reducing progression of DN in adults with type 2 DM. Unlike steroidal MRAs (spironolactone, eplerenone), finerenone has higher receptor selectivity for kidney and cardiac tissue and causes significantly less hyperkalemia due to rapid tissue distribution and a non-steroidal scaffold.
Its mechanism blocks mineralocorticoid receptor (MR) overactivation in the kidney and heart — the pathway through which aldosterone drives glomerular inflammation, podocyte injury, and progressive interstitial fibrosis.
- FIDELIO-DKD trial (Bakris 2020, NEJM): finerenone versus placebo in type 2 DM with DN (ACR 30–5,000 mg/g and estimated glomerular filtration rate ≥25) reduced the composite kidney outcome — sustained ≥40% estimated glomerular filtration rate decline, ESRD, or renal death — by 18% (17.8% vs 21.1% of patients over a median 2.6 years), and reduced cardiovascular events by 14%. Stopping the drug because of high potassium happened in 2.3% on finerenone versus 0.9% on placebo.
- FIGARO-DKD trial (Pitt 2021, NEJM): in a similar population with greater emphasis on cardiovascular outcomes (7,437 patients, median 3.4 years), finerenone reduced the composite of cardiovascular death, non-fatal myocardial infarction (MI), non-fatal stroke, or hospitalization for heart failure by 13% (12.4% vs 14.2%; hazard ratio 0.87), a benefit driven primarily by fewer hospitalizations for heart failure (hazard ratio 0.71). The kidney composite (kidney failure, ≥40% eGFR decline, or renal death) was not significantly lower (hazard ratio 0.87, 95% confidence interval 0.76 to 1.01). Stopping the drug because of high potassium happened in 1.2% on finerenone versus 0.4% on placebo.
- CONFIDENCE trial (Agarwal 2025, NEJM): in people with type 2 diabetes and albuminuric chronic kidney disease (eGFR 30–90; ACR 100–5,000 mg/g) already taking a renin-angiotensin system blocker, starting finerenone and empagliflozin together lowered urine ACR at 180 days 29% more than finerenone alone and 32% more than empagliflozin alone. Symptomatic low blood pressure, acute kidney injury, and high potassium leading to stopping the drugs were uncommon.
Finerenone is indicated as add-on therapy to RAAS blockade and sodium-glucose cotransporter-2 inhibitors for patients with type 2 DM and DN, eGFR ≥25, and ACR ≥30 mg/g. The combination of an angiotensin-converting enzyme inhibitor or angiotensin receptor blocker, sodium-glucose cotransporter-2 inhibitor, and finerenone represents the current gold standard of DN pharmacotherapy.
Emerging therapies:
- Endothelin receptor antagonists: Sparsentan (dual endothelin/angiotensin receptor antagonist) is approved for immunoglobulin A (IgA) nephropathy and under study in DN. Atrasentan in the SONAR trial (de Zeeuw 2019, The Lancet) reduced the composite kidney endpoint by 35% in patients with DN selected for an acute antiproteinuric response.
- Bardoxolone methyl: An Nrf2 activator that raises estimated glomerular filtration rate by reducing filtration restriction. Phase 2 data were promising, but the phase 3 BEACON trial (de Zeeuw 2013, NEJM; 2,185 patients with type 2 diabetes and stage 4 chronic kidney disease) found no reduction in ESRD or cardiovascular death (hazard ratio 0.98), and 96 patients on bardoxolone were hospitalized for or died from heart failure versus 55 on placebo (hazard ratio 1.83); the higher rate of cardiovascular events prompted termination of the trial. The CARDINAL phase 3 trial in Alport syndrome informed the DN program; ongoing evaluation in DN at risk of progression.
Dietary and Lifestyle Management
Dietary and lifestyle interventions are integral to slowing DN progression alongside pharmacotherapy:
- Protein restriction: 0.8 g/kg/day is the standard recommended intake for patients with CKD (KDIGO 2024). Protein restriction reduces glomerular hyperfiltration. High-protein diets accelerate glomerular filtration rate decline. Protein intake below 0.6 g/kg/day provides no additional benefit and risks malnutrition.
- Sodium restriction: Less than 2 g of sodium per day reduces blood pressure and potentiates the antiproteinuric effect of RAAS blockade. Most processed and restaurant foods substantially exceed this target.
- Weight management: Obesity is a direct driver of glomerular hyperfiltration through adipokine-mediated and hemodynamic mechanisms. Each 10% reduction in body weight reduces proteinuria by approximately 30%. Bariatric surgery improves DN — studies show reduced albuminuria and stabilized estimated glomerular filtration rate in morbidly obese patients with type 2 DM following Roux-en-Y gastric bypass.
- Physical activity: 150 minutes per week of moderate-intensity aerobic exercise improves insulin sensitivity, reduces blood pressure, and lowers cardiovascular risk — the dominant competing cause of death in diabetic chronic kidney disease.
- Smoking cessation: Smoking doubles the rate of DN progression through endothelial injury, oxidative stress, and worsening glomerular hemodynamics. Cessation measurably slows glomerular filtration rate decline.
- Dietary patterns: The DASH diet and Mediterranean diet both reduce chronic kidney disease progression. Kidney diets typically limit processed meats, added sugars, and excess phosphorus, and restrict dietary potassium when estimated glomerular filtration rate falls below 30 mL/min, particularly in patients on RAAS blockade and/or finerenone.
- Kidney-toxic drugs and contrast: nonsteroidal anti-inflammatory drugs (NSAIDs) worsen DN through combined hemodynamic and direct tubulotoxic effects, which is why kidney care keeps them to brief use or none. Iodinated contrast media carry acute kidney injury risk; the standard precautions are iso-osmolar agents, adequate hydration, and holding sodium-glucose cotransporter-2 inhibitors for 48 hours before elective contrast procedures.
Prognosis and ESRD Prevention
Without treatment: type 1 DM patients with overt DN face approximately 50% ESRD risk over 25 years. Type 2 DM patients with DN have variable outcomes — many die of cardiovascular disease before reaching ESRD (the "competing risk" phenomenon), making cardiovascular risk reduction as important as kidney protection in this population.
With modern multimodal therapy — hemoglobin A1c <7%, angiotensin-converting enzyme inhibitor or angiotensin receptor blocker, sodium-glucose cotransporter-2 inhibitor, finerenone, glucagon-like peptide-1 receptor agonist, blood pressure <130/80, statin therapy, and lifestyle modification — ESRD rates have declined 30–40% in the US over the past 20 years. The combination of all four pillars (RAAS + SGLT2i + finerenone + GLP-1RA) is now achievable for most patients and represents the standard of care.
Cardiovascular mortality is the leading cause of death in diabetic chronic kidney disease — 10–20 times higher than matched non-diabetic chronic kidney disease patients. Aggressive cardiovascular risk reduction (statins, antiplatelet therapy where indicated, blood pressure control, smoking cessation) is essential and often achieves greater life-year gains than renal protection alone.
Renal replacement therapy for ESRD:
- Hemodialysis — most common modality in the US; requires vascular access (arteriovenous fistula preferred)
- Peritoneal dialysis — home-based option; suitable for motivated patients with adequate abdominal clearance
- Kidney transplant — best outcomes in eligible patients; pre-emptive transplant (before dialysis initiation) is strongly preferred over transplant after a period of dialysis, with substantially better graft and patient survival
- Simultaneous pancreas-kidney (SPK) transplant — the optimal treatment for eligible patients with type 1 DM and ESRD, restoring both glucose homeostasis and kidney function
Key Research Papers
- Perkovic V, et al. Canagliflozin and Renal Outcomes in Type 2 Diabetes and Nephropathy (CREDENCE). N Engl J Med. 2019;380(24):2295–2306. — PubMed PMID: 30990260 · doi:10.1056/NEJMoa1811744
- Bakris GL, et al. Effect of Finerenone on Chronic Kidney Disease Outcomes in Type 2 Diabetes (FIDELIO-DKD). N Engl J Med. 2020;383(23):2219–2229. — PubMed PMID: 33264825 · doi:10.1056/NEJMoa2025845
- Pitt B, et al. Cardiovascular Events with Finerenone in Kidney Disease and Type 2 Diabetes (FIGARO-DKD). N Engl J Med. 2021;385(24):2252–2263. — PubMed PMID: 34449181 · doi:10.1056/NEJMoa2110956
- Heerspink HJL, et al. Dapagliflozin in Patients with Chronic Kidney Disease (DAPA-CKD). N Engl J Med. 2020;383(15):1436–1446. — PubMed PMID: 32970396 · doi:10.1056/NEJMoa2024816
- Perkovic V, et al. Effects of Semaglutide on Chronic Kidney Disease in Patients with Type 2 Diabetes (FLOW). N Engl J Med. 2024;391(2):109–121. — PubMed PMID: 38785209 · doi:10.1056/NEJMoa2403347
- Lewis EJ, et al. Renoprotective Effect of the Angiotensin-Receptor Antagonist Irbesartan in Patients with Nephropathy Due to Type 2 Diabetes (IDNT). N Engl J Med. 2001;345(12):851–860. — PubMed PMID: 11565517 · doi:10.1056/NEJMoa011303
- Brenner BM, et al. Effects of Losartan on Renal and Cardiovascular Outcomes in Patients with Type 2 Diabetes and Nephropathy (RENAAL). N Engl J Med. 2001;345(12):861–869. — PubMed PMID: 11565518 · doi:10.1056/NEJMoa011161
- EMPA-KIDNEY Collaborative Group. Empagliflozin in Patients with Chronic Kidney Disease. N Engl J Med. 2023;388(2):117–127. — PubMed PMID: 36331190 · doi:10.1056/NEJMoa2204233
- Marso SP, et al. Liraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER). N Engl J Med. 2016;375(4):311–322. — PubMed PMID: 27295427 · doi:10.1056/NEJMoa1603827
- DCCT Research Group. The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus. N Engl J Med. 1993;329(14):977–986. — PubMed PMID: 8366922 · doi:10.1056/NEJM199309303291401
- Thomas MC, et al. Diabetic kidney disease. Nat Rev Dis Primers. 2015;1:15018. — PubMed PMID: 27188921 · doi:10.1038/nrdp.2015.18
- Kidney Disease: Improving Global Outcomes (KDIGO) Diabetes Work Group. KDIGO 2022 Clinical Practice Guideline for Diabetes Management in Chronic Kidney Disease. Kidney Int. 2022;102(5S):S1–S127. — PubMed PMID: 36272764 · doi:10.1016/j.kint.2022.06.008
- Mann JFE, et al. Liraglutide and Renal Outcomes in Type 2 Diabetes (LEADER). N Engl J Med. 2017;377(9):839–848. — PubMed PMID: 28854085 · doi:10.1056/NEJMoa1616011
- Marso SP, et al. Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (SUSTAIN-6). N Engl J Med. 2016;375(19):1834–1844. — PubMed PMID: 27633186 · doi:10.1056/NEJMoa1607141
- Heart Outcomes Prevention Evaluation Study Investigators. Effects of ramipril on cardiovascular and microvascular outcomes in people with diabetes mellitus: results of the HOPE study and MICRO-HOPE substudy. Lancet. 2000;355(9200):253–259. — PubMed PMID: 10675071
- UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet. 1998;352(9131):837–853. — PubMed PMID: 9742976
- de Zeeuw D, et al. Bardoxolone methyl in type 2 diabetes and stage 4 chronic kidney disease (BEACON). N Engl J Med. 2013;369(26):2492–2503. — PubMed PMID: 24206459 · doi:10.1056/NEJMoa1306033
- Agarwal R, et al. Finerenone with Empagliflozin in Chronic Kidney Disease and Type 2 Diabetes (CONFIDENCE). N Engl J Med. 2025;393(6):533–543. — PubMed PMID: 40470996 · doi:10.1056/NEJMoa2410659
PubMed Topic Searches
- PubMed: Diabetic nephropathy SGLT2 inhibitors canagliflozin empagliflozin
- PubMed: Diabetic kidney disease finerenone FIDELIO FIGARO
- PubMed: Diabetic nephropathy ACE inhibitor ARB RAAS
- PubMed: Diabetic nephropathy GLP-1 receptor agonist semaglutide FLOW
- PubMed: Diabetic nephropathy pathophysiology TGF-beta AGE RAGE
- PubMed: Diabetic nephropathy HbA1c glycemic control DCCT UKPDS
- PubMed: Diabetic nephropathy ESRD outcomes dialysis transplant
Connections
- Nephrology & Hepatology
- Chronic Kidney Disease
- Acute Kidney Injury
- Nephrotic Syndrome
- Glomerulonephritis
- Membranous Nephropathy
- FSGS
- Lupus Nephritis
- Kidney Stones
- Kidney Function Tests
- Urinalysis
- Astragalus for Kidney & Diabetic Nephropathy
- Type 2 Diabetes — drives the overwhelming majority of diabetic nephropathy worldwide, and 20–30% of these patients develop kidney disease.
- Endocrinology