Inflammatory Bowel Disease (IBD) Surgery Decisions — Resection, J-Pouch, and Ostomy
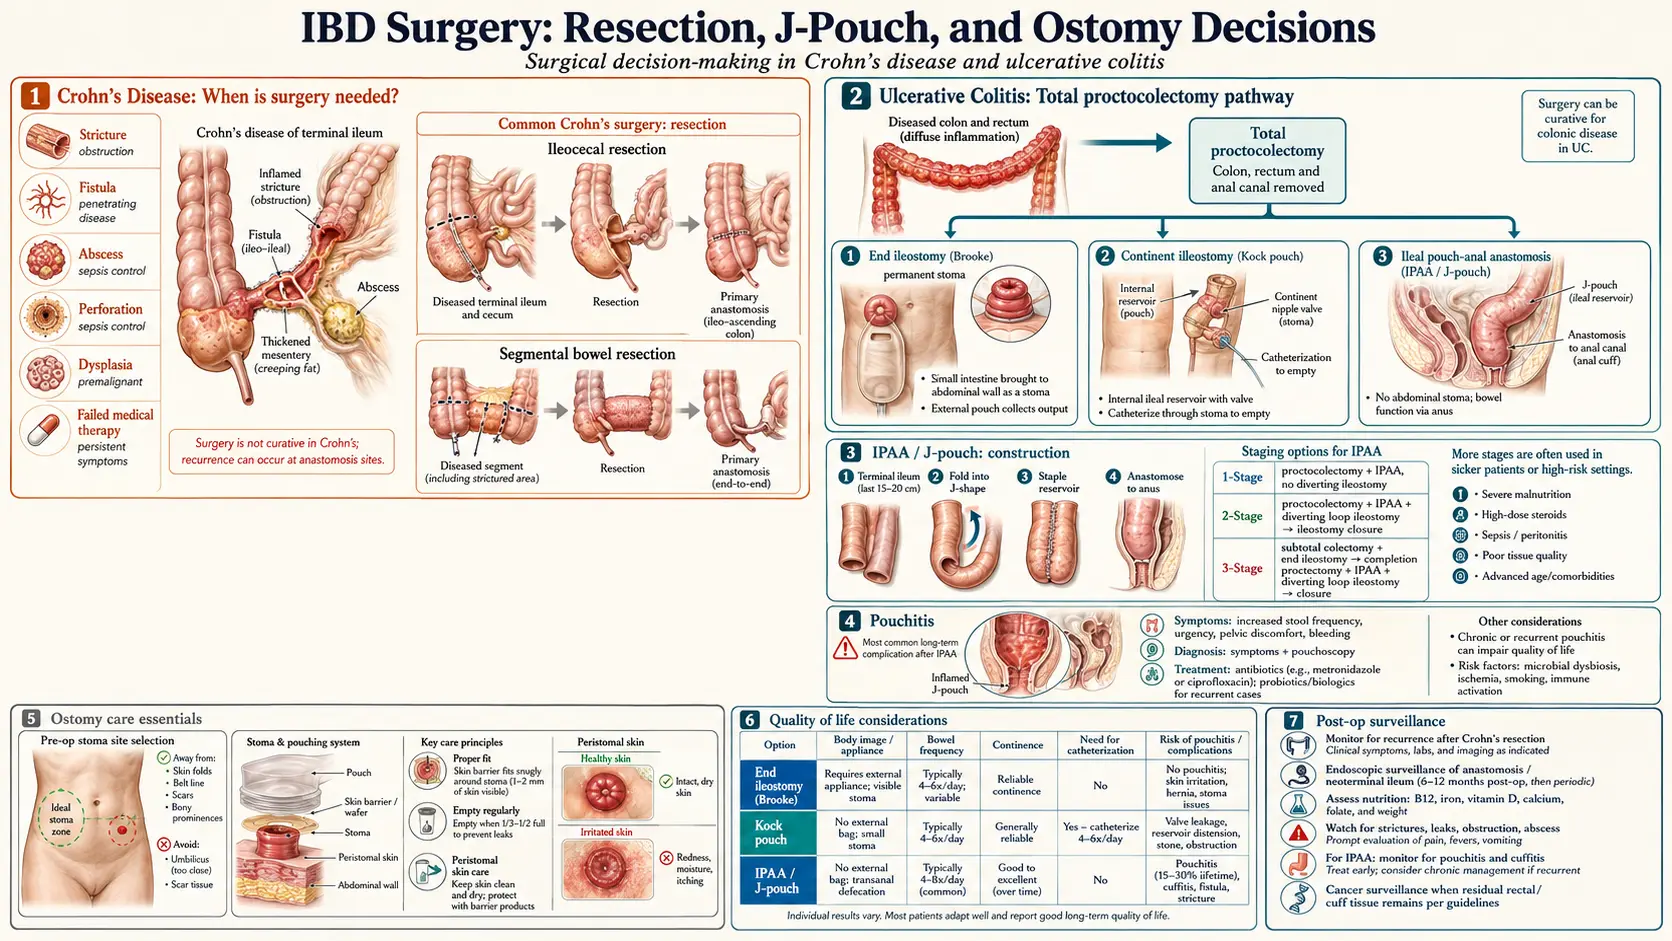
Table of Contents
- When Surgery Beats Another Biologic
- Crohn's: Ileocecal Resection and the LIR!C Trial
- Stricturoplasty — Saving Bowel Length
- Fistula Surgery in Crohn's
- Post-Op Prophylaxis and the Rutgeerts Score
- UC: Subtotal Colectomy — Emergency vs Elective
- The J-Pouch (IPAA) — 2-Stage vs 3-Stage
- Pouchitis, Cuffitis, and Pouch Failure
- Fertility, Pregnancy, and Sexual Function
- The Kock Pouch — A Historical Alternative
- Life with a Permanent Ileostomy
- Supplies, Appliance Types, and Insurance
- Choosing a Surgeon — Volume Matters
- Post-Op Diet — First Weeks and Beyond
- Key Research Papers
- Connections
- Featured Videos
When Surgery Beats Another Biologic
Surgery in inflammatory bowel disease (IBD) is no longer a last resort. Thirty years ago it carried that reputation because the only patients who reached an operating room were the ones whose disease had already wrecked their bodies — perforation, obstruction, sepsis, cancer. Today the calculus is different. For the right patient, an operation done early is faster, safer, and often cheaper than cycling through a third or fourth biologic while losing weight, missing work, and watching a stricture slowly close.
Four scenarios tip the balance toward surgery:
- Short-segment Crohn's at the ileocecal valve that responds poorly to medication. The LIR!C trial changed practice here.
- Fibrotic (non-inflammatory) strictures. A scar is not going to be fixed by a tumor necrosis factor (TNF) inhibitor. Magnetic resonance enterography (MRE) or computed tomography (CT) with careful reading can show whether the wall is inflamed or fibrosed — fibrosis points straight to surgery or endoscopic dilation.
- Ulcerative colitis (UC) with steroid dependence after two or more biologic classes have failed, especially in a patient who is chronically anemic, underweight, or unable to work.
- Dysplasia on surveillance colonoscopy in long-standing colitis. High-grade dysplasia is a recognised indication for colectomy.
The question patients rarely get asked directly is: what do you want the next year of your life to look like? A well-performed surgery at a high-volume center can close the door on years of inflammation in a single admission. A new biologic started today will tell you in 12–16 weeks whether it worked. If it didn't, you are another four months older, still sick, and down another insurance-authorized option.
Crohn's: Ileocecal Resection and the LIR!C Trial
The terminal ileum and cecum are the single most common location for Crohn's disease. An ileocecal resection removes the last few inches of small bowel and the cecum, then connects (anastomoses) the healthy small bowel to the ascending colon. Done laparoscopically at an experienced center, the hospital stay is 3–5 days and most patients are back to light activity in two weeks.
The landmark LIR!C trial (Ponsioen et al., published in Lancet Gastroenterology & Hepatology in 2017, with long-term follow-up in 2020) randomized 143 patients with limited ileocecal Crohn's — failing conventional therapy but not yet on biologics — to either laparoscopic ileocecal resection or infliximab. At one year, quality-of-life scores were equivalent. In the long-term follow-up (median 63.5 months, about five years), 48% of the infliximab group (31 of 65 people) eventually had a Crohn's-related resection anyway, while 26% of the resection group (18 of 69) went on to start anti-TNF therapy and none needed a second resection; the time without needing any extra Crohn's treatment was similar in both groups (median 33 vs 34 months). Cost analysis favored the surgical arm.
The trial does not mean every person with ileocecal Crohn's needs surgery. The follow-up authors concluded that it supports laparoscopic resection as a treatment option for limited (40 cm or less), mainly inflammatory disease when conventional treatment has not worked — for short-segment disease, surgery is a first-line option rather than a rescue maneuver, and deferring it in favor of biologics does not reliably prevent the operation — it often just delays it.
Stricturoplasty — Saving Bowel Length
Patients with multifocal small-bowel Crohn's can accumulate several strictures over years. Resecting each one would eventually shorten the bowel enough to cause short bowel syndrome — chronic diarrhea, malabsorption, and dependence on intravenous nutrition. Stricturoplasty is the length-sparing alternative: the surgeon opens the narrowed segment longitudinally and sews it closed transversely, widening the lumen without removing tissue.
The two common techniques are the Heineke-Mikulicz (for short strictures under 10 cm) and the Finney or side-to-side isoperistaltic (for long strictures). Recurrence at a stricturoplasty site is no higher than at a resection anastomosis, and preserved bowel length is the payoff. A patient with five small-bowel strictures may leave the operating room with all five widened and every centimeter of intestine intact.
Fistula Surgery in Crohn's
Perianal fistulas affect roughly 25% of Crohn's patients over their lifetime, and they are miserable: constant drainage, recurrent abscesses, pain with sitting, and a sharp hit to body image and sexual function. Surgery for fistulas in Crohn's is deliberately conservative, because aggressive cutting in an inflamed anal sphincter risks incontinence the patient will live with forever.
- Exam under anesthesia (EUA) with magnetic resonance imaging (MRI) mapping is usually the first step — defining tracks, identifying abscesses, and often placing a seton (a soft silicone loop) through each fistula tract to keep it draining while medications work.
- Seton drainage + biologic therapy (infliximab is best studied) is the mainstay. The seton prevents abscess; the biologic reduces inflammation and allows some tracts to close.
- Fistulotomy (laying open the tract) is reserved for low, simple fistulas not crossing significant sphincter muscle.
- Advancement flap and LIFT procedure (ligation of the intersphincteric fistula tract) are sphincter-sparing options for complex disease.
- Mesenchymal stem-cell therapy (darvadstrocel) was approved in the European Union in 2018 for complex perianal Crohn's fistulas, but the European Commission withdrew that approval on 13 December 2024 at the request of the company that held it, which stopped marketing it in the EU (European Medicines Agency record); it does not appear on the U.S. Food and Drug Administration (FDA) list of approved cellular and gene therapy products. Its larger confirmation trial, ADMIRE CD II (568 people with complex perianal fistulas, published 2026), did not meet its main goal: at week 24 the fistula openings had closed, with no fluid collection over 2 cm, in 48.8% of people given darvadstrocel and 46.3% of people given a placebo (both groups also had the tract cleaned and its inner opening closed), a difference that could be chance (P = .571). Side effects were reported at similar rates in both groups (73.0% vs 73.4%).
Post-Op Prophylaxis and the Rutgeerts Score
Here is the brutal truth about Crohn's surgery: the disease comes back. Endoscopic recurrence — visible inflammation at the anastomosis — appears in 70–90% of patients within one year if no medication is given afterward. Clinical symptoms follow later, and surgical recurrence (another operation) happens in 25–35% at ten years.
Why? The honest answer is that no one fully knows. The favored theory is that stool exposure triggers the immune reaction that drives Crohn's, and the neoterminal ileum — the new end of small bowel sitting just upstream of the anastomosis — is suddenly bathed in colonic contents it wasn't designed to handle. Bile acids, bacterial load, and oxygen gradients all change at that junction.
The Rutgeerts score, developed by Paul Rutgeerts in 1990, grades endoscopic recurrence at colonoscopy performed 6–12 months post-op:
- i0 — no lesions. Prognosis excellent.
- i1 — fewer than five aphthous ulcers. Still good.
- i2 — more than five aphthous ulcers, or skip lesions. Usually watched closely.
- i3 — diffuse aphthous ileitis with inflamed mucosa. Usually prompts stronger therapy.
- i4 — diffuse inflammation with larger ulcers, nodules, or narrowing. High risk of clinical recurrence.
The modern approach: start post-op prophylaxis within 4–8 weeks of surgery in anyone with risk factors (smoking, prior resection, penetrating disease, active inflammation at the margin, young age at diagnosis). Most guidelines now recommend an anti-TNF agent as prophylaxis for high-risk patients, confirmed with colonoscopy at 6–12 months to catch recurrence early. In smokers, quitting after surgery is reported to cut recurrence risk roughly in half.
UC: Subtotal Colectomy — Emergency vs Elective
Because ulcerative colitis is confined to the colon, removing the colon is curative for the intestinal disease. That fact drives every UC surgical decision. The two paths into the operating room are very different.
Emergency colectomy means acute severe UC that is failing rescue therapy (intravenous steroids, then infliximab or cyclosporine) — or worse, toxic megacolon or perforation. The operation is a subtotal colectomy with end ileostomy: the colon comes out, the rectum is stapled closed and left in place (the “Hartmann stump”), and the small bowel is brought to the skin as a temporary stoma. The patient recovers, builds nutrition back up, and returns months later for the next stage. Doing more than this during an emergency is unsafe — the inflamed rectum cannot hold an anastomosis.
Elective colectomy is scheduled, usually for medication-refractory chronic disease or dysplasia. It can still begin with a subtotal colectomy, but in a healthy patient at a high-volume center, the surgeon and patient may go directly to a one- or two-stage reconstruction.
The J-Pouch (IPAA) — 2-Stage vs 3-Stage
The ileal pouch-anal anastomosis (IPAA), almost always shaped like the letter J, is the modern reconstruction of choice after colectomy for UC. The surgeon folds the last 30–40 cm of small bowel back on itself, staples it into a pouch that serves as a neorectum, and connects the bottom of the pouch to the anal canal. The patient keeps bowel continuity and sits on the toilet like anyone else — just more often.
Two staging strategies dominate:
- 2-stage IPAA. Stage 1: total proctocolectomy + J-pouch + diverting loop ileostomy (so the new pouch heals with no stool passing through it). Stage 2, about 8–12 weeks later: reverse the loop ileostomy. Used in healthy elective patients.
- 3-stage IPAA. Stage 1: subtotal colectomy + end ileostomy (the emergency or very-sick scenario). Stage 2, 3–6 months later when the patient is off steroids and nutritionally stable: completion proctectomy + J-pouch + diverting loop ileostomy. Stage 3, another 8–12 weeks later: ileostomy reversal.
Expect 4–8 bowel movements per day with a mature pouch, sometimes one at night. Most patients describe life a year after the final stage as “completely different — I'm a person again.” Continence is preserved in the large majority. The trade-off is that the pouch is not a normal colon and it has its own set of complications, discussed next.
Pouchitis, Cuffitis, and Pouch Failure
Pouchitis is inflammation of the J-pouch mucosa — the most common long-term complication, affecting roughly 50% of IPAA patients at least once within five years; the EARNEST trial authors note that about one in five of those go on to have chronic pouchitis. Symptoms: increased stool frequency, urgency, cramping, sometimes blood and low-grade fever. First-line treatment is a two-week course of ciprofloxacin or metronidazole, which works in over 80% of acute episodes. The trial evidence behind the two antibiotics is small: in the one trial comparing them, reviewed by Cochrane in 2019, all 7 people given ciprofloxacin and 3 of 9 given metronidazole were in remission at two weeks, which the review rated very low certainty evidence. Chronic or antibiotic-refractory pouchitis may respond to vedolizumab, budesonide, or biologic therapy used for inflammatory bowel disease. In the EARNEST trial (2023), 102 people with chronic pouchitis were given vedolizumab or a placebo, with ciprofloxacin for everyone during the first 4 weeks; at week 14, 31% of the vedolizumab group and 10% of the placebo group were in remission, and serious side effects occurred in 6% and 8%.
Cuffitis is inflammation of the short strip of residual rectal mucosa (the “cuff”) left when the pouch is stapled rather than hand-sewn. It acts like a tiny patch of persistent UC and responds to topical mesalamine or hydrocortisone suppositories.
Pouch failure — pouch excision or permanent diversion — occurs in 5–10% of patients at 10 years. In one U.S. centre's series of 3,707 people operated on between 1984 and 2010, pouch failure occurred in 5.3% over a median 84 months of follow-up (3.2% had the pouch removed); early complications after surgery occurred in 33.5% and 0.1% died, and 95% had function and quality of life rated good or excellent. The most common causes are Crohn's disease discovered after colectomy (the pathology changed the diagnosis), refractory pouchitis, and pelvic sepsis from anastomotic leak. A failed pouch does not mean a failed life: conversion to permanent ileostomy is straightforward, and most patients feel better afterward than during the years of pouch trouble.
Fertility, Pregnancy, and Sexual Function
For women of reproductive age, IPAA has one documented cost: infertility roughly triples compared with women whose ulcerative colitis is treated with medicines (relative risk 3.17 in a 2006 meta-analysis). The presumed mechanism is pelvic adhesions (scar tissue) around the fallopian tubes; the meta-analysis could not identify any operative factor that consistently changed the risk. In that meta-analysis, 48% of women had not become pregnant after 12 months of trying following IPAA, compared with 15% of women with medically treated ulcerative colitis. In vitro fertilisation (IVF) bypasses the problem completely; outcomes with IVF are equivalent to the general population.
Two strategies can reduce this risk:
- Laparoscopic or robotic IPAA creates fewer adhesions than open surgery, so whether a surgeon operates this way is one of the questions women planning a pregnancy ask about.
- Delayed reconstruction. Some women with severe UC take the subtotal colectomy first, keep the end ileostomy, complete their family, and then have the J-pouch created afterward. Some women plan this sequence with the colorectal surgeon and a fertility specialist (reproductive endocrinologist) before the first operation.
Sexual function: most men have unchanged erectile and ejaculatory function after J-pouch surgery; retrograde ejaculation occurs in a small minority, usually from nerve irritation that recovers over months. Women may have dyspareunia from pelvic scarring. Both are far more likely with open surgery than with minimally invasive technique.
The Kock Pouch — A Historical Alternative
Before the J-pouch became standard in the 1980s, Swedish surgeon Nils Kock developed the continent ileostomy (“Kock pouch”) in 1969. A reservoir of small bowel is built inside the abdomen with a nipple-valve leading to a flush stoma on the skin. Instead of wearing an external bag, the patient intubates the stoma with a catheter several times a day to empty the pouch.
Kock pouches are now performed at only a few specialized centers. Indications are narrow: the J-pouch failed or is not an option, but the patient refuses a traditional external appliance. Long-term complications — valve slippage, difficulty catheterizing, pouchitis — are common enough that most surgeons steer patients toward an end ileostomy instead. The Kock pouch still exists as an option, but it is rarely chosen in 2026.
Life with a Permanent Ileostomy
A permanent ileostomy is not a failure. For many patients with extensive Crohn's of the colon, poor anal sphincter function, pelvic radiation history, or recurrent pouch failure, it is the operation that gives back the most life. Surveys repeatedly show post-ileostomy quality-of-life scores that exceed matched pre-operative inflammatory bowel disease scores. The reason is simple: the disease is over. Urgency is over. The 3 a.m. sprints to the bathroom are over. You plan your day around ordinary things again.
Practical realities worth knowing:
- Output: 600–1200 mL of liquid-to-porridge stool per day. You empty the pouch 4–8 times daily.
- Diet: most people eat a near-normal diet within three months. High-fiber raw foods (corn, nuts, mushrooms, celery) can occasionally block the stoma, especially when poorly chewed.
- Hydration: the colon normally reabsorbs a liter of water a day; without it, people with an ileostomy lose more water and sodium in their output, so their fluid and salt needs rise. Oral rehydration solution helps during heat, exercise, or high output.
- Activity: swimming, weightlifting, running, sex — all routine with a stoma. Contact sports use a stoma guard.
- Appearance: modern low-profile flat appliances are invisible under most clothing. The stigma in patients' heads is almost always worse than the reality in strangers' eyes.
- Body image and mental health: the first 3–6 months are hard. Many people describe ostomy support groups (the United Ostomy Associations of America, a non-profit; local online groups) as helpful, and some also see a therapist who specializes in chronic illness.
Supplies, Appliance Types, and Insurance
A few large manufacturers supply most of the U.S. ostomy appliance market, each with one-piece and two-piece systems, cut-to-fit and pre-cut wafers, and drainable or closed pouches. The main types:
- Two-piece systems — a separate wafer (skin barrier) and pouch that join together; widely prescribed as a starter system.
- Flexible one-piece wafers — popular with active patients.
- Convex wafers — firmer, curved barriers for flush or retracted stomas.
What works for one stoma shape, skin, and lifestyle can fail for another, so many people try several. Manufacturers send free sample kits on request, which lets people compare systems in the first three months before settling on a supplier.
Insurance tactics. Medicare covers ostomy supplies as durable medical equipment (Healthcare Common Procedure Coding System, HCPCS, codes A4375–A4434). Private insurance usually follows, often with monthly quantity caps — a common baseline is 20 pouches and 10 wafers per month, with higher use covered when it is documented in writing. Mail-order medical-supply distributors usually charge less than pharmacy pickup and handle insurance billing directly. A WOC nurse (Wound, Ostomy, and Continence certified) is available at many hospitals before surgery, during the hospital stay, and for follow-up visits. Many insurers pay for at least two outpatient WOC visits.
Choosing a Surgeon — Volume Matters
This is the single most under-discussed variable in inflammatory bowel disease surgery outcomes. Study after study shows that high-volume surgeons and high-volume centers have lower complication rates, lower mortality, shorter hospital stays, and fewer re-operations for the same procedures. The effect is largest for complex operations like IPAA, where a leak rate of 3% at a high-volume center can become 12% at a low-volume one.
Markers often used to describe a high-volume program:
- The surgeon personally performs at least 20 IPAA operations per year (ideally 50+).
- The center has a dedicated inflammatory bowel disease surgical program, a WOC nurse, and a gastrointestinal (GI) team that co-manages in-hospital.
- The surgeon is board-certified in colon and rectal surgery.
- The surgeon can state their own complication rate, leak rate, and conversion rate without hedging.
Many people travel to a specialist center for a planned operation, because a single decision shapes the next forty years of their life. Large academic inflammatory bowel disease surgery programs exist in several U.S. regions. Academic programs with active inflammatory bowel disease research generally do better than community centers at complex pouch work.
Post-Op Diet — First Weeks and Beyond
Every surgical team has its own exact protocol, but the general arc looks like this:
- Days 0–3 in hospital: sips of clear liquids, advanced to full liquids as bowel function returns. Chewing gum and early ambulation genuinely speed return of motility — not folklore, backed by Enhanced Recovery After Surgery (ERAS) data.
- Weeks 1–3 at home: low-residue diet sheets typically list soft foods such as bananas, eggs, tender cooked chicken, fish, smooth peanut butter, and applesauce, eaten as small frequent meals, and leave out raw vegetables, seeds, nuts, corn, popcorn, and tough skins. This is the riskiest window for a stoma blockage.
- Weeks 4–12: higher-fiber foods are usually reintroduced one at a time and chewed thoroughly. Many people keep a food diary for the first month, which makes cause-and-effect patterns obvious.
- Long term after ileostomy: hydration (2.5–3 L/day including oral rehydration), more salt than usual, and electrolyte monitoring during heat or exercise.
- Long term after J-pouch: most patients reach a near-normal diet by month 6. Slowing stool output may require soluble fiber (psyllium), loperamide, or bile-acid sequestrants — all compatible with a pouch.
See the sibling diet for inflammatory bowel disease article for longer-term eating strategies once healing is complete.
Key Research Papers
- Ponsioen CY, et al. Laparoscopic ileocaecal resection versus infliximab for terminal ileitis in Crohn's disease (LIR!C): a randomised controlled, open-label, multicentre trial. Lancet Gastroenterol Hepatol. 2017. — doi:10.1016/S2468-1253(17)30248-0
- Stevens TW, et al. Laparoscopic ileocaecal resection versus infliximab for terminal ileitis in Crohn's disease: retrospective long-term follow-up of the LIR!C trial. Lancet Gastroenterol Hepatol. 2020. — doi:10.1016/S2468-1253(20)30117-5
- Rutgeerts P, et al. Predictability of the postoperative course of Crohn's disease. Gastroenterology. 1990. — doi:10.1016/0016-5085(90)90613-6 (Original Rutgeerts score.)
- Travis S, et al. Vedolizumab for the treatment of chronic pouchitis (EARNEST). N Engl J Med. 2023. — doi:10.1056/NEJMoa2208450
- Fazio VW, et al. Ileal pouch anal anastomosis: analysis of outcome and quality of life in 3707 patients. Ann Surg. 2013. — doi:10.1097/sla.0b013e31827d99a2
- Waljee A, et al. Threefold increased risk of infertility: a meta-analysis of infertility after ileal pouch anal anastomosis in ulcerative colitis. Gut. 2006. — doi:10.1136/gut.2005.090316
- Nguyen N, Zhang B, Holubar SD, Pardi DS, Singh S. Treatment and prevention of pouchitis after ileal pouch-anal anastomosis for chronic ulcerative colitis. Cochrane Database Syst Rev. 2019;11:CD001176. — PubMed PMID: 31785173
- Colombel JF, Garcia Olmo D, Chen ST, et al. Darvadstrocel in Patients With Crohn's Disease With Complex Perianal Fistulas: The ADMIRE CD II Phase 3 Randomized Trial. Gastroenterology. 2026;170(7):1562-1570. — PubMed PMID: 41790076
PubMed Topic Searches
For deeper reading, these PubMed topic searches return current peer-reviewed work on inflammatory bowel disease surgical decision-making, reconstruction, and post-operative care:
- PubMed: LIR!C trial and ileocecal resection in Crohn's
- PubMed: Stricturoplasty in Crohn's disease
- PubMed: Perianal Crohn's fistula management
- PubMed: Rutgeerts score and post-operative recurrence
- PubMed: Ileal pouch-anal anastomosis outcomes
- PubMed: Pouchitis and vedolizumab (EARNEST)
- PubMed: IPAA and female fertility
- PubMed: Permanent ileostomy and quality of life
- PubMed: Surgeon volume and colorectal surgery outcomes
- PubMed: Kock pouch and continent ileostomy
Connections
- Gastroenterology
- Inflammatory Bowel Disease Overview
- Crohn's vs Ulcerative Colitis: Key Differences
- Diagnostic Workup: Calprotectin, Colonoscopy, MRE
- Biologics: Tumor Necrosis Factor, IL-23, and Integrin Inhibitors
- JAK Inhibitors and S1P Modulators
- Diet for IBD: SCD and Mediterranean
- Extraintestinal Manifestations: Joints, Skin, Eyes
- Inflammatory Bowel Disease Fatigue, Anemia, and Nutrient Deficiencies
- Pregnancy and Inflammatory Bowel Disease
- Crohn's Disease
- Ulcerative Colitis
- Diverticulitis
- Irritable Bowel Syndrome
- Chronic Diarrhea
- AS and Inflammatory Bowel Disease Overlap