Lipoprotein(a): The Inherited Heart Risk Factor Guidelines Recommend Measuring Once

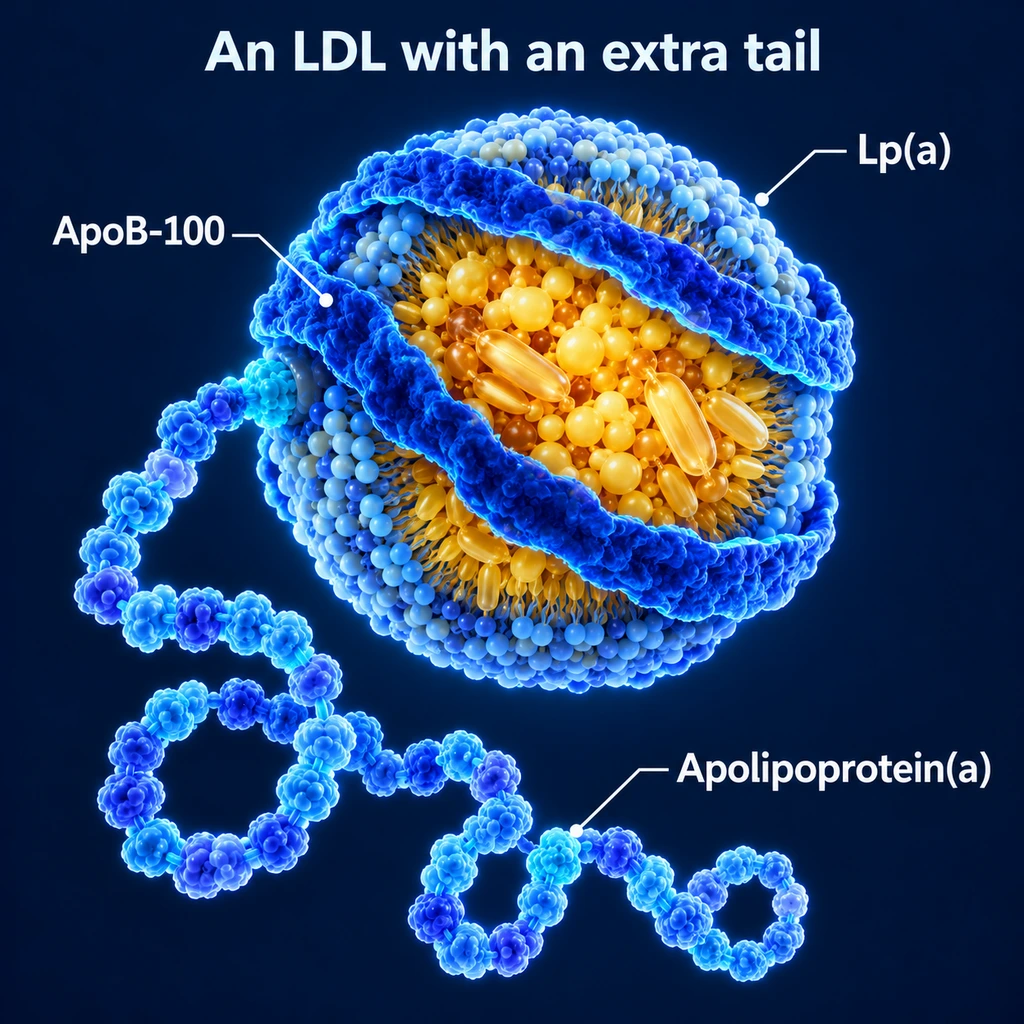
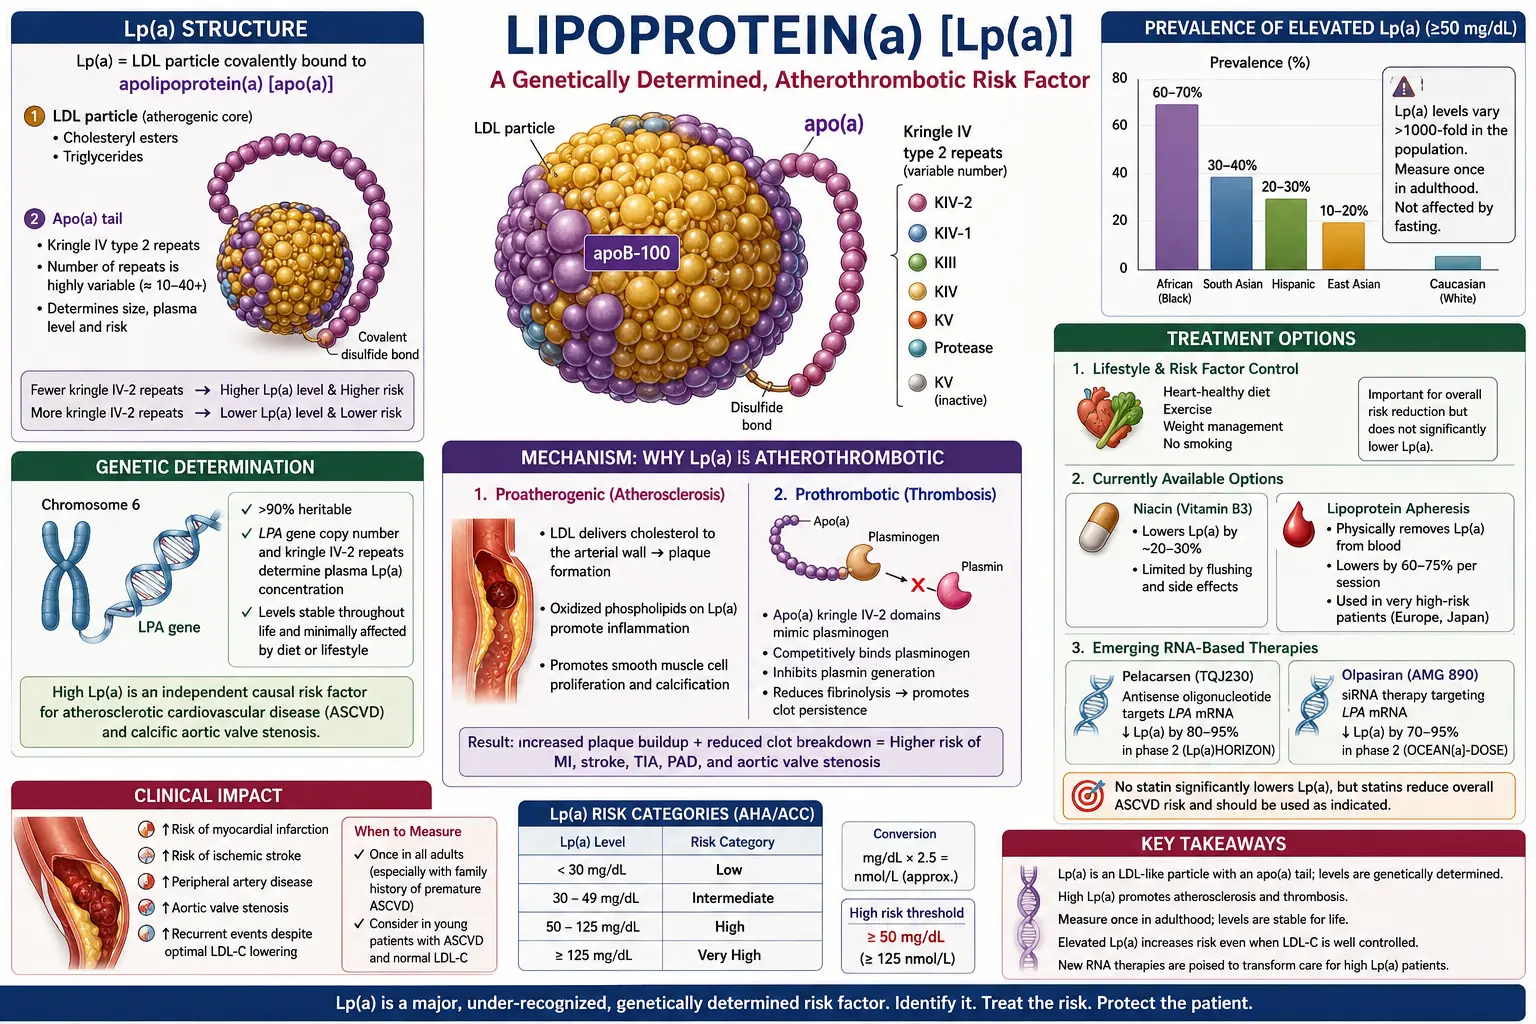
Lipoprotein(a), pronounced “lipoprotein little a” and written Lp(a), is a low-density lipoprotein-like particle with a distinctive extra protein called apolipoprotein(a) stitched to it. Lp(a) level is roughly 90 percent genetically determined, remains essentially stable across a lifetime, and confers independent cardiovascular risk that is not captured by any other standard test — including low-density lipoprotein (LDL) cholesterol, ApoB, or blood pressure. An estimated one in five adults has elevated Lp(a) and most do not know it, because the test is not part of a routine lipid panel.
Elevated Lp(a) is a major risk factor for premature coronary artery disease, stroke, aortic stenosis, and peripheral artery disease. Because the level is stable, the 2022 European Atherosclerosis Society consensus statement recommends testing Lp(a) concentration at least once in adults (PubMed PMID: 36036785).
Table of Contents
What Lp(a) Is
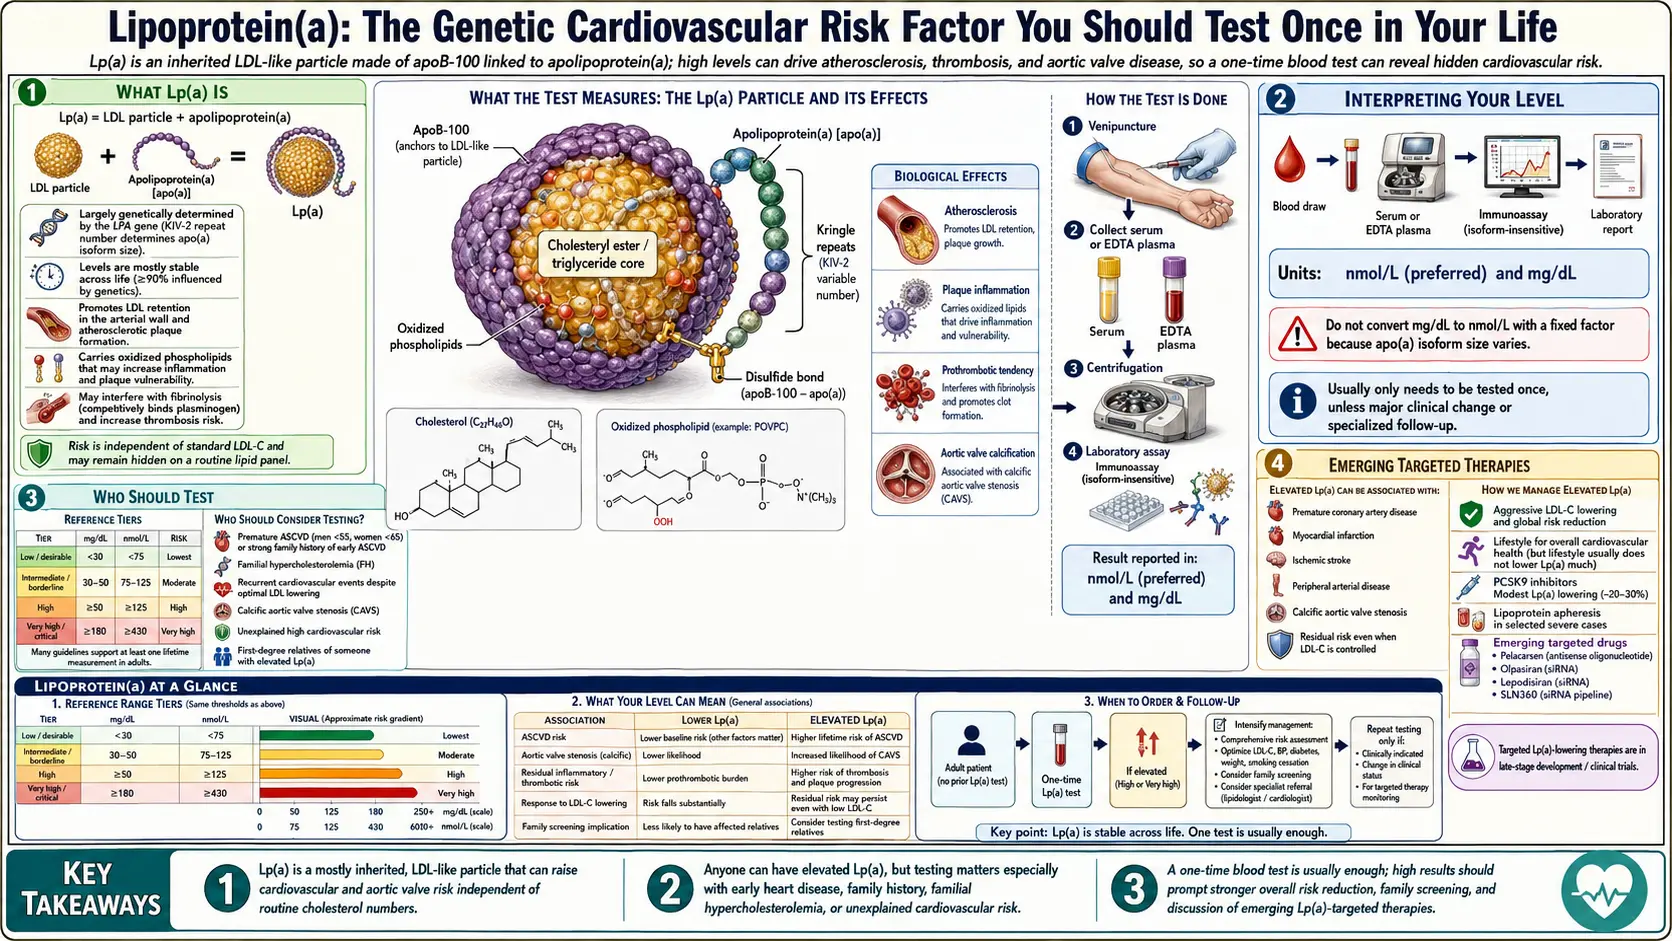
An Lp(a) particle is structurally similar to low-density lipoprotein — a single ApoB-100 molecule wraps a cholesterol-rich core — with one additional protein, apolipoprotein(a), bound by a disulfide bond. Apolipoprotein(a) is a highly variable protein encoded by the LPA gene; the number of kringle-IV repeats in it determines circulating Lp(a) level (shorter isoforms produce higher levels). Population levels span four orders of magnitude, from undetectable to over 300 mg/dL.
How Lp(a) Drives Disease
- Atherosclerosis. Like low-density lipoprotein, Lp(a) can enter the artery wall and deposit cholesterol.
- Thrombosis. Apolipoprotein(a) resembles plasminogen and can interfere with fibrinolysis, promoting clot formation.
- Inflammation. Lp(a) carries oxidized phospholipids, potent drivers of vascular inflammation.
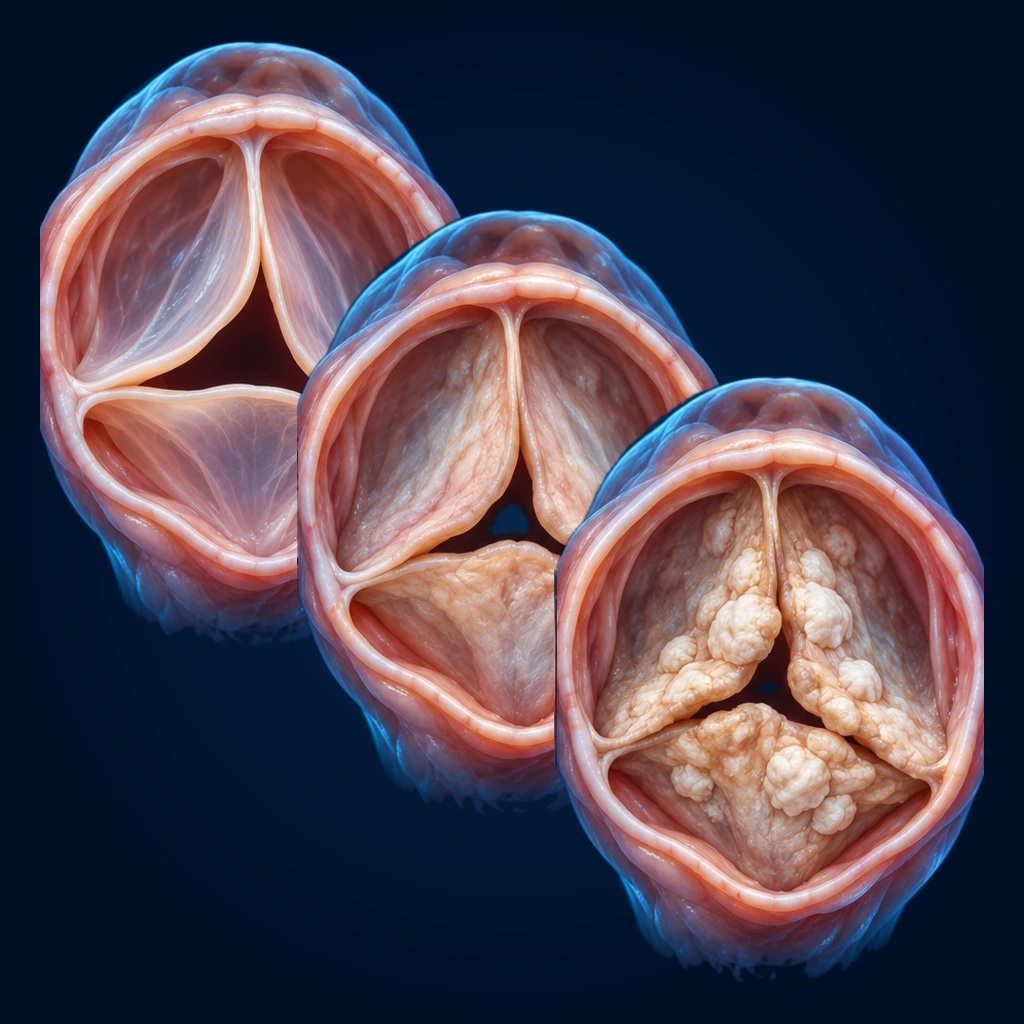
- Aortic valve calcification. Lp(a) is the dominant causal risk factor for calcific aortic stenosis.
Mendelian-randomization studies — which use genetic variation to establish causality — confirm that lifetime Lp(a) exposure causally drives coronary disease and aortic stenosis.
Interpreting an Lp(a) Level
- <30 mg/dL (<75 nmol/L): Low risk attributable to Lp(a).
- 30–50 mg/dL (75–125 nmol/L): Moderate risk.
- 50–100 mg/dL (125–250 nmol/L): High risk.
- >100 mg/dL (>250 nmol/L): Very high risk. The 2022 European Atherosclerosis Society consensus statement recommends early, intensive management of other cardiovascular risk factors, targeted to global risk and Lp(a) level.
Units matter: nmol/L is increasingly preferred because it reflects particle concentration. Mass units (mg/dL) can mislead because particle size varies.
Who the Guidelines Name for Testing
The 2022 European Atherosclerosis Society consensus statement recommends testing Lp(a) at least once in adults, and notes the potential value of cascade (family) testing in familial hypercholesterolaemia and in people with a family or personal history of (very) high Lp(a) or premature cardiovascular disease (PubMed PMID: 36036785). Groups commonly named for testing:
- Every adult, at least once.
- People with a personal or family history of premature cardiovascular disease (<55 in men, <65 in women).
- People with unexplained cardiovascular events despite normal standard risk factors.
- First-degree relatives of a person with elevated Lp(a) — the trait is inherited.
How Elevated Lp(a) Is Managed
There is no approved drug that specifically targets Lp(a) yet (several are being tested in cardiovascular-outcomes trials, and the first of these reported topline results in 2026 — see below). Without specific Lp(a)-lowering therapies, the 2022 European Atherosclerosis Society consensus statement recommends early, intensive management of every other cardiovascular risk factor (PubMed PMID: 36036785). The measures usually described:
- Intensive lowering of ApoB and low-density lipoprotein cholesterol (LDL-C) — high-intensity statin, ezetimibe, and PCSK9 inhibitors where indicated.
- Blood-pressure control (<120/80).
- Control of diabetes, smoking, and insulin resistance.
- Low-dose aspirin, discussed with a clinician, in some very-high-risk individuals.
- A Mediterranean-style diet, regular exercise, and weight optimization.
- Imaging (coronary calcium, computed tomography (CT) angiography, carotid ultrasound) to refine overall risk.
Statins do not lower Lp(a); niacin modestly lowers it but without outcomes benefit. PCSK9 inhibitors lower Lp(a) by roughly 20–30%. Lipoprotein apheresis can acutely lower Lp(a) and is used in extreme cases.
Emerging Targeted Therapies
Several candidate drugs that strongly lower Lp(a) are being tested in cardiovascular-outcomes trials:
- Pelacarsen — an antisense oligonucleotide, reduces Lp(a) by 80–90%. It was tested in Lp(a)HORIZON, the first large phase-3 outcomes trial of an Lp(a)-lowering drug, in people with established cardiovascular disease. Topline results announced in September 2026 showed that pelacarsen lowered Lp(a) but did not significantly reduce the main combined cardiovascular endpoint; complete peer-reviewed results are not yet available.
- Olpasiran — a small interfering RNA (siRNA), similar reductions with infrequent dosing. Zerlasiran and lepodisiran are other drugs of the same kind.
- Muvalaplin — an oral small molecule that blocks apolipoprotein(a) assembly.
The neutral HORIZON topline result leaves open whether, and under what conditions, lowering Lp(a) translates into fewer cardiovascular events. Full peer-reviewed HORIZON data and the outcome trials still running for olpasiran, zerlasiran, lepodisiran and muvalaplin are expected to answer this.
Key Research Papers
The first two entries are 2026 reviews of the Lp(a)HORIZON topline result. The rest are curated PubMed literature searches covering the evidence base for Lipoprotein(a) testing, interpretation, and clinical management. Each link opens a live, filtered PubMed query so the results stay current as new studies are indexed.
- Sabouret P, Giamundo DM, Asher E, De Rosa S, Andò G, Gragnano F, Blumenthal RS, Atar D, Mamas MA (2026). Pelacarsen and Lp(a)HORIZON: Interpreting the Disconnect Between Lipoprotein(a) Lowering and Cardiovascular Outcomes. American Journal of Medicine. — PubMed PMID: 42880684
- Gogan A, Ardelean S, Rus D, Căruntu FR, Buz BF, Parvanescu T, Andor M (2026). Lipoprotein(a) After Myocardial Infarction: Residual Risk, Measurement, and the Unresolved Therapeutic Question. Biomedicines. — PubMed PMID: 42940145
- Lipoprotein(a) cardiovascular risk — PubMed literature search
- Lp(a) genetics — PubMed literature search
- Lp(a) and atherosclerosis — PubMed literature search
- Lp(a) and aortic stenosis — PubMed literature search
- Pelacarsen Lp(a) lowering trial — PubMed literature search
- Lp(a) assay standardization — PubMed literature search
- PCSK9 inhibitors and Lp(a) — PubMed literature search
- Niacin and Lp(a) — PubMed literature search
- Lp(a) population screening — PubMed literature search
- Lp(a) Mendelian randomization — PubMed literature search
External Authoritative Resources
Connections
- All Lab Tests
- ApoB
- Lipid Panel
- Coronary Calcium Score
- Atherosclerosis
- Coronary Artery Disease
- Cardiovascular Disease
- Stroke
- Peripheral Artery Disease
- Insulin Resistance
- Diabetes
- Omega-3 Fatty Acids
- Anti-Inflammatory Diet
- Calcium
- Full Body Magnetic Resonance Imaging
- Soft Plaque and Coronary Artery Calcium Limitations
- Statin Threshold and Coronary Artery Calcium
- Coronary Artery Calcium Zero and the Power of Negative Result
- MESA Risk Calculator and Age Percentiles
- Valvular Heart Disease
Featured Videos