Oral Microbiome — Benefits Deep Dive
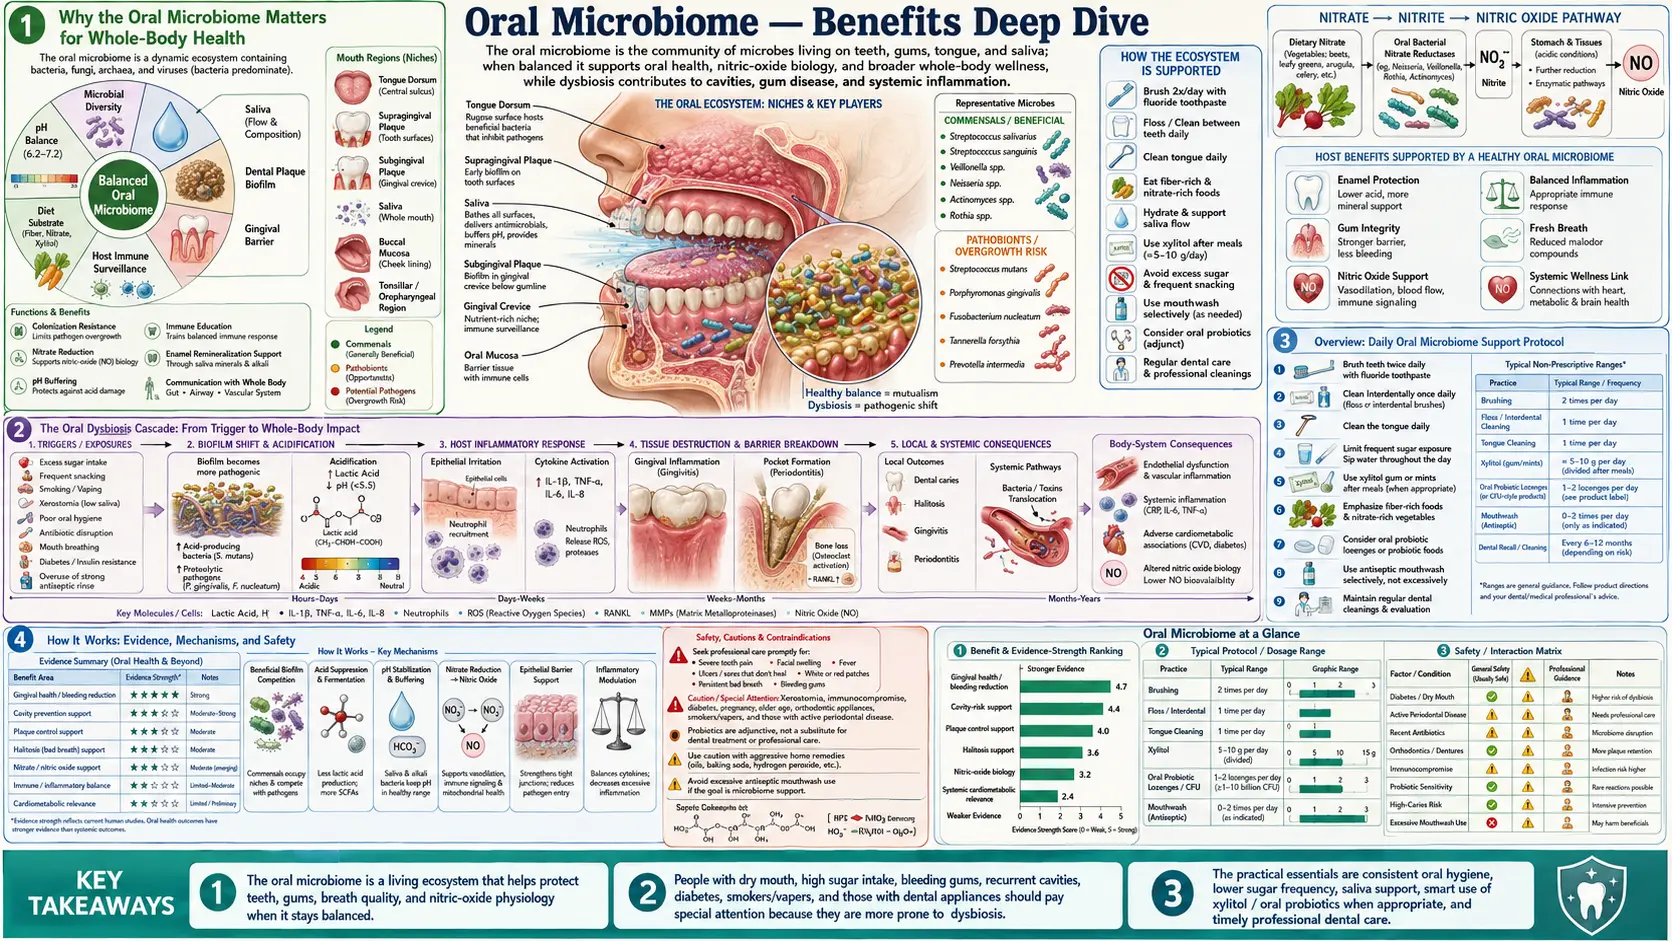
The oral microbiome is the second most diverse microbial community in the human body after the gut — roughly 700 bacterial species colonize the teeth, gingival sulcus, tongue, palate, cheek mucosa, and saliva. Unlike the gut, which is partitioned from the bloodstream by an intact epithelial barrier, the oral cavity bleeds easily and intimately into the systemic circulation through the highly vascular gingival tissue. This is one proposed reason oral dysbiosis is linked with cardiovascular disease, Alzheimer's, rheumatoid arthritis, preterm birth, and gut microbiome composition — links documented as associations, not as proven cause and effect. The four deep-dive pages below explore four low-cost, non-pharmaceutical interventions aimed at a healthy oral microbiome — hydroxyapatite toothpaste as an alternative to fluoride, oil pulling, tongue scraping, and targeted oral probiotic strains.
Deep-Dive Articles
Hydroxyapatite vs Fluoride
Why nano-hydroxyapatite (n-HAp) toothpaste, originally developed by NASA in the 1970s for astronaut tooth-remineralization and refined in Japan as an over-the-counter (OTC) nano-hydroxyapatite toothpaste, is now backed by randomized trials showing non-inferiority to fluoride toothpaste for caries prevention (in an 18-month trial of 189 adults, 89.3% on hydroxyapatite and 87.4% on 1,450 ppm fluoride had no new decay) — without the dose-dependent fluorosis, neurodevelopmental, and thyroid concerns associated with systemic fluoride exposure. The biochemistry of enamel remineralization, the calcium-phosphate vs calcium-fluoride lattice, and the consumer-product landscape.
Read the deep dive →Oil Pulling
The traditional Ayurvedic practice of swishing 1 tablespoon of cold-pressed coconut or sesame oil in the mouth for 10-20 minutes daily. A 2024 meta-analysis of 25 randomized trials (1,184 people) found a probable benefit for gum inflammation — oil pulling beat non-chlorhexidine mouthwashes on gingival scores — while chlorhexidine mouthwash remained better at reducing plaque; the overall quality of the evidence was very low. In one small 4-day crossover trial (29 people), coconut-oil pulling held back plaque regrowth about as well as chlorhexidine, with less tooth staining; practitioners also point to the absence of chlorhexidine's microbiome disruption. The lauric acid in coconut oil and its conversion to monolaurin gives the practice its specific antimicrobial action.
Read the deep dive →Tongue Scraping
A two-thousand-year-old Ayurvedic practice using a U-shaped copper or stainless steel scraper to mechanically remove the coating (biofilm) in which volatile sulfur compound (VSC)-producing bacteria live on the posterior dorsum of the tongue. In one 10-person crossover study, a scraper cut VSCs by 75%, against 45% for a toothbrush; a 16-person study found two weeks of scraping or brushing reduced tongue coating and improved taste but barely changed the number of bacteria on the tongue (less than 0.5 log). Why tongue scraping out-performs tongue brushing.
Read the deep dive →Oral Probiotic Strains
The three oral-cavity-specific probiotic strains with the strongest randomized-trial evidence: Streptococcus salivarius K12 and M18 for halitosis, strep throat, and otitis media; a Lactobacillus reuteri lozenge (strains DSM 17938 + ATCC PTA 5289) for gingivitis and periodontitis; and Lactobacillus paracasei for ear infections and dental caries reduction. Why oral-specific strains have the most mouth-focused trials — though one gut strain, Lactobacillus rhamnosus GG given in milk, reduced caries in a 594-child trial — and how lozenge format matters.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why the Oral Microbiome Matters for Whole-Body Health
- The Oral Dysbiosis Cascade
- Research Papers: Hydroxyapatite vs Fluoride
- Research Papers: Oil Pulling
- Research Papers: Tongue Scraping
- Research Papers: Oral Probiotic Strains
- Research Papers: Oral-Systemic Links
- External Authoritative Resources
- Connections
- Featured Videos
Why the Oral Microbiome Matters for Whole-Body Health
The mouth is unique among microbial habitats. Unlike the colon, where 38 trillion bacteria are partitioned from the bloodstream by a single layer of enterocytes plus a thick mucin layer plus the largest concentration of immune tissue in the body, the gingival sulcus — the V-shaped pocket between tooth and gum — is a fragile junction that bleeds even from gentle flossing in a healthy mouth. In gingivitis or periodontitis, that bleeding becomes constant and the bacterial entry into the bloodstream becomes a continuous low-grade systemic insult.
Three links are well documented as associations; causation is not established:
- Cardiovascular disease — Porphyromonas gingivalis, the keystone periodontal pathogen, has been recovered intact from human carotid atheroma plaque by polymerase chain reaction (PCR) and culture. Periodontitis raises C-reactive protein (CRP) and interleukin-6 (IL-6) and is independently associated with increased risk of myocardial infarction and stroke even after adjustment for traditional cardiovascular risk factors. The 2012 American Heart Association scientific statement concluded that observational studies support an association independent of known confounders but “do not, however, support a causative relationship,” and that “there is no evidence” periodontal treatment prevents atherosclerotic vascular disease or changes its outcomes.
- Alzheimer's disease — P. gingivalis DNA, and the bacterium's characteristic gingipain proteases, have been detected in postmortem Alzheimer brain tissue at higher rates than in cognitively normal controls (Dominy et al. 2019). The hypothesis that chronic oral pathogen translocation drives a fraction of late-life cognitive decline was tested with the gingipain inhibitor atuzaginstat, which failed its primary endpoints in the Phase 2/3 GAIN trial, with benefits reported only in a subgroup of participants positive for P. gingivalis; a follow-on inhibitor is in a Phase 2 trial. A 2026 review states that “direct targeting of a single periodontal pathogen has not shown clinical benefit.”
- Pregnancy outcomes — Fusobacterium nucleatum, an oral commensal, is recovered from amniotic fluid in cases of preterm birth and stillbirth. Periodontitis is associated with approximately 2-fold increased risk of preterm low-birth-weight delivery. Whether treating gum disease in pregnancy lowers preterm birth is unsettled: the 823-woman OPT trial (2006) found preterm birth in 12.0% of treated and 12.8% of untreated women, no significant difference; a 2017 Cochrane review of 15 trials found “no clear difference in preterm birth” (risk ratio 0.87, 95% confidence interval 0.70 to 1.10, low-quality evidence), with low-quality evidence that low birth weight may fall; and a 2026 meta-analysis of 14 trials (8,316 participants) found a risk ratio of 0.85 (0.71 to 1.02, moderate certainty), concluding treatment “may reduce” preterm birth.
Beyond these systemic associations, the oral microbiome also seeds the gut: most swallowed saliva passes the stomach and contributes oral microbes to the small intestine and colon. Patients with periodontitis have measurably higher gut abundance of oral-origin taxa, including the same F. nucleatum that is now strongly linked to colorectal cancer. A healthy mouth feeds a healthy gut, not just figuratively.
What is not known. None of these links has been shown to be cause and effect. Gum-treatment trials have not shown fewer heart attacks or strokes, the one Alzheimer's drug trial aimed at the gum bacterium failed its main goals, and gum treatment in pregnancy gave null results in large trials and a borderline result in the newest pooled analysis.
A rare lung hazard of oil pulling. Doctors in Japan described two people who developed lipoid pneumonia (oil in the lungs, seen as hazy “ground-glass” patches on a chest scan) after several months of habitual sesame-oil pulling, one with a dry cough and one with shortness of breath. One improved with steroids and a lung wash-out (bronchoalveolar lavage); the other needed no intensive treatment. A Korean report described recurrent lipoid pneumonia associated with oil pulling.
The Oral Dysbiosis Cascade
A healthy oral microbiome is dominated by commensal Streptococcus (especially S. salivarius, S. sanguinis, S. mitis), Veillonella, Actinomyces, Rothia, and Neisseria species that maintain a near-neutral pH at the tooth surface, produce hydrogen peroxide and bacteriocins that suppress pathogenic species, and form a stable biofilm that competitively excludes invasive organisms.
The dysbiosis cascade typically proceeds in three stages:
- Acid stress (caries-favoring dysbiosis) — frequent dietary sugar intake feeds Streptococcus mutans and Lactobacillus species, which produce lactic acid that drops local pH below the critical 5.5 threshold for hydroxyapatite demineralization. Repeated demineralization cycles erode the enamel surface and create the carious lesion. The driver here is dietary sugar frequency, not total sugar — the mouth recovers between exposures, but not if exposures are continuous (sipping a sugary drink all afternoon is far worse than the same amount consumed at one sitting).
- Inflammation-favoring dysbiosis (gingivitis) — plaque accumulation along the gumline drives a local inflammatory response. Aggregatibacter actinomycetemcomitans, Tannerella forsythia, and Treponema denticola begin to displace commensals. Gums become red, swollen, and bleed easily. This stage is fully reversible with mechanical plaque removal.
- Red-complex dysbiosis (periodontitis) — P. gingivalis becomes the keystone organism, suppressing local immune defenses through its gingipain proteases and reshaping the entire microbial community toward the red complex (P. gingivalis + T. forsythia + T. denticola). The periodontal pocket deepens, bone is resorbed around the tooth root, and the tooth eventually loosens. This stage is not fully reversible — once bone is lost, it doesn't come back without surgical intervention.
The four deep-dive interventions below address different stages of this cascade. Hydroxyapatite addresses stage 1 (remineralization of acid-stressed enamel). Oil pulling and tongue scraping are aimed at stage 2: oil pulling at plaque and gum inflammation, and tongue scraping at the tongue coating that odour-producing bacteria feed on — a 16-person study found scraping barely changed the number of bacteria on the tongue but did remove the coating and improve taste. Oral probiotics address all three stages by restoring competitive exclusion from commensal taxa.
Research Papers: Hydroxyapatite vs Fluoride
- Amaechi BT et al. (2019). Comparative efficacy of a hydroxyapatite and a fluoride toothpaste for prevention and remineralization of dental caries in children. BDJ Open 5:18. Despite its title, an in situ study: enamel blocks from children's primary teeth were worn in mouth appliances by 30 adults for 14 days per arm; 10% hydroxyapatite and 500 ppm fluoride toothpaste did not differ significantly. — PubMed PMID: 31839988
- O'Hagan-Wong K et al. (2022). The use of hydroxyapatite toothpaste to prevent dental caries. Odontology. — PubMed
- Kani T et al. (1989). Effect of apatite-containing dentifrices on dental caries in school children (the original Japanese apatite-toothpaste trial). — PubMed
- Hannig M, Hannig C (2010). Nanomaterials in preventive dentistry. Nature Nanotechnology. — PubMed
- NASA hydroxyapatite enamel remineralization research history — PubMed
- Najibfard K et al. (2011). Remineralization of early caries by a nano-hydroxyapatite dentifrice. — PubMed
- Bashash M et al. (2017). Prenatal fluoride exposure and cognitive outcomes in children. Environmental Health Perspectives. — PubMed
- Grandjean P (2019). Developmental fluoride neurotoxicity: an updated review. — PubMed
- NTP fluoride monograph 2024 (US National Toxicology Program review) — PubMed
- Esteves-Oliveira M et al. (2017). Caries-preventive effect of anti-erosive and nano-hydroxyapatite-containing toothpastes. — PubMed
- Paszynska E, Pawinska M, Enax J, et al. (2023). Caries-preventing effect of a hydroxyapatite-toothpaste in adults: a 18-month double-blinded randomized clinical trial. Frontiers in Public Health 11:1199728. 189 adults; no increase in decayed, missing or filled surfaces in 89.3% (hydroxyapatite) vs 87.4% (1,450 ppm fluoride); hydroxyapatite “not statistically inferior”. — PubMed PMID: 37533523
- Pawinska M, Paszynska E, Amaechi BT, Meyer F, Enax J, Limeback H (2024). Clinical evidence of caries prevention by hydroxyapatite: An updated systematic review and meta-analysis. Journal of Dentistry 151:105429. Pooled 5 clinical trials and 8 in situ trials and concluded fluoride-free hydroxyapatite toothpastes and rinses reduce caries; the paper discloses that two authors are employed by a toothpaste maker and that all authors received travel grants from it. — PubMed PMID: 39471896
- Taylor KW, Eftim SE, Sibrizzi CA, Blain RB, Magnuson K, Hartman PA, Rooney AA, Bucher JR (2025). Fluoride Exposure and Children's IQ Scores: A Systematic Review and Meta-Analysis. JAMA Pediatrics 179(3):282–292. 74 studies (45 from China): higher fluoride exposure was linked to lower children's IQ, with IQ 1.63 points lower per 1 mg/L more fluoride in urine; the link was uncertain for drinking water alone below 1.5 mg/L. — PubMed PMID: 39761023
Research Papers: Oil Pulling
- Asokan S et al. (2009). Effect of oil pulling on plaque induced gingivitis: a randomized, controlled, triple-blind study. Indian Journal of Dental Research. — PubMed
- Asokan S et al. (2008). Effect of oil pulling on Streptococcus mutans count in plaque and saliva using Dentocult SM Strip mutans test. — PubMed
- Peedikayil FC et al. (2015). Effect of coconut oil in plaque related gingivitis — a preliminary report. Nigerian Medical Journal. — PubMed
- Naseem M et al. (2017). Oil pulling and importance of traditional medicine in oral health maintenance. International Journal of Health Sciences. — PubMed
- Shanbhag VK (2017). Oil pulling for maintaining oral hygiene — a review. Journal of Traditional and Complementary Medicine. — PubMed
- Lauric acid and monolaurin antimicrobial mechanism — PubMed
- Anand TD et al. (2008). Effect of oil-pulling on dental caries causing bacteria. African Journal of Microbiology Research. — PubMed
- Sezgin Y, Memis Ozgul B, Alptekin NO (2019). Efficacy of oil pulling therapy with coconut oil on four-day supragingival plaque growth: A randomized crossover clinical trial. Complementary Therapies in Medicine 47:102193. 29 volunteers, 4 days per arm. — PubMed PMID: 31780023
- Kaushik M et al. (2016). The effect of coconut oil pulling on Streptococcus mutans count in saliva in comparison with chlorhexidine mouthwash. — PubMed
- Jong FJX, Ooi J, Teoh SL (2024). The effect of oil pulling in comparison with chlorhexidine and other mouthwash interventions in promoting oral health: A systematic review and meta-analysis. International Journal of Dental Hygiene 22(1):78–94. 25 trials, 1,184 participants; chlorhexidine better for plaque, probable gum benefit, very low quality of evidence. — PubMed PMID: 37635453
- Kuroyama M, Kagawa H, Kitada S, Maekura R, Mori M, Hirano H (2015). Exogenous lipoid pneumonia caused by repeated sesame oil pulling: a report of two cases. BMC Pulmonary Medicine 15:135. — PubMed PMID: 26518258
- Kim JY, Jung JW, Choi JC, Shin JW, Park IW, Choi BW (2014). Recurrent lipoid pneumonia associated with oil pulling. International Journal of Tuberculosis and Lung Disease 18(2):251–252. — PubMed PMID: 24429325
Research Papers: Tongue Scraping
- Outhouse TL, Al-Alawi R, Fedorowicz Z, Keenan JV (2006). Tongue scraping for treating halitosis. Cochrane Database of Systematic Reviews. WITHDRAWN by Cochrane Oral Health as of Issue 5, 2016; it is being replaced by a broader review of interventions for halitosis. — PubMed PMID: 27227886
- Pedrazzi V et al. (2004). Tongue-cleaning methods: a comparative clinical trial employing a toothbrush and a tongue scraper. Journal of Periodontology 75(7):1009–1012. 10-person crossover: scraper 75% fewer VSCs, toothbrush 45%. — PubMed PMID: 15341360
- Quirynen M et al. (2004). Impact of tongue cleansers on microbial load and taste. Journal of Clinical Periodontology 31(7):506–510. 16 people, 2 weeks: negligible change in tongue bacteria (<0.5 log), less coating, better taste. — PubMed PMID: 15191584
- Van der Sleen MI et al. (2010). Effectiveness of mechanical tongue cleaning on breath odour and tongue coating: a systematic review. International Journal of Dental Hygiene. — PubMed
- Yaegaki K, Coil JM (2000). Examination, classification, and treatment of halitosis; clinical perspectives. — PubMed
- Volatile sulfur compounds (VSCs) and tongue dorsum bacteria — PubMed
- Faveri M et al. (2006). A cross-over study on the effect of various therapeutic approaches to morning breath odour. — PubMed
- Tongue coating index and oral hygiene measurement — PubMed
- Roldan S et al. (2003). The effects of a new mouthrinse containing chlorhexidine, cetylpyridinium chloride and zinc lactate on the microflora of oral halitosis patients. — PubMed
Research Papers: Oral Probiotic Strains
- Burton JP et al. (2006). A preliminary study of the effect of probiotic Streptococcus salivarius K12 on oral malodour parameters. Journal of Applied Microbiology. — PubMed
- Di Pierro F et al. (2014). Use of Streptococcus salivarius K12 in the prevention of streptococcal and viral pharyngotonsillitis in children. Drug, Healthcare and Patient Safety. — PubMed
- Burton JP et al. (2013). Influence of the probiotic Streptococcus salivarius strain M18 on indices of dental health in children. — PubMed
- Krasse P et al. (2006). Decreased gum bleeding and reduced gingivitis by the probiotic Lactobacillus reuteri. Swedish Dental Journal. — PubMed
- Vivekananda MR et al. (2010). Effect of the probiotic Lactobacilli reuteri (Prodentis) in the management of periodontal disease. Journal of Oral Microbiology. — PubMed
- Tekce M et al. (2015). Clinical and microbiological effects of probiotic lozenges in the treatment of chronic periodontitis. — PubMed
- Náse L et al. (2001). Effect of long-term consumption of a probiotic bacterium, Lactobacillus rhamnosus GG, in milk on dental caries and caries risk in children. Caries Research 35(6):412–420. 594 children aged 1–6, 7 months: less caries and lower mutans streptococcus counts; caries risk odds ratio 0.56. — PubMed PMID: 11799281
- Wescombe PA et al. (2009). Streptococcus salivarius K12: a colonizing oral probiotic. Future Microbiology. — PubMed
- Power DA et al. (2008). Preliminary investigations of the colonisation of upper respiratory tract tissues of infants using a paediatric formulation of the oral probiotic Streptococcus salivarius K12. — PubMed
- Stensson M et al. (2014). Oral administration of Lactobacillus reuteri during the first year of life reduces caries prevalence in the primary dentition. Caries Research. — PubMed
Research Papers: Oral-Systemic Links
- Dominy SS et al. (2019). Porphyromonas gingivalis in Alzheimer's disease brains: evidence for disease causation and treatment with small-molecule inhibitors. Science Advances. — PubMed
- Haraszthy VI et al. (2000). Identification of periodontal pathogens in atheromatous plaques. Journal of Periodontology. — PubMed
- Lockhart PB et al. (2012). Periodontal disease and atherosclerotic vascular disease: does the evidence support an independent association?: a scientific statement from the American Heart Association. Circulation 125(20):2520–2544. Association supported, causation not; no evidence treatment prevents vascular disease. — PubMed PMID: 22514251
- Han YW et al. (2010). Term stillbirth caused by oral Fusobacterium nucleatum. Obstetrics & Gynecology. — PubMed
- Castellarin M et al. (2012). Fusobacterium nucleatum infection is prevalent in human colorectal carcinoma. Genome Research. — PubMed
- Mougeot JC et al. (2017). Porphyromonas gingivalis is the most abundant species detected in coronary and femoral arteries. Journal of Oral Microbiology. — PubMed
- Olsen I, Yamazaki K (2019). Can oral bacteria affect the microbiome of the gut? Journal of Oral Microbiology. — PubMed
- Bui FQ et al. (2019). Association between periodontal pathogens and systemic disease. Biomedical Journal. — PubMed
- Hajishengallis G (2015). Periodontitis: from microbial immune subversion to systemic inflammation. Nature Reviews Immunology. — PubMed
- Kassebaum NJ et al. (2014). Global burden of severe periodontitis in 1990-2010: a systematic review and meta-regression. Journal of Dental Research. — PubMed
- Michalowicz BS, Hodges JS, DiAngelis AJ, et al.; OPT Study (2006). Treatment of periodontal disease and the risk of preterm birth. New England Journal of Medicine 355(18):1885–1894. 823 women; preterm birth 12.0% treated vs 12.8% control (hazard ratio 0.93, 95% CI 0.63–1.37). — PubMed PMID: 17079762
- Iheozor-Ejiofor Z, Middleton P, Esposito M, Glenny AM (2017). Treating periodontal disease for preventing adverse birth outcomes in pregnant women. Cochrane Database of Systematic Reviews 6:CD005297. 15 trials, 7,161 participants; preterm birth RR 0.87 (0.70–1.10), low birth weight RR 0.67 (0.48–0.95), low-quality evidence. — PubMed PMID: 28605006
- Thomas C, Ahmed S, Berghella V, Brignardello-Petersen R, El-Rabbany M, Devion C, Ronzoni S (2026). Effect of dental treatments on reduction of preterm birth: a systematic review and meta-analysis. American Journal of Obstetrics & Gynecology MFM 8(3):101884. 14 trials, 8,316 participants; RR 0.85 (0.71–1.02), moderate certainty. — PubMed PMID: 41421601
- Dhar I, Gupta S, Mishra R, Dadhich A (2026). Gingipains as macromolecular mediators at the periodontal-brain interface: Mechanistic, diagnostic, and therapeutic evidence in Alzheimer's and Parkinson's diseases. International Journal of Biological Macromolecules 377:153320. Atuzaginstat failed its GAIN primary endpoints; LHP588 in the Phase 2 SPRING trial. — PubMed PMID: 42392383
- Bijoch J, Jędrasiak K (2026). Red Complex Pathogens, Periodontal Dysbiosis and Periodontal Therapy in Alzheimer's Disease and Dementia. Journal of Clinical Medicine 15(13). — PubMed PMID: 42452755
External Authoritative Resources
- eHOMD — Expanded Human Oral Microbiome Database — the canonical reference for oral microbial taxonomy maintained at the Forsyth Institute / Marine Biological Laboratory
- NIH NIDCR — National Institute of Dental and Craniofacial Research
- American Academy of Periodontology
- FDI World Dental Federation
- PubMed — All research on oral microbiome (~25,000+ papers)