Oral Probiotic Strains — S. salivarius K12, M18, and L. reuteri
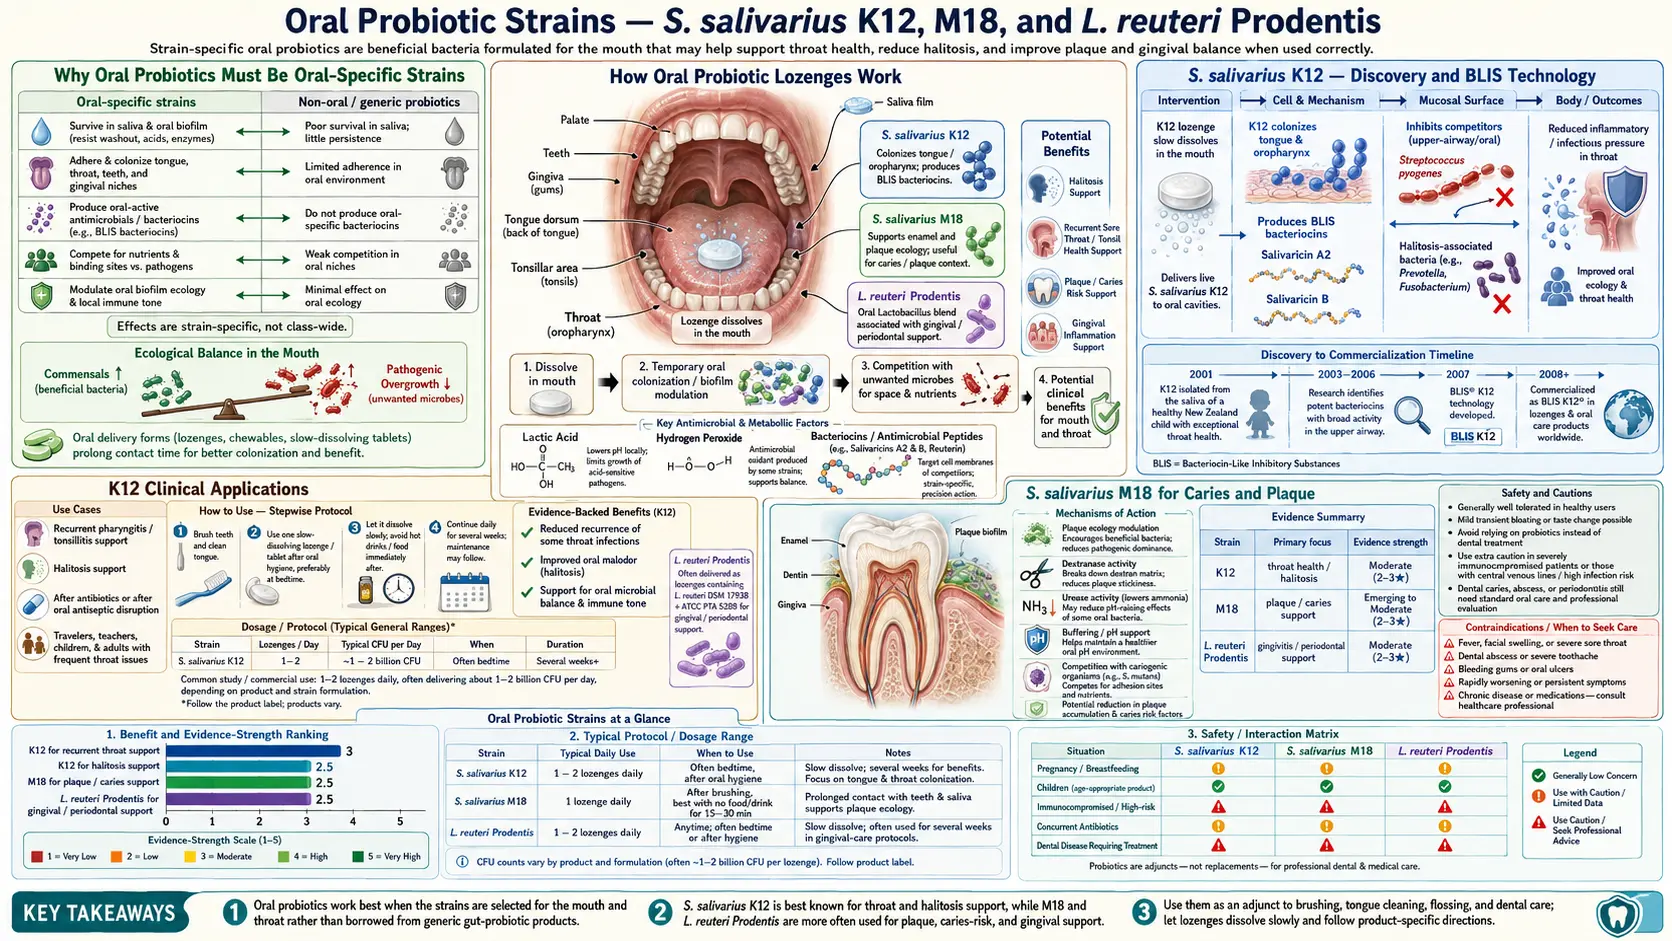
Most probiotic products on the market contain Lactobacillus and Bifidobacterium strains evolved for the lower gastrointestinal tract — they do nothing for the oral cavity because they cannot colonize the very different microenvironment of the mouth. Three specific probiotic strains, evolved or selected to colonize the oral cavity itself, have been tested in clinical trials for targeted oral indications: Streptococcus salivarius K12 for halitosis, recurrent streptococcal pharyngitis, and otitis media; S. salivarius M18 for caries reduction and plaque; and Lactobacillus reuteri (the strain combination DSM 17938 + ATCC PTA 5289) for gingivitis and periodontitis. All three are delivered in lozenge format, usually dissolved slowly in the mouth as the last thing before bed, so that the colonizing organisms can adhere to the oral epithelium overnight without being washed away by eating or drinking.
Table of Contents
- Why Oral Probiotics Must Be Oral-Specific Strains
- S. salivarius K12 — Discovery and BLIS Technology
- K12 Clinical Applications
- S. salivarius M18 for Caries and Plaque
- L. reuteri for Gingivitis and Periodontitis
- Alpha-Streptococcal Nasal Spray and Otitis Media
- Why Lozenge Format Matters
- Regimens Studied and Described, by Indication
- Cautions and Limitations
- Key Research Papers
- Connections
- Featured Videos
Why Oral Probiotics Must Be Oral-Specific Strains
A common consumer misconception is that any probiotic supplement will help with oral health. It will not. The oral cavity and the lower gastrointestinal tract are radically different microbial habitats:
- Oxygen — the mouth is aerobic to microaerophilic. The colon is strictly anaerobic. Strains that thrive in the colon (most Bifidobacterium, most Lactobacillus) are oxygen-sensitive and cannot colonize the mouth.
- pH — saliva pH is near-neutral (6.5-7.5), buffered tightly. Colon contents are also near-neutral but the stomach acid bath in between (pH 1-3) selects for acid-tolerant strains. Strains evolved to survive stomach transit may not be the strains best at oral colonization.
- Surfaces and biofilm — the mouth provides hard mineralized surfaces (teeth), keratinized mucosa (palate), and non-keratinized mucosa (cheek, tongue, floor of mouth). The colon provides only mucus-coated soft epithelium. Bacterial adhesion mechanisms are surface-specific.
- Diet — the oral microbiome encounters all food and drink in original form, including sugars, acids, alcohol, and antimicrobial spices. The colon receives only what survives upper digestion.
Strains that work in the oral cavity must (a) tolerate the local oxygen and pH conditions, (b) adhere to oral surfaces against the continuous washing by saliva swallowing, and (c) actively suppress competing pathogenic species through bacteriocin production or competitive exclusion. Only a small subset of probiotic strains meet all three requirements. The four that have the strongest evidence base are listed in this article.
Strains specifically NOT useful for oral health (despite being good gut probiotics):
- Most Bifidobacterium species — obligate anaerobes, cannot colonize mouth
- Lactobacillus acidophilus — can transiently inhabit mouth but does not colonize
- Lactobacillus rhamnosus GG (LGG) — minor effects on caries in milk-delivery studies but does not colonize the oral cavity
- Saccharomyces boulardii — a yeast probiotic for gut; no oral application
- Most "broad-spectrum" 10-strain probiotic blends marketed for general gut health
S. salivarius K12 — Discovery and BLIS Technology
Streptococcus salivarius is the most abundant bacterial species in the healthy human oral cavity. It colonizes the tongue, palate, throat, and saliva from the first 24 hours of life and remains a dominant member of the oral commensal community throughout the lifespan. Within the species, individual strains differ dramatically in their ability to produce inhibitory substances against pathogenic species.
The K12 strain was isolated in 1999 by Professor John Tagg at the University of Otago in New Zealand from the throat of a healthy child who had never experienced a strep throat infection — an unusually rare phenotype. Tagg's research group hypothesized that this child's natural resistance to strep throat was due to colonization with a particularly potent strain of S. salivarius that out-competed Streptococcus pyogenes (group A strep) by producing bacteriocins — protein antibiotics — that selectively killed the pathogen while leaving commensals intact.
This bacteriocin production capability was named BLIS (Bacteriocin-Like Inhibitory Substance) technology. K12 produces two characterized bacteriocins:
- Salivaricin A2 — active against multiple oral and pharyngeal pathogens
- Salivaricin B — active against Streptococcus pyogenes specifically
The combination of these two lantibiotics provides K12 with broad inhibitory activity against:
- Streptococcus pyogenes (strep throat)
- Volatile-sulfur-compound producing bacteria (halitosis)
- Some Moraxella catarrhalis strains (otitis media)
- Some Streptococcus pneumoniae strains
K12 is the most-studied oral probiotic strain. It is commercialized globally by a New Zealand company and licensed to multiple consumer brands. Cost is moderate ($20-30 per month) due to the need for specialized cold-chain manufacturing and lozenge formulation.
K12 Clinical Applications
The clinical evidence base for K12 covers three main indications:
- Halitosis — in a preliminary study, Burton 2006 in Journal of Applied Microbiology gave 23 subjects with halitosis a 3-day course of chlorhexidine mouth rinse, followed by lozenges containing K12 or placebo. One week after treatment began, 85% of the K12 group and 30% of the placebo group had substantial (>100 ppb) reductions in volatile sulfur compounds (VSCs). The mechanism is competitive exclusion of the gram-negative anaerobes (predominantly tongue-coating bacteria, see Tongue Scraping) that produce H₂S and methyl mercaptan.
- Recurrent streptococcal pharyngitis — Di Pierro 2014 enrolled 61 children with recurrent streptococcal throat infections: 31 took K12 daily for 90 days and the other 30 served as an untreated control group (the study is not described as randomized or placebo-controlled). Compared with their own infection rates in the previous year, the children who completed K12 treatment had more than a 90% reduction in streptococcal throat infections and an 80% reduction in oral viral infections; the control group showed no difference.
- Otitis media (middle ear infections) — Di Pierro 2015 in International Journal of General Medicine, a pilot, uncontrolled study of 22 children with secretory otitis media treated daily with K12 for 90 days, reported a substantial reduction of acute otitis media episodes; the authors describe it as a starting point for a placebo-controlled study. The proposed mechanism is K12 colonization of the nasopharynx and Eustachian tube outlet, where it competitively excludes the bacterial pathogens responsible for otitis media.
- Adjunct in dental caries — smaller body of evidence supports K12 colonization producing modest reductions in Streptococcus mutans abundance, though M18 is the better-studied salivarius strain for this indication.
The Wescombe 2012 review in Future Microbiology is a comprehensive summary of K12's mechanism and clinical applications, written by members of the University of Otago group.
The key practical point: K12 actually colonizes the throat and oral cavity, persisting for weeks to months after a course of supplementation, rather than producing only a transient effect during the supplementation period. Most users following the commonly described regimen (1 lozenge per night for 30-90 days) achieve persistent colonization that continues to produce benefits long after stopping supplementation.
S. salivarius M18 for Caries and Plaque
The M18 strain was isolated by the same Tagg group at Otago through systematic screening of S. salivarius isolates for those producing salivaricins active specifically against Streptococcus mutans, the principal cariogenic organism. M18 produces salivaricins A, B, M, 9, and MPS, plus the enzyme dextranase, which breaks down the extracellular polysaccharide matrix produced by S. mutans as it forms cariogenic plaque biofilm.
The principal randomized trial is Burton 2013 in Journal of Medical Microbiology. Researchers randomized 100 schoolchildren aged 5-10 to M18 lozenges twice daily for 3 months vs placebo. At treatment end:
- Plaque scores were significantly lower (P = 0.05) in the M18 group, especially in children with high initial plaque scores
- No significant benefit for gingival health was reported
- Salivary counts of S. mutans and the other measured organisms did not differ between the M18 and placebo groups, except in the subgroup most effectively colonized by M18, which had reduced S. mutans counts
- Persistence of M18 colonization in most subjects 3 months after supplementation ended
A subsequent Italian randomized trial (Di Pierro 2015) of 76 children at high risk of dental caries, treated or not treated with M18 for 90 days, reported that M18 increased the chances of avoiding new caries, measured with the Cariogram risk-assessment score.
Several commercial products include both M18 and K12 in the same lozenge. In the studies on this page, M18 was tested for caries and plaque, and K12 for halitosis, throat infections and ear infections.
L. reuteri for Gingivitis and Periodontitis
The oral Lactobacillus reuteri product studied in these trials is a commercial combination of two characterized strains: L. reuteri DSM 17938 and L. reuteri ATCC PTA 5289. These two strains were selected from a screening program by a Swedish probiotic company for their adhesion to oral epithelial cells, suppression of periodontal pathogens, and production of reuterin, a broad-spectrum antimicrobial compound that L. reuteri produces from glycerol metabolism.
Unlike most Lactobacillus species, this L. reuteri combination does adhere to oral surfaces and can colonize transiently, though it does not appear to achieve the long-term colonization that K12 and M18 do. Effects depend on continued daily supplementation.
The pivotal randomized trial is Krasse 2006 in Swedish Dental Journal: 59 patients with moderate to severe gingivitis were randomized to one of two L. reuteri formulations (LR-1 or LR-2, 2 × 10⁸ CFU per day) or placebo for 2 weeks. Gingival index fell in all three groups; LR-1, but not LR-2, improved more than placebo. Plaque index fell within both L. reuteri groups but not in the placebo group.
The subsequent Vivekananda 2010 trial extended the evidence to periodontitis specifically: 30 chronic periodontitis patients were randomized to L. reuteri lozenges vs placebo, with and without scaling and root planing. The L. reuteri arm showed greater reductions in probing pocket depth, clinical attachment level, and bleeding on probing — both as monotherapy and as adjunct to scaling.
The Tekce 2015 trial (40 patients) found L. reuteri lozenges a useful adjunct to scaling and root planing for chronic periodontitis: plaque, gingival, bleeding and probing-depth scores were lower than on placebo at every time point up to 1 year.
The combination is sold as lozenges. Regimens described for them are 1 lozenge twice daily, dissolved slowly in the mouth, for 4-12 weeks, often alongside periodontal scaling and root planing. Cost: $25-35 per month.
In the periodontitis trials it was an addition to periodontal scaling, not a replacement for it; it does not replace periodontal surgery where indicated, or treatment of contributing factors (smoking cessation, diabetes management).
Alpha-Streptococcal Nasal Spray and Otitis Media
A fourth approach studied for otitis media is a nasal spray of "interfering" alpha streptococci — bacteria able to inhibit the growth of common ear pathogens. In the Roos 2001 randomized, placebo-controlled trial in BMJ (130 otitis-prone children aged 6 months to 6 years, 108 of them followed for 3 months), the spray was given for 10 days after a course of antibiotics and again for 10 days from day 60. At 3 months, 42% of the children given the streptococcal spray were healthy with a normal eardrum, compared with 22% of those given placebo.
Some commercial otitis-prevention products combine several oral strains into single lozenges or sprays, with the rationale that the strains cover overlapping but somewhat different microbial niches in the upper respiratory tract / nasopharynx / oral cavity.
Of the otitis media studies on this page, the Roos 2001 nasal-spray trial is the randomized, placebo-controlled one; the K12 otitis study (Di Pierro 2015) was a small, uncontrolled pilot.
Why Lozenge Format Matters
The format in which an oral probiotic is delivered matters more than for gut probiotics. The key requirements:
- Slow dissolution in the mouth — the bacteria need extended contact time with oral surfaces to adhere and colonize. A swallowed capsule delivers the organisms directly to the stomach (where gastric acid kills most of them) and bypasses the oral cavity entirely — defeating the purpose. A lozenge that dissolves slowly over 5-10 minutes provides extended exposure of oral surfaces to high concentrations of viable organisms.
- No subsequent eating or drinking — immediately after lozenge dissolution, eating or drinking will mechanically wash unattached organisms away. The usual instruction is for the lozenge to be the last thing in the mouth, with no food, drink, brushing, mouthwash, or oil pulling for at least 30 minutes afterward — ideally last thing before sleep, so the entire overnight period is available for colonization.
- Adequate dose — the standard K12 dose is 1 billion CFU per lozenge; M18 also 1 billion CFU; L. reuteri (DSM 17938 + ATCC PTA 5289) ~200 million CFU per lozenge. Sub-dose products are common in the consumer market; the CFU count is stated on the label.
- Viable organisms — probiotic lozenges have a finite shelf life and viability declines especially in heat. Refrigerated storage extends shelf life. Some labels guarantee the CFU count at expiration rather than only at manufacture.
- Sugar-free or xylitol-sweetened — lozenges sweetened with sucrose or fructose feed cariogenic bacteria, partially counteracting the probiotic benefit. Xylitol-sweetened lozenges are often chosen because xylitol itself has anti-cariogenic activity (it inhibits S. mutans growth and metabolism).
The pattern described for these products: teeth brushed as usual before bed, then one oral probiotic lozenge dissolved in the mouth as the last thing before sleep, with no eating, drinking, rinsing, or brushing afterward. The idea is that colonization happens overnight while the mouth is relatively dormant.
Regimens Studied and Described, by Indication
- Chronic halitosis (after ruling out underlying cause) — the Burton 2006 study gave K12 lozenges after a 3-day chlorhexidine rinse and measured volatile sulfur compounds at 1 week. Practitioners describe combining tongue scraping and oil pulling (morning) with a K12 lozenge (evening, last thing before sleep) for 4-6 weeks, then K12 every 1-2 days as maintenance if breath has improved.
- Recurrent strep throat (3+ episodes per year) — the Di Pierro 2014 study gave K12 daily for 90 days. Intermittent use during cold and flu season is also described.
- Recurrent otitis media in otitis-prone children — the Di Pierro 2015 pilot gave K12 daily for 90 days; the Roos 2001 trial used an alpha-streptococcal nasal spray in two 10-day courses. Decisions for children belong with the pediatrician.
- Gingivitis, plaque accumulation, mild periodontitis — the Burton 2013 trial gave M18 for 3 months, and the Krasse 2006 gingivitis trial gave L. reuteri for 2 weeks. Practitioners describe M18 lozenges twice daily for 90 days alongside brushing, flossing, tongue scraping and oil pulling, with a re-evaluation at the next dental cleaning.
- Moderate to severe periodontitis (with active scaling and root planing) — the L. reuteri lozenge trials (Vivekananda 2010, Tekce 2015) gave the lozenges alongside scaling and root planing. Regimens described in practice run twice daily for 12 weeks from the time of scaling, then once daily for 6-12 months, coordinated with the periodontist.
- General oral microbiome optimization — no study on this page tested this use; the regimen practitioners describe is a combined K12 + M18 lozenge nightly for 30-60 days, then 2-3 times per week as maintenance.
None of these regimens replaces standard dental care. The oral probiotics were studied, and are described, as additions to brushing, flossing, regular cleanings, and treatment of any active dental disease — not as substitutes for any of those.
Cautions and Limitations
- Immunocompromised patients — oral probiotics are live organisms. In severely immunocompromised patients (advanced human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), active hematologic malignancy on intensive chemotherapy, post-transplant on heavy immunosuppression), bacteremia from live probiotics has been reported as a rare complication. Decisions about probiotic use in these populations belong with the treating physician.
- Central venous catheter — patients with central lines have a higher risk of probiotic-associated bacteremia from live probiotic supplementation.
- Endocarditis prophylaxis — patients with prosthetic heart valves, history of infective endocarditis, or certain congenital cardiac conditions are at increased risk of bacteremia-related endocarditis. Although oral commensal streptococcal bacteremia is what already happens during routine tooth brushing, the introduction of high-dose probiotic strains is a question for the cardiologist.
- Concurrent antibiotics — oral antibiotics (especially broad-spectrum) will kill the probiotic strains. Probiotic doses are commonly spaced at least 2 hours from antibiotic doses, and colonization generally has to be re-established after the antibiotic course is complete.
- Concurrent chlorhexidine mouthwash — chlorhexidine will kill probiotic strains used at the same time. In the Burton 2006 halitosis study, a 3-day chlorhexidine mouthwash course came before the K12 lozenges rather than alongside them. Practitioners describe restarting probiotics about 1 week after a course of chlorhexidine ends.
- Concurrent oil pulling — regimens that include both separate them in time: oil pulling in the morning, probiotic lozenge in the evening.
- Diabetes (poorly controlled) — the oral microbiome is significantly altered by hyperglycemia. Probiotic colonization may be less stable in poorly controlled diabetes, and glycemic control underlies sustainable oral microbiome health.
- Smoking — tobacco smoke is severely toxic to the oral microbiome (commensals and probiotics alike) and is a major contributor to periodontitis progression.
- Cost — quality oral probiotics cost $20-35 per month. This is not trivial for many patients. Tongue scraping (a one-time scraper purchase, no recurring cost) and oil pulling (a modest recurring cost for coconut oil) cost less than ongoing probiotic supplementation.
- Marketing claims — the oral probiotic market includes some products with weak or no evidence base. The strains with published oral trials are K12, M18, and the two L. reuteri strains (DSM 17938 and ATCC PTA 5289), at the doses those trials used. "10-strain oral probiotic" blends often include strains with no oral evidence base.
Key Research Papers
- Burton JP, Chilcott CN, Moore CJ, Speiser G, Tagg JR (2006). A preliminary study of the effect of probiotic Streptococcus salivarius K12 on oral malodour parameters. Journal of Applied Microbiology, 100(4):754-64. — PubMed
- Di Pierro F, Colombo M, Zanvit A, Risso P, Rottoli AS (2014). Use of Streptococcus salivarius K12 in the prevention of streptococcal and viral pharyngotonsillitis in children. Drug, Healthcare and Patient Safety, 6:15-20. — PubMed PMID: 24600248
- Di Pierro F, Di Pasquale D, Di Cicco M (2015). Oral use of Streptococcus salivarius K12 in children with secretory otitis media: preliminary results of a pilot, uncontrolled study. International Journal of General Medicine, 8:303-8. — PubMed PMID: 26396541
- Burton JP, Drummond BK, Chilcott CN et al. (2013). Influence of the probiotic Streptococcus salivarius strain M18 on indices of dental health in children. Journal of Medical Microbiology, 62(Pt 6):875-884. — PubMed PMID: 23449874
- Wescombe PA, Hale JD, Heng NC, Tagg JR (2012). Developing oral probiotics from Streptococcus salivarius. Future Microbiology, 7(12):1355-71. — PubMed PMID: 23231486
- Krasse P, Carlsson B, Dahl C, Paulsson A, Nilsson A, Sinkiewicz G (2006). Decreased gum bleeding and reduced gingivitis by the probiotic Lactobacillus reuteri. Swedish Dental Journal, 30(2):55-60. — PubMed
- Vivekananda MR, Vandana KL, Bhat KG (2010). Effect of the probiotic Lactobacilli reuteri (Prodentis) in the management of periodontal disease: a preliminary randomized clinical trial. Journal of Oral Microbiology, 2:5344. — PubMed
- Tekce M, Ince G, Gursoy H et al. (2015). Clinical and microbiological effects of probiotic lozenges in the treatment of chronic periodontitis: a 1-year follow-up study. Journal of Clinical Periodontology, 42(4):363-72. — PubMed PMID: 25728888
- Power DA, Burton JP, Chilcott CN, Dawes PJ, Tagg JR (2008). Preliminary investigations of the colonisation of upper respiratory tract tissues of infants using a paediatric formulation of the oral probiotic Streptococcus salivarius K12. European Journal of Clinical Microbiology & Infectious Diseases, 27(12):1261-3. — PubMed
- Stensson M, Koch G, Coric S et al. (2014). Oral administration of Lactobacillus reuteri during the first year of life reduces caries prevalence in the primary dentition at 9 years of age. Caries Research, 48(2):111-7. — PubMed PMID: 24296746
- Náse L, Hatakka K, Savilahti E et al. (2001). Effect of long-term consumption of a probiotic bacterium, Lactobacillus rhamnosus GG, in milk on dental caries and caries risk in children. Caries Research, 35(6):412-20. — PubMed PMID: 11799281
- Roos K, Hakansson EG, Holm S (2001). Effect of recolonisation with "interfering" alpha streptococci on recurrences of acute and secretory otitis media in children: randomised placebo controlled trial. BMJ, 322(7280):210-2. — PubMed PMID: 11159619
- Hillman JD (2002). Genetically modified Streptococcus mutans for the prevention of dental caries. Antonie van Leeuwenhoek, 82(1-4):361-6. — PubMed PMID: 12369203