Tongue Scraping — Halitosis, Taste, and the Oral Microbiome
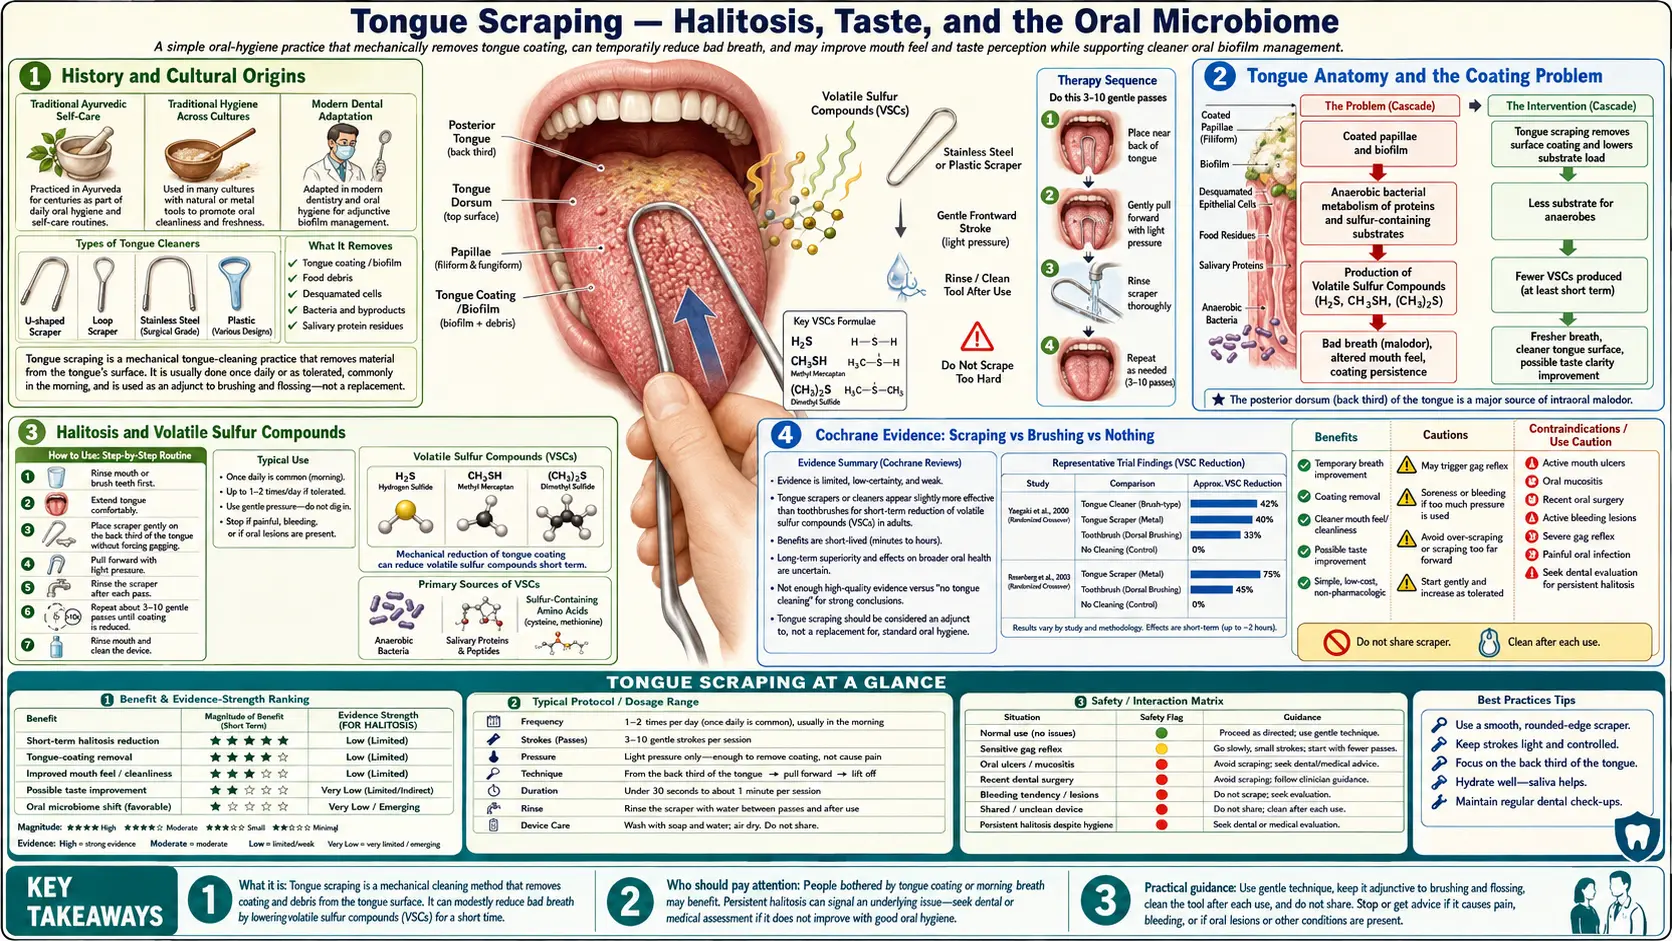
The posterior dorsum of the tongue is the largest reservoir of bacteria in the mouth — the rough surface of filiform papillae creates a vast surface area with microscopic crypts that trap food debris, dead epithelial cells, and bacterial biofilm. Approximately 60% of the bacterial load contributing to bad breath originates not from teeth or gums, but from this tongue coating. The volatile sulfur compounds (VSCs) responsible for the smell — hydrogen sulfide, methyl mercaptan, and dimethyl sulfide — are produced by gram-negative anaerobic bacteria metabolizing sulfur-containing amino acids (cysteine, methionine) from this trapped protein debris. A 2-thousand-year-old Ayurvedic intervention — the U-shaped copper or steel tongue scraper — mechanically removes this coating in 30 seconds of morning use. In one 10-person crossover trial (Pedrazzi 2004) a scraper cut VSC levels by 75%, against 45% for a soft toothbrush; in a 30-person trial (Seemann 2001) the drops were 40% for a scraper and 33% for a toothbrush, and none lasted more than 30 minutes. This page covers the mechanism, the Cochrane evidence, copper vs steel scraper choice, and the swallowed-bacteria pathway to the gut.
Table of Contents
- History and Cultural Origins
- Tongue Anatomy and the Coating Problem
- Halitosis and Volatile Sulfur Compounds
- Cochrane Evidence: Scraping vs Brushing vs Nothing
- Taste Perception and Tongue Coating
- The Swallowed-Bacteria Pathway to the Gut
- Choosing a Tongue Scraper: Copper, Stainless Steel, Plastic
- How Tongue Scraping Is Done
- Key Research Papers
- Connections
- Featured Videos
History and Cultural Origins
Tongue scraping is one of the oldest documented hygienic practices in human medicine. The Charaka Samhita (compiled approximately 200 BCE - 200 CE) prescribes it as a daily morning dinacharya (daily routine) practice, alongside oil pulling and oil massage. The Ayurvedic recommendation was for a copper scraper (jihwa prakshalana), based on the belief that copper's mild antimicrobial activity added to the mechanical effect.
The practice is documented independently across multiple cultures:
- India (Ayurveda) — copper or gold scrapers, daily morning use, embedded in the dinacharya routine.
- Africa — chewed-stick variants (Miswak from Salvadora persica) with tongue-scraping fibers, used across much of the Islamic world and East Africa.
- Pre-modern Europe — aristocratic European hygiene from the 15th-19th centuries included ivory, tortoiseshell, and silver tongue scrapers as standard items in personal grooming kits. Surviving examples from this period are common in museums.
- South America — indigenous Amazonian practices using carved wooden scrapers.
The practice essentially disappeared from mainstream Western dental hygiene during the 20th century, overtaken by the focus on toothbrush + toothpaste + dental floss. It re-entered Western awareness through two pathways in the early 2000s: the Ayurvedic revival in the natural-products movement, and the work of academic dental researchers (Quirynen, Pedrazzi, Outhouse) systematically comparing tongue scraping to tongue brushing in randomized trials.
Tongue Anatomy and the Coating Problem
The tongue surface is not smooth. It is covered in four types of specialized epithelial structures called papillae:
- Filiform papillae — the most numerous, distributed across the entire dorsum. These are slender, conical projections that do NOT contain taste buds. Their function is mechanical (grip and friction during chewing and speech) and tactile. They create a surface texture similar to fine velvet or a soft hairbrush — lots of crevices and microscopic surface area.
- Fungiform papillae — mushroom-shaped, scattered between the filiform papillae across the front two-thirds of the tongue. These DO contain taste buds (mostly sweet, salty, and umami detection).
- Foliate papillae — on the posterior lateral edges, containing taste buds (predominantly sour).
- Circumvallate papillae — the large, prominent papillae forming a V-shape near the back of the tongue, surrounded by deep moats containing taste buds (predominantly bitter).
The filiform papillae are the structural problem. Their microscopic crevices trap and accumulate three things:
- Sloughed-off dead epithelial cells from the tongue surface itself (constant turnover)
- Food debris that doesn't get washed away by saliva (especially protein-rich material from meat, dairy, eggs)
- Bacterial biofilm — predominantly anaerobic gram-negative species that thrive in the oxygen-poor microenvironment created by the dense biofilm structure
This combined material is what is called the "tongue coating" — visible to the eye as a white, yellow, brown, or sometimes black layer on the dorsum, especially the posterior third (the part closer to the throat that is harder to reach and harder to clean). The coating thickness correlates with halitosis severity, bacterial load, and the concentration of volatile sulfur compounds in exhaled breath.
The coating is also self-perpetuating. The bacterial biofilm produces an extracellular matrix of polysaccharides and proteins that holds the bacteria together and protects them from saliva, oxygen, and antimicrobials. Once established, the biofilm is resistant to removal by saliva alone or by gentle brushing.
Halitosis and Volatile Sulfur Compounds
The smell of bad breath is overwhelmingly produced by three small molecules collectively called volatile sulfur compounds (VSCs):
- Hydrogen sulfide (H₂S) — the rotten-egg smell, the dominant VSC in most cases of halitosis.
- Methyl mercaptan (CH₃SH) — rotting cabbage / sulfurous, particularly noxious; the principal VSC in patients with periodontal disease.
- Dimethyl sulfide ((CH₃)₂S) — cabbage-like odor; quantitatively smaller contribution but with very low olfactory threshold.
VSCs are produced by anaerobic gram-negative bacteria (predominantly Solobacterium moorei, Atopobium parvulum, Fusobacterium nucleatum, Prevotella species, Tannerella forsythia, Porphyromonas gingivalis) metabolizing sulfur-containing amino acids derived from protein debris. The metabolic pathway:
- Bacterial proteases break down protein debris into individual amino acids
- Sulfur-containing amino acids (cysteine, methionine) are taken up by VSC-producing bacteria
- Bacterial cysteine desulfhydrase and methionine gamma-lyase enzymes liberate the sulfur atoms as H₂S and CH₃SH respectively
- These small gases diffuse out of the biofilm into the air space, contributing to exhaled odor
Approximately 60-90% of bad-breath cases originate in the mouth (not from the lungs, sinuses, stomach, or systemic disease). Of the oral fraction, the tongue coating contributes more than the teeth and gums combined. A 2000 review by Yaegaki and Coil lists tongue cleaning, oral hygiene instruction and mouth rinsing among the simple treatment measures dental clinicians use for bad breath that starts in the mouth.
The Outhouse Cochrane review (2006) on tongue scraping for halitosis called the evidence “weak and unreliable”: it found a small but statistically significant difference in VSC reduction when tongue scrapers or cleaners rather than toothbrushes were used, and its two trials gave no data on its main outcomes. Cochrane withdrew this review in 2016 and replaced it with a broader 2019 review (see below). The Pedrazzi 2004 trial (Journal of Periodontology) directly compared toothbrush and tongue scraper for tongue cleaning in 10 healthy adults, finding the scraper produced 75% reduction in VSCs vs the toothbrush's 45% reduction. In the 30-person Seemann 2001 trial, reductions were 42% with a combined brush-scraper “tongue cleaner”, 40% with a scraper and 33% with a toothbrush, and the drop in sulfur gases could not be detected for more than 30 minutes after cleaning in any group.
Cochrane Evidence: Scraping vs Brushing vs Nothing
The Cochrane Collaboration's Outhouse 2006 systematic review on tongue scraping for halitosis was for ten years the main evidence-grading effort on this question. Cochrane withdrew it in 2016 and replaced it with a broader review of all halitosis treatments (Kumbargere Nagraj 2019). Key findings of the 2006 review:
- Two randomized controlled trials (RCTs) with 40 participants met inclusion criteria (the Pedrazzi 2004 and Seemann 2001 trials).
- Neither trial gave data on the review's main outcomes; both measured sulfur gases (VSCs) with a portable monitor.
- Both trials compared tongue-cleaning devices with a toothbrush, not with no cleaning. In Seemann 2001 (30 people) VSCs fell 42% with a combined brush-scraper “tongue cleaner”, 40% with a tongue scraper and 33% with a toothbrush; in Pedrazzi 2004 (10 people) they fell 75% with a scraper and 45% with a soft toothbrush.
- In Seemann 2001 the drop in sulfur gases could not be detected for more than 30 minutes after cleaning in any group.
- In one of the two trials, the toothbrush caused nausea in 60% and minor injury in 10% of participants; all participants were receptive to the scraper.
- The authors concluded there is “weak and unreliable evidence” of a small but statistically significant difference in favour of tongue scrapers or cleaners over toothbrushes.
The 2019 Cochrane review that replaced it (44 trials, 1,809 people, all halitosis treatments) found, for mechanical tongue cleaning versus no tongue cleaning, a small drop in dentist-rated breath odour (mean difference −0.20, 95% CI −0.34 to −0.07; 2 trials, 46 people), rated “very low-certainty evidence”. The authors were unable to draw any conclusions about whether any treatment was better than another.
A 2024 randomized trial in 52 young adults aged 18–25 with bad breath (13 per group) found that tongue scraping lowered mouth sulfur gases immediately after use, but no significant differences were found at the follow-up visits (7, 14 and 30 days), and the numbers of the three gum-disease bacteria tested (Porphyromonas gingivalis, Tannerella forsythia, Treponema denticola) did not fall.
The usual explanation for why scrapers did better than toothbrushes in these trials: a tongue brush's soft bristles compress against the tongue surface but do not effectively pull material out of the inter-papillary crevices. A scraper's rigid edge, drawn across the surface with downward pressure, mechanically excavates the coating from between the filiform papillae and removes it bodily. The visible material accumulated on the scraper edge after each pull (white-yellow paste, often with substantial volume) is offered by practitioners as visible evidence of the difference — users can see what was extracted.
Additional evidence:
- Quirynen 2004 — in 16 people without gum disease, two weeks of twice-daily tongue scraping or tongue brushing reduced tongue coating significantly but gave only negligible reductions in tongue bacteria (less than 0.5 log); taste improved, significantly for bitter and salty.
- Van der Sleen 2010 systematic review — five studies (three RCTs, two controlled trials): mechanical tongue cleaning (scraper or tongue brush) added to toothbrushing has the potential to reduce breath odor and tongue coating, but data on its effect on chronic bad breath (halitosis) are insufficient.
- Faveri 2006 — cross-over in 19 periodontally healthy volunteers, each routine used for 7 days: tongue scraping added to toothbrushing gave the lowest morning breath odor; flossing did not improve odor scores further but did lower sulfur-gas concentration. The authors judged tongue scraping the most important hygiene step for morning breath.
Taste Perception and Tongue Coating
A frequently overlooked benefit of regular tongue scraping is improved taste sensitivity. The mechanism is straightforward: the taste buds in the fungiform, foliate, and circumvallate papillae need direct contact with dissolved food chemicals to function. A thick coating of biofilm and debris physically shields the taste buds from this contact, dulling taste.
The Quirynen 2004 trial measured taste for bitter, sweet, salty and sour in 16 people before and after 2 weeks of twice-daily tongue cleaning. Tongue coating fell significantly and taste improved, especially with the scraper, with significant improvements for bitter (quinine) and salty (sodium chloride) only. Tongue bacteria barely changed; the authors concluded that tongue cleaning seems to remove the material odor bacteria feed on (“the substrata for putrefaction”) rather than the bacteria themselves. People often report that food becomes "more flavorful" after a few weeks of consistent tongue scraping — this is the unmasking of taste buds that had been functionally blunted by coating.
This has practical relevance for:
- Patients with reduced appetite (especially elderly patients) where dulled taste contributes to under-eating
- Patients trying to reduce sugar or salt intake (more sensitive taste means lower thresholds needed)
- Patients trying to enjoy whole-food cooking after years of processed-food diet (rediscovering subtle flavors)
- Patients post-chemotherapy with treatment-related taste alteration (mechanism is different but tongue hygiene supports any return of function)
The taste-perception benefit is one of the more immediately rewarding effects of starting a tongue-scraping practice — users commonly describe noticing within 1-2 weeks that morning coffee, fruit, and salads taste fuller and more interesting.
The Swallowed-Bacteria Pathway to the Gut
An adult swallows approximately 1.5 liters of saliva per day. That saliva carries with it a continuous bacterial load harvested from the oral cavity — primarily from the tongue coating (largest reservoir) and the gingival sulcus. Most of these swallowed bacteria are killed by gastric acid in the stomach. However, in two scenarios, swallowed oral bacteria reach the gut alive in significant numbers:
- Hypochlorhydria (low stomach acid) — older adults, patients on long-term proton pump inhibitors (omeprazole, esomeprazole, etc.), patients with atrophic gastritis, and patients with H. pylori infection have reduced gastric acid output. Without adequate acid, swallowed oral bacteria survive transit to the small intestine, where they can colonize ectopically (contributing to small intestinal bacterial overgrowth (SIBO)) and downstream colon dysbiosis.
- Bolus protection — bacteria embedded within food boluses are partially protected from gastric acid by the surrounding food matrix. Subsequent gastric emptying delivers viable bacteria to the duodenum.
The 2019 Olsen and Yamazaki review (Journal of Oral Microbiology) summarizes the evidence that oral bacteria translocate to and influence the gut microbiome. Patients with periodontitis have measurably increased abundance of oral-origin taxa (including Fusobacterium nucleatum, the same organism strongly linked to colorectal cancer) in their stool. The same connection has been demonstrated for inflammatory bowel disease, liver cirrhosis, and rheumatoid arthritis — conditions where downstream microbiome consequences of oral dysbiosis appear to play a measurable role.
Practitioners describe tongue scraping as a way to reduce the bacteria swallowed with saliva each day. This idea has not been tested: in the Quirynen 2004 trial, two weeks of tongue scraping gave only negligible reductions in tongue bacteria (less than 0.5 log), and the Olsen and Yamazaki review describes the oral-gut research field as “in its infancy”.
For people with diagnosed small intestinal bacterial overgrowth, inflammatory bowel disease (IBD), or chronic gut inflammation, practitioners describe tongue scraping as an add-on to gut-directed treatment. It is not reported to reverse those conditions by itself; the idea is that it removes one ongoing input. For more on the gut connection, see small intestinal bacterial overgrowth and Inflammatory Bowel Disease.
Choosing a Tongue Scraper: Copper, Stainless Steel, Plastic
Three materials dominate the tongue-scraper market. Each has tradeoffs:
- Copper (traditional Ayurvedic choice) — The original material specified in Ayurvedic texts. Copper has mild antimicrobial activity (the Cu ion releases at low rate from the metal surface), which adds an antimicrobial effect on top of the mechanical cleaning. Copper develops a darker patina over time which is cosmetic, not harmful. Slightly heavier and stiffer than stainless steel; the U-shape holds its form well. Cost: $8-15. Sold by many Ayurvedic sellers and natural food stores.
- Stainless steel — the most common modern material. Inert (no copper-style ion release, no patina), easy to clean, dishwasher-safe, lasts indefinitely. The most hygienic choice from a "what is on the scraper between uses" perspective. Slightly less rigid than copper, sometimes flexes during use. Cost: $5-10.
- Plastic — cheapest, lightest, slightly flexible. Modern plastic scrapers are widely sold under many consumer brands. Limitations: plastic eventually shows wear at the scraping edge and is usually replaced every 6-12 months. Some plastic scrapers add bristles; in the Seemann 2001 trial a combined brush-and-scraper tongue cleaner lowered sulfur gases slightly more (42%) than a plain scraper (40%) or a toothbrush (33%). Cost: $3-5.
The differences in clinical outcome between copper, stainless steel, and plastic scrapers are small in published trials — practitioners describe consistent use as the dominant factor. The handful of head-to-head trials comparing materials (mostly small studies) have not shown a definitively superior material.
What practitioners describe: stainless steel is the most common choice (hygienic, inexpensive, long-lasting); copper is the traditional choice and needs cleaning and drying after each use to keep its surface. In the one trial that tested a combined brush-and-scraper (Seemann 2001), it lowered sulfur gases slightly more than a plain scraper, though no drop lasted more than 30 minutes.
Points raised in the trials and by users:
- A toothbrush used on the tongue lowered sulfur gases less than a scraper in the Pedrazzi data (45% vs 75%); in one trial in the 2006 Cochrane review, the toothbrush caused nausea in 60% of participants
- Scrapers with attached bristles — in Seemann 2001 a combined brush-scraper did slightly better than a plain scraper (42% vs 40%)
- Very wide scrapers (more than 1.5 inches across) — described as harder to get to the back of the tongue
- Strongly curved scrapers — described as fitting the tongue's natural curve less well
How Tongue Scraping Is Done
The technique, as practitioners describe it, is simple:
- When — first thing in the morning, before eating, drinking, brushing, or oil pulling, when the overnight build-up is greatest.
- Position — standing at the bathroom sink, mouth open wide, tongue stretched forward as far as comfortable.
- Grip — the scraper is held with both hands, one on each end of the U, which gives even pressure across the scraping edge.
- Placement — the scraper goes as far back on the tongue as possible without triggering the gag reflex. The back third of the tongue is where the coating is heaviest.
- The stroke — the scraper is pressed onto the tongue with moderate pressure and pulled forward in one continuous motion from back to front. The coating collects on the scraping edge.
- Rinsing the scraper — the collected material is rinsed off under the tap after each stroke.
- Repeats — 5-10 strokes in total, covering the whole tongue surface (center, then each side).
- Rinsing the mouth — once with warm water at the end.
- The rest of the morning routine — many people follow with oil pulling, tooth brushing and flossing.
The whole tongue scraping process takes 30-60 seconds once the technique is learned. Practitioners describe it as one of the quickest oral hygiene steps aimed at bad breath.
Two common technique mistakes users describe:
- Not reaching far enough back — scraping only the front and middle of the tongue misses the back third, the most heavily coated zone. People describe the gag reflex easing over the first week of practice.
- Excessive pressure — the aim is removing the surface coating, not scraping the tongue surface itself. A sore or bleeding tongue is a sign of too much pressure; users describe firm but moderate pressure, letting the scraper's edge do the work.
Between uses, the scraper is usually rinsed, shaken dry and stored in a clean place (a closed wet container lets bacteria grow). Stainless steel scrapers can go in the dishwasher; copper scrapers are hand-washed and dried to keep the surface.
Key Research Papers
- Outhouse TL, Al-Alawi R, Fedorowicz Z, Keenan JV (2006). Tongue scraping for treating halitosis. Cochrane Database of Systematic Reviews, (2):CD005519. — PubMed PMID: 16625641
- Outhouse TL, Al-Alawi R, Fedorowicz Z, Keenan JV (2016). WITHDRAWN: Tongue scraping for treating halitosis. Cochrane Database of Systematic Reviews, 2016(5):CD005519. — PubMed PMID: 27227886
- Kumbargere Nagraj S, Eachempati P, Uma E, Singh VP, Ismail NM, Varghese E (2019). Interventions for managing halitosis. Cochrane Database of Systematic Reviews, 12(12):CD012213. — PubMed PMID: 31825092
- Seemann R, Kison A, Bizhang M, Zimmer S (2001). Effectiveness of mechanical tongue cleaning on oral levels of volatile sulfur compounds. Journal of the American Dental Association, 132(9):1263-7. — PubMed PMID: 11665351
- Pedrazzi V, Sato S, de Mattos Mda G, Lara EH, Panzeri H (2004). Tongue-cleaning methods: a comparative clinical trial employing a toothbrush and a tongue scraper. Journal of Periodontology, 75(7):1009-12. — PubMed PMID: 15341360
- Quirynen M, Avontroodt P, Soers C et al. (2004). Impact of tongue cleansers on microbial load and taste. Journal of Clinical Periodontology, 31(7):506-10. — PubMed PMID: 15191584
- Van der Sleen MI, Slot DE, Van Trijffel E et al. (2010). Effectiveness of mechanical tongue cleaning on breath odour and tongue coating: a systematic review. International Journal of Dental Hygiene, 8(4):258-68. — PubMed PMID: 20961381
- Yaegaki K, Coil JM (2000). Examination, classification, and treatment of halitosis; clinical perspectives. Journal of the Canadian Dental Association, 66(5):257-61. — PubMed PMID: 10833869
- Faveri M, Hayacibara MF, Pupio GC, Cury JA, Tsuzuki CO, Hayacibara RM (2006). A cross-over study on the effect of various therapeutic approaches to morning breath odour. Journal of Clinical Periodontology, 33(8):555-60. — PubMed PMID: 16899098
- Kapoor U, Sharma G, Juneja M, Nagpal A (2016). Halitosis: current concepts on etiology, diagnosis and management. European Journal of Dentistry, 10(2):292-300. — PubMed PMID: 27095913
- Tonzetich J (1977). Production and origin of oral malodor: a review of mechanisms and methods of analysis. Journal of Periodontology, 48(1):13-20. — PubMed PMID: 264535
- Roldan S, Herrera D, Sanz M (2003). Biofilms and the tongue: therapeutical approaches for the control of halitosis. Clinical Oral Investigations, 7(4):189-97. — PubMed PMID: 14513303
- Olsen I, Yamazaki K (2019). Can oral bacteria affect the microbiome of the gut? Journal of Oral Microbiology, 11(1):1586422. — PubMed PMID: 30911359
- Allaker RP, Waite RD, Hickling J et al. (2008). Topographic distribution of bacteria associated with oral malodour on the tongue. Archives of Oral Biology, 53 Suppl 1:S8-12. — PubMed PMID: 18460402
- Motta PB, Gonçalves MLL, Gallo JMAS, Sobral APT, Motta LJ, Mayer MPA, Kawamoto D, de Andrade DC, Santos EM, Fernandes KPS, Mesquita-Ferrari RA, Deana AM, Horliana ACRT, Kalil Bussadori S (2024). Short term effect of antimicrobial photodynamic therapy and probiotic L. salivarius WB21 on halitosis: a controlled and randomized clinical trial. PLoS One, 19(7):e0297351. — PubMed PMID: 38954692