N-acetyl-cysteine (NAC) & Cardiovascular Health
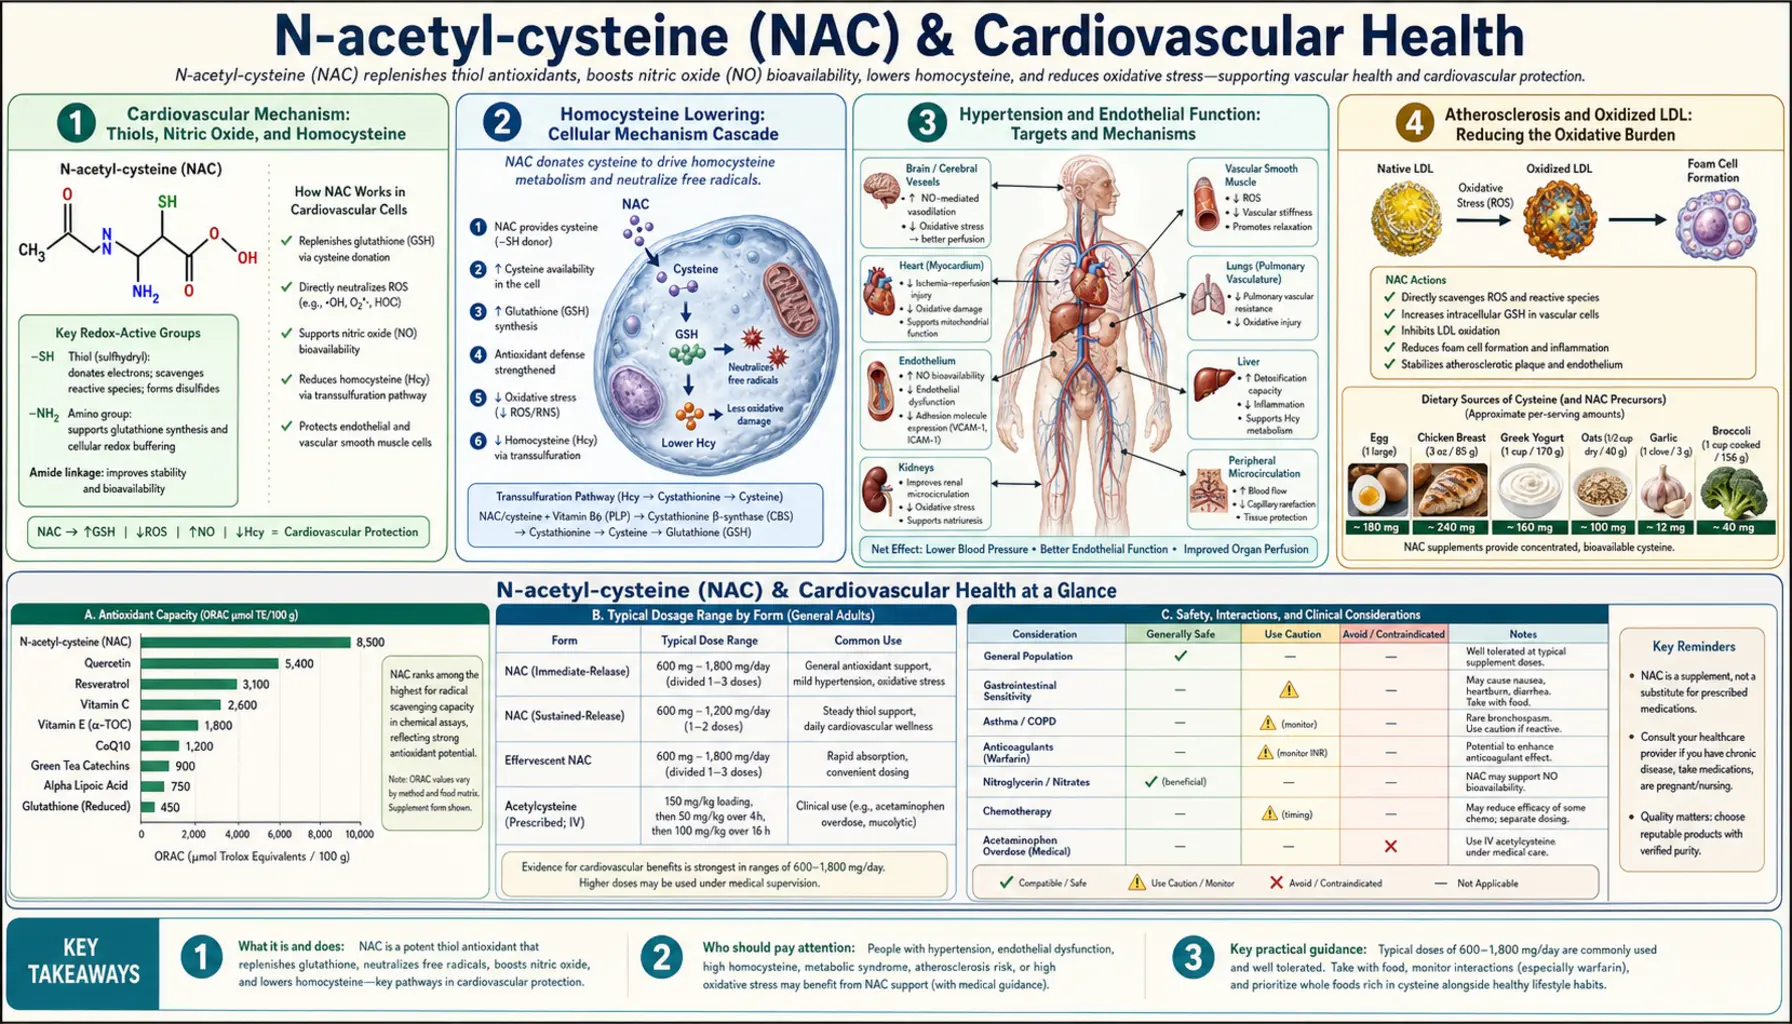
NAC has been studied in cardiovascular medicine in two main ways. The older work paired it with nitroglycerin: a continuous nitroglycerin infusion loses much of its effect over 48 hours (nitrate tolerance), and in heart failure oral NAC partially reversed this in eight patients (Packer 1987); in 46 patients with unstable angina, NAC plus nitroglycerin was followed by fewer heart attacks than nitroglycerin alone (3 versus 10) but more symptomatic hypotension (7 versus 0) (Horowitz 1988). The newer work is the NACIAM trial (Pasupathy 2017, Circulation), in which high-dose intravenous NAC given with low-dose nitroglycerin to STEMI patients undergoing primary PCI was associated with an absolute 5.5% reduction in MRI-measured infarct size (median 11.0% versus 16.5%) and approximately doubled myocardial salvage; its authors called for a larger trial of clinical outcomes. Smaller studies have measured homocysteine, endothelial function, blood pressure and lipids, with mixed results, and two large trials, ACT and PRESERVE, found no benefit of NAC for preventing kidney injury after angiography. The best-documented hazard in this area is symptomatic hypotension when NAC is combined with nitroglycerin.
Interactive Visualization Free Radicals & Your Antioxidant Network Follow one superoxide radical down the whole relay — SOD, catalase, glutathione, vitamin E, vitamin C, NADPH — then release free iron and watch a membrane tear itself apart. Launch →Table of Contents
- Cardiovascular Mechanism: Thiols, Nitric Oxide, and Homocysteine
- Homocysteine Lowering
- Hypertension and Endothelial Function
- Atherosclerosis and Oxidized LDL
- Acute Myocardial Infarction — the NACIAM Trial
- Heart Failure
- Nitrate Tolerance
- Type 2 Diabetes and Metabolic Syndrome
- Blood Lipids and Lipoprotein(a)
- Peripheral Artery Disease
- Doses Used in the Studies
- Safety and the Nitroglycerin Interaction
- Key Research Papers
- Connections
- Featured Videos
Cardiovascular Mechanism: Thiols, Nitric Oxide, and Homocysteine
Reactive oxygen species and inflammation are considered important in the development of atherosclerosis (Zhu 2022), and oxidized LDL, rather than native LDL, is regarded as the atherogenic form (Cui 2015). Nitric oxide is thought to lose its beneficial effects on blood vessels in the presence of oxygen radicals, which is the rationale researchers have given for testing antioxidants such as NAC in people with diabetes and high blood pressure (Martina 2008).
The mechanisms proposed for NAC in the cardiovascular studies are:
- Glutathione supply — NAC provides cysteine, a building block of glutathione; in one trial in type 2 diabetes, oral NAC raised glutathione inside platelets in people whose levels were low (Treweeke 2012).
- Interaction with nitroglycerin — nitroglycerin's vasodilator effect is believed to require free sulfhydryl groups, and NAC, a sulfhydryl donor, potentiates the vasodilator effects of nitroglycerin; the two may also form S-nitroso-NAC, which inhibits platelet aggregation (Horowitz 1988).
- Homocysteine displacement — NAC is proposed to break the disulfide bonds that hold homocysteine to plasma proteins and to form mixed disulfides that the kidney clears; after a single infusion, urinary homocysteine excretion rose about fivefold (Ventura 1999). This is a different route from B vitamins, which also lower homocysteine (Hildebrandt 2015).
- Endothelium-dependent vasodilation — infused directly into coronary and leg arteries, NAC enhanced the dilation produced by acetylcholine, a test of endothelial function (Andrews 2001).
Homocysteine Lowering
Elevated total plasma homocysteine is considered an independent cardiovascular risk factor, although lowering it with B vitamins has improved only certain clinical endpoints (Hildebrandt 2015). The NAC studies measured homocysteine levels; none measured heart attacks or strokes.
- Hildebrandt 2015 (Am J Clin Nutr): a reanalysis of two double-blind, placebo-controlled trials in unmedicated middle-aged men, one in 40 men with high blood lipids and one in 42 men without. Four weeks of oral NAC 1.8 g/day lowered total homocysteine, the primary endpoint, by 11.7% (placebo: 4.1%), regardless of lipid or smoking status.
- Wiklund 1996 (Atherosclerosis): a double-blind crossover study in 11 people with high lipoprotein(a). NAC lowered plasma homocysteine by 45% but had no significant effect on lipoprotein(a), the trial's other main outcome.
- Ventura 1999 (Pharmacol Res): a single intravenous infusion (50 mg/kg) in ten healthy older adults. Total plasma homocysteine fell by approximately 69% at its lowest point, five hours after the infusion began, and urinary homocysteine excretion rose about fivefold that day.
- Friedman 2003 (Am J Kidney Dis): a randomized placebo-controlled trial in 38 vitamin-replete hemodialysis patients given NAC 1.2 g twice daily for four weeks. NAC did not significantly reduce total homocysteine compared with placebo.
- Faghfouri 2020 (Eur J Pharmacol): a meta-analysis of 28 controlled trials found that NAC lowered homocysteine, malondialdehyde and IL-8, with no significant effect on CRP.
Hypertension and Endothelial Function
The blood pressure data come from small trials, two of which combined NAC with another active treatment.
- Barrios 2002 (Blood Press): a crossover study in 18 hypertensive smokers already taking an ACE inhibitor. Adding NAC 600 mg three times daily for 21 days lowered 24-hour blood pressure compared with the ACE inhibitor alone (systolic 146.1 versus 137 mmHg; diastolic 89.2 versus 83.5 mmHg); night-time blood pressure did not differ. The authors proposed a nitric-oxide-dependent mechanism.
- Martina 2008 (Diabetes Care): a double-blind trial in 24 men with type 2 diabetes and hypertension, randomized to NAC plus L-arginine or placebo for six months. The combination lowered systolic and diastolic blood pressure and reduced oxidized LDL, high-sensitivity CRP, and the adhesion molecules ICAM and VCAM. Because NAC was given with L-arginine, the effect of NAC alone cannot be separated.
- Hildebrandt 2015: four weeks of NAC 1.8 g/day lowered systolic blood pressure in men with and without high lipids; diastolic pressure fell significantly only in the high-lipid group.
- Andrews 2001 (J Am Coll Cardiol): in 16 patients undergoing cardiac catheterization, intracoronary NAC raised acetylcholine-induced coronary blood flow by 36 ± 11%, and the epicardial artery changed from slight constriction to dilation. NAC did not enhance the response to nitroglycerin in this study.
Atherosclerosis and Oxidized LDL
- Cui 2015 (Sci Rep): mainly a mouse study. NAC reduced the oxidation of injected human LDL and reduced plaque formation in LDL-receptor-knockout mice; the paper also reports lower serum oxidized LDL in patients with coronary artery disease and hyperlipidemia given NAC, with no effect on LDL level.
- Martina 2008: NAC plus L-arginine reduced oxidized LDL and was reported to improve intima-media thickness during endothelial post-ischemic vasodilation testing.
- Zhu 2022 (Atherosclerosis): in aging LDL-receptor-deficient mice, six months of NAC (but not three) slowed atherosclerosis progression without reversing lesions, and preserved anti-inflammatory M2 macrophages; NAC had no effect on lesions in mice fed a high-fat diet.
No trial measuring atherosclerosis progression in people taking NAC was among the papers checked for this page.
Acute Myocardial Infarction — the NACIAM Trial
NACIAM (Pasupathy 2017, Circulation)
A randomized, double-blind, placebo-controlled, multicenter trial in 112 STEMI patients undergoing primary PCI. Intravenous high-dose NAC (29 g over 2 days) plus background low-dose nitroglycerin (7.2 mg over 2 days) was compared with placebo plus the same nitroglycerin. Of the 112 patients, 75 had the early cardiac MRI used for the primary endpoint.
- Absolute 5.5% reduction in MRI-assessed infarct size (median 11.0% versus 16.5%, P=0.02)
- Myocardial salvage approximately doubled (60% versus 27%, P<0.01)
- Creatine kinase release did not differ significantly (P=0.08)
- The authors concluded that a larger study is required to assess the effect on clinical cardiac outcomes
Other Acute MI and Reperfusion Data
- Arstall 1995 (Circulation): the first study of NAC in evolving acute MI. Twenty patients received 15 g of NAC over 24 hours and seven received no NAC, all with intravenous nitroglycerin and streptokinase. No significant adverse events occurred; NAC was associated with less oxidative stress, a non-significant trend toward faster reperfusion, and better preservation of left ventricular function (cardiac index 3.4 versus 2.6 L/min/m²).
- Koramaz 2006 (Ann Thorac Surg): in 30 patients undergoing coronary bypass surgery, cold-blood cardioplegia enriched with NAC (50 mg/kg) was followed by lower cardiac troponin I and lower malondialdehyde after surgery than cardioplegia without NAC.
Cardiac Surgery and Postoperative Atrial Fibrillation
The meta-analyses of NAC around heart surgery disagree on atrial fibrillation:
- Gu 2012 (BMC Cardiovasc Disord): 8 trials, 578 patients; NAC reduced postoperative atrial fibrillation (OR 0.62) but not hospital stay. The authors rated the overall quality of the studies as poor.
- Liu 2014 (BMC Cardiovasc Disord): 10 studies, 1,026 patients; NAC reduced postoperative atrial fibrillation (OR 0.56) and all-cause mortality (OR 0.40), but not ICU or hospital stay.
- Hassan 2025 (Minerva Cardiol Angiol): 15 trials; postoperative atrial fibrillation in 16.38% with NAC versus 23.53% in controls (RR 0.69).
- Wang 2011 (J Cardiothorac Vasc Anesth): 15 trials, 1,407 patients; NAC did not significantly reduce new atrial fibrillation (OR 0.67, P=0.19), mortality, or kidney failure requiring dialysis, and the authors found no proven benefit or risk on clinically important outcomes.
- Pereira 2019 (PLoS One): 29 trials, 2,486 participants; reductions in mortality (RR 0.71), acute kidney injury and arrhythmia (RR 0.79) were not statistically significant.
Heart Failure
- Yazdi 2022 (Ir J Med Sci): 55 patients with stable NYHA class II–III systolic heart failure on optimal therapy, randomized to oral NAC 600 mg twice daily or placebo for 12 weeks. NAC improved left ventricular ejection fraction and Tei index more than placebo; the shift in NYHA class was not significant. The authors called the data preliminary.
- Giam 2016 (Physiol Rep, mouse study): in mice with cardiomyopathy, NAC 40 mg/kg/day for 8 weeks left perivascular and interstitial cardiac fibrosis 40% and 57% lower than saline.
- Camuglia 2013 (Heart Lung Circ): a pilot crossover trial in nine outpatients with both heart failure and kidney failure (cardiorenal syndrome), NAC 500 mg twice daily for 28 days. Forearm blood flow improved with NAC; BNP did not differ significantly.
Nitrate Tolerance
Continuous nitroglycerin infusion loses much of its effect over 48 hours, a phenomenon called nitrate tolerance. Depletion of sulfhydryl groups is one proposed cause, which led researchers to test the sulfhydryl donor NAC.
- Packer 1987 (NEJM): in 35 patients with severe chronic heart failure, the benefit of a continuous 48-hour nitroglycerin infusion was greatly diminished by 48 hours, while intermittent infusion kept its effect. In eight patients who developed tolerance, oral NAC (200 mg/kg) partially reversed it; NAC had little effect in patients not receiving nitroglycerin. The authors wrote that direct studies of vascular tissue were still needed to test the sulfhydryl-depletion hypothesis.
- Horowitz 1988 (Circulation): a double-blind trial in 46 patients with severe unstable angina unresponsive to conventional treatment. Intravenous nitroglycerin plus intravenous NAC (5 g every 6 hours, 24 patients) was followed by fewer heart attacks than nitroglycerin alone (22 patients): 3 versus 10 (P=0.013). Symptomatic hypotension occurred in 7 versus 0 patients.
- Pizzulli 1997 (Am J Cardiol): in patients with angina and normal left ventricular function given a 48-hour nitroglycerin infusion, tolerance developed in 14 of 15 patients on nitroglycerin alone; with NAC, 11 of 16 kept significant vasodilation and 5 of 16 lost it.
- Ardissino 1997 (J Am Coll Cardiol): a randomized, double-blind trial in 200 patients with unstable angina followed for 4 months. Death, heart attack or refractory angina requiring revascularization occurred in 31% on transdermal nitroglycerin, 42% on oral NAC, 13% on both, and 39% on placebo. Side effects, mainly intolerable headache, occurred in 35% on the combination, almost twice as often as with nitroglycerin alone; the authors wrote that this limits the strategy's clinical applicability at the doses used.
Type 2 Diabetes and Metabolic Syndrome
The results on blood sugar are mixed and come from small, short studies.
- Szkudlinska 2016 (J Diabetes Complications): 13 people with type 2 diabetes took NAC 600 mg twice daily for two weeks, then 1,200 mg twice daily for two weeks. Glycemic control, glucose tolerance, insulin release and oxidative markers did not change with either dose.
- Sekhar 2022 (Antioxidants): a pilot study of glycine plus NAC (GlyNAC) for 14 days in 10 adults with type 2 diabetes, compared with 10 unsupplemented non-diabetic controls. Insulin resistance fell by 22% and mitochondrial fat oxidation rose by 30%. There was no NAC-only arm and no placebo group.
- Treweeke 2012 (Diabetologia): a placebo-controlled crossover trial in 14 people with type 2 diabetes. Oral NAC (1,200 mg) reduced platelet-monocyte conjugation from 53.1% to 42.5% two hours after a dose, with the effect maintained after 7 days, and raised intraplatelet glutathione in people whose levels were low.
- Martina 2008: NAC plus L-arginine in men with hypertension and type 2 diabetes improved markers of endothelial function and lowered blood pressure.
In these studies, NAC alone did not change glucose tolerance in two weeks of use, while the platelet and endothelial findings come from small trials of laboratory markers.
Blood Lipids and Lipoprotein(a)
- Wiklund 1996: NAC had no significant effect on plasma lipoprotein(a) in 11 people with high levels, although it lowered homocysteine by 45%. The study had been designed to test whether NAC's disulfide-breaking action could lower lipoprotein(a); it did not.
- Franceschini 1993 (Pharmacol Res): 10 hyperlipidemic patients on rising doses of NAC from 1,200 to 3,600 mg/day. Total cholesterol, triglycerides and lipoprotein(a) did not change appreciably; HDL-cholesterol rose in a dose-related way, by approximately 10 mg/dL (16.2%) at the highest dose.
- Martina 2008: with NAC plus L-arginine, total and LDL cholesterol fell and HDL cholesterol rose.
Peripheral Artery Disease
The evidence is limited to vascular-function measurements:
- Andrews 2001: in 14 patients, NAC infused into the femoral artery potentiated acetylcholine-mediated leg-artery vasodilation (p=0.001).
No trial of NAC in people with peripheral artery disease was among the papers checked for this page.
Doses Used in the Studies
The doses below are those reported by the studies cited on this page, not dosing guidance.
Oral
- Homocysteine and blood pressure: 1.8 g/day for 4 weeks (Hildebrandt 2015); 1.2 g twice daily for 4 weeks in hemodialysis (Friedman 2003)
- Blood pressure with an ACE inhibitor: 600 mg three times daily for 21 days (Barrios 2002)
- Heart failure: 600 mg twice daily for 12 weeks (Yazdi 2022); 500 mg twice daily for 28 days (Camuglia 2013)
- Type 2 diabetes: 600 mg then 1,200 mg twice daily, two weeks each (Szkudlinska 2016); 1,200 mg (Treweeke 2012)
- Lipids: 1,200 rising to 3,600 mg/day (Franceschini 1993)
- Nitrate tolerance: a single 200 mg/kg dose (Packer 1987)
Intravenous (hospital studies)
- NACIAM: 29 g over 2 days with nitroglycerin 7.2 mg over 2 days (Pasupathy 2017)
- Acute MI with streptokinase: 15 g over 24 hours (Arstall 1995)
- Unstable angina: 5 g every 6 hours with intravenous nitroglycerin (Horowitz 1988)
- Nitroglycerin tolerance: 2,000 mg bolus, then 5 mg/kg/hour for 48 hours (Pizzulli 1997)
- Coronary bypass surgery: 50 mg/kg added to cardioplegia solution (Koramaz 2006)
In a study of six healthy volunteers, the oral bioavailability of NAC was 4.0% for reduced NAC and 9.1% for total NAC (Olsson 1988).
Safety and the Nitroglycerin Interaction
The Nitroglycerin Interaction
NAC potentiates the vasodilator effects of nitroglycerin. In the Horowitz 1988 unstable-angina trial, symptomatic hypotension occurred in 7 of 24 patients given intravenous NAC with intravenous nitroglycerin versus none of 22 given nitroglycerin alone. In the Ardissino 1997 trial, side effects, mainly intolerable headache, occurred in 35% of patients on transdermal nitroglycerin plus oral NAC, almost twice the rate with nitroglycerin alone. These findings matter most for people who use nitrates; decisions about medicines and supplements belong with a clinician.
Other Safety Findings
- Intravenous NAC: in a UK trial in acetaminophen overdose, severe anaphylactoid reactions were recorded in 31 patients given the standard 20.25-hour intravenous regimen versus 5 given a shorter 12-hour regimen, and vomiting was also less frequent with the shorter regimen (Bateman 2014).
- Contrast-induced kidney injury: two large trials found no benefit of NAC in people undergoing angiography. In ACT (2,308 patients), contrast-induced acute kidney injury occurred in 12.7% with NAC and 12.7% with placebo. In PRESERVE (4,993 patients analysed), death, dialysis or a persistent rise in creatinine at 90 days occurred in 4.6% with NAC and 4.5% with placebo, and contrast-associated kidney injury did not differ. The full story is on the NAC & Kidney Health page.
- No significant adverse events were seen in the 1995 acute MI study (Arstall 1995), and NAC was well tolerated in hemodialysis patients (Friedman 2003); these were small studies.
- Inhaled NAC and asthma are covered on the NAC & Respiratory Health page.
Key Research Papers
- Hildebrandt W, Sauer R, Bonaterra G, Dugi KA, Edler L, Kinscherf R. Oral N-acetylcysteine reduces plasma homocysteine concentrations regardless of lipid or smoking status. Am J Clin Nutr 2015;102(5):1014–1024. PubMed PMID: 26447155
- Wiklund O, Fager G, Andersson A, Lundstam U, Masson P, Hultberg B. N-acetylcysteine treatment lowers plasma homocysteine but not serum lipoprotein(a) levels. Atherosclerosis 1996;119(1):99–106. PubMed PMID: 8929261
- Friedman AN, Bostom AG, Laliberty P, Selhub J, Shemin D. The effect of N-acetylcysteine on plasma total homocysteine levels in hemodialysis: a randomized, controlled study. Am J Kidney Dis 2003;41(2):442–446. PubMed PMID: 12552508
- Ventura P, Panini R, Pasini MC, Scarpetta G, Salvioli G. N-Acetyl-cysteine reduces homocysteine plasma levels after single intravenous administration by increasing thiols urinary excretion. Pharmacol Res 1999;40(4):345–350. PubMed PMID: 10527647
- Martina V, Masha A, Gigliardi VR, Brocato L, Manzato E, Berchio A, et al. Long-term N-acetylcysteine and L-arginine administration reduces endothelial activation and systolic blood pressure in hypertensive patients with type 2 diabetes. Diabetes Care 2008;31(5):940–944. PubMed PMID: 18268065
- Andrews NP, Prasad A, Quyyumi AA. N-acetylcysteine improves coronary and peripheral vascular function. J Am Coll Cardiol 2001;37(1):117–123. PubMed PMID: 11153725
- Packer M, Lee WH, Kessler PD, Gottlieb SS, Medina N, Yushak M. Prevention and reversal of nitrate tolerance in patients with congestive heart failure. N Engl J Med 1987;317(13):799–804. PubMed PMID: 3114637
- Horowitz JD, Henry CA, Syrjanen ML, Louis WJ, Fish RD, Smith TW, et al. Combined use of nitroglycerin and N-acetylcysteine in the management of unstable angina pectoris. Circulation 1988;77(4):787–794. PubMed PMID: 3127076
- Ardissino D, Merlini PA, Savonitto S, Demicheli G, Zanini P, Bertocchi F, et al. Effect of transdermal nitroglycerin or N-acetylcysteine, or both, in the long-term treatment of unstable angina pectoris. J Am Coll Cardiol 1997;29(5):941–947. PubMed PMID: 9120179
- Pasupathy S, Tavella R, Grover S, Raman B, Procter NEK, Du YT, et al. Early use of N-acetylcysteine with nitrate therapy in patients undergoing primary percutaneous coronary intervention for ST-segment-elevation myocardial infarction reduces myocardial infarct size (the NACIAM trial [N-acetylcysteine in Acute Myocardial Infarction]). Circulation 2017;136(10):894–903. PubMed PMID: 28634219
- Arstall MA, Yang J, Stafford I, Betts WH, Horowitz JD. N-acetylcysteine in combination with nitroglycerin and streptokinase for the treatment of evolving acute myocardial infarction. Safety and biochemical effects. Circulation 1995;92(10):2855–2862. PubMed PMID: 7586252
- Koramaz I, Pulathan Z, Usta S, Karahan SC, Alver A, Yaris E, et al. Cardioprotective effect of cold-blood cardioplegia enriched with N-acetylcysteine during coronary artery bypass grafting. Ann Thorac Surg 2006;81(2):613–618. PubMed PMID: 16427861
- Wang G, Bainbridge D, Martin J, Cheng D. N-acetylcysteine in cardiac surgery: do the benefits outweigh the risks? A meta-analytic reappraisal. J Cardiothorac Vasc Anesth 2011;25(2):268–275. PubMed PMID: 20638862
- Yazdi A, Khansari N, Mehrpooya M, Mohammadi Y, Zareie S. Oral N-acetylcysteine as an adjunct to standard medical therapy improved heart function in cases with stable class II and III systolic heart failure. Ir J Med Sci 2022;191(5):2063–2075. PubMed PMID: 34727343
- Giam B, Chu PY, Kuruppu S, Smith AI, Horlock D, Kiriazis H, et al. N-acetylcysteine attenuates the development of cardiac fibrosis and remodeling in a mouse model of heart failure. Physiol Rep 2016;4(7):e12757. PubMed PMID: 27081162
- Cui Y, Narasimhulu CA, Liu L, Zhang Q, Liu PZ, Li X, et al. N-acetylcysteine inhibits in vivo oxidation of native low-density lipoprotein. Sci Rep 2015;5:16339. PubMed PMID: 26536834
- Franceschini G, Werba JP, Safa O, Gikalov I, Sirtori CR. Dose-related increase of HDL-cholesterol levels after N-acetylcysteine in man. Pharmacol Res 1993;28(3):213–218. PubMed PMID: 8108311
- Szkudlinska MA, von Frankenberg AD, Utzschneider KM. The antioxidant N-Acetylcysteine does not improve glucose tolerance or β-cell function in type 2 diabetes. J Diabetes Complications 2016;30(4):618–622. PubMed PMID: 26922582
- Treweeke AT, Winterburn TJ, Mackenzie I, Barrett F, Barr C, Rushworth GF, et al. N-Acetylcysteine inhibits platelet-monocyte conjugation in patients with type 2 diabetes with depleted intraplatelet glutathione: a randomised controlled trial. Diabetologia 2012;55(11):2920–2928. PubMed PMID: 22935960
- Hosseini H, Naderi-Behdani F, Zarghami N, et al. NAC effects on metabolic syndrome: RCT. Complement Ther Med 2022;71:102898. — Editorial note: this reference could not be found in PubMed or Crossref (checked 2026-10-14); no statement on this page relies on it.
- Zhu Q, Xiao Y, Jiang M, Liu X, Cui Y, Hao H, et al. N-acetylcysteine attenuates atherosclerosis progression in aging LDL receptor deficient mice with preserved M2 macrophages and increased CD146. Atherosclerosis 2022;357:41–50. PubMed PMID: 36041358
- Wilmink HW, Stroes ES, Erkelens WD, et al. NAC prevents post-methionine endothelial dysfunction. Arterioscler Thromb Vasc Biol 1999;19(12):2862–2866. Search PubMed — Editorial note: this reference could not be found in PubMed or Crossref (checked 2026-10-14); no statement on this page relies on it.
- Pizzulli L, Hagendorff A, Zirbes M, Jung W, Lüderitz B. N-acetylcysteine attenuates nitroglycerin tolerance in patients with angina pectoris and normal left ventricular function. Am J Cardiol 1997;79(1):28–33. PubMed PMID: 9024731
- Barrios V, Calderón A, Navarro-Cid J, Lahera V, Ruilope LM. N-acetylcysteine potentiates the antihypertensive effect of ACE inhibitors in hypertensive patients. Blood Press 2002;11(4):235–239. PubMed PMID: 12361192
- Camuglia AC, Maeder MT, Starr J, Farrington C, Kaye DM. Impact of N-acetylcysteine on endothelial function, B-type natriuretic peptide and renal function in patients with the cardiorenal syndrome: a pilot cross over randomised controlled trial. Heart Lung Circ 2013;22(4):256–259. PubMed PMID: 23219310
- Sekhar RV. GlyNAC (glycine and N-acetylcysteine) supplementation improves impaired mitochondrial fuel oxidation and lowers insulin resistance in patients with type 2 diabetes: results of a pilot study. Antioxidants (Basel) 2022;11(1):154. PubMed PMID: 35052658
- Faghfouri AH, Zarezadeh M, Tavakoli-Rouzbehani OM, Radkhah N, Faghfuri E, Kord-Varkaneh H, et al. The effects of N-acetylcysteine on inflammatory and oxidative stress biomarkers: a systematic review and meta-analysis of controlled clinical trials. Eur J Pharmacol 2020;884:173368. PubMed PMID: 32726657
- Gu WJ, Wu ZJ, Wang PF, Aung LH, Yin RX. N-Acetylcysteine supplementation for the prevention of atrial fibrillation after cardiac surgery: a meta-analysis of eight randomized controlled trials. BMC Cardiovasc Disord 2012;12:10. PubMed PMID: 22364379
- Liu XH, Xu CY, Fan GH. Efficacy of N-acetylcysteine in preventing atrial fibrillation after cardiac surgery: a meta-analysis of published randomized controlled trials. BMC Cardiovasc Disord 2014;14:52. PubMed PMID: 24739515
- Hassan AA, Ismail NR, Rezk AE, Elfeky HM, Mady AM, Allam AG, et al. Efficacy of N-acetylcysteine in reducing the risk of postoperative atrial fibrillation in cardiothoracic surgery: a systematic review and meta-analysis of randomized controlled trials. Minerva Cardiol Angiol 2025;73(3):387–396. PubMed PMID: 38842239
- Pereira JEG, El Dib R, Braz LG, Escudero J, Hayes J, Johnston BC. N-acetylcysteine use among patients undergoing cardiac surgery: a systematic review and meta-analysis of randomized trials. PLoS One 2019;14(5):e0213862. PubMed PMID: 31071081
- ACT Investigators. Acetylcysteine for prevention of renal outcomes in patients undergoing coronary and peripheral vascular angiography: main results from the randomized Acetylcysteine for Contrast-induced nephropathy Trial (ACT). Circulation 2011;124(11):1250–1259. PubMed PMID: 21859972
- Weisbord SD, Gallagher M, Jneid H, Garcia S, Cass A, Thwin SS, et al. Outcomes after angiography with sodium bicarbonate and acetylcysteine. N Engl J Med 2018;378(7):603–614. PubMed PMID: 29130810
- Bateman DN, Dear JW, Thanacoody HK, Thomas SH, Eddleston M, Sandilands EA, et al. Reduction of adverse effects from intravenous acetylcysteine treatment for paracetamol poisoning: a randomised controlled trial. Lancet 2014;383(9918):697–704. PubMed PMID: 24290406
- Olsson B, Johansson M, Gabrielsson J, Bolme P. Pharmacokinetics and bioavailability of reduced and oxidized N-acetylcysteine. Eur J Clin Pharmacol 1988;34(1):77–82. PubMed PMID: 3360052
PubMed Topic Searches
Selected PubMed topic searches relevant to N-acetylcysteine in cardiovascular medicine, including nitrate tolerance, homocysteine, and endothelial function.
- PubMed: NAC and nitrate tolerance
- PubMed: NAC and homocysteine reduction
- PubMed: NAC and endothelial function
- PubMed: NAC in STEMI (NACIAM trial)
- PubMed: NAC and cardiac ischemia-reperfusion
- PubMed: NAC and atrial fibrillation prevention
- PubMed: NAC in heart failure
- PubMed: NAC and contrast nephropathy
- PubMed: NAC and platelet aggregation
- PubMed: Glutathione and cardiovascular disease
- PubMed: Homocysteine and cardiovascular risk
- PubMed: Nitric oxide and vascular function
Connections
- Free Radicals & Your Antioxidant Network — interactive animation
- NAC
- NAC and Glutathione
- NAC and Kidney Health
- Cardiovascular Disease
- Hypertension
- Heart Failure
- Coronary Artery Disease
- Peripheral Artery Disease
- Atherosclerosis
- Arginine
- Taurine
- Cysteine
- Homocysteine
- Blood Sugar
- NAD+ and NMN
- Longevity Protocols
- Metabolic Syndrome
- Atrial Fibrillation