EGCG (Epigallocatechin Gallate): The Most-Studied Green Tea Catechin
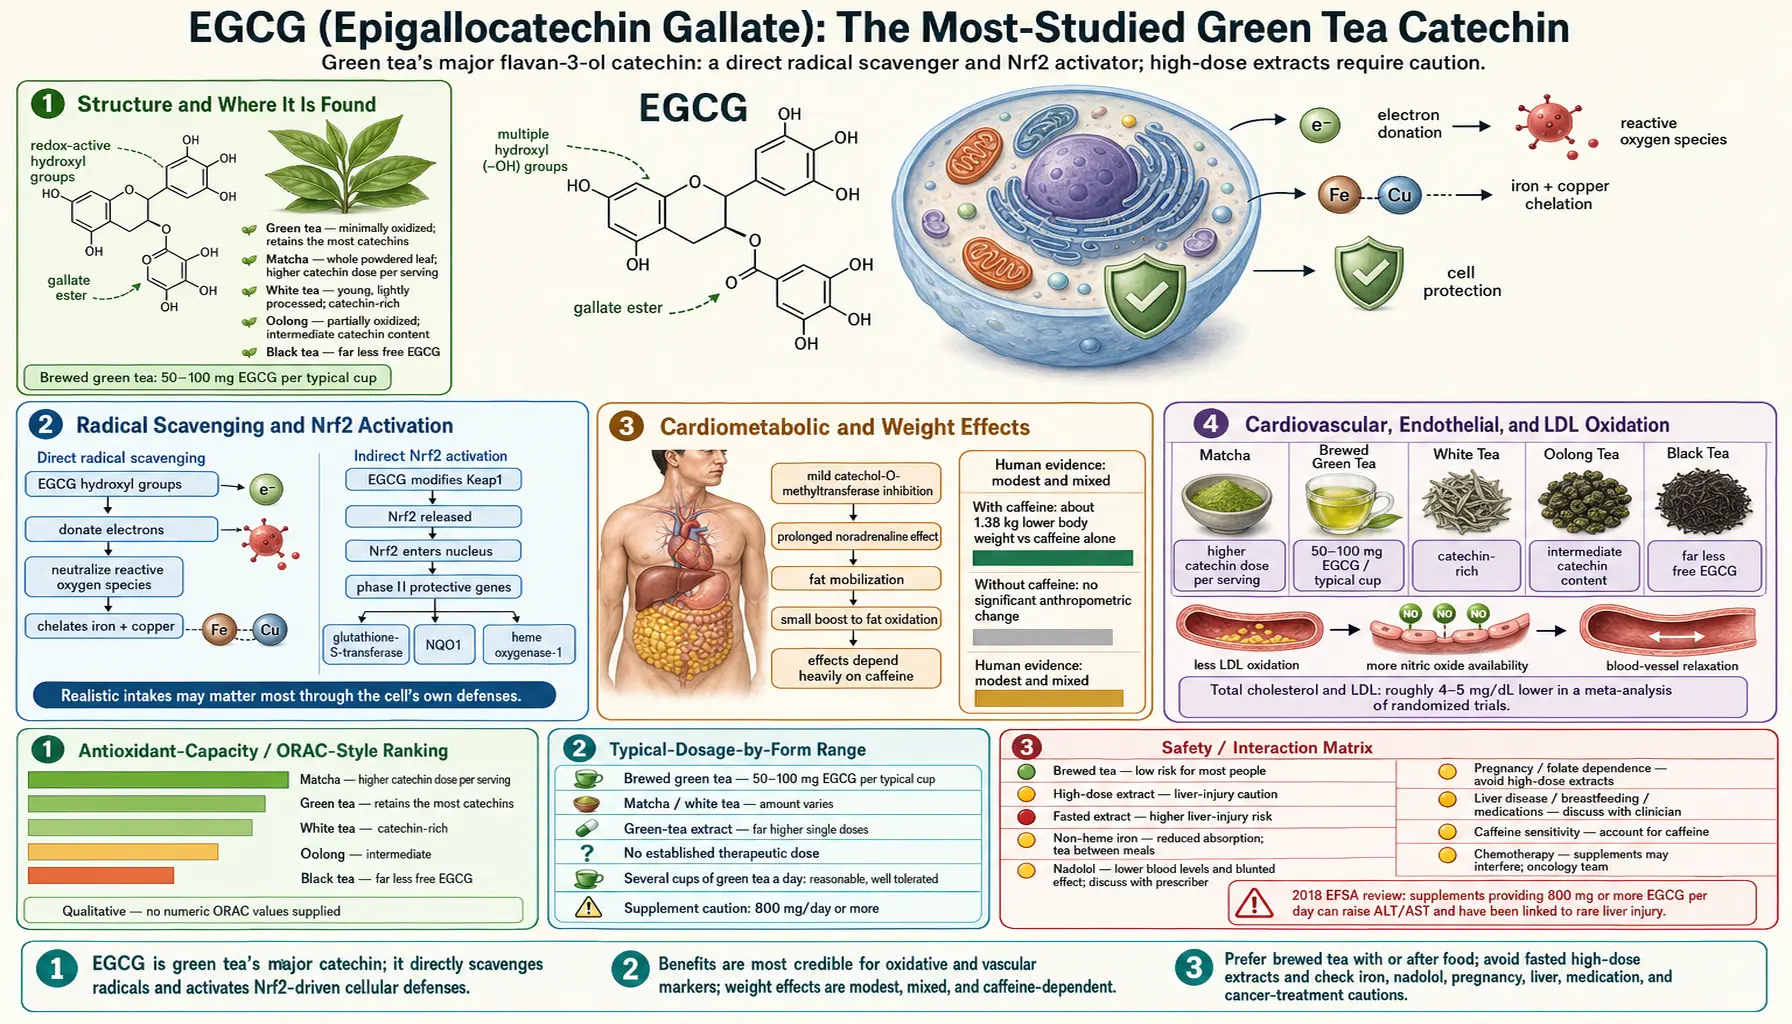
EGCG (epigallocatechin gallate) is the major catechin — a type of flavan-3-ol polyphenol — in the leaves of Camellia sinensis, the tea plant. Most of the polyphenols in green tea are catechins, and the European Food Safety Authority (EFSA) describes EGCG as the most relevant catechin in green tea. Because green tea is widely consumed, EGCG is also heavily researched, with a large body of laboratory studies and a smaller, uneven body of human trials.
This article separates what is well established from what is still uncertain. In laboratory studies EGCG scavenges free radicals and activates the body's own antioxidant defenses, and EFSA concluded that catechins from traditionally brewed green tea are in general considered safe at the intakes reported in Europe, while noting rare cases of liver injury after green tea infusions. But many of the dramatic claims attached to EGCG — fat-burning, cancer cures, brain rejuvenation — rest mostly on cell-culture and animal work that does not translate cleanly to people, partly because EGCG is poorly absorbed when swallowed. We cover the structure and food sources, the antioxidant mechanisms, the modest and mixed cardiometabolic data, cardiovascular and neuroprotective effects, the cancer-chemoprevention evidence, dosing and bioavailability, and the real safety issues with high-dose supplements.
Table of Contents
- Structure and Where It Is Found
- Radical Scavenging and Nrf2 Activation
- Cardiometabolic and Weight Effects
- Cardiovascular, Endothelial, and LDL Oxidation
- Neuroprotection and the Brain
- Cancer Chemoprevention (Not a Treatment)
- Forms, Dosing, and Bioavailability
- Safety and Interactions
- Key Research Papers
- Connections
- Featured Videos
Structure and Where It Is Found
EGCG is a flavan-3-ol (a subclass of flavonoid polyphenols) carrying multiple hydroxyl (−OH) groups and a gallate ester. Those hydroxyl groups can donate electrons to neutralize reactive molecules, which is the basis of its antioxidant activity in laboratory tests. Its chemical relatives in tea include epicatechin (EC), epigallocatechin (EGC), and epicatechin gallate (ECG).
EGCG is found almost exclusively in tea made from Camellia sinensis. The richest sources are:
- Green tea — the classic source; minimally oxidized leaves retain the most catechins.
- Matcha — powdered whole green-tea leaf, so the leaf itself is consumed rather than an infusion of it.
- White tea — young, lightly processed leaves and buds, also catechin-rich.
- Oolong tea — partially oxidized, with intermediate catechin content.
Black tea is fully oxidized during processing, which converts much of the EGCG into larger polymerized polyphenols (theaflavins and thearubigins), so black tea contains far less free EGCG than green tea. The amount in a cup varies with the leaf, water temperature and steeping time. EFSA estimated mean EGCG intake from green tea infusions at 90–300 mg per day in European adults, with high consumers reaching up to about 866 mg per day; food supplements containing green tea catechins supplied 5–1,000 mg of EGCG per day.
Radical Scavenging and Nrf2 Activation
EGCG protects cells against oxidative stress in two distinct ways, and the distinction matters for understanding the evidence.
1. Direct radical scavenging. The hydroxyl-rich structure lets EGCG directly quench reactive oxygen species and chelate (bind) transition metals such as iron and copper that otherwise catalyze damaging free-radical reactions. In a test tube, EGCG is a potent antioxidant. The catch is that to scavenge radicals directly throughout the body, the molecule has to reach the tissues at meaningful concentrations — and, as the dosing section explains, very little swallowed EGCG actually does.
2. Indirect "antioxidant response" (Nrf2) activation. This is the mechanism researchers increasingly think matters most at realistic intakes. EGCG activates Nrf2 (nuclear factor erythroid 2–related factor 2), the master transcription factor that switches on the cell's own antioxidant and detoxification machinery. It does this largely by modifying Keap1, the protein that normally holds Nrf2 inactive; releasing Nrf2 lets it move into the nucleus and turn up genes for protective phase II enzymes such as glutathione-S-transferase, NAD(P)H:quinone oxidoreductase 1 (NQO1), and heme oxygenase-1. In this model, EGCG behaves less like a direct antioxidant and more like a mild hormetic signal that prompts cells to produce more of their own antioxidants — the same model proposed for compounds like sulforaphane.
Cardiometabolic and Weight Effects
EGCG is widely marketed for fat loss and metabolism; the human data are modest and mixed. Proposed mechanisms include mild inhibition of catechol-O-methyltransferase (which prolongs the fat-mobilizing effect of noradrenaline) and a small boost to fat oxidation — effects that appear to depend heavily on caffeine being present alongside the catechins.
A 2010 meta-analysis of 15 randomized trials (1,243 participants) in the American Journal of Clinical Nutrition (Phung and colleagues) found that green tea catechins with caffeine reduced body weight by 1.38 kg compared with caffeine alone, with small reductions in BMI and waist circumference; compared with a caffeine-free control the reduction was 0.44 kg. Studies of catechins without caffeine showed no benefit on any measure, and the authors judged the clinical significance of the reductions "modest at best". A 2012 Cochrane review (Jurgens and colleagues) found that green tea preparations produced a small, statistically non-significant weight loss in overweight or obese adults that was not likely to be clinically important; trials run in Japan showed larger but too dissimilar effects to pool. More detail is on the Metabolism & Weight page.
Cardiovascular, Endothelial, and LDL Oxidation
The cardiovascular signal is more consistent than the weight signal. EGCG and the other green-tea catechins have been shown to improve several markers of vascular health.
- Cholesterol. A 2020 meta-analysis of 31 randomized trials (3,321 participants; Xu and colleagues) found that green tea intake lowered total cholesterol by 4.66 mg/dL and LDL cholesterol by 4.55 mg/dL compared with controls, with no effect on HDL cholesterol or triglycerides.
- LDL oxidation. Oxidized LDL is a step in plaque formation. In laboratory studies EGCG reduces the oxidative modification of LDL particles by scavenging radicals and chelating metals.
- Endothelial function. Catechins are proposed to support nitric oxide, the molecule that lets blood vessels relax and widen. In 42 people with coronary artery disease, flow-mediated dilation of the brachial artery improved from 7.1% to 8.6% two hours after a single 300 mg dose of EGCG, but was similar to baseline after two weeks of 150 mg twice daily, measured about 14 hours after the last dose (Widlansky and colleagues, 2007).
In the Ohsaki cohort of Japanese adults (Kuriyama and colleagues, 2006), green tea consumption was associated with lower mortality from all causes and from cardiovascular disease, but not from cancer; the associations were stronger in women. Observational associations cannot prove cause and effect.
Neuroprotection and the Brain
EGCG concentrations in the blood are very low and fall within hours of a dose; a 2019 review (Pervin and colleagues) notes that in vitro experiments suggest EGCG and its gut-microbial metabolites can reach brain tissue through the blood-brain barrier. Once there (and via its metabolites), it has shown a range of neuroprotective actions in laboratory and animal models: scavenging radicals, chelating the excess iron implicated in neurodegeneration, activating Nrf2-driven defenses, dampening neuroinflammation, and — notably — inhibiting the misfolding and aggregation of the proteins central to disease, namely amyloid-beta in Alzheimer's and alpha-synuclein in Parkinson's.
This is an active research area, but nearly all of the neuroprotective evidence is preclinical — cell cultures and animals. Rigorous human trials showing that EGCG or green tea prevents or treats Alzheimer's or Parkinson's disease do not yet exist, and EGCG supplements are not a proven neuroprotective therapy.
Cancer Chemoprevention (Not a Treatment)
EGCG is the green-tea component most studied for cancer chemoprevention. In cell-culture and animal models it interferes with many of the pathways tumors rely on: it can inhibit pro-cancer signaling (such as NF-κB and AP-1 and several receptor tyrosine kinases), influence the cell cycle, trigger programmed cell death (apoptosis) in malignant cells, and alter epigenetic marks. A 2009 review (Yang and colleagues) reports that tea extracts and tea polyphenols inhibit the formation and development of tumors at different organ sites in animal models.
The human picture is far weaker. Some epidemiological studies associate higher green-tea consumption with modestly lower risk of certain cancers, but findings are inconsistent across populations and cancer types, and association is not proof. EGCG is not a proven cancer treatment, and it is not a substitute for medical care. Its translation to people is also limited by its poor oral bioavailability and chemical instability. In cell and mouse experiments, EGCG blocked the anticancer effect of the drug bortezomib (Golden and colleagues, 2009; not tested in patients), and high-dose extracts carry the liver-injury findings discussed below.
Forms, Dosing, and Bioavailability
The defining practical fact about EGCG is its poor oral bioavailability. After swallowing, only a small percentage of EGCG enters the bloodstream intact — estimates from human studies put systemic levels far below the concentrations used to produce effects in test-tube experiments. EGCG is also chemically unstable, sensitive to extensive phase II metabolism, and broken down by gut bacteria, all of which limit how much reaches the tissues.
Common forms and considerations:
- Brewed green tea, matcha, white tea — EGCG delivered along with the other catechins, L-theanine, and caffeine; EFSA considers traditionally brewed green tea in general safe at the intakes reported in Europe.
- Green-tea extract (GTE) supplements — standardized to a percentage of EGCG; deliver far higher single doses than tea, which is exactly why they carry the safety concerns below.
- Absorption with food and timing. Food reduces EGCG uptake. In one crossover study, plasma EGCG exposure (AUC) was 2.7 times higher when capsules were taken with water than with a light breakfast (Naumovski and colleagues, 2015), and in a trial of 30 volunteers the peak plasma level of free EGCG was more than 3.5-fold higher after an overnight fast than with a light breakfast (Chow and colleagues, 2005). USP and EFSA have connected that same fasted condition with a higher risk of adverse effects from concentrated extracts.
There is no established therapeutic dose of EGCG. Regulators have set limits instead: the EU requires a daily portion of a food containing green tea extract to supply less than 800 mg of EGCG, and requires a label warning against consumption on an empty stomach. The Safety & Liver page sets out the details.
Safety and Interactions
EFSA concluded in 2018 that catechins from traditionally brewed green tea are in general considered safe at the intakes reported in Europe, while noting that rare cases of liver injury have been reported after drinking green tea infusions, most probably as an idiosyncratic reaction; LiverTox likewise describes rare cases after large amounts of green tea. The main concerns apply to concentrated green tea extracts.
- Liver injury from concentrated extracts. EFSA found that intervention trials of EGCG doses of 800 mg or more per day taken as a food supplement produced a statistically significant rise in serum transaminases (liver enzymes), and it could not identify an intake from supplements that does not give rise to concern. Taking extracts fasted and as a single bolus raises EGCG exposure. In the Minnesota Green Tea Trial, ALT elevations occurred in 6.7% of women taking 843 mg of EGCG a day versus 0.7% on placebo (Dostal and colleagues, 2015). USP's 2008 and 2020 reviews and a 2009 case review (Mazzanti and colleagues, 34 cases) document liver injury from green tea products, and in the U.S. Drug-Induced Liver Injury Network the immune gene variant HLA-B*35:01 was found in 72% of green tea cases (Hoofnagle and colleagues, 2021). Since 2022, EU Regulation 2022/2340 requires a daily portion of a food to contain less than 800 mg of EGCG from green tea extracts.
- Non-heme iron absorption. Tea polyphenols bind the plant-derived (non-heme) iron in food and lower its absorption. The research raises this concern mainly for people with iron-deficiency anemia and those relying on plant iron.
- Nadolol interaction. In 10 healthy volunteers, drinking green tea (700 ml a day for 14 days) lowered the peak level and total exposure of the beta-blocker nadolol by about 85% and reduced its effect on systolic blood pressure; cell experiments showed green tea inhibits OATP1A2, a transporter that carries nadolol (Misaka and colleagues, 2014). A single cup of green tea taken with nadolol lowered its exposure (AUC) to 37% of that with water, and a cup taken an hour before lowered it to 54% (Misaka and colleagues, 2020).
- Folic acid. In healthy volunteers, green tea taken with a 0.4 mg folic acid tablet lowered peak serum folate by 39% and total exposure by 27% (Alemdaroglu and colleagues, 2008). EFSA noted that none of the intervention studies it reviewed included pregnant or lactating women, and the EU regulation requires a label warning that green tea extracts should not be consumed by them or by children under 18.
- Caffeine. Tea and many extracts contain caffeine; some extracts are decaffeinated.
- Label warnings. The U.S. Pharmacopeia's cautionary label statement for its powdered decaffeinated green tea extract monograph reads: “Do not take on an empty stomach. Take with food. Do not use if you have a liver problem and discontinue use and consult a healthcare practitioner if you develop symptoms of liver trouble, such as abdominal pain, dark urine, or jaundice (yellowing of the skin or eyes).” Decisions about supplements belong with a clinician.
Key Research Papers
A selection of peer-reviewed papers on EGCG covering its mechanisms, cardiometabolic and lipid effects, neuroprotection, cancer chemoprevention, bioavailability, and safety. Each citation links to its DOI; journal and author names are plain text.
- Singh BN, Shankar S, Srivastava RK. Green tea catechin, epigallocatechin-3-gallate (EGCG): mechanisms, perspectives and clinical applications. Biochemical Pharmacology — 2011;82(12):1807–1821. — doi:10.1016/j.bcp.2011.07.093
- Negri A, Naponelli V, Rizzi F, Bettuzzi S. Molecular targets of epigallocatechin—gallate (EGCG): a special focus on signal transduction and cancer. Nutrients — 2018;10(12):1936. — doi:10.3390/nu10121936
- Xu R, Yang K, Li S, Dai M, Chen G. Effect of green tea consumption on blood lipids: a systematic review and meta-analysis of randomized controlled trials. Nutrition Journal — 2020;19(1):48. — doi:10.1186/s12937-020-00557-5
- Phung OJ, Baker WL, Matthews LJ, Lanosa M, Thorne A, Coleman CI. Effect of green tea catechins with or without caffeine on anthropometric measures: a systematic review and meta-analysis. The American Journal of Clinical Nutrition — 2010;91(1):73–81. — doi:10.3945/ajcn.2009.28157
- Pervin M, Unno K, Takagaki A, Isemura M, Nakamura Y. Function of green tea catechins in the brain: epigallocatechin gallate and its metabolites. International Journal of Molecular Sciences — 2019;20(15):3630. — doi:10.3390/ijms20153630
- Naumovski N, Blades BL, Roach PD. Food inhibits the oral bioavailability of the major green tea antioxidant epigallocatechin gallate in humans. Antioxidants — 2015;4(2):373–393. — doi:10.3390/antiox4020373
- EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal — 2018;16(4):5239. — doi:10.2903/j.efsa.2018.5239
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. British Journal of Clinical Pharmacology — 2020;86(11):2314–2318. — doi:10.1111/bcp.14315
- Misaka S, Yatabe J, Müller F, et al. Green tea ingestion greatly reduces plasma concentrations of nadolol in healthy subjects. Clinical Pharmacology & Therapeutics — 2014;95(4):432–438. — PubMed PMID: 24419562
- Jurgens TM, Whelan AM, Killian L, Doucette S, Kirk S, Foy E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane Database of Systematic Reviews — 2012;12:CD008650. — PubMed PMID: 23235664
- Widlansky ME, Hamburg NM, Anter E, et al. Acute EGCG supplementation reverses endothelial dysfunction in patients with coronary artery disease. Journal of the American College of Nutrition — 2007;26(2):95–102. — PubMed PMID: 17536120
- Kuriyama S, Shimazu T, Ohmori K, et al. Green tea consumption and mortality due to cardiovascular disease, cancer, and all causes in Japan: the Ohsaki study. JAMA — 2006;296(10):1255–1265. — PubMed PMID: 16968850
- Yang CS, Wang X, Lu G, Picinich SC. Cancer prevention by tea: animal studies, molecular mechanisms and human relevance. Nature Reviews Cancer — 2009;9(6):429–439. — PubMed PMID: 19472429
- Golden EB, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood — 2009;113(23):5927–5937. — PubMed PMID: 19190249
- Chow HH, Hakim IA, Vining DR, et al. Effects of dosing condition on the oral bioavailability of green tea catechins after single-dose administration of Polyphenon E in healthy individuals. Clinical Cancer Research — 2005;11(12):4627–4633. — PubMed PMID: 15958649
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food and Chemical Toxicology — 2015;83:26–35. — PubMed PMID: 26051348
- Hoofnagle JH, Bonkovsky HL, Phillips EJ, et al. HLA-B*35:01 and green tea-induced liver injury. Hepatology — 2021;73(6):2484–2493. — PubMed PMID: 32892374
- Mazzanti G, Menniti-Ippolito F, Moro PA, et al. Hepatotoxicity from green tea: a review of the literature and two unpublished cases. European Journal of Clinical Pharmacology — 2009;65(4):331–341. — PubMed PMID: 19198822
- Sarma DN, Barrett ML, Chavez ML, et al. Safety of green tea extracts: a systematic review by the US Pharmacopeia. Drug Safety — 2008;31(6):469–484. — PubMed PMID: 18484782
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicology Reports — 2020;7:386–402. — PubMed PMID: 32140423
- Alemdaroglu NC, Dietz U, Wolffram S, Spahn-Langguth H, Langguth P. Influence of green and black tea on folic acid pharmacokinetics in healthy volunteers: potential risk of diminished folic acid bioavailability. Biopharmaceutics & Drug Disposition — 2008;29(6):335–348. — PubMed PMID: 18551467
PubMed Topic Searches
- PubMed: EGCG antioxidant activity
- PubMed: EGCG and Nrf2 antioxidant enzymes
- PubMed: Green tea catechins and body weight
- PubMed: Green tea catechins and LDL cholesterol
- PubMed: EGCG and endothelial function
- PubMed: EGCG and the blood-brain barrier
- PubMed: EGCG and cancer chemoprevention
- PubMed: Green tea catechins and liver safety
Connections
- EGCG (Epigallocatechin Gallate) History
- EGCG (Epigallocatechin Gallate) Benefits
- Green Tea
- Quercetin
- Curcumin
- Anthocyanins
- Resveratrol
- Sulforaphane
- Glutathione
- Grape Seed Extract
- French Maritime Pine Bark
- Antioxidants
- Vitamin C
- Selenium
- Cardiovascular Disease
- Cancer
- Oxidative Stress
- Longevity Protocols