Taurine for Retinal and Eye Health
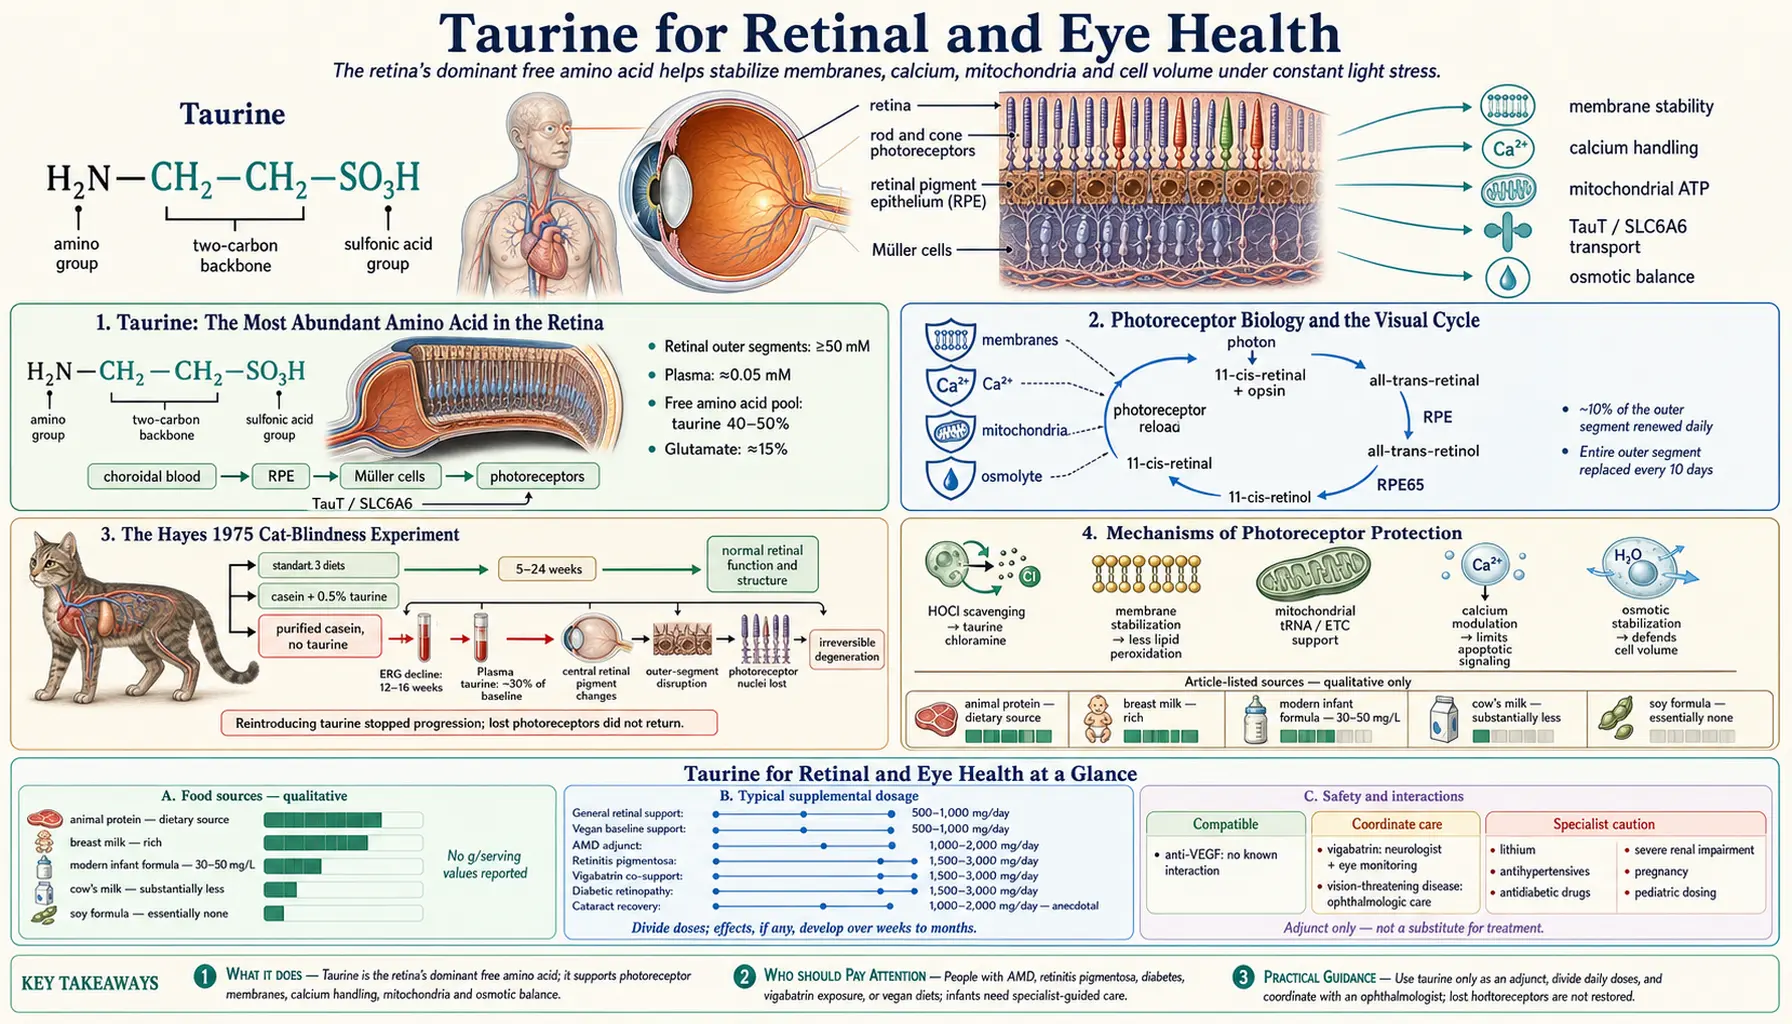
Taurine is the most abundant amino acid in the retina (Froger and colleagues 2014; Ripps and Shen 2012). The first experiment to link it to retinal health came in 1975, when K. C. Hayes, R. E. Carey, and S. Y. Schmidt reported in Science that a degeneration of the retina's photoreceptor cells developed in cats fed casein as their protein source, associated with a selective fall in plasma and retinal taurine. Taurine deficiency was later reported in many cats on unfortified commercial diets, and commercial cat food came to be fortified; taurine was also added to many infant formulas. This deep-dive covers photoreceptor biology, the Hayes study and what it showed, the mechanisms studied in the laboratory, and the research on age-related macular degeneration, retinitis pigmentosa, vigabatrin-associated retinopathy, and diabetic retinopathy.
Table of Contents
- Taurine: The Most Abundant Amino Acid in the Retina
- Photoreceptor Biology and the Visual Cycle
- The Hayes 1975 Cat Retina Study
- Mechanisms of Photoreceptor Protection
- Osmotic Regulation in Retinal Pigment Epithelium
- Calcium Handling in Photoreceptors
- Mitochondrial Function in the Retina
- Age-Related Macular Degeneration and Taurine
- Retinitis Pigmentosa
- Vigabatrin-Associated Retinopathy
- Diabetic Retinopathy
- Infant Formula and the Pediatric Story
- Doses Used in Eye Research
- Safety Findings
- Key Research Papers
- Connections
- Featured Videos
Taurine: The Most Abundant Amino Acid in the Retina
The retina is one of the most metabolically active tissues in the body. The mitochondria packed into the inner segments of rods and cones regenerate the light-sensitive pigment, pump ions, and produce the ATP needed to maintain the photoreceptors' resting “dark current”. Taurine is the most abundant amino acid in this tissue (Froger and colleagues 2014).
In an analysis of rat eye tissues, taurine was the most abundant amino acid in the retina, vitreous, lens, cornea, iris, and ciliary body (Ripps and Shen 2012). Studies of the free amino acids of chicken and rat retina (Pasantes-Morales and colleagues 1972) and of the developing rat retina (Macaione and colleagues 1974) documented the composition of the retinal amino acid pool.
Cells take up taurine through a sodium-dependent taurine transporter (TauT, gene SLC6A6) (Han and colleagues 2006). Mice in which this gene is disrupted have markedly lower taurine in many tissues and lose vision through severe retinal degeneration, identifying the transporter as important for the development and maintenance of normal retinal function and structure (Heller-Stilb and colleagues 2002). Froger and colleagues (2014) note that taurine's effects depend on its uptake into retinal cells, retinal blood-vessel cells, and the retinal pigment epithelium.
The functions proposed for retinal taurine include photoprotection, calcium modulation, osmotic regulation, mitochondrial preservation, and membrane stabilization — most of them studied in animal and cell models. In the retina, taurine is described as critical for photoreceptor development and as a protectant against stress-related damage to retinal neurons, although its cellular and biochemical mechanisms are not fully known (Ripps and Shen 2012).
Photoreceptor Biology and the Visual Cycle
Vision begins with the absorption of a photon by a pigment molecule embedded in the disc membranes of a rod or cone photoreceptor outer segment. The pigment in rods is rhodopsin (which mediates scotopic / low-light vision), and the pigments in cones are the related photopsins (mediating color vision and high-acuity photopic vision). All visual pigments share the same fundamental architecture: a seven-transmembrane opsin protein covalently linked, via a Schiff base, to the small molecule 11-cis-retinal (the active form of Vitamin A in vision).
When a photon strikes the pigment, the 11-cis-retinal absorbs the energy and isomerizes to all-trans-retinal. This conformational change is transmitted to the opsin protein, which activates a G-protein cascade (transducin in rods) that ultimately closes cation channels in the outer segment plasma membrane, hyperpolarizing the photoreceptor and producing the electrical signal that the inner retina processes into vision.
The all-trans-retinal then dissociates from the opsin and must be regenerated to 11-cis-retinal to make the pigment receptive again. This requires the retinoid visual cycle, in which the all-trans-retinal is transported to the retinal pigment epithelium (RPE), reduced to all-trans-retinol, isomerized to 11-cis-retinol by the RPE65 enzyme, oxidized to 11-cis-retinal, and shuttled back to the photoreceptor outer segment to reload the opsin. The whole cycle takes a few seconds in the dark.
The metabolic cost of running this cycle continuously, plus the constant pumping required to maintain the dark current, plus the daily renewal of about 10% of the photoreceptor outer segment (the entire outer segment is replaced every 10 days through a process of basal addition and apical phagocytosis by the RPE), makes the retina enormously demanding. The mitochondria in the inner segments produce ATP at near-maximum rates throughout life. The byproducts of this metabolism include large quantities of reactive oxygen species, which must be neutralized continuously to prevent photoreceptor damage.
Laboratory studies suggest that taurine contributes to the defences against this metabolic stress: it interacts with membrane phospholipids, influences calcium handling, and acts as an organic osmolyte (Schaffer and colleagues 2010; Lambert and colleagues 2015). How much each of these matters in the living human retina is not known.
The Hayes 1975 Cat Retina Study
The first evidence that taurine matters for the retina came from cats. In 1975, K. C. Hayes, R. E. Carey, and S. Y. Schmidt published a paper in Science titled “Retinal degeneration associated with taurine deficiency in the cat.”
The abstract reports three findings. A degeneration of the retinal photoreceptor cells develops in cats when casein is the source of dietary protein. Amino acid profiles showed that the degeneration was associated with a selective decrease in plasma and retinal taurine. The authors related it to a sulfur amino acid deficit in the casein diet combined with the cat's specific amino acid requirements (Hayes and colleagues 1975).
A 1989 review by Hayes and Trautwein summarized the later picture in cats:
- Taurine deficiency occurs in a large number of cats fed unfortified commercial diets
- Cats cannot absorb all the taurine in processed diets and/or cannot synthesize enough to make up the deficit, which makes taurine an essential amino acid for cats
- Taurine-depleted cats develop retinal degeneration, cardiomyopathy, altered white-cell function, and abnormal growth and development
- Plasma taurine below 30 µmol/L is considered deficient
The experimental design details sometimes quoted for the 1975 study (numbers of diets, weeks to blindness, electroretinogram timing) are not given in its abstract.
The study did not by itself show that humans have the same dependency. Cats, unlike many mammals, depend heavily on dietary taurine (Hayes and Trautwein 1989).
Developments that followed:
- Commercial cat food came to be fortified with taurine (Hayes and Trautwein 1989)
- Taurine was added to many infant formulas during the 1980s “as a measure of prudence”, to match the margin of safety found in human milk (Gaull 1989)
- In 1987, Pion and colleagues linked low plasma taurine in cats to a reversible dilated cardiomyopathy
- Later work linked taurine depletion to the retinal toxicity of the drug vigabatrin in animals (Jammoul and colleagues 2009)
A 2014 review notes that, apart from its use in infant milk and parenteral nutrition, taurine has not been incorporated into any commercial treatment aimed at slowing photoreceptor degeneration (Froger and colleagues 2014).
Mechanisms of Photoreceptor Protection
The photoreceptor outer segment is exposed to a higher intensity of oxidative stress than almost any other cell in the body. Every photon absorbed by rhodopsin initiates a chemistry that produces reactive intermediates. Light energy itself drives photochemical reactions in the lipid-rich outer segment membranes, generating singlet oxygen, peroxyl radicals, and hydrogen peroxide. The mitochondria packed into the inner segments produce additional reactive oxygen species (ROS) as a byproduct of constant high-rate ATP synthesis.
The retina's antioxidant defenses include enzymatic systems (superoxide dismutase, catalase, glutathione peroxidase), small-molecule antioxidants (glutathione, ascorbate, α-tocopherol, the carotenoids lutein and zeaxanthin in the macula), and structural protection from melanin in the RPE. Taurine contributes to this defense in several ways:
- Direct hypochlorous acid scavenging. Taurine reacts with hypochlorous acid (HOCl) produced by activated immune cells in the retinal vasculature to form taurine chloramine, a much less toxic oxidant that itself has anti-inflammatory signaling properties. This protects retinal tissue from collateral damage during inflammatory responses to infection or injury.
- Membrane phospholipid stabilization. Taurine binds reversibly to phosphatidylcholine and phosphatidylethanolamine head groups in cellular membranes, reducing lipid peroxidation and stabilizing the membrane against oxidative damage. The disc membranes of photoreceptor outer segments are particularly rich in polyunsaturated fatty acids (especially DHA, the predominant fatty acid in retinal phospholipids) and therefore particularly vulnerable to peroxidation.
- Mitochondrial protection. Through its role in mitochondrial tRNA modification (forming 5-taurinomethyluridine, τm&sup5;U), taurine supports normal mitochondrial protein synthesis and electron transport chain function. Adequate taurine reduces electron leak from the ETC and lowers superoxide generation at the source. Taurine also inhibits mitochondrial permeability transition pore opening, preventing the catastrophic apoptotic cascade triggered by calcium overload or oxidative stress.
- Calcium modulation. Photoreceptor outer segments are exquisitely sensitive to intracellular calcium concentrations, which must be tightly regulated through the phototransduction cycle. Taurine modulates calcium handling in photoreceptors through effects on plasma membrane channels and intracellular calcium stores, preventing the calcium-driven cell death pathways that contribute to photoreceptor loss in various retinal degenerations.
- Osmotic stabilization. The retinal extracellular environment is osmotically stressed by the high metabolic activity of the tissue, with rapid local changes in ion concentrations as the dark and light currents shift. Taurine, as the principal organic osmolyte in retinal cells, defends cell volume against these osmotic swings.
The combined effect of these mechanisms is to provide the photoreceptor with an extraordinarily robust protective system that allows it to survive the metabolic intensity of constant light exposure for a human lifetime. When that system is compromised — by taurine deficiency, by aging, by drug exposure, by genetic mutation — the photoreceptors progressively succumb to oxidative damage and apoptotic cell death, producing the characteristic patterns of retinal degeneration.
Osmotic Regulation in Retinal Pigment Epithelium
The retinal pigment epithelium (RPE) is a single layer of cells separating the photoreceptors from the choroidal blood supply. Its functions include phagocytosis of shed photoreceptor outer segment tips, recycling of all-trans-retinal to 11-cis-retinal via the visual cycle, transport of nutrients from choroid to retina, ion transport (particularly maintenance of the subretinal space ion composition), and the blood-retina barrier function that separates immunologically privileged neural retina from circulating blood.
The RPE maintains extraordinary taurine concentrations both for its own metabolic needs and as the supplier of taurine to the photoreceptor layer. RPE cells express TauT at their basolateral membrane (facing the choroidal blood supply, importing taurine from circulation) and at their apical membrane (releasing taurine into the subretinal space for photoreceptor uptake).
The osmotic environment of the subretinal space is particularly demanding. During light adaptation, photoreceptor outer segment ion currents shift dramatically, producing local osmotic changes that the RPE must accommodate while maintaining its barrier function. Taurine, betaine, and myo-inositol serve as the principal compatible osmolytes that allow the RPE to defend cell volume through these shifts. Loss of any of these osmolytes — whether through deficient supply or genetic mutation — compromises RPE function and ultimately photoreceptor survival.
Declining RPE function is considered a major contributor to age-related macular degeneration (AMD, see below). Whether retinal taurine handling changes with age in people has not been established.
Calcium Handling in Photoreceptors
Photoreceptors maintain among the steepest calcium gradients in the body. The outer segment cytoplasm holds calcium at submicromolar concentrations during darkness, with the gradient maintained by the plasma membrane sodium-calcium-potassium exchanger (NCKX, the principal calcium extrusion mechanism in photoreceptors). During phototransduction, calcium concentrations drop further as cyclic GMP levels fall and the cation channels close.
This calcium signaling is essential for visual processing, but it also makes photoreceptors vulnerable to calcium dysregulation. Inappropriate calcium elevation in the outer segment activates calpain proteases and triggers apoptotic cascades that kill the photoreceptor. Many forms of inherited retinal degeneration involve mutations that disturb calcium handling, either directly (mutations in NCKX, calmodulin, or calcium-binding proteins) or indirectly (mutations in phototransduction components that lead to abnormal calcium loads).
Taurine modulates photoreceptor calcium handling at several levels:
- Stabilizing NCKX function through membrane phospholipid interactions
- Modulating L-type calcium channel activity in the inner segment (where calcium-dependent neurotransmitter release occurs at the photoreceptor synaptic terminal)
- Inhibiting mitochondrial permeability transition pore opening, preventing the calcium-driven apoptotic cascade
- Supporting ATP production needed to drive the calcium pumps that maintain low cytoplasmic calcium
The protective effects of taurine on photoreceptor calcium handling are particularly relevant in retinitis pigmentosa, where many of the disease-causing mutations create dysregulated calcium states in the outer segment.
Mitochondrial Function in the Retina
Photoreceptor inner segments are densely packed with mitochondria, which produce the ATP needed for the dark current and phototransduction. Mitochondrial diseases such as Leber hereditary optic neuropathy, MELAS, and Kearns-Sayre syndrome can cause visual loss.
Taurine is built into two modified uridines of human mitochondrial tRNAs, and these modifications are missing in mutant tRNAs from cells of patients with the mitochondrial diseases MELAS and MERRF (Suzuki and colleagues 2002). Whether a shortage of dietary taurine impairs mitochondria in human photoreceptors has not been shown.
Photoreceptors do not divide and are not replaced, so photoreceptors lost to any cause do not return.
Age-Related Macular Degeneration and Taurine
Age-related macular degeneration (AMD) is the leading cause of irreversible vision loss in adults over 60 in the developed world. The disease involves progressive degeneration of the macula — the central retina responsible for high-acuity central vision — through a complex pathology involving RPE dysfunction, drusen accumulation (subretinal deposits of lipid, protein, and oxidative damage products), choroidal vascular changes, and ultimately photoreceptor loss.
The pathogenesis of AMD involves multiple converging factors:
- Chronic oxidative stress in the macula (driven by light exposure, mitochondrial activity, and inflammation)
- RPE dysfunction and lipofuscin accumulation
- Inflammation (the complement pathway, particularly factor H polymorphisms, plays a major role in genetic susceptibility)
- Choroidal vascular changes (reduced choroidal blood flow with aging)
- Genetic predisposition (CFH and ARMS2 polymorphisms are the strongest risk factors)
- Modifiable risk factors: smoking, hypertension, obesity, diet poor in antioxidants and omega-3s
The AREDS (Age-Related Eye Disease Study) and AREDS2 trials tested supplements containing vitamins C and E, zinc, copper and, in AREDS2, lutein and zeaxanthin, for the progression of AMD. Neither formula included taurine.
The case made for taurine in AMD is mechanistic rather than trial-based:
- A 2023 study reported that circulating taurine declines with age in mice, monkeys, and humans (Singh and colleagues 2023), but a 2025 study found that it increased or stayed the same with age in three human cohorts (Fernandez and colleagues 2025); age-related changes in retinal taurine in people have not been established
- Taurine's photoprotective, calcium-modulating, mitochondrial-supporting, and membrane-stabilizing functions all address mechanisms implicated in AMD pathogenesis
- Taurine's antioxidant properties may influence retinal disease processes (Froger and colleagues 2014)
No large randomized trial has tested taurine for AMD progression.
Retinitis Pigmentosa
Retinitis pigmentosa (RP) is a heterogeneous group of inherited retinal degenerations characterized by progressive death of rod photoreceptors (causing night blindness as the first symptom), followed by cone degeneration (causing loss of peripheral and then central vision). It can result from mutations in many different genes.
Taurine was considered for retinal degenerations from the 1970s onward because cats on a taurine-free diet lost photoreceptors (Froger and colleagues 2014).
No controlled trial of taurine in RP is cited in the reviews on this page. Gene therapy is available for one genetic form (voretigene neparvovec, for RPE65-related disease).
The 2014 review argues that taurine, along with other antioxidant molecules, should be reconsidered as a potential treatment for retinal diseases, but this is a research proposal rather than an established therapy (Froger and colleagues 2014).
Vigabatrin-Associated Retinopathy
Vigabatrin is an antiepileptic medication that inhibits GABA transaminase, raising GABA levels in the nervous system. It remains a potent therapy for infantile spasms and a third-line drug for refractory epilepsies, but it irreversibly constricts the visual field (Jammoul and colleagues 2009).
In rats and mice treated with vigabatrin, the retinal lesions were prevented by keeping the animals in darkness, and plasma taurine was 67% lower than in untreated animals. Among six vigabatrin-treated infants, plasma taurine was below normal in three and undetectable in two. The authors concluded that vigabatrin generates a taurine deficiency responsible for its retinal phototoxicity (Jammoul and colleagues 2009).
Taurine supplementation reduced all components of the retinal lesions in rats and mice (Jammoul and colleagues 2009), and in neonatal rats treated from postnatal days 4 to 29 it partially prevented cone damage and the loss of retinal ganglion cells (Jammoul and colleagues 2010). These are animal results. The 2009 paper discloses that patents were filed on the results and that the work received drug-company funding.
What the researchers proposed:
- Future studies to test whether taurine co-treatment can limit seizures without constricting the visual field (Jammoul and colleagues 2009)
- That patients taking vigabatrin could gain immediate benefit from reduced light exposure and from dietary advice on taurine-rich foods (Jammoul and colleagues 2009)
- That taurine supplementation be given with vigabatrin for infantile spasms or epilepsy, a conclusion drawn from the neonatal-rat study (Jammoul and colleagues 2010)
Whether taurine co-treatment protects vision in people taking vigabatrin has not been tested in a published randomized trial cited by these reviews. The visual field loss vigabatrin causes is irreversible (Jammoul and colleagues 2010).
Diabetic Retinopathy
Diabetic retinopathy is a major cause of vision loss in working-age adults. It involves high-glucose damage to the small blood vessels of the retina, oxidative stress, and inflammation, leading to ischemia, abnormal new vessels, macular edema, and bleeding.
The evidence connecting taurine to diabetic retinopathy:
- Low plasma taurine concentrations have been observed in diabetic patients, and disturbed retinal blood flow may reduce taurine uptake by the retina (Froger and colleagues 2014)
- In diabetic rats, a diet with 1.2% taurine for 4 to 12 weeks improved retinal tissue changes and raised retinal taurine without lowering plasma glucose (Yu and colleagues 2008)
- A 2012 review reports protective effects of taurine against diabetic complications, including retinopathy, in several animal models (Ito and colleagues 2012)
These are animal and observational findings; no randomized trial of taurine for diabetic retinopathy in people is cited in these reviews.
Infant Formula and the Pediatric Story
Newborn mammals have a limited ability to synthesize taurine and rely on dietary supply (Lambert and colleagues 2015). A 2002 overview describes taurine as essential for preterm newborns, with breast milk as their source (Lourenço and Camilo 2002).
A 1984 analysis measured an average of 458 mg of taurine per kg of dry matter in human milk, 68 mg/kg in cow's milk, and 38 mg/kg in the 24 milk-based infant formulas tested (Erbersdobler and colleagues 1984).
In infant rhesus monkeys, a taurine-free, soy-protein-based infant formula fed from birth led to significantly impaired visual acuity, with changes in the photoreceptors, compared with the same formula with taurine added (Neuringer and Sturman 1987).
In people, the 1989 Pediatrics review cited these findings as justification for adding taurine to infant formula (Gaull 1989):
- Improved fat absorption in preterm infants and in children with cystic fibrosis given taurine
- Effects on auditory brainstem-evoked responses in preterm infants
Taurine is now added to many infant formulas “as a measure of prudence” to provide the same margin of safety as human milk (Gaull 1989).
In children on long-term parenteral nutrition without taurine, plasma taurine was low and electroretinograms were abnormal in all eight children examined; adding taurine to the intravenous solutions restored plasma levels in four children and normalized the electroretinograms of three, and the authors concluded that children, and possibly adults, on long-term parenteral nutrition have a nutritional requirement for taurine (Geggel and colleagues 1985). A 2002 overview states that further studies are required to decide whether to include taurine routinely in parenteral nutrition regimens (Lourenço and Camilo 2002).
Doses Used in Eye Research
- Parenteral nutrition: taurine added to intravenous nutrition solutions in children (Geggel and colleagues 1985); the oral dose was not the subject of that study.
- Vigabatrin: taurine supplementation was tested in rats and mice, not in a published human trial (Jammoul and colleagues 2009, 2010).
- Diabetic retinopathy: a 1.2% taurine diet in rats (Yu and colleagues 2008).
- AMD and retinitis pigmentosa: no trial dose has been established.
No oral dose of taurine has been established for any eye condition in people. The research doses above describe studies, not recommendations.
The AREDS formulas studied for AMD did not include taurine.
Safety Findings
- Research stage. For AMD, retinitis pigmentosa, and diabetic retinopathy, taurine is a research topic, not an established treatment (Froger and colleagues 2014).
- Vigabatrin. The taurine findings come from animal studies; the drug's visual field loss is irreversible (Jammoul and colleagues 2009, 2010).
- General safety. A 2008 risk assessment found strong evidence for the absence of adverse effects in normal healthy adults at supplemental intakes up to 3 g/day (Shao and Hathcock 2008); it does not address children, pregnancy, or people with kidney disease. Decisions about supplements belong with a clinician.
Key Research Papers
- Hayes KC, Carey RE, Schmidt SY. Retinal degeneration associated with taurine deficiency in the cat. Science. 1975;188(4191):949-51. — doi:10.1126/science.1138364 · PubMed PMID: 1138364
- Sturman JA. Taurine in development. Physiological Reviews. 1993;73(1):119-47. — doi:10.1152/physrev.1993.73.1.119 · PubMed PMID: 8419963
- Ripps H, Shen W. Review: taurine: a "very essential" amino acid. Molecular Vision. 2012;18:2673-86. — PubMed PMID: 23170060
- Froger N, Cadetti L, Lorach H, Martins J, Bemelmans AP, Dubus E, et al. Taurine provides neuroprotection against retinal ganglion cell degeneration. PLOS ONE. 2012;7(10):e42017. — doi:10.1371/journal.pone.0042017 · PubMed PMID: 23115615
- Jammoul F, Wang Q, Nabbout R, Coriat C, Duboc A, Simonutti M, et al. Taurine deficiency is a cause of vigabatrin-induced retinal phototoxicity. Annals of Neurology. 2009;65(1):98-107. — doi:10.1002/ana.21526 · PubMed PMID: 19194884
- Jammoul F, Dégardin J, Pain D, Gondouin P, Simonutti M, Dubus E, et al. Taurine deficiency damages photoreceptors and retinal ganglion cells in vigabatrin-treated neonatal rats. Molecular and Cellular Neurosciences. 2010;43(4):414-21. — doi:10.1016/j.mcn.2010.01.008 · PubMed PMID: 20132888
- Heller-Stilb B, van Roeyen C, Rascher K, Hartwig HG, Huth A, Seeliger MW, et al. Disruption of the taurine transporter gene (taut) leads to retinal degeneration in mice. FASEB Journal. 2002;16(2):231-3. — doi:10.1096/fj.01-0691fje · PubMed PMID: 11772953
- Lima L, Obregon F, Cubillos S, Fazzino F, Jaimes I. Taurine as a micronutrient in development and regeneration of the central nervous system. Nutritional Neuroscience. 2001;4(6):439-43. — doi:10.1080/1028415x.2001.11747379 · PubMed PMID: 11843263
- Yu X, Xu Z, Mi M, Xu H, Zhu J, Wei N, et al. Dietary taurine supplementation ameliorates diabetic retinopathy via anti-excitotoxicity of glutamate in streptozotocin-induced Sprague-Dawley rats. Neurochemical Research. 2008;33(3):500-7. — doi:10.1007/s11064-007-9465-z · PubMed PMID: 17762918
- Macaione S, Ruggeri P, De Luca F, Tucci G. Free amino acids in developing rat retina. Journal of Neurochemistry. 1974;22(6):887-91. — doi:10.1111/j.1471-4159.1974.tb04313.x · PubMed PMID: 4852089
- Pasantes-Morales H, Klethi J, Ledig M, Mandel P. Free amino acids of chicken and rat retina. Brain Research. 1972;41(2):494-7. — doi:10.1016/0006-8993(72)90523-9 · PubMed PMID: 5038343
- Geggel HS, Ament ME, Heckenlively JR, Martin DA, Kopple JD. Nutritional requirement for taurine in patients receiving long-term parenteral nutrition. New England Journal of Medicine. 1985;312(3):142-6. — doi:10.1056/NEJM198501173120302 · PubMed PMID: 3917547
- Froger N, Moutsimilli L, Cadetti L, Jammoul F, Wang QP, Fan Y, et al. Taurine: the comeback of a neutraceutical in the prevention of retinal degenerations. Progress in Retinal and Eye Research. 2014;41:44-63. — doi:10.1016/j.preteyeres.2014.03.001 · PubMed PMID: 24721186
- Hayes KC, Trautwein EA. Taurine deficiency syndrome in cats. Veterinary Clinics of North America. Small Animal Practice. 1989;19(3):403-13. — doi:10.1016/s0195-5616(89)50052-4 · PubMed PMID: 2658282
- Gaull GE. Taurine in pediatric nutrition: review and update. Pediatrics. 1989;83(3):433-42. — PubMed PMID: 2645571
- Lourenço R, Camilo ME. Taurine: a conditionally essential amino acid in humans? An overview in health and disease. Nutrición Hospitalaria. 2002;17(6):262-70. — PubMed PMID: 12514918
- Neuringer M, Sturman J. Visual acuity loss in rhesus monkey infants fed a taurine-free human infant formula. Journal of Neuroscience Research. 1987;18(4):597-601. — doi:10.1002/jnr.490180413 · PubMed PMID: 3437473
- Erbersdobler HF, Trautwein E, Greulich HG. Determinations of taurine in milk and infant formula diets. European Journal of Pediatrics. 1984;142(2):133-4. — doi:10.1007/BF00445594 · PubMed PMID: 6332023
- Han X, Patters AB, Jones DP, Zelikovic I, Chesney RW. The taurine transporter: mechanisms of regulation. Acta Physiologica. 2006;187(1-2):61-73. — doi:10.1111/j.1748-1716.2006.01573.x · PubMed PMID: 16734743
- Suzuki T, Suzuki T, Wada T, Saigo K, Watanabe K. Taurine as a constituent of mitochondrial tRNAs: new insights into the functions of taurine and human mitochondrial diseases. EMBO Journal. 2002;21(23):6581-9. — doi:10.1093/emboj/cdf656 · PubMed PMID: 12456664
- Schaffer SW, Jong CJ, Ramila KC, Azuma J. Physiological roles of taurine in heart and muscle. Journal of Biomedical Science. 2010;17 Suppl 1(Suppl 1):S2. — doi:10.1186/1423-0127-17-S1-S2 · PubMed PMID: 20804594
- Lambert IH, Kristensen DM, Holm JB, Mortensen OH. Physiological role of taurine--from organism to organelle. Acta Physiologica. 2015;213(1):191-212. — doi:10.1111/apha.12365 · PubMed PMID: 25142161
- Ito T, Schaffer SW, Azuma J. The potential usefulness of taurine on diabetes mellitus and its complications. Amino Acids. 2012;42(5):1529-39. — doi:10.1007/s00726-011-0883-5 · PubMed PMID: 21437784
- Singh P, Gollapalli K, Mangiola S, Schranner D, Yusuf MA, Chamoli M, et al. Taurine deficiency as a driver of aging. Science. 2023;380(6649):eabn9257. — doi:10.1126/science.abn9257 · PubMed PMID: 37289866
- Fernandez ME, Bernier M, Price NL, Camandola S, Aon MA, Vaughan K, et al. Is taurine an aging biomarker? Science. 2025;388(6751):eadl2116. — doi:10.1126/science.adl2116 · PubMed PMID: 40472098
- Shao A, Hathcock JN. Risk assessment for the amino acids taurine, L-glutamine and L-arginine. Regulatory Toxicology and Pharmacology. 2008;50(3):376-99. — doi:10.1016/j.yrtph.2008.01.004 · PubMed PMID: 18325648
PubMed Topic Searches
- PubMed: Taurine and retinal photoreceptors
- PubMed: Taurine and age-related macular degeneration
- PubMed: Taurine and vigabatrin retinopathy
- PubMed: Taurine and retinitis pigmentosa
- PubMed: Taurine and diabetic retinopathy
- PubMed: Taurine in infant formula
- PubMed: TauT knockout and retinal degeneration
Connections
- All Amino Acids
- Taurine Overview
- Taurine Benefits Hub
- Taurine for Cardiac Function
- Taurine for Bile Acids
- Taurine for Electrolyte Balance
- Vitamin A (Retinal Substrate)
- Vitamin A for Vision
- Macular Degeneration
- Diabetes
- Omega-3 Fatty Acids (DHA)
- Zinc
- Vitamin E
- Cysteine (Taurine Precursor)
- Vitamin B6 (P5P)
- Calcium — the ion whose influx taurine modulates inside photoreceptors.
- History
- Sources