⚠ Evidence warning: Clinical trials or other evidence do not support the claims that sublingual L-glutamine ends sugar and alcohol cravings within minutes, steadies blood sugar and protects muscle during dieting. This page keeps it as a report of what people, websites or other media say.
Glutamine for Weight Loss Support
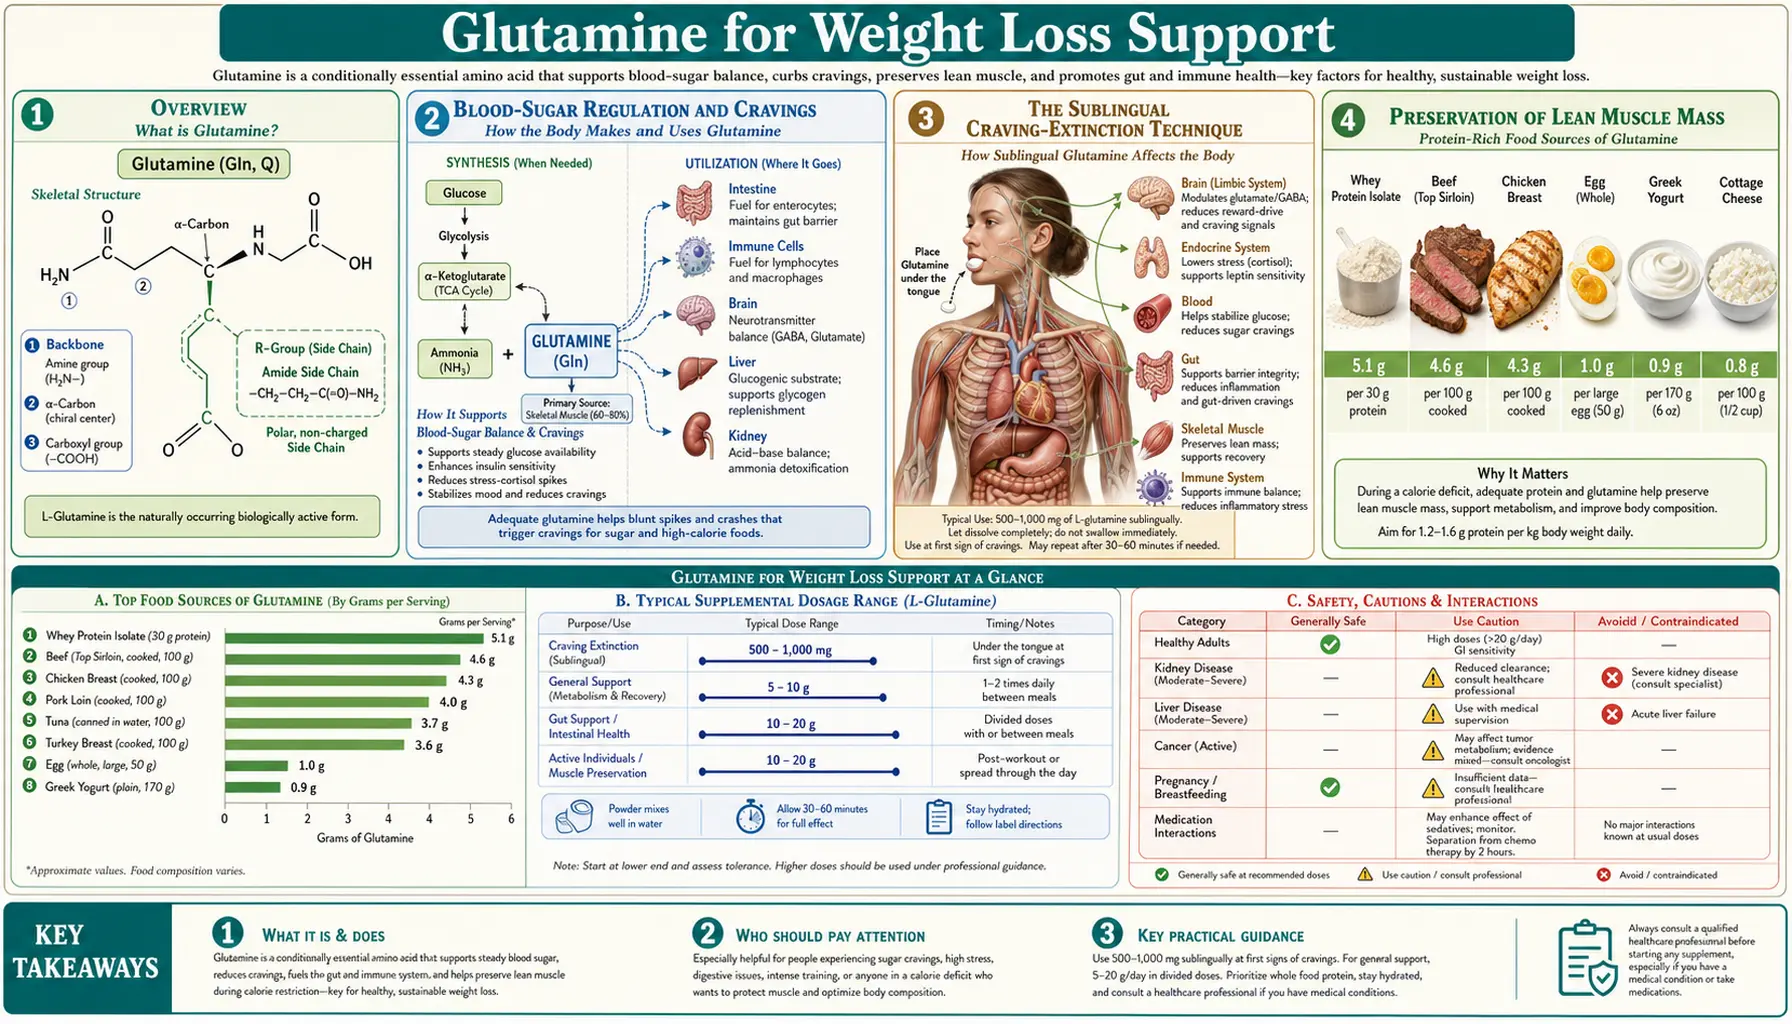
L-glutamine is not a weight-loss drug, a stimulant, or an appetite suppressant. It is a conditionally essential amino acid that supports several underlying physiological processes that, when optimized, make it meaningfully easier to lose fat and sustain a healthy body composition: blood-sugar stabilization, sugar and alcohol craving extinction, preservation of lean muscle during calorie restriction, glucagon-like peptide-1 (GLP-1) augmentation, and favorable shifts in the gut microbiota that reduce metabolic endotoxemia. The most striking single intervention is the sublingual technique — 1-2 grams dissolved under the tongue at the onset of a craving, with relief arriving within minutes via direct gluconeogenic glucose supply to the brain — but the broader story includes the Laviano 2014 pilot trial in nondieting obese women, the de Souza 2015 gut-microbiota shift in overweight adults, and the Greenfield 2009 glucagon-like peptide-1 augmentation finding in lean, obese, and type 2 diabetic subjects.
Table of Contents
- Overview
- Blood-Sugar Regulation and Cravings
- The Sublingual Craving-Extinction Technique
- Preservation of Lean Muscle Mass
- Gut Microbiome and Metabolic Endotoxemia
- Glucagon-Like Peptide-1 Augmentation and Insulin Sensitivity
- Reducing Chronic Inflammation
- Benefits for a Sedentary Lifestyle
- Doses Naturopathic Practitioners Describe for Weight Management
- Combining Glutamine with Other Strategies
- Limitations and Realistic Expectations
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Overview
L-glutamine is not a weight-loss drug, a stimulant, or an appetite suppressant in the pharmacological sense. It is a conditionally essential amino acid that supports several underlying physiological processes that, when optimized, make it meaningfully easier to lose fat and sustain a healthy body composition. Unlike typical "fat burners," the effects of glutamine on body weight are upstream and foundational, improving the biochemical environment in which fat loss can occur.
Naturopathic practitioners often include glutamine in weight loss protocols not because it forces fat to burn faster, but because it addresses four of the most common obstacles to successful weight management: blood-sugar instability, chronic cravings, loss of lean tissue during calorie restriction, and the low-grade inflammation driven by a compromised gut barrier.
Blood-Sugar Regulation and Cravings
Perhaps the most practical benefit of glutamine during a weight-loss effort is its ability to stabilize blood sugar and diminish cravings. The brain requires a constant supply of glucose, and when blood sugar drops even briefly, it generates urgent cravings for sugar, refined carbohydrates, or alcohol. These cravings are among the most common reasons that people abandon an otherwise successful eating plan.
L-glutamine is a preferred substrate for gluconeogenesis, the process by which the liver and kidneys produce glucose from non-carbohydrate precursors. By feeding this pathway, glutamine helps maintain steady blood glucose between meals and during fasting windows. The result is a noticeable reduction in the intensity and frequency of cravings, which in turn makes it easier to adhere to caloric reductions or intermittent-fasting protocols.
The Sublingual Craving-Extinction Technique
A well-known clinical technique is to dissolve 1 to 2 grams of L-glutamine powder directly under the tongue at the onset of a sugar or alcohol craving. Because sublingual absorption bypasses the digestive system, the amino acid reaches the bloodstream within minutes, often extinguishing the craving before it can drive a behavioral lapse.
The relationship between glutamine and alcohol cravings was first explored in the 1950s by researcher Roger Williams at the University of Texas, who observed that glutamine supplementation reduced voluntary alcohol consumption in animal studies. Subsequent clinical observations have supported this finding, with many practitioners reporting that patients in recovery from alcohol dependence experience reduced cravings and improved mood stability when taking glutamine.
The mechanism is straightforward: the brain is highly glucose-dependent, and acute drops in blood glucose are interpreted as urgent fuel-shortage signals that drive craving behavior. By supplying the brain with a rapid-onset gluconeogenic substrate, sublingual glutamine effectively communicates "fuel has arrived" within minutes, eliminating the physiological driver of the craving even when the underlying caloric pattern hasn't changed.
Preservation of Lean Muscle Mass
One of the most overlooked problems with traditional dieting is that roughly 20 to 30 percent of weight lost through calorie restriction alone comes from lean body mass rather than fat. Since muscle is several times more metabolically active than fat, losing muscle during weight loss progressively slows the resting metabolic rate. This explains why many dieters find it harder and harder to keep losing weight and why they regain it so easily when they return to normal eating.
Glutamine helps prevent this by supplying nitrogen and fuel to the immune system, gut, and kidneys — tissues that would otherwise draw on skeletal muscle glutamine stores during periods of stress or reduced intake. By sparing muscle protein from catabolism, glutamine helps preserve basal metabolic rate, maintain physical strength during weight loss, and improve the ratio of fat lost to lean mass lost.
For individuals combining calorie restriction with resistance training, the muscle-preserving effect is especially valuable. Practitioners describe a dose of 5 to 10 grams daily, split between morning and post-workout, as background support for nitrogen balance without noticeably adding calories to the diet.
Gut Microbiome and Metabolic Endotoxemia
Over the last fifteen years, research has revealed a tight bidirectional link between the composition of the gut microbiota and host metabolism. Obese individuals consistently show altered gut flora, elevated circulating bacterial endotoxins called lipopolysaccharides (LPS), and increased intestinal permeability. This "metabolic endotoxemia" drives chronic low-grade inflammation, insulin resistance, and fat accumulation around the abdominal organs.
Glutamine intervenes in this process on two levels. First, by repairing tight junctions and nourishing enterocytes (covered in detail in the companion Gut Health & Leaky Gut page), it reduces the translocation of lipopolysaccharide from the gut into systemic circulation, directly lowering the endotoxin load. Second, small clinical studies have shown that oral glutamine supplementation can favorably shift the balance of gut bacteria, including a reduction in the Firmicutes-to-Bacteroidetes ratio — a pattern commonly associated with leaner body composition.
De Souza and colleagues (2015) reported that 14 days of oral glutamine at 30 g/day, compared with 30 g/day of the amino acid alanine, measurably changed the gut microbiota of 33 overweight and obese adults. The Firmicutes-to-Bacteroidetes ratio fell from 0.85 to 0.57 on glutamine and rose from 0.91 to 1.12 on alanine, a change the authors said resembled weight loss programs. While the research is still early, the mechanistic case for glutamine as a gut-mediated metabolic-support nutrient is becoming increasingly strong.
The same research group also tested people directly. Abboud and colleagues (2019) gave 39 overweight or obese volunteers 30 g of glutamine or alanine for 14 days. Glutamine lowered waist size and blood lipopolysaccharide, and the two falls were linked. The authors write that longer human studies are needed before glutamine is prescribed as a treatment for overweight and obesity.
Glucagon-Like Peptide-1 Augmentation and Insulin Sensitivity
One of the more intriguing recent findings is that oral glutamine directly augments the release of glucagon-like peptide 1 from intestinal L-cells. Greenfield and colleagues (2009) demonstrated that a single 30 g oral dose of glutamine increased circulating glucagon-like peptide-1, glucagon, and insulin concentrations in lean, obese, and type 2 diabetic subjects alike. In those 24 people, glucagon-like peptide-1 peaked at 22.5, 17.9 and 17.3 pmol/L in the lean, obese non-diabetic and obese diabetic or glucose-intolerant groups, against 31.9, 24.3 and 19.5 pmol/L after 75 g of glucose. Glucagon rose too. This is the same incretin pathway exploited by the now-popular semaglutide and tirzepatide drugs — not the same magnitude of effect, but a clear mechanistic overlap.
The Samocha-Bonet 2011 follow-up confirmed that oral glutamine reduces postprandial glycemia and augments the glucagon-like peptide-1 response specifically in type 2 diabetes patients, and the Mansour 2015 trial (30 g/day for 6 weeks, 53 people with type 2 diabetes completing) reported lower body fat and waist size, lower fasting glucose and a significant difference in hemoglobin A1c, with no change in body weight, body mass index, total, HDL or LDL cholesterol, triglycerides or C-reactive protein. The Abboud 2019 study covered both rats and people. In diet-induced obese Wistar rats, oral glutamine reduced body fat and improved insulin action across the body, while leading to insulin resistance specifically in fat tissue. In overweight and obese volunteers it lowered waist size, and lowered serum insulin in the obese group only. The paper's title also reports lower pro-inflammatory markers.
A single-meal study by Iwashita and colleagues (2006) gave 10 healthy young adults a mixed meal containing either glutamine or an amino acid mix of equal calories. Energy burned after the meal was 49% greater with glutamine, and fat burning was higher by about 42 kcal in the late phase after the meal. This single-meal study reports no effect on body weight, which it did not set out to measure.
On insulin sensitivity itself, the human trials on this page give a mixed picture. Mansour found no significant difference in fasting insulin, homeostasis-model insulin resistance or the quantitative insulin sensitivity index; the 20% fall in insulin and insulin resistance in the Laviano pilot was not statistically significant; and Abboud found lower serum insulin only in the obese group. The mechanism remains under investigation. Proposed pathways include reduced inflammation, improved glucagon-like peptide-1 secretion from intestinal L-cells, and better maintenance of pancreatic beta-cell function. Improved insulin sensitivity means the body is able to store glucose as muscle glycogen rather than fat, and fat cells become more willing to release stored fuel for energy.
Reducing Chronic Inflammation
Chronic low-grade inflammation is now recognized as one of the central drivers of metabolic dysfunction. Elevated inflammatory cytokines interfere with insulin signaling, disrupt satiety hormones such as leptin, and promote fat storage particularly in visceral depots. Anything that reduces background inflammation without pharmaceutical intervention tends to improve the metabolic environment for fat loss.
Glutamine contributes several anti-inflammatory actions: it nourishes the gut barrier (reducing endotoxin-driven inflammation), induces protective heat-shock proteins, and serves as a precursor to glutathione, the body's most powerful endogenous antioxidant. Together these effects lower the inflammatory background load and support healthier insulin signaling.
Benefits for a Sedentary Lifestyle
Most weight-loss research is conducted on either athletes or clinical patients, leaving a gap when it comes to the needs of sedentary office workers, drivers, remote employees, and older adults who cannot easily exercise. This group often experiences slow, age-related muscle loss (sarcopenia), declining metabolism, and a chronic drain on glutamine reserves from psychological stress and sub-optimal diet.
For sedentary individuals attempting weight loss, a modest daily glutamine dose of 2 to 5 grams offers several advantages: it helps preserve the muscle that exists, supports gut and immune function, curbs cravings, and provides biochemical support for the kind of metabolic resilience that sedentary lifestyles steadily erode.
Doses Naturopathic Practitioners Describe for Weight Management
Dosing
These figures come from naturopathic practice, except where a trial is named.
- General weight-management support: 5 grams of powdered L-glutamine once or twice daily, taken on an empty stomach
- Craving management: 1 to 2 grams dissolved under the tongue at onset of a craving (up to 3 times daily)
- Muscle preservation during calorie restriction: 5 grams in the morning and 5 grams after any physical activity
- Gut-microbiota shift: practitioners describe 30 g/day in divided doses for 30 days, then a taper to a maintenance 5-10 g/day; the de Souza trial itself gave 30 g/day for 14 days, with no taper or maintenance phase in its abstract
Timing
Practitioners name morning, between meals, before bed, and the onset of a craving as the most effective times. They also describe keeping it out of hot beverages and taking it on an empty stomach whenever possible for best absorption.
Duration
In naturopathic practice, 8 to 16 weeks of consistent daily use for weight management is typical, often continued as a low-dose maintenance protocol beyond that point.
Combining Glutamine with Other Strategies
Glutamine is most effective when it is part of a comprehensive approach to weight management rather than a stand-alone tactic. Foundational elements include:
- A whole-foods diet built around lean protein, colorful vegetables, healthy fats, and minimal refined sugar
- Consistent resistance training at least two or three times per week to stimulate muscle maintenance
- Adequate sleep (7 to 9 hours), since sleep deprivation sabotages leptin, ghrelin, and insulin signaling
- Stress management through meditation, breathwork, or time outdoors, to reduce cortisol-driven abdominal fat deposition
- Hydration and electrolyte balance, particularly for those using intermittent fasting
- Complementary supplements such as berberine, magnesium, omega-3 fatty acids, and probiotics
Limitations and Realistic Expectations
L-glutamine is not a substitute for dietary change, physical activity, or stress management. Large randomized trials have not established it as an independent weight-loss drug, and the existing clinical studies that do show benefits generally involve relatively small populations. What glutamine does well is remove biochemical obstacles, reduce cravings, protect lean tissue, and support gut and immune health in ways that make it easier to sustain the lifestyle changes that actually produce lasting fat loss.
The human trials behind this page are small and short. The Laviano 2014 pilot had 6 women on 0.5 g/kg/day for 4 weeks; weight went from 85.0 to 82.2 kg and waist from 102.7 to 98.9 cm. De Souza 2015 had 33 adults for 14 days. Mansour 2015 had 53 people completing 6 weeks, with no change in body weight or body mass index. The human studies cited here used 15 to 30 g of glutamine or 0.5 g/kg/day, while most of the practitioner doses on this page are 1 to 10 g, so those lower doses are not what these trials tested.
Think of glutamine as a supportive nutrient that optimizes the environment for weight loss rather than a direct fat-burning agent. For most people, the benefits are real but subtle, and they accumulate over weeks rather than days.
Cautions
- Liver disease / hepatic encephalopathy — ammonia clearance is impaired. A 2022 review of amino acid supplements states that most glutamine taken is used to form ammonia, so raised intake may cause harm in people with high blood ammonia, such as those with liver disease or urea cycle disorders. In 238 people with cirrhosis, an oral glutamine dose was given as a test of ammonia handling: those with high ammonia beforehand and a large rise after the dose had a much higher risk of hepatic encephalopathy, a brain disturbance of liver disease (subhazard ratio 4.67, 95% CI 2.19-9.98).
- Severe kidney disease — the 2022 review reports that raised glutamine intake, especially by vein, substantially increases kidney filtration, kidney blood flow and ammonia production in the kidneys, and calls high doses inappropriate where there is no glutamine deficiency, especially in older people and people with liver or kidney impairment.
- Active cancer — some tumor cells exhibit "glutamine addiction". The 2022 review describes tumor cells using glutamine much faster than normal cells and a risk that more glutamine could promote tumor growth, also notes animal studies with no effect on tumor weight, and states that research is needed on whether glutamine supplements are safe for people with cancer.
- Seizure disorders — glutamine converts to glutamate; practitioners describe starting at low doses.
- Glucagon-like peptide-1 receptor agonist users (semaglutide, tirzepatide, liraglutide) — given that oral glutamine augments endogenous glucagon-like peptide-1, theoretically additive effects on appetite and gastric emptying are possible. This is a theoretical concern.
- Long-term and high-dose use in general — the 2022 review states that higher intake of most amino acid supplements, glutamine included, "may not be risk-free", and that the effects of high doses and long-term use still need research, including in older people, children, pregnancy, nursing, diabetes and liver disease. It also reports that glutamine supplementation shows no signs of toxicity or mutagenic activity.
Key Research Papers
- Laviano A, Molfino A, Lacaria MT, Canelli A, De Leo S, Preziosa I, Rossi Fanelli F (2014). Glutamine supplementation favors weight loss in nondieting obese female patients: A pilot study. European Journal of Clinical Nutrition. — PubMed PMID: 25226827
- de Souza AZ, Zambom AZ, Abboud KY et al. (2015). Oral supplementation with L-glutamine alters gut microbiota of obese and overweight adults. Nutrition. — PubMed PMID: 25933498
- Greenfield JR et al. (2009). Oral glutamine increases circulating glucagon-like peptide 1, glucagon, and insulin concentrations in lean, obese, and type 2 diabetic subjects. American Journal of Clinical Nutrition. — PubMed PMID: 19056578
- Mansour A, Mohajeri-Tehrani MR, Qorbani M, Heshmat R, Larijani B, Hosseini S (2015). Effect of glutamine supplementation on cardiovascular risk factors in patients with type 2 diabetes. Nutrition. — PubMed PMID: 25466655
- Samocha-Bonet D, Wong O, Synnott EL et al. (2011). Glutamine reduces postprandial glycemia and augments the glucagon-like peptide-1 response in type 2 diabetes patients. Journal of Nutrition. — PubMed PMID: 21593352
- Abboud KY et al. (2019). Oral Glutamine Supplementation Reduces Obesity, Pro-Inflammatory Markers, and Improves Insulin Sensitivity in DIO Wistar Rats and Reduces Waist Circumference in Overweight and Obese Humans. Nutrients. 11(3):536. — PubMed PMID: 30832230
- Williams RJ (1959). Alcoholism: The Nutritional Approach. Foundational observation that glutamine reduces voluntary alcohol consumption.
- Rogers LL, Pelton RB, Williams RJ (1955). Voluntary alcohol consumption by rats following administration of glutamine. Journal of Biological Chemistry. 214(2):503-6. — PubMed PMID: 14381386
- Rogers LL, Pelton RB (1957). Glutamine in the treatment of alcoholism; a preliminary report. Quarterly Journal of Studies on Alcohol. 18(4):581-7. — PubMed PMID: 13506018
- Iwashita S, Mikus C, Baier S, Flakoll PJ (2006). Glutamine supplementation increases postprandial energy expenditure and fat oxidation in humans. JPEN Journal of Parenteral and Enteral Nutrition. 30(2):76-80. — PubMed PMID: 16517950
- Reimann F, Tolhurst G, Gribble FM (2012). G-protein-coupled receptors in intestinal chemosensation. Cell Metabolism. 15(4):421-31. — PubMed PMID: 22482725
- Cruzat V et al. (2018). Glutamine: Metabolism and Immune Function, Supplementation and Clinical Translation. Nutrients. — PubMed PMID: 30360490
- Ampuero J, Gil A, Viloria MDM, Rico MC, Millán R, Camacho I, Romero-Gómez M (2020). Oral glutamine challenge is a marker of altered ammonia metabolism and predicts the risk of hepatic encephalopathy. Liver International. 40(4):921-930. — PubMed PMID: 31729816
- Holecek M (2022). Side effects of amino acid supplements. Physiological Research. 71(1):29-45. — PubMed PMID: 35043647
PubMed Topic Searches
Connections
- All Amino Acids
- Glutamine Overview
- Glutamine Benefits Hub
- Glutamine for Gut Health & Leaky Gut
- Glutamine for Immune Function
- Glutamine for Exercise Recovery
- Leucine
- Arginine
- Glycine
- Blood Sugar
- Gut-Brain Axis
- Fasting
- Stress Management
- Glucagon-Like Peptide-1 Receptor Agonists
- Insulin Resistance
- Diabetes
- Obesity
- Metabolic Syndrome
- Berberine
- Magnesium
- Gut Microbiome
- CGM
- History
- Sources