Glutamine for Exercise Recovery
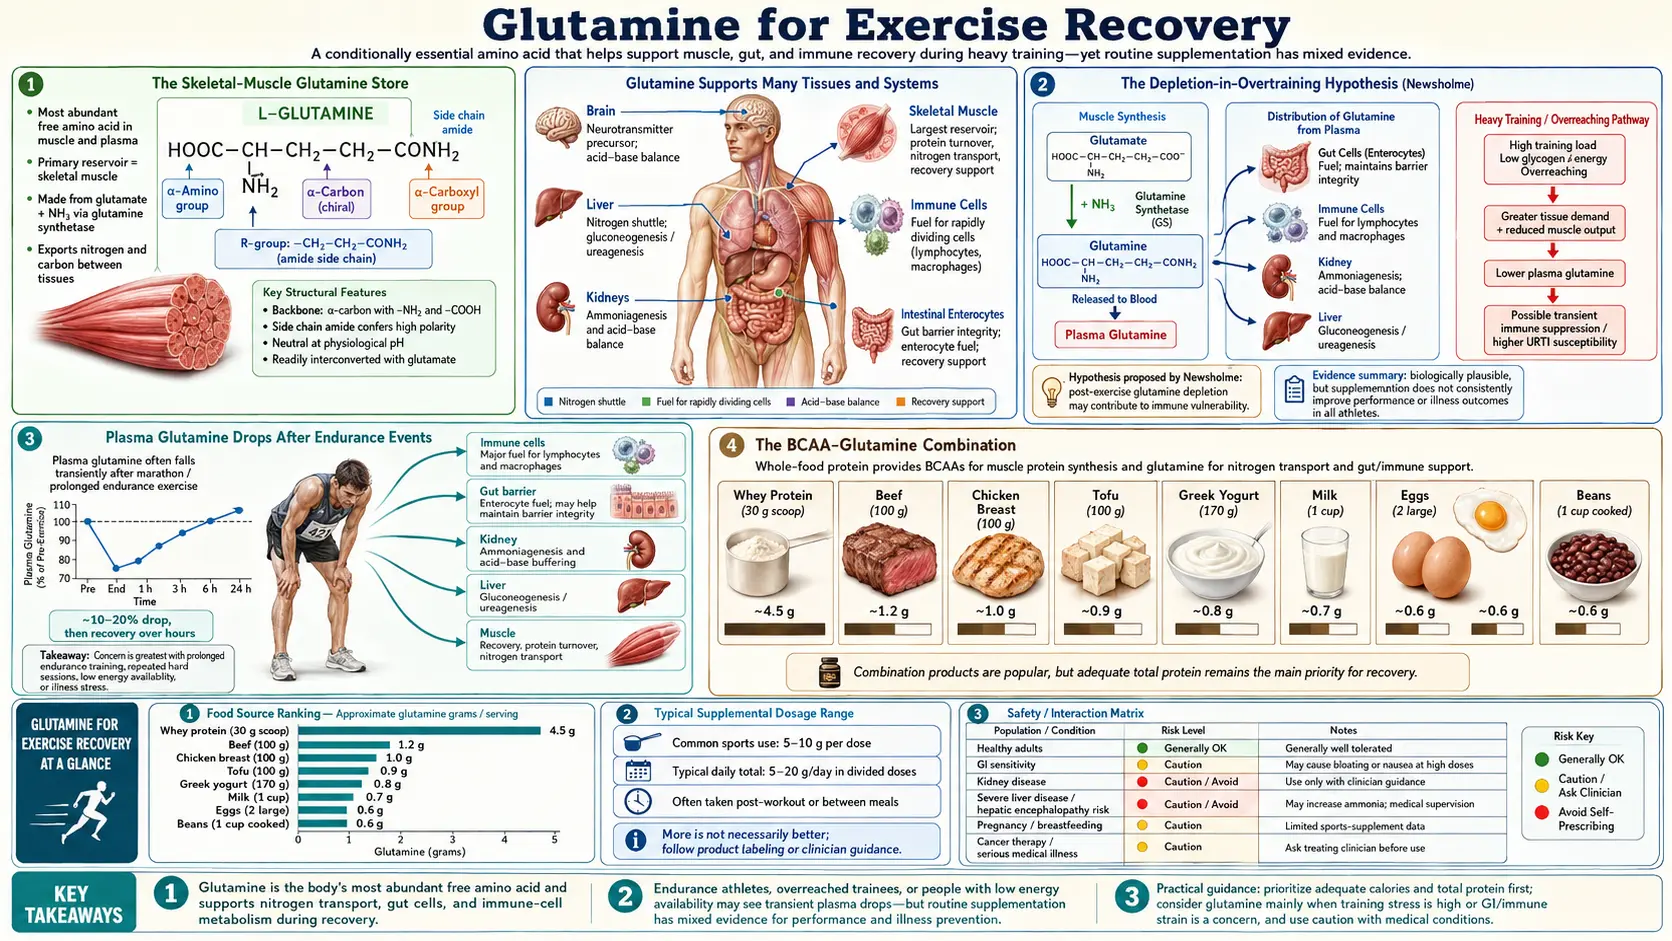
Skeletal muscle is the body's glutamine warehouse — roughly 60% of the intramuscular free amino acid pool is glutamine, and that store is the body's principal buffer against the glutamine demands of the immune system, gut, and kidney under stress. Prolonged or intense exercise drains this store in a measurable way: plasma glutamine falls 20-40% after marathons and ultra-endurance events and remains depressed for 12-72 hours, and chronic overtraining is associated with persistently low plasma glutamine that Eric Newsholme proposed as one of the biochemical markers of the overtraining syndrome. The clinical picture for the recreational lifter is more nuanced — glutamine has not been shown to increase strength, lean mass, or hypertrophy in well-fed weight-trained subjects — but for endurance athletes, athletes during high-volume training blocks, and athletes managing post-exercise URTIs and gut symptoms, the studies below are where a role for supplementation has been examined. This deep-dive walks through the depletion mechanism, the trial evidence, the branched-chain amino acid-glutamine combination, and where the evidence is strong versus where it remains thin.
Table of Contents
- The Skeletal-Muscle Glutamine Store
- The Depletion-in-Overtraining Hypothesis (Newsholme)
- Plasma Glutamine Drops After Endurance Events
- The Branched-Chain Amino Acid-Glutamine Combination
- Glycogen Resynthesis (Bowtell 1999)
- Muscle Soreness and Recovery (Legault, Street)
- Exercise-Induced Gut Permeability
- Oral vs Intravenous Glutamine
- What the Trials Found — And Where the Evidence Remains Thin
- Amounts Used by Athletes
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Skeletal-Muscle Glutamine Store
The free amino-acid pool in skeletal muscle is dominated by glutamine: roughly 60% of the intramuscular free amino acid pool is glutamine, and the total body free glutamine pool is approximately 70-80 grams, with the vast majority residing in skeletal muscle. By comparison, plasma free glutamine accounts for only a few hundred milligrams. Skeletal muscle is therefore functioning as the body's glutamine warehouse, releasing glutamine into circulation on demand whenever the immune system, gut, kidney, or liver require it.
Under ordinary resting conditions this works smoothly — muscle synthesizes glutamine continuously (the glutamine synthetase reaction adds an amide nitrogen from ammonia to glutamate, using adenosine triphosphate (ATP)), and exports it to circulation at a rate that matches uptake by the immune system, gut, kidney, and liver. Under conditions of catabolic stress — major trauma, sepsis, severe burns, intense or prolonged exercise — muscle glutamine release accelerates, but eventually demand outstrips intramuscular synthesis, and net protein breakdown follows to liberate additional amino acids that can feed into the glutamine synthesis pathway.
This is the mechanism behind the visible muscle wasting of chronically ill or septic patients, and it is also the mechanism behind the more subtle catabolism that competitive endurance athletes experience during heavy training blocks.
The Depletion-in-Overtraining Hypothesis (Newsholme)
In the early 1990s, Eric Newsholme at Oxford proposed that the so-called overtraining syndrome — the constellation of fatigue, performance decrement, sleep disturbance, mood symptoms, and increased URTI susceptibility that affects athletes in chronic high-volume training — could be partly explained by chronic depletion of plasma glutamine. Athletes in heavy training were measured to have plasma glutamine levels 20-40% below those of less-active controls or below their own pre-season baseline, with the lowest values correlating with the most severe symptoms.
The depletion-in-overtraining hypothesis has held up partially. Glutamine depletion is reliably documented in overtrained athletes, and supplementation does appear to attenuate some of the immune consequences (URTI rate, lymphocyte function). But overtraining syndrome is multifactorial — cortisol elevation, autonomic dysregulation, central fatigue mechanisms, sleep disruption, micronutrient depletion, and possibly mitochondrial adaptations all play roles — and glutamine repletion does not by itself reverse the syndrome. The Walsh 1998 Sports Medicine review and the Coqueiro 2019 Nutrients update treat glutamine as one component of overtraining management, not as a silver bullet.
Plasma Glutamine Drops After Endurance Events
Castell and Newsholme's 1997 paper in Nutrition documented the classic finding: marathon runners showed a 20% drop in plasma glutamine in the hours after race completion, with values remaining below baseline for 24-72 hours. Ultra-endurance events (Ironman triathlons, multi-day stage races) produce larger and longer-lasting drops. The mechanism is a combination of accelerated immune-cell uptake during the post-exercise inflammatory response, accelerated gut uptake to repair exercise-induced barrier dysfunction, and reduced rate of intramuscular synthesis during the recovery period.
The clinical relevance: this post-event glutamine valley correlates with the well-documented post-event "open-window" of immune vulnerability, during which marathon runners and ultra-endurance athletes experience URTIs at roughly 2-6× the rate of less-active controls. In a 1996 study by Castell, Poortmans and Newsholme, athletes taking part in different types of exercise (runners and rowers) drank either glutamine or a placebo immediately after and 2 hours after exercise; in questionnaires covering the following 7 days, 81% of the glutamine group reported no infections, compared with 49% of the placebo group.
For practical purposes, endurance athletes whose training or competition schedule includes events longer than 90-120 minutes typically supplement with 5-10 g of L-glutamine daily during the high-volume period, with an additional 5 g immediately after long sessions or races.
The Branched-Chain Amino Acid-Glutamine Combination
Branched-chain amino acids (leucine, isoleucine, valine) and glutamine are often combined in sports-nutrition products because they target complementary aspects of the muscle catabolism problem. Branched-chain amino acids (BCAAs) — particularly leucine — are the principal anabolic-signaling amino acids, activating mTORC1 and driving muscle protein synthesis. Glutamine does not directly activate mTORC1 to a meaningful degree (the early literature on this was complicated by cell-culture artifacts), but it supplies the gut and immune system substrate that prevents the catabolic side of the equation from overwhelming the anabolic stimulus of leucine.
In trained subjects, isolated glutamine supplementation has not been shown to increase muscle protein synthesis, strength, or hypertrophy in well-controlled trials. The branched-chain amino acid-glutamine combination has more support, but the active ingredient is generally the branched-chain amino acids — glutamine is the gut-and-immune supporting partner, not the anabolic driver. In sports-nutrition practice glutamine is taken for recovery and immune support rather than for direct hypertrophy. The Gleeson 2008 Journal of Nutrition review on dosing in exercise found that glutamine feeding does not prevent the post-exercise changes in several aspects of immune function, and that the suggested reasons for taking glutamine supplements (support for the immune system, increased glycogen synthesis, an anticatabolic effect) “have received little support from well-controlled scientific studies in healthy, well-nourished humans.”
Glycogen Resynthesis (Bowtell 1999)
Bowtell and colleagues' 1999 paper in the Journal of Applied Physiology tested whether oral glutamine could promote carbohydrate storage and muscle glycogen resynthesis after glycogen-depleting exercise. After the exercise, subjects drank 330 ml of a glucose-polymer drink, the same drink with 8 g of glutamine added, or 8 g of glutamine in a placebo drink. In the second hour of recovery, whole-body non-oxidative glucose disposal (glucose stored rather than burned) was 25% higher when glutamine was added to the glucose drink — the glutamine came on top of the same glucose, so carbohydrate intake was not matched. Glutamine alone promoted storage of muscle glycogen to an extent similar to the glucose drink.
The authors concluded that glutamine taken together with the glucose drink promoted the storage of carbohydrate outside skeletal muscle, the most feasible site being the liver (the liver and kidney can convert glutamine to glucose). For an endurance athlete who needs to recover quickly between sessions (multi-day races, two-a-day training, tournaments), extra carbohydrate storage is the effect that draws interest. The study used a fixed 8 g dose of glutamine; it did not test doses scaled to body weight.
Muscle Soreness and Recovery (Legault, Street)
The Legault, Bagnall, and Kimmerly 2015 trial in IJSNEM was a double-blind, placebo-controlled crossover study in 16 healthy young adults (8 women, 8 men), who took L-glutamine (0.3 g per kg of body weight per day) or a placebo once a day for 72 hours and were tested for recovery of muscle strength and soreness following a session of unilateral knee-extension eccentric exercise. The glutamine condition showed:
- Greater peak torque in fast contractions (180° per second) immediately after and 72 hours after the exercise; the authors noted the effect on force recovery may be greater in men than in women
- Lower subjective muscle soreness ratings at 24, 48, and 72 hours
- No effect on serum creatine kinase or other markers of structural muscle damage
The Street et al. 2011 trial in the Journal of Exercise Science and Fitness reported similar findings using a different eccentric exercise protocol. The Córdova-Martínez 2021 crossover study in 12 professional basketball players found that 6 g of glutamine a day for 20 days, compared with 20 days of placebo, gave lower blood markers of muscle damage (aspartate transaminase, creatine kinase and myoglobin) and lower levels of the stress hormone ACTH; it measured blood markers only, not recovery time.
The consistent finding across these trials is that glutamine modestly accelerates functional recovery (strength return, perceived soreness) without affecting the underlying structural muscle damage. The mechanism is probably some combination of immune-modulation (reducing the secondary inflammatory damage that follows initial mechanical injury), gut-barrier preservation (reducing the systemic endotoxin load from exercise-induced permeability), and possibly direct effects on muscle glutamine availability for protein synthesis during the repair phase.
Exercise-Induced Gut Permeability
Prolonged intense exercise — particularly endurance events in heat — produces a transient but measurable increase in intestinal permeability. The mechanism is splanchnic ischemia (blood is shunted away from the gut to the muscles), followed by reperfusion injury and inflammatory damage to the gut barrier. Endurance athletes are well aware of this phenomenon under its informal name: "runner's gut" or "runner's diarrhea."
The systemic consequence is endotoxemia — bacterial lipopolysaccharide (LPS) translocates across the compromised gut barrier into systemic circulation, where it activates innate immune signaling. This is one of the mechanisms contributing to the post-exercise immune dip and to the systemic inflammation that follows prolonged events. Glutamine supplementation supports the recovery of gut barrier function in this setting (covered in detail in the companion Gut Health & Leaky Gut page), reducing endotoxin translocation and the downstream inflammatory cascade.
Glutamine is used in sports-nutrition practice in the days before and immediately after long endurance events with the aim of reducing this endotoxin leak, the inflammation that follows, and gastrointestinal (GI) symptoms. The trials so far are laboratory studies rather than studies at real races. In a 2017 study by Pugh and colleagues, ten recreationally active men took glutamine 2 hours before a 60-minute treadmill run in a 30°C chamber; a blood marker of intestinal permeability (the lactulose-to-rhamnose ratio) was lower than with placebo, more so at the largest dose, while GI symptoms were low and were not changed. A 2022 study by Ogden and colleagues, which gave a single 0.3 g per kg dose that its authors called low before 80 minutes of exertional heat stress, found no protective effect on permeability, gut-lining injury or bacterial-translocation markers.
Oral vs Intravenous Glutamine
Oral L-glutamine powder is the form used in essentially all sports nutrition contexts. Bioavailability is good (roughly 70-80% survives first-pass splanchnic extraction; the splanchnic bed retains 20-30% for enterocyte and hepatic use, which is itself a desirable effect for the gut-barrier and gut-permeability applications). Onset of plasma elevation is approximately 30-45 minutes for ingested doses up to 10 g.
Intravenous (IV) glutamine (as the alanyl-glutamine dipeptide) is used in clinical critical-care settings, mainly for patients who cannot tolerate enteral feeding, and has no role in normal sports-nutrition contexts. In hospital, the largest trial raised a safety signal: in the REDOXS trial (2013) of 1,223 critically ill adults with multiorgan failure on mechanical ventilation, glutamine given both intravenously and by feeding tube was associated with higher mortality (28-day mortality 32.4% vs 27.2%; in-hospital and 6-month mortality were significantly higher with glutamine). The clinical intravenous-dosing protocols (0.3-0.4 g/kg/day) are also much higher than the doses sports-nutrition athletes typically use.
What the Trials Found — And Where the Evidence Remains Thin
Positive findings reported in trials
- Fewer self-reported infections in the week after endurance exercise — Castell 1996 and 1997 questionnaire studies; the Gleeson 2008 review found that later feeding studies did not show glutamine preventing the post-exercise changes in immune function
- More whole-body carbohydrate storage when glutamine was added to a glucose drink — Bowtell 1999, a single study; the extra storage was most likely in the liver rather than in muscle
- Reduced subjective muscle soreness and faster strength recovery after eccentric exercise — Legault 2015, Street 2011
- Lower markers of gut permeability during running in the heat — Pugh 2017, a laboratory study of 10 men (a 2022 laboratory study of a single 0.3 g/kg dose found no protection)
- Lower blood markers of muscle damage in basketball players — Córdova-Martínez 2021 (12 players, crossover)
Evidence is thin or absent
- Increased muscle protein synthesis in well-fed trained subjects — not supported
- Direct hypertrophy or strength gains in resistance-trained subjects — not supported in well-controlled trials
- Improved aerobic capacity or VO2max — not supported
- Performance benefit in single-session events under 90 minutes — not supported
- Improved nitrogen balance and lean-mass preservation during catabolic stress — extrapolated from clinical-care literature to extreme training; in the largest critical-care trial (REDOXS, 2013) glutamine was associated with higher mortality in critically ill patients
In sports-nutrition practice glutamine is treated as a recovery and immune-support nutrient, not a performance-enhancing aid. It is mainly used by athletes with high training volume, endurance athletes, and athletes with recurrent URTIs or gut symptoms, rather than by power athletes or recreational lifters looking for hypertrophy.
Amounts Used by Athletes
The amounts below are those described in sports-nutrition practice, not protocols taken from a specific trial. On safety, the Gleeson 2008 review reports that single intakes of about 20–30 g of glutamine seem to be without ill effect in healthy adults, and that no harm was reported in one study in which athletes took 28 g every day for 14 days.
Endurance athletes during high-volume training blocks
- 5 g L-glutamine on an empty stomach in the morning
- 5 g immediately post-training, often taken with carbohydrate, as in the Bowtell glycogen study
- Total daily amount 10-15 g during peak weeks, about 5 g/day off-season
Around-event protocol for marathons, ultras, triathlons
- 5 g daily for 2 weeks before the event
- 5 g 2 hours before the event start (the timing, though not the dose, of the Pugh gut-permeability study)
- 5 g immediately at finish
- 5 g twice daily for 5-7 days post-event (the post-event week in which the Castell studies counted infections)
Strength / resistance training athletes
- 5 g post-workout, combined with whey protein or other complete-protein source — primarily as gut-immune support during high-volume blocks; little expected anabolic benefit
- Usually not used in off-season or maintenance training
Recovery from a defined overtraining episode
- 10-20 g/day in divided doses for 2-4 weeks
- Combined with rest, nutritional adequacy, and management of contributing factors (sleep, stress, micronutrient status)
Cautions
- Liver disease / hepatic encephalopathy — glutamine is broken down to ammonia, and a damaged liver clears ammonia poorly; ammonia build-up is what drives hepatic encephalopathy (the confusion of liver failure).
- Severe kidney disease — the kidney turns glutamine into ammonia as part of its normal acid handling; this pathway is normally protective, but in severe chronic kidney disease (CKD) it can become problematic.
- Active cancer — some tumor cell types depend heavily on glutamine for growth ("glutamine addiction"), which is the reason for concern about glutamine supplements during active cancer.
- Seizure disorders — glutamine converts to glutamate, an excitatory brain messenger, which is the basis for caution in seizure disorders.
- Inadequate carbohydrate intake — the glycogen study above tested glutamine over a single 2-hour recovery; it did not test glutamine as a replacement for regular carbohydrate intake during training.
- Acute gastrointestinal distress while running — if oral glutamine is taken too close to event start, it can occasionally cause gastrointestinal symptoms in sensitive individuals, which is why athletes usually try pre-event amounts in training first.
Key Research Papers
- Castell LM, Newsholme EA (1997). The effects of oral glutamine supplementation on athletes after prolonged, exhaustive exercise. Nutrition. The foundational "open-window" trial. — PubMed PMID: 9263279
- Legault Z, Bagnall N, Kimmerly DS (2015). The Influence of Oral L-Glutamine Supplementation on Muscle Strength Recovery and Soreness Following Unilateral Knee Extension Eccentric Exercise. International Journal of Sport Nutrition and Exercise Metabolism. — PubMed PMID: 25811544
- Street B, Byrne C, Eston R (2011). Glutamine Supplementation in Recovery From Eccentric Exercise Attenuates Strength Loss and Muscle Soreness. Journal of Exercise Science and Fitness 9(2):116–122. Not indexed in PubMed. — doi:10.1016/s1728-869x(12)60007-0
- Bowtell JL et al. (1999). Effect of oral glutamine on whole body carbohydrate storage during recovery from exhaustive exercise. Journal of Applied Physiology. — PubMed PMID: 10368336
- Coqueiro AY, Rogero MM, Tirapegui J (2019). Glutamine as an Anti-Fatigue Amino Acid in Sports Nutrition. Nutrients. The modern sports-nutrition review. — PubMed PMID: 30999561
- Walsh NP, Blannin AK, Robson PJ, Gleeson M (1998). Glutamine, exercise and immune function. Links and possible mechanisms. Sports Medicine. The classic mechanistic review. — PubMed PMID: 9802174
- Gleeson M (2008). Dosing and efficacy of glutamine supplementation in human exercise and sport training. Journal of Nutrition. — PubMed PMID: 18806122
- Hickson RC et al. (1995). Glutamine prevents downregulation of myosin heavy chain synthesis and muscle atrophy from glucocorticoids. American Journal of Physiology. — PubMed PMID: 7733273
- Biolo G, Zorat F, Antonione R, Ciocchi B (2005). Muscle glutamine depletion in the intensive care unit. International Journal of Biochemistry and Cell Biology. — PubMed PMID: 16084750
- Córdova-Martínez A, Caballero-García A, Bello HJ, Pérez-Valdecantos D, Roche E (2021). Effect of Glutamine Supplementation on Muscular Damage Biomarkers in Professional Basketball Players. Nutrients. — PubMed PMID: 34204359
- Castell LM, Poortmans JR, Newsholme EA (1996). Does glutamine have a role in reducing infections in athletes? European Journal of Applied Physiology and Occupational Physiology. — PubMed PMID: 8803512
- Heyland D, Muscedere J, Wischmeyer PE, Cook D, Jones G, Albert M, Elke G, Berger MM, Day AG; Canadian Critical Care Trials Group (2013). A randomized trial of glutamine and antioxidants in critically ill patients. New England Journal of Medicine. The REDOXS trial. — PubMed PMID: 23594003
- Pugh JN, Sage S, Hutson M, Doran DA, Fleming SC, Highton J, Morton JP, Close GL (2017). Glutamine supplementation reduces markers of intestinal permeability during running in the heat in a dose-dependent manner. European Journal of Applied Physiology. — PubMed PMID: 29058112
- Ogden HB, Fallowfield JL, Child RB, Davison G, Fleming SC, Delves SK, Millyard A, Westwood CS, Layden JD (2022). No protective benefits of low dose acute L-glutamine supplementation on small intestinal permeability, epithelial injury and bacterial translocation biomarkers in response to subclinical exertional-heat stress: A randomized cross-over trial. Temperature. — PubMed PMID: 36106146
- Cruzat V et al. (2018). Glutamine: Metabolism and Immune Function, Supplementation and Clinical Translation. Nutrients. — PubMed PMID: 30360490
PubMed Topic Searches
Connections
- All Amino Acids
- Glutamine Overview
- Glutamine Benefits Hub
- Glutamine for Gut Health & Leaky Gut
- Glutamine for Immune Function
- Glutamine for Weight Loss Support
- Leucine (Branched-Chain Amino Acid)
- Isoleucine
- Valine
- Arginine
- Glycine
- N-Acetylcysteine & Glutathione
- Magnesium
- Zinc
- Vitamin D3
- Vitamin C
- Stress Management
- Gut Healing
- Fatigue
- Pain
- Bone Broth
- Collagen
- Inflammatory Markers
- History
- Sources