Arginine for Erectile Function
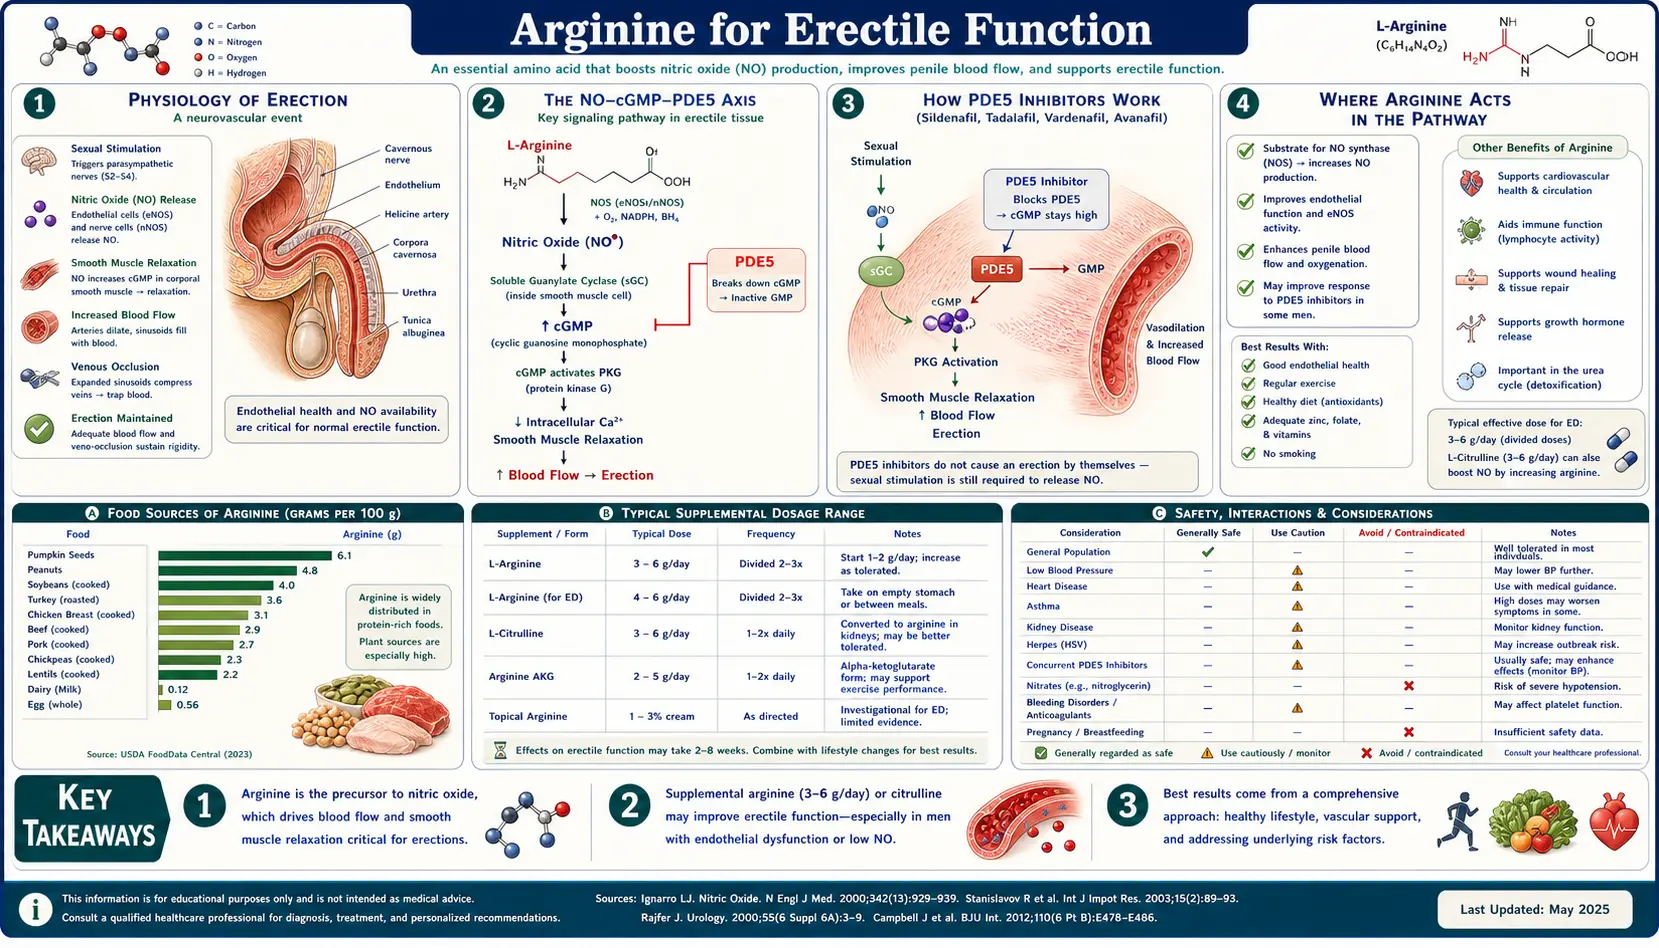
Penile erection is, at its core, a vascular event. The trigger is sexual stimulation; the proximate cause is nitric oxide (NO) released by nerves and by the endothelium in the corpus cavernosum; and NO is made from L-arginine by nitric oxide synthase (Toda 2005). Arginine therefore sits upstream of the pathway on which the PDE5-inhibitor drugs act — sildenafil, tadalafil, vardenafil and avanafil preserve the cyclic GMP signal that NO triggers, and they increase the response to sexual stimulation rather than causing an erection on their own (Goldstein 1998). The trial evidence for oral arginine, or for citrulline, comes from small, short studies in men with mild to moderate erectile dysfunction: a 2019 meta-analysis of 10 randomized trials found improvement compared with placebo or no treatment, with a wide confidence interval (Rhim 2019), and one placebo-controlled crossover trial of a lower dose found no difference (Klotz 1999). The highest figure in this literature — 92.5% of 40 men reporting a normal erection after arginine with a French maritime pine bark extract — comes from a study with no placebo group (Stanislavov 2003). This deep-dive covers the NO-cGMP-PDE5 axis, how arginine differs pharmacologically from PDE5 inhibitors, the trial evidence for arginine alone, for citrulline, for arginine with a pine bark extract and for arginine added to a PDE5 inhibitor, and what guidelines and trials describe.
Table of Contents
- The Physiology of Erection
- The NO-cGMP-PDE5 Axis
- How PDE5 Inhibitors Work
- Where Arginine Acts in the Pathway
- Clinical Trial Evidence for Arginine Alone
- Citrulline Trials in Erectile Dysfunction
- The Arginine + Pine Bark Extract Combination
- Arginine vs PDE5 Inhibitors
- When PDE5 Inhibitors Are Not Enough
- What Guidelines and Trials Describe
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Physiology of Erection
Penile erection results from increased arterial inflow to the corpus cavernosum combined with restricted venous outflow, producing engorgement of the erectile tissue with blood. The corpus cavernosum is a paired cylinder of vascular sinusoids surrounded by the tunica albuginea, a tough fibrous sheath. In the flaccid state, the arterial inflow to the cavernosum is restricted by tonic sympathetic vasoconstriction, and the sinusoids are largely empty. Erection requires three coordinated events:
- Sympathetic withdrawal and parasympathetic activation — sexual stimulation, either central (psychogenic) or peripheral (tactile via the dorsal penile nerve), triggers parasympathetic outflow via the pelvic splanchnic nerves and the cavernous nerves. These nerves release acetylcholine onto endothelial cells of the cavernosal sinusoids and noncholinergic, nonadrenergic (NANC) signals that release NO directly from neuronal terminals.
- NO release and smooth muscle relaxation — NO from both endothelial NOS3 (activated by acetylcholine and shear stress) and neuronal NOS1 (released directly from cavernous nerve terminals) diffuses into adjacent cavernosal smooth muscle. There it activates soluble guanylate cyclase, generating cGMP, which causes smooth muscle relaxation. Relaxed smooth muscle allows the sinusoids to fill with blood under arterial pressure.
- Venous restriction (the corporeal veno-occlusive mechanism) — as the sinusoids expand against the rigid tunica albuginea, the emissary veins that exit through the tunic are mechanically compressed, restricting venous outflow. The result is increased intracavernosal pressure approaching systemic arterial pressure, producing the rigidity characteristic of full erection.
The reverse process — detumescence — requires cGMP breakdown by phosphodiesterase type 5 (PDE5), which hydrolyzes cGMP to inactive 5'-GMP, allowing smooth muscle to return to its contracted baseline state and blood to drain from the sinusoids. This balance between NO/cGMP-driven relaxation and PDE5-driven cGMP breakdown is what determines erectile capacity at any given moment.
The NO-cGMP-PDE5 Axis
The molecular cascade that produces erection follows a well-defined four-step sequence:
- Substrate → Enzyme: L-arginine is the obligate substrate for nitric oxide synthase. The cavernosum expresses both NOS1 (in neurons) and NOS3 (in endothelium). Both convert arginine to citrulline and release NO.
- Enzyme → Signaling molecule: NO diffuses across cell membranes (it is a small, lipid-permeable, uncharged molecule), reaching smooth muscle cells without requiring a receptor.
- Signaling molecule → Second messenger: NO binds the heme group of soluble guanylate cyclase (sGC), activating it. sGC converts GTP to cGMP, the relaxant second messenger.
- Second messenger → Effect: cGMP activates protein kinase G (PKG), which phosphorylates targets including IP3 receptors, BKCa channels, and myosin light chain phosphatase. The net effect is reduced intracellular calcium and dephosphorylation of myosin, producing smooth muscle relaxation.
Impaired formation and action of NO is described as a major mechanism of erectile dysfunction (Toda 2005; Burnett 2006). Proposed contributors in men with hypertension, diabetes or vascular disease include reduced endothelial NOS activity, oxidation of the BH4 cofactor that "uncouples" NOS, and raised levels of ADMA, an endogenous NOS inhibitor; the proposed result is too little NO to build enough cGMP against basal PDE5 activity, despite intact nerve signalling and intact downstream machinery.
The broader cardiovascular biology of NO and ADMA is covered on the Cardiovascular and NO deep-dive.
How PDE5 Inhibitors Work
Sildenafil was the first PDE5 inhibitor approved for erectile dysfunction. Two sequential double-blind trials published in 1998 — a 24-week dose-response study in 532 men and a 12-week dose-escalation study in 329 men with organic, psychogenic or mixed erectile dysfunction — reported that 69% of attempts at intercourse were successful on sildenafil versus 22% on placebo in the last four weeks of the dose-escalation study; headache, flushing and dyspepsia were the most common adverse effects, in 6–18% of men (Goldstein 1998).
The mechanism is inhibition of phosphodiesterase type 5, the enzyme that hydrolyzes cGMP to 5'-GMP. By inhibiting PDE5, sildenafil prolongs the life of cGMP in cavernosal smooth muscle, amplifying and prolonging the relaxation produced by any given pulse of NO release. The key point is that PDE5 inhibitors do not produce erection in the absence of sexual stimulation — they increase the penile response to sexual stimulation (Goldstein 1998), and they need upstream NO release to have any cGMP to preserve.
The four PDE5 inhibitors available in the United States differ in pharmacokinetics and side-effect profile (Wright 2006; Smith 2013):
- Sildenafil — half-life approximately 4 hours; fatty food affects its pharmacokinetics; associated with a higher rate of visual changes
- Vardenafil — half-life approximately 4 hours; fatty food affects its pharmacokinetics; associated with QT prolongation
- Tadalafil — half-life 17.5 hours, the longest of the four; food does not affect its pharmacokinetics; associated with lower back pain
- Avanafil — reaches peak plasma concentration rapidly, which gives a faster onset of action
All four work through the same mechanism: prolongation of cGMP signalling downstream of arginine-derived NO. Because not all patients respond to PDE5 inhibitors, other therapies acting on the NO pathway, such as NO donors and soluble guanylyl cyclase activators, are under investigation (Burnett 2006). Whether arginine helps men who do not respond to a PDE5 inhibitor has been tested only in small add-on studies, described below.
Where Arginine Acts in the Pathway
Arginine supplementation acts at step 1 of the cascade — the substrate input to NOS. Its mechanism is fundamentally different from PDE5 inhibitors:
- PDE5 inhibitors work downstream by preventing degradation of an already-produced cGMP signal. They require functional NO production to work.
- Arginine works upstream by providing substrate for NOS, increasing NO production at the source. It does not depend on functional PDE5 inhibition; the cGMP signal can still be rapidly degraded, but the amplitude of the initial NO pulse is higher.
The proposed implication is that the two approaches could be complementary rather than redundant: more NO produced (arginine) and more cGMP preserved per NO molecule (PDE5 inhibitor). This is a mechanistic rationale; the trials that tested it are below.
Three randomized trials have added daily arginine to a PDE5 inhibitor in men with erectile dysfunction in general (not specifically men who had failed a PDE5 inhibitor). In 300 men given L-arginine 2,500 mg, tadalafil 5 mg, or both daily for 12 weeks, the erectile-function score (IIEF-EF) rose from 15 to 18.1 on arginine, 14.8 to 20.8 on tadalafil and 14.9 to 22 on the combination, which the authors reported as superior to either alone; 11, 53 and 67 adverse events were recorded in the three groups (Gallo 2020). In 108 diabetic men with mild to moderate ED, daily arginine plus tadalafil improved IIEF-5 scores and total testosterone more than either drug alone, with no difference on penile duplex ultrasound (El Taieb 2019). Adding arginine 3 g/day to sildenafil 50 mg every other day for 8 weeks gave a mean IIEF-5 score of 19.8 versus 18.5 on sildenafil alone (p = 0.05), and gastritis was more common in the combination group (El-Wakeel 2020).
Clinical Trial Evidence for Arginine Alone
The trial literature on arginine alone for erectile dysfunction is small and mixed. Chen et al. (1999) randomized 50 men with confirmed organic ED, after a 2-week placebo run-in, to L-arginine 5 g/day or placebo for six weeks. Nine of 29 men on arginine (31%) and 2 of 17 on placebo reported a significant subjective improvement in sexual function; all objective measures, including penile haemodynamics, were unchanged. All nine men who improved had low urinary NO metabolites (NOx) at the start, and their levels had doubled by the end; the authors concluded that the subjective benefit appeared only in men with decreased NOx excretion or production.
Klotz et al. (1999) tested a lower dose, 500 mg three times a day (1.5 g/day), against placebo in a randomized crossover trial of 32 men with mixed-type ED (two 17-day courses with a 7-day washout; 30 completed). Five men (17%) reported significant improvement on arginine and six (20%) on placebo, with no statistical difference; the authors concluded this dose was not better than placebo as a first-line treatment.
Cormio et al. (2011) gave 24 men with mild ED one month of placebo followed by one month of L-citrulline 1.5 g/day. Twelve of the 24 (50%) reached a normal erection-hardness score on citrulline versus 2 of 24 (8.3%) on placebo, and no adverse events were recorded. The study was single-blind and not randomized — every man took placebo first and citrulline second, with no parallel control group — so order effects, expectation and regression to the mean are not excluded. The authors described citrulline as less effective than PDE5 inhibitors, at least in the short term. Citrulline escapes the presystemic breakdown that limits oral arginine and is converted to arginine (Cormio 2011); the pharmacokinetics are covered on the Cardiovascular and NO page.
A meta-analysis by Rhim et al. (2019) pooled 10 randomized trials reporting 540 patients and found that arginine supplements at 1,500–5,000 mg improved erectile dysfunction compared with placebo or no treatment, with an odds ratio of 3.37 (95% CI 1.29–8.77; I² = 44%). The confidence interval is wide, and the authors note that dose and duration varied between studies. The analysis included only trials in men with mild to moderate ED, so it does not address severe ED. Adverse effects occurred in 8.3% of arginine-treated men versus 2.3% on placebo; none were severe. The pooled trials included arginine alone and arginine combined with other substances.
Taken together, the controlled trials of arginine alone were small and short (17 days to 6 weeks per treatment period in the trials described here) and enrolled men with mild to moderate or mixed-type ED. The pooled analysis found an improvement over placebo with a wide confidence interval, a 1.5 g/day crossover trial found no difference, and in the 5 g/day trial the subjective benefit was confined to men with low NO-metabolite excretion and was not accompanied by any change in objective measures.
Citrulline Trials in Erectile Dysfunction
The citrulline trials are more recent than the arginine trials and fewer in number. The key studies:
- Cormio et al. (2011) — L-citrulline 1.5 g/day, 24 men with mild ED, one month of placebo then one month of citrulline. 50% reached a normal erection-hardness score versus 8.3% on placebo. The study was single-blind and non-randomized, with no parallel control arm.
- Shirai et al. (2018) — a randomized, double-blind, placebo-controlled crossover pilot study in men whose ED persisted despite on-demand PDE5-inhibitor use (SHIM score below 16). Participants continued their PDE5 inhibitor and took placebo for one month and L-citrulline 800 mg/day plus trans-resveratrol 300 mg/day for another month. Of 20 men enrolled, 13 completed the study, without adverse events. The mean SHIM score was higher on the active treatment (10.96) than at baseline (8.32) or on placebo (8.31); the erection-hardness score rose from 2.31 to 2.56, which was not statistically significant. Because the supplement combined citrulline with trans-resveratrol and was added to a PDE5 inhibitor, the study does not test citrulline on its own.
- Duration. In the citrulline studies described here, each treatment period lasted one month or less. A 2021 crossover pilot from the same group tested a drink combining a fenugreek seed extract (600 mg/day), L-citrulline (800 mg/day), resveratrol (300 mg/day) and caffeine (40 mg/day) for 14 days, against a placebo drink for 14 days with a 7-day washout, in 20 men who continued on-demand PDE5 inhibitors; all 20 completed it without adverse events, and several IIEF domains, including erection firmness, improved (Shirai 2021).
The citrulline doses used in these erectile-function studies were 1.5 g/day (Cormio 2011) and 800 mg/day in combination products (Shirai 2018; Shirai 2021).
On tolerability, no adverse events were recorded in the citrulline studies above. In the arginine meta-analysis, adverse effects occurred in 8.3% of arginine-treated men versus 2.3% on placebo, none severe (Rhim 2019), and in one sildenafil trial gastritis was more common when arginine was added (El-Wakeel 2020).
The Arginine + Pine Bark Extract Combination
The highest response rates reported in the arginine ED literature come from studies combining L-arginine with a French maritime pine bark extract, a standardized extract of Pinus pinaster bark that is rich in oligomeric proanthocyanidins. Stanislavov and Nikolova chose the extract because it is reported to increase NO production by nitric oxide synthase; other proposed mechanisms include antioxidant activity that protects the BH4 cofactor of NOS from oxidation.
The most-quoted study is Stanislavov and Nikolova (2003), published in the Journal of Sex and Marital Therapy. Forty men aged 25–45 without confirmed organic erectile dysfunction took a drinkable arginine aspartate solution (equivalent to 1.7 g L-arginine per day) throughout the 3-month study. In the second month they also took a French maritime pine bark extract, 40 mg twice daily, and in the third month 40 mg three times daily. Erectile function was recorded with a sexual function questionnaire and a sexual activity diary.
Two features of the design bear on the numbers below. There was no placebo group and no randomization — every man received every treatment in the same fixed order, so the month-to-month rise cannot be separated from expectation, from the natural course of a non-organic complaint, or from time in the study. And the men did not have confirmed organic ED.
The results:
- After arginine alone (month 1): 2 men (5%) experienced a normal erection, a number the authors describe as statistically nonsignificant
- After arginine + pine bark extract 80 mg/day (month 2): 80% reported restored sexual ability
- After arginine + pine bark extract 120 mg/day (month 3): 92.5% experienced a normal erection
The same authors, with Rohdewald, later ran a randomized, double-blind, placebo-controlled crossover trial in 50 men with mild to moderate ED, who took placebo or a combination of L-arginine aspartate and the pine bark extract for one month each; the authors report that erectile function was restored to normal and intercourse frequency doubled on the combination, with no unwanted effects (Stanislavov 2008).
Two further placebo-controlled trials tested combination products. Ledda et al. (2010) gave a fixed combination of the pine bark extract with L-arginine aspartate or placebo for 6 months to 124 men aged 30–50 with moderate ED; the erectile domain of the IIEF rose from 15.2 to 25.2 at 3 months and 27.1 at 6 months on the combination, versus 15.1 to 19.1 and 19.0 on placebo. The abstract identifies the tested product by its manufacturer. Aoki et al. (2012) gave Japanese men with mild to moderate ED a supplement of the pine bark extract 60 mg/day, L-arginine 690 mg/day and aspartic acid 552 mg/day, or an identical placebo, for 8 weeks; the IIEF-5 total score improved and no adverse reactions were observed. The first author of that trial is listed at a pharmaceutical company's laboratories.
In summary, the combination has been tested in small trials of one to six months in men with mild to moderate ED, with commercial involvement noted in two of the trial records (Ledda 2010; Aoki 2012); no large independent trial was found for this page. The headline 92.5% figure comes from a study with no control group in men without confirmed organic ED, so it is not comparable with results from large placebo-controlled trials of PDE5 inhibitors such as the 1998 sildenafil trials (Goldstein 1998).
Arginine vs PDE5 Inhibitors
How arginine-based supplements and PDE5 inhibitors compare in the studies cited on this page:
- How they are taken — PDE5 inhibitors were taken as needed in the 1998 sildenafil trials (Goldstein 1998); daily tadalafil has also been studied (Smith 2013). The arginine and citrulline trials used daily dosing for 17 days to 6 months.
- Response — first-time response to PDE5 inhibitors is approximately 60–70%, with no significant difference in efficacy among the drugs (Smith 2013). For arginine, the pooled odds ratio versus placebo or no treatment was 3.37 with a wide confidence interval (Rhim 2019). The 80–92.5% figures quoted for arginine with a pine bark extract come from an uncontrolled study and are not comparable with placebo-controlled results.
- Severe ED — the arginine meta-analysis included only mild to moderate ED (Rhim 2019); one combination trial also enrolled men with severe ED, but its abstract reports subgroup results only for mild ED (Gallo 2020).
- Side effects — PDE5 inhibitors: headache, flushing and dyspepsia were the most common in the 1998 sildenafil trials (Goldstein 1998); a 2018 safety review found a small increase in the risk of non-arteritic ischaemic optic neuropathy and called a link to sensorineural hearing loss uncertain (Yafi 2018). Arginine: adverse effects in 8.3% versus 2.3% on placebo, none severe (Rhim 2019). Citrulline: no adverse events recorded in the small studies above.
- Drug interactions — PDE5-inhibitor prescribing information lists organic nitrates as a contraindication because of the risk of severe hypotension, and carries a precaution for alpha-blockers. For arginine with nitrates, an additive effect is theoretical; no trial was found for this page.
- Underlying disease — PDE5 inhibitors act on the cGMP signal rather than on the underlying vascular disease. Arginine and citrulline are proposed to act on endothelial NO production, but the trials above measured erectile function, not vascular outcomes, and the 5 g/day arginine trial found no change in penile haemodynamics (Chen 1999).
Erectile dysfunction is a strong predictor of coronary artery disease (Shamloul 2013), and the 2024 Princeton IV consensus states that the evidence supports the need for providers to treat men with ED as being at risk for cardiac events until proven otherwise (Köhler 2024). Whether arginine-based supplements change cardiovascular outcomes in men with ED has not been tested; in the VINTAGE MI trial after heart attack, more deaths were recorded on arginine than on placebo (Schulman 2006).
When PDE5 Inhibitors Are Not Enough
A 2013 review put the first-time response to PDE5 inhibitors at approximately 60–70%, and reported a treatment success rate of 89% when patients were prescribed all available PDE5 inhibitors (Smith 2013). Proposed explanations for a poor response include:
- Insufficient NO production to generate enough cGMP for PDE5 inhibition to amplify
- Cavernosal smooth muscle structural changes that reduce responsiveness to cGMP
- Nerve damage that prevents adequate parasympathetic NO release
- Sub-therapeutic dosing or improper administration timing
For men whose ED persisted despite on-demand PDE5 inhibitors, the evidence on adding citrulline comes from two small crossover pilots from one group: citrulline with trans-resveratrol for one month (13 of 20 men completed; SHIM score improved, erection-hardness score did not change significantly; Shirai 2018) and a four-ingredient drink for 14 days (20 men; several IIEF domains improved; Shirai 2021). No trial of higher-dose citrulline followed by a re-trial of a PDE5 inhibitor was found for this page.
When PDE5 inhibitors are ineffective, vacuum erection devices, intracavernous injections and penile prosthesis implantation are described as second- or third-line therapies (Shirai 2018).
What Guidelines and Trials Describe
What published guidelines and the trials on this page describe:
- Cardiovascular and endocrine assessment — the 2017 British Society for Sexual Medicine guidelines state that newly presenting patients should be evaluated for cardiovascular and endocrine risk factors, and that fasting glucose, a lipid profile and morning total testosterone should be considered mandatory (Hackett 2018). The Princeton III consensus emphasized exercise ability and stress testing to make sure a man's cardiovascular health matches the physical demands of sexual activity before ED treatment is prescribed (Nehra 2012); Princeton IV added coronary artery calcium scoring for risk stratification (Köhler 2024).
- Lifestyle factors — obesity, limited or absent physical exercise and lower urinary tract symptoms have been linked to the development of ED (Shamloul 2013).
- Doses used in supplement trials — L-arginine 5 g/day for 6 weeks (Chen 1999); 1,500–5,000 mg in the pooled trials (Rhim 2019); L-citrulline 1.5 g/day for one month (Cormio 2011); arginine aspartate equivalent to 1.7 g arginine/day with a French maritime pine bark extract at 80–120 mg/day (Stanislavov 2003); and fixed combination products (Stanislavov 2008; Ledda 2010; Aoki 2012).
- PDE5 inhibitors — reviews describe PDE5 inhibitors as first-line therapy for most causes of ED (Wright 2006; Yafi 2018); the 1998 sildenafil trials used 25, 50 or 100 mg as needed (Goldstein 1998).
- Second- and third-line options — vacuum erection devices, intracavernous injections and penile prosthesis implantation (Shirai 2018).
Decisions about ED treatment and supplements belong with a clinician.
Erectile dysfunction as a clinical entity is covered on the Erectile Dysfunction page.
Cautions and Drug Interactions
- Nitrate medications — nitroglycerin, isosorbide and other organic nitrates release NO directly. PDE5-inhibitor prescribing information lists organic nitrates as a contraindication because the combination can cause severe hypotension, and specifies an interval between the two. An additive effect of high-dose arginine with nitrates is theoretical; no trial was found for this page.
- Concurrent PDE5 inhibitors — in the combination trials, adverse events were more frequent on arginine plus tadalafil (67) than on arginine alone (11) or tadalafil alone (53) (Gallo 2020), and gastritis was more common when arginine was added to sildenafil (El-Wakeel 2020).
- Alpha-blockers (for benign prostatic hyperplasia) — tamsulosin, doxazosin and similar drugs carry a precaution in PDE5-inhibitor prescribing information because the combination can cause orthostatic hypotension. No trial of arginine with alpha-blockers was found for this page.
- Herpes simplex — in cell culture, herpes simplex virus needs arginine to replicate and lysine antagonises it; human trials of lysine supplements are small and mixed, and a 2015 Cochrane review found no evidence of efficacy for lysine in preventing cold sores. Whether arginine supplements make herpes outbreaks more frequent has not been tested in a trial found for this page. The lysine evidence is covered on the L-Lysine page.
- After a heart attack — in the VINTAGE MI trial, 153 patients after a first ST-elevation myocardial infarction took L-arginine (goal dose 3 g three times a day) or placebo for 6 months; 6 patients (8.6%) on arginine died versus none on placebo, enrollment was closed, and the authors concluded that L-arginine should not be recommended following acute myocardial infarction (Schulman 2006). The trial is discussed on the Cardiovascular page.
- Uncontrolled cardiovascular disease — the Princeton consensus recommendations address cardiac risk with sexual activity in men with known cardiovascular disease and emphasize confirming that cardiovascular health matches the physical demands of sexual activity before ED treatment is prescribed (Nehra 2012).
Key Research Papers
- Chen J et al. (1999). Effect of oral administration of high-dose nitric oxide donor L-arginine in men with organic erectile dysfunction: results of a double-blind, randomized, placebo-controlled study. BJU International — PubMed PMID: 10233492
- Stanislavov R, Nikolova V (2003). Treatment of erectile dysfunction with pycnogenol and L-arginine. Journal of Sex and Marital Therapy — PubMed PMID: 12851125 — an uncontrolled study: 40 men took arginine alone for one month, then arginine with a French maritime pine bark extract for two months; there was no placebo group.
- Cormio L et al. (2011). Oral L-citrulline supplementation improves erection hardness in men with mild erectile dysfunction. Urology — PubMed PMID: 21195829
- Rhim HC et al. (2019). The potential role of arginine supplements on erectile dysfunction: a systemic review and meta-analysis. Journal of Sexual Medicine — PubMed PMID: 30770070
- Burnett AL (2006). The role of nitric oxide in erectile dysfunction: implications for medical therapy. Journal of Clinical Hypertension — PubMed PMID: 17170606
- Goldstein I et al. (1998). Oral sildenafil in the treatment of erectile dysfunction. Sildenafil Study Group. NEJM — PubMed PMID: 9580646
- Klotz T et al. (1999). Effectiveness of oral L-arginine in first-line treatment of erectile dysfunction in a controlled crossover study. Urologia Internationalis — PubMed PMID: 10743698
- Aoki H et al. (2012). Clinical assessment of a supplement of Pycnogenol and L-arginine in Japanese patients with mild to moderate erectile dysfunction. Phytotherapy Research — PubMed PMID: 21618639
- Ledda A et al. (2010). Investigation of a complex plant extract for mild to moderate erectile dysfunction in a randomized, double-blind, placebo-controlled, parallel-arm study. BJU International — PubMed PMID: 20184576
- Andersson KE, Wagner G (1995). Physiology of penile erection. Physiological Reviews — PubMed PMID: 7831397
- Toda N et al. (2005). Nitric oxide and penile erectile function. Pharmacology and Therapeutics — PubMed PMID: 15866322
- Shamloul R, Ghanem H (2013). Erectile dysfunction. The Lancet — PubMed PMID: 23040455
- Shirai M et al. (2018). Oral L-citrulline and transresveratrol supplementation improves erectile function in men with phosphodiesterase 5 inhibitors: a randomized, double-blind, placebo-controlled crossover pilot study. Sexual Medicine — PubMed PMID: 30150102 — 20 men enrolled and 13 completed; the supplement combined citrulline with trans-resveratrol, so the effect of citrulline alone was not tested.
- Schulman SP et al. (2006). L-arginine therapy in acute myocardial infarction: the Vascular Interaction With Age in Myocardial Infarction (VINTAGE MI) randomized clinical trial. JAMA — PubMed PMID: 16391217 — enrollment was closed after 6 deaths (8.6%) in the arginine group and none on placebo.
- Hackett G et al. (2018). British Society for Sexual Medicine guidelines on the management of erectile dysfunction in men: 2017. Journal of Sexual Medicine — PubMed PMID: 29550461
- Stanislavov R, Nikolova V, Rohdewald P (2008). Improvement of erectile function with Prelox: a randomized, double-blind, placebo-controlled, crossover trial. International Journal of Impotence Research — PubMed PMID: 17703218
- Shirai M et al. (2021). Oral Testofen, L-citrulline, resveratrol, and caffeine supplement drink improves sexual function in men with phosphodiesterase 5 inhibitors: randomized, double-blind, placebo-controlled crossover pilot study. World Journal of Men's Health — PubMed PMID: 33151048
- Gallo L et al. (2020). The daily therapy with L-arginine 2,500 mg and tadalafil 5 mg in combination and in monotherapy for the treatment of erectile dysfunction: a prospective, randomized multicentre study. Sexual Medicine — PubMed PMID: 32192966
- El Taieb M, Hegazy E, Ibrahim A (2019). Daily oral L-arginine plus tadalafil in diabetic patients with erectile dysfunction: a double-blinded, randomized, controlled clinical trial. Journal of Sexual Medicine — PubMed PMID: 31326304
- El-Wakeel LM et al. (2020). Efficacy and tolerability of sildenafil/L-arginine combination relative to sildenafil alone in patients with organic erectile dysfunction. Andrology — PubMed PMID: 31267684
- Wright PJ (2006). Comparison of phosphodiesterase type 5 (PDE5) inhibitors. International Journal of Clinical Practice — PubMed PMID: 16780568
- Smith WB 2nd et al. (2013). PDE5 inhibitors: considerations for preference and long-term adherence. International Journal of Clinical Practice — PubMed PMID: 23869678
- Yafi FA, Sharlip ID, Becher EF (2018). Update on the safety of phosphodiesterase type 5 inhibitors for the treatment of erectile dysfunction. Sexual Medicine Reviews — PubMed PMID: 28923561
- Nehra A et al. (2012). The Princeton III Consensus recommendations for the management of erectile dysfunction and cardiovascular disease. Mayo Clinic Proceedings — PubMed PMID: 22862865
- Köhler TS et al. (2024). The Princeton IV Consensus recommendations for the management of erectile dysfunction and cardiovascular disease. Mayo Clinic Proceedings — PubMed PMID: 39115509
PubMed Topic Searches
Connections
- All Amino Acids
- Arginine Overview
- Arginine Benefits Hub
- Arginine for Cardiovascular Health
- Arginine for Wound Healing
- Arginine for Immune Function
- Erectile Dysfunction
- Cardiovascular Disease
- Hypertension
- Diabetes
- Metabolic Syndrome
- Lysine
- Lysine
- Taurine
- Kidney Function
- Citrulline — the alternative NO precursor that worked at a fraction of the arginine dose.
- History
- Sources