Beta-Carotene vs Preformed Retinol — The Conversion Problem
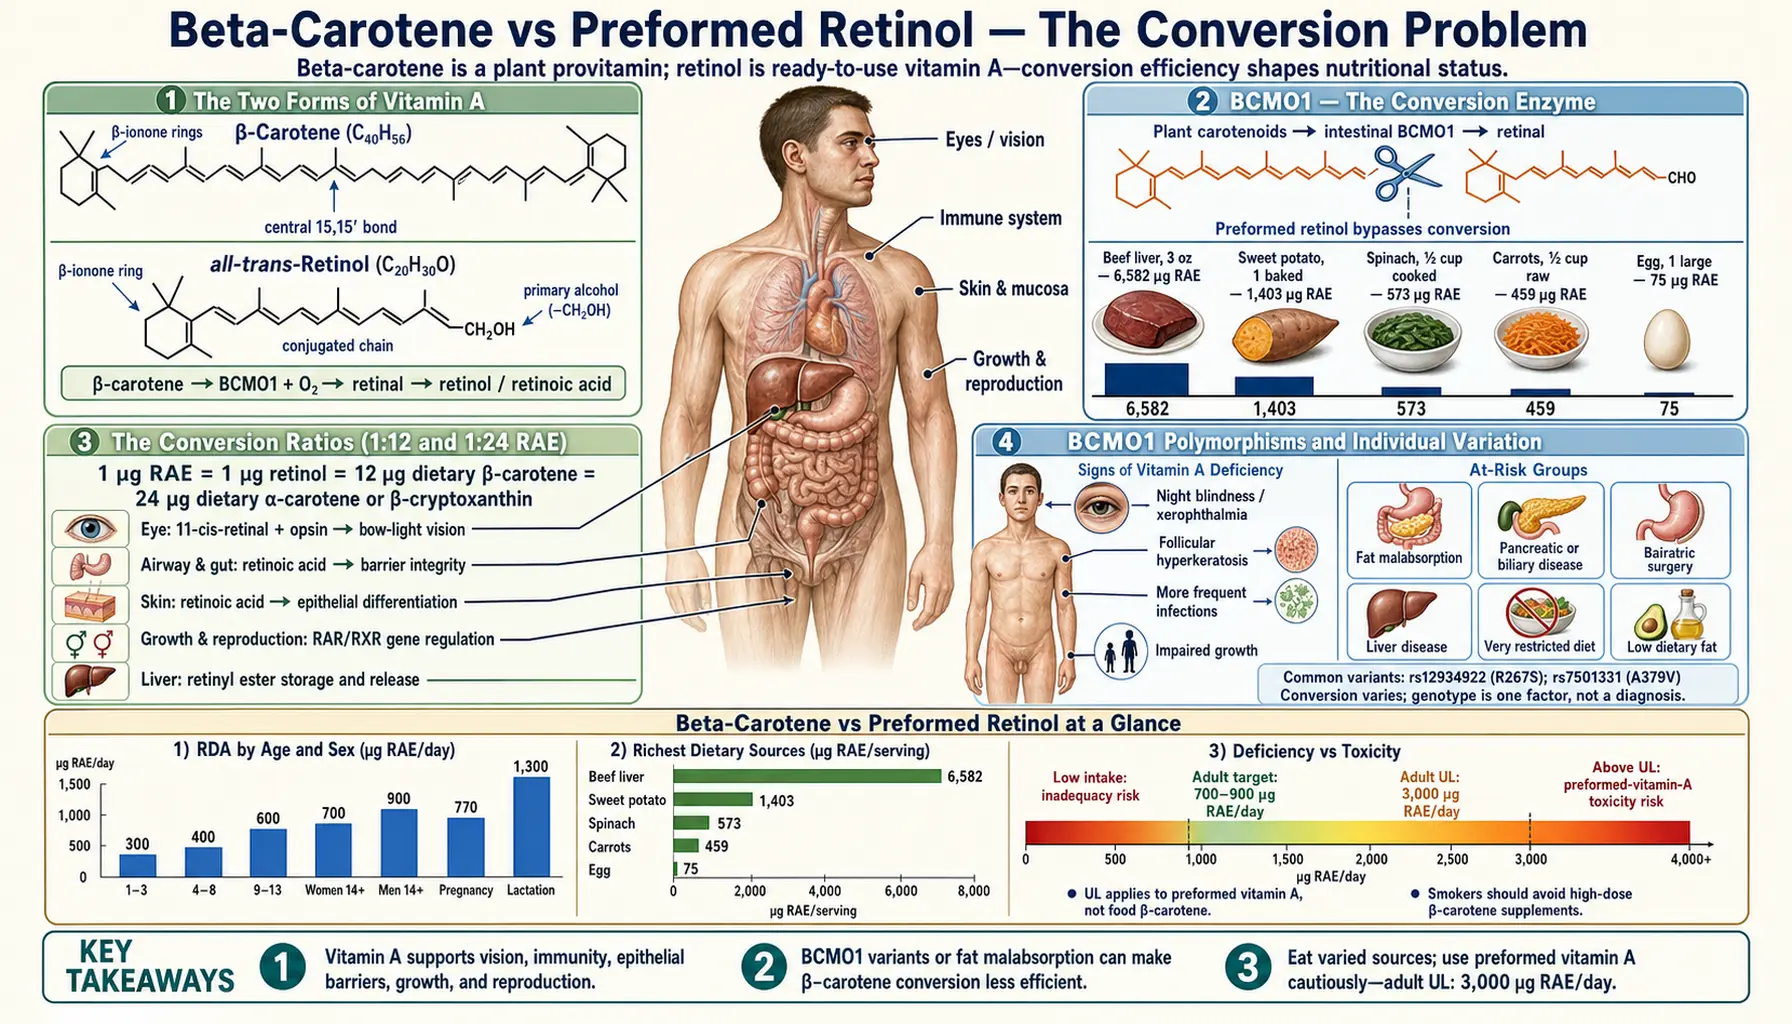
Plant-source beta-carotene and animal-source preformed retinol are both labeled "Vitamin A" on food and supplement packaging, but they behave very differently in the human body. Beta-carotene is converted to retinol by a single enzyme, beta-carotene oxygenase 1 (BCMO1), with highly variable efficiency — the official conversion ratio is 1:12 for dietary beta-carotene (dark leafy greens included) and 1:24 for alpha-carotene and beta-cryptoxanthin, but individual conversion rates vary widely; in one study, women carrying common BCMO1 variants converted 32% to 69% less beta-carotene. The pivotal ATBC and CARET trials documented that high-dose isolated beta-carotene supplements actually increased lung cancer in current and former heavy smokers, fundamentally reshaping public health thinking. Meanwhile preformed retinol bypasses the conversion bottleneck but accumulates in the liver and produces predictable teratogenicity at >3,000 mcg RAE/day chronic intake during pregnancy. This deep-dive unpacks the conversion biology, the genetic variation, the trial cautions, and how each form fits different groups of people.
Table of Contents
- The Two Forms of Vitamin A
- BCMO1 — The Conversion Enzyme
- The Conversion Ratios (1:12 and 1:24 RAE)
- BCMO1 Polymorphisms and Individual Variation
- Who Needs Preformed Retinol
- Retinyl Palmitate vs Retinyl Acetate
- The ATBC Trial — Beta-Carotene and Smokers
- The CARET Trial — Confirmation
- Liver Storage Kinetics
- Teratogenicity at High Preformed Doses
- Vitamin A Sources by Group
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Two Forms of Vitamin A
The phrase "Vitamin A" on a food label, supplement label, or nutrition fact panel can refer to two chemically distinct categories of molecules with very different metabolic behavior:
- Preformed Vitamin A (retinoids) — molecules with the retinol backbone already assembled, requiring no further conversion to be biologically active. The forms found in food and supplements are retinol itself, retinyl palmitate, and retinyl acetate. Sources are exclusively animal: liver (richest), egg yolks, dairy fat, fish oils, cod liver oil. The body absorbs preformed retinol very efficiently — approximately 70-90% absorbed in the small intestine, stored in the liver as retinyl esters, and mobilized as needed bound to retinol-binding protein.
- Provitamin A carotenoids — orange and yellow pigment molecules in plants that the body can convert to retinol on demand. The major dietary provitamin A carotenoid is beta-carotene; minor ones include alpha-carotene and beta-cryptoxanthin. These molecules are found in carrots, sweet potatoes, pumpkin, dark leafy greens (where the chlorophyll masks the orange color), mangoes, papayas, and apricots. Hundreds of additional carotenoids exist in plants but do not get converted to Vitamin A — lutein, zeaxanthin, lycopene, and astaxanthin are antioxidants but not provitamin A.
The fundamental difference: preformed retinol is directly usable but uncontrollably accumulating, while provitamin A carotenoids must be converted but are self-regulating — the body converts only as much beta-carotene to retinol as it needs and stores or excretes the rest. This regulatory difference explains every clinical contrast between the two forms.
The unified measurement system that lets you compare them is Retinol Activity Equivalents (RAE). By definition, 1 mcg RAE = 1 mcg of preformed retinol = 2 mcg of supplemental beta-carotene = 12 mcg of dietary beta-carotene = 24 mcg of dietary alpha-carotene or beta-cryptoxanthin. The conversion ratios reflect the realistic average efficiency of carotenoid-to-retinol conversion in the human gut and liver.
BCMO1 — The Conversion Enzyme
The conversion of beta-carotene to retinol is catalyzed primarily by a single enzyme: beta-carotene-15,15'-monooxygenase, abbreviated as BCMO1 (also called BCO1 in newer nomenclature). The enzyme cleaves the central 15,15' double bond of beta-carotene, producing two molecules of retinaldehyde, which can then be reduced to retinol or oxidized to retinoic acid.
BCMO1 is expressed primarily in the small intestinal enterocytes, with secondary expression in the liver, kidney, and several other tissues. The intestinal expression is regulated by retinoic acid feedback — when the body has adequate Vitamin A, BCMO1 transcription is suppressed, reducing further beta-carotene conversion. This negative feedback loop is what makes plant-source beta-carotene self-regulating and prevents the carotenodermia patient from progressing to overt hypervitaminosis A despite consuming pounds of carrots per week.
A secondary cleavage enzyme, BCO2 (beta-carotene oxygenase 2), performs asymmetric cleavage of beta-carotene producing apocarotenoids and a single retinal molecule. BCO2 is more widely expressed across tissues and may contribute meaningfully to total retinol production, particularly in extrahepatic tissues.
Both enzymes require iron as a cofactor. Iron deficiency can subtly impair carotenoid-to-retinol conversion, contributing to the Vitamin A deficiency seen in iron-deficient populations even when carotenoid intake appears adequate. This is part of the rationale for the combined iron/Vitamin A supplementation packages used in some developing-country nutrition programs.
The Conversion Ratios (1:12 and 1:24 RAE)
The Institute of Medicine's 2001 Dietary Reference Intake (DRI) report dramatically revised the conversion ratio between dietary beta-carotene and retinol — from the older 1:6 ratio (used in International Units calculations) to a 1:12 ratio for dietary beta-carotene from all foods, dark leafy greens included, and 1:24 for dietary alpha-carotene and beta-cryptoxanthin.
The basis for this revision was studies showing that the bioavailability and conversion efficiency of beta-carotene in real foods is substantially lower than older isotope-tracer studies had suggested. Key factors that reduce the ratio:
- Food matrix — beta-carotene in raw vegetables is partly trapped inside intact plant cell walls. Cooking softens the matrix and increases bioavailability 3-4 fold. A cooked carrot delivers far more usable Vitamin A than a raw carrot of equal beta-carotene content.
- Fat co-ingestion — beta-carotene is fat-soluble; absorption requires bile salt micellation and dietary fat. A salad with avocado or olive oil dressing yields 4-5 times the carotenoid absorption of a fat-free salad.
- Fiber content — high fiber meals reduce carotenoid absorption slightly through bile-salt sequestration and faster transit time.
- Variety of carotenoid — beta-carotene is twice as efficient a provitamin A as alpha-carotene or beta-cryptoxanthin, because it has the conjugated polyene structure on both halves of the molecule. The DRI uses 1:12 for beta-carotene and 1:24 for alpha-carotene and beta-cryptoxanthin.
- Vitamin A status — an already-replete person converts less beta-carotene to retinol (feedback regulation), while a deficient person converts more. The 1:12 number is an average across mixed-status populations.
The numerical translation:
- The adult male Recommended Dietary Allowance (RDA) of 900 mcg RAE/day ≈ 900 mcg preformed retinol OR 1,800 mcg supplemental beta-carotene OR 10,800 mcg (10.8 mg) dietary beta-carotene from typical food sources
- One large cooked sweet potato delivers approximately 1,400 mcg RAE (or 16,800 mcg of beta-carotene) — well above adult Recommended Dietary Allowance from a single food serving
- One medium raw carrot delivers approximately 500-700 mcg RAE depending on size
- One cup of cooked kale delivers approximately 900 mcg RAE
Practical implication: a healthy mixed diet with regular orange/yellow vegetables and dark leafy greens easily meets the Vitamin A Recommended Dietary Allowance through carotenoids alone, even with the conservative 1:12 ratio.
BCMO1 Polymorphisms and Individual Variation
The 1:12 conversion ratio is a population average. Individual variation around that average is substantial, and a significant fraction is genetic. The BCMO1 gene has two common single-nucleotide polymorphisms (SNPs) that meaningfully reduce enzyme activity:
- R267S (rs12934922) — an arginine-to-serine substitution in the protein. Leung et al. (2009) gave no separate conversion figure for this variant alone; female volunteers carrying both 267S and 379V converted beta-carotene about 69% less well (measured as the retinyl palmitate to beta-carotene ratio), and the double-variant enzyme had 57% lower activity in the test tube.
- A379V (rs7501331) — an alanine-to-valine substitution. Carriers of 379V in the same study converted about 32% less well.
Both variants are common: Leung et al. (2009) found variant allele frequencies of 42% for R267S and 24% for A379V. A later study by the same group (Lietz 2012) found that three further variants upstream of the gene (rs6420424, rs11645428 and rs6564851) reduced conversion in female volunteers by 59, 51 and 48%, with allele frequencies that differ widely between ethnic groups. Up to 45% of people are low responders to dietary beta-carotene.
The clinical phenotype of reduced BCMO1 activity:
- Reduced conversion of dietary beta-carotene to retinol
- Slightly higher serum beta-carotene (the unconverted precursor accumulates)
- Slightly lower or marginal serum retinol on a vegetarian diet that relies on carotenoids
- Higher risk of functional Vitamin A deficiency on a vegan diet
- Better response to preformed retinol supplementation than to beta-carotene supplementation
Consumer genetic tests, read through third-party interpretation services, report BCMO1 variants and can identify carriers. In people who eat mainly plant-source Vitamin A and have signs of low retinol (night vision difficulty, persistently low serum retinol despite high dietary carotenoid intake), the BCMO1 genotype may explain the gap; preformed retinol from animal foods or supplements does not depend on this enzyme.
A small fraction of people have functionally near-absent BCMO1 due to compound heterozygosity for multiple SNPs or rare loss-of-function variants. These individuals are functionally dependent on preformed retinol and can develop deficiency on an otherwise nutritious vegan diet.
Who Needs Preformed Retinol
While the typical mixed-diet adult easily meets Vitamin A needs from carotenoid conversion, certain populations have a clinically meaningful need for preformed retinol from animal sources or supplements:
- Strict vegans with low intake of cooked orange/yellow vegetables and dark leafy greens, especially if also iron-deficient (iron is a BCMO1 cofactor)
- BCMO1 reduced-activity genotype carriers on a vegetarian or vegan diet (see above)
- Premature infants and very young children with limited BCMO1 expression and high relative Vitamin A demand
- Patients with fat malabsorption (cystic fibrosis, pancreatic insufficiency, Crohn's disease, celiac, post-bariatric surgery, short bowel syndrome) — both pathways are impaired but preformed retinyl ester supplementation is more reliably absorbed
- Patients with diabetes — some evidence that diabetic gut and liver have reduced BCMO1 activity
- Hypothyroid patients — thyroid hormone supports BCMO1 expression; severe hypothyroidism reduces conversion
- Iron-deficient women (iron is a BCMO1 cofactor)
- Heavy alcohol users with liver disease — impaired hepatic Vitamin A storage and mobilization, and direct depletion of stores by alcohol-induced hepatic stellate cell loss
The classic food source of preformed retinol is liver — particularly beef liver, which provides approximately 6,500 mcg RAE per 3 oz serving. One serving per week comfortably meets adult Recommended Dietary Allowance. Cod liver oil provides a more controlled and palatable alternative at approximately 1,300 mcg RAE per teaspoon, with the bonus of Vitamin D and eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA). Egg yolks, butter from grass-fed cows, and full-fat dairy provide moderate amounts.
For more on the dietary side of preformed Vitamin A, see our Organ Meats page.
Retinyl Palmitate vs Retinyl Acetate
Supplemental preformed Vitamin A is almost always provided as an ester — either retinyl palmitate or retinyl acetate. Both are hydrolyzed in the gut to free retinol before absorption, and both ultimately deliver the same retinol to circulation.
| Aspect | Retinyl Palmitate | Retinyl Acetate |
|---|---|---|
| Esterified with | Palmitic acid (16-carbon saturated fatty acid) | Acetic acid (2-carbon) |
| Natural form in liver | Yes — the body's storage form | No — synthetic |
| Bioavailability | Comparable when taken with fat | Slightly more rapid absorption |
| Stability | Excellent (the dominant supplement form) | Good but less stable than palmitate |
| Common in | Multivitamins, cosmetics, fortified milk | Some pharmaceutical preparations |
Practically, the two are interchangeable for nutritional purposes. Retinyl palmitate is the more common supplement form because of its better stability and the fact that it matches the body's natural storage form in hepatic stellate cells. The same retinyl palmitate appears in cosmetic skincare formulations as a gentle topical retinoid (see Skin & Cellular Differentiation) and in fortified milk and cereals as part of public nutrition programs.
Cod liver oil contains Vitamin A primarily as a complex mixture of natural retinyl esters from the cod liver itself — not as added retinyl palmitate. Some traditional-foods proponents argue this is preferable to single-ester supplementation, but the controlled clinical evidence does not show meaningful difference between the natural ester mixture and added retinyl palmitate.
The ATBC Trial — Beta-Carotene and Smokers
The Alpha-Tocopherol Beta-Carotene Cancer Prevention Study (ATBC) was a landmark Finnish trial published in NEJM in 1994. 29,133 male smokers aged 50-69 were randomized to one of four arms: alpha-tocopherol (Vitamin E) 50 mg/day, beta-carotene 20 mg/day, both, or placebo. The trial was designed to test whether antioxidant supplementation could prevent lung cancer in this high-risk population.
Results were dramatically opposite to the hypothesis:
- The beta-carotene group had an 18% higher incidence of lung cancer than placebo (statistically significant)
- The beta-carotene group also had higher overall mortality (8% increase, statistically significant)
- Increased death from cardiovascular disease was also observed in the beta-carotene group
- The Vitamin E arm showed no significant effect on lung cancer either positively or negatively
Follow-up continued for five to eight years. Follow-up analyses showed the increased lung cancer risk was concentrated in the heaviest smokers and in those who continued to smoke during the trial.
The mechanism proposed for the beta-carotene harm: in the high-oxidative-stress environment of smokers' lungs, beta-carotene itself becomes pro-oxidant rather than antioxidant. The autooxidation of beta-carotene in the presence of cigarette-smoke-derived oxidants produces reactive carotenoid breakdown products (4-oxo-retinoic acid, beta-apo-carotenals) that may promote rather than prevent carcinogenesis. The same molecule is antioxidant at low oxidative stress and pro-oxidant at high oxidative stress — a "redox switch" behavior that contradicts the simple antioxidant model.
The CARET Trial — Confirmation
The Beta-Carotene and Retinol Efficacy Trial (CARET) was a U.S. trial that ran in parallel to ATBC, testing essentially the same hypothesis but with the addition of preformed retinol. 18,314 participants at high lung cancer risk (heavy smokers, former smokers, and asbestos-exposed workers) were randomized to a combination of beta-carotene 30 mg/day + retinyl palmitate 25,000 international units (IU)/day, or placebo. Published in NEJM in 1996.
Results essentially replicated ATBC:
- The active arm had a 28% higher incidence of lung cancer than placebo
- 17% higher overall mortality
- 26% higher cardiovascular mortality
- The trial was terminated 21 months early due to the harm signal
Together, ATBC and CARET fundamentally reshaped thinking about isolated antioxidant supplementation. The reductionist hypothesis that "antioxidants are good, more is better" failed empirically when subjected to large randomized testing. The complex behavior of isolated antioxidants in high-stress redox environments is now a central caution in nutritional supplementation research.
Practical consequences:
- In current and former heavy smokers, isolated high-dose beta-carotene supplements (20 mg/day in ATBC, 30 mg/day in CARET) were followed by more lung cancer
- Food-source beta-carotene from carrots, sweet potatoes, leafy greens has not shown the same harm signal — the matrix and mixed-carotenoid context may protect
- The AREDS2 trial in 2013 substituted lutein/zeaxanthin for beta-carotene specifically because of the ATBC/CARET signal in former smokers
- The standard multivitamin formulations have reduced or eliminated beta-carotene since the 1990s in favor of lower-dose mixed carotenoids or none at all
The trials did not show harm from preformed retinol at the CARET dose (25,000 international units/day) over the trial duration — though chronic retinol intake at that dose carries other concerns (hepatotoxicity, bone loss, teratogenicity in pregnancy) discussed below.
Liver Storage Kinetics
Approximately 70-90% of total body Vitamin A is stored in the liver, predominantly as retinyl palmitate within hepatic stellate cells (also called Ito cells or fat-storing cells of the perisinusoidal space). The healthy adult liver contains 100-1,000 mcg of retinyl ester per gram of liver tissue, equivalent to approximately 6-12 months of normal Vitamin A turnover.
This large hepatic reservoir explains several clinical features:
- Long lag time before deficiency develops — an adult with normal baseline liver stores can go 6-12 months on a Vitamin-A-poor diet before developing functional deficiency. Children with smaller liver reserves can develop deficiency in weeks-to-months.
- Single megadose strategy works — the WHO 200,000 international units biannual supplementation program for children works because a single large dose floods the liver storage compartment and can supply the body for 4-6 months as the storage form slowly releases retinol to circulation.
- Slow accumulation of toxicity — chronic high-dose preformed Vitamin A doesn't produce acute hepatotoxicity. Liver damage accumulates over months-to-years of intake above approximately 25,000 international units/day, eventually producing elevated transaminases, then portal fibrosis, then frank cirrhosis with stellate cell loss.
- Stellate cell activation and fibrosis — in chronic alcoholic liver disease, hepatitis C, and other liver injuries, hepatic stellate cells lose their stored Vitamin A and trans-differentiate into activated myofibroblasts that produce extracellular matrix and drive fibrosis. The lost Vitamin A from stellate cells is part of the depletion mechanism in alcoholic liver disease.
Measuring liver Vitamin A directly requires biopsy and is rarely done outside research settings. Serum retinol is the standard clinical marker, but it is tightly homeostatically regulated and remains within normal range until liver stores are severely depleted — a normal serum retinol does not rule out marginal deficiency. The relative dose response (RDR) test is a more sensitive functional assessment: serum retinol is measured at baseline, the patient takes a small Vitamin A dose, and serum retinol is re-measured at 5 hours. A large rise in serum retinol indicates depleted liver stores (the small bolus dose displaces retinol from RBP rapidly because the normal feedback regulation is missing). RDR is rarely used clinically but is the gold-standard research method for assessing marginal status.
Teratogenicity at High Preformed Doses
Excessive preformed Vitamin A (retinol, retinyl esters) during pregnancy is teratogenic. The classic Rothman et al. 1995 NEJM study established the dose-response:
- Pregnant women consuming >15,000 international units/day (4,500 mcg RAE/day) preformed Vitamin A from food and supplements had a prevalence ratio of 3.5 for birth defects of cranial-neural-crest origin, compared with women consuming 5,000 international units or less; for more than 10,000 international units/day from supplements alone, the ratio was 4.8. The authors estimated that about 1 infant in 57 born to women taking more than 10,000 international units/day as supplements had a malformation attributable to the supplement
- The increased malformations affected structures derived from cranial neural crest cells: facial deformities (cleft palate, microtia, micrognathia), central nervous system (CNS) anomalies (hydrocephalus, microcephaly), cardiac outflow tract defects, thymic hypoplasia
- The study found an apparent threshold near 10,000 international units/day of supplemental Vitamin A; the Institute of Medicine upper limit for adults, pregnancy included, is 3,000 mcg RAE (10,000 international units) per day of preformed Vitamin A
- Provitamin A carotenoids did not show increased teratogenic risk — food-source beta-carotene from carrots, sweet potatoes, leafy greens is safe at any practical intake during pregnancy
The mechanism: at high concentrations, retinoic acid (the active metabolite of retinol) saturates the normal feedback regulation of RAR/RXR signaling and produces pathological gene-expression changes in embryonic neural crest cells. The cranial neural crest is the source population for facial cartilage, outflow tract septum of the heart, and thymic stroma — precisely the tissues affected by retinoic acid embryopathy.
The same teratogenic mechanism is the basis for the absolute pregnancy contraindication for oral isotretinoin and the iPLEDGE pregnancy-prevention program described on the Skin & Cellular Differentiation page. Topical retinoids are also typically avoided in pregnancy as a precaution, though the systemic absorption from topical use is very low and observational studies have not consistently demonstrated harm.
Figures that matter for women who are pregnant or planning pregnancy:
- The upper limit for preformed Vitamin A is 3,000 mcg RAE (10,000 international units) per day from all sources combined
- One 3-oz serving of beef liver provides approximately 6,500 mcg RAE
- Prenatal vitamins typically contain 1,800-2,700 mcg RAE per dose — well within the safe range when no other high-dose source is added
- High-potency Vitamin A supplements (10,000 international units and above) reach the level at which Rothman et al. found the apparent threshold for birth defects
- Cod liver oil provides about 1,300 mcg RAE per teaspoon
- Beta-carotene from food: converted on demand with feedback regulation that prevents toxicity
- Oral isotretinoin, acitretin, bexarotene: contraindicated in pregnancy
- Topical tretinoin and adapalene: typically discontinued as a precaution
Vitamin A Sources by Group
Adults eating a mixed diet
- The Recommended Dietary Allowance is 700-900 mcg RAE/day, and it can be met from food
- Orange/yellow vegetables (sweet potato, carrot, butternut squash) give more usable beta-carotene when cooked with some fat
- Dark leafy greens (kale, spinach, collards) are commonly cooked with olive oil or butter, which aids carotenoid absorption
- Organ meats (beef liver, chicken liver), cod liver oil, egg yolks and full-fat dairy supply preformed retinol
- A diet with these foods meets the Recommended Dietary Allowance without supplementation
Strict vegans
- All Vitamin A comes from carotenoids, so cooked orange/yellow vegetables and dark leafy greens eaten with fat (avocado, olive oil, tahini) are the main sources
- BCMO1 genotype testing can show reduced-activity variants when symptoms suggest functional deficiency
- Low-dose retinyl palmitate supplements (1,500-3,000 mcg RAE / 5,000-10,000 international units per day) are the form described for carriers of reduced-activity variants, since they do not need conversion
- Serum retinol is the usual blood test for status
People with malabsorption (cystic fibrosis, Crohn's, post-bariatric)
- Water-miscible retinyl palmitate, 3,000-10,000 mcg RAE (10,000-33,000 international units) per day depending on severity, is the form and range described for these conditions
- Cystic fibrosis: the CF Foundation publishes age-stratified guidelines
- Clinics typically measure serum retinol every 6-12 months
- The usual target is serum retinol in the mid-normal range (1.5-3.0 µmol/L)
Pregnancy
- A standard prenatal vitamin (1,800-2,700 mcg RAE) plus food sources stays within the 3,000 mcg RAE upper limit when no other high-dose source is added
- High-dose preformed Vitamin A supplements are linked to birth defects (see above)
- A 3-oz serving of beef liver provides approximately 6,500 mcg RAE
- Beta-carotene from food has not shown teratogenic risk
- Oral retinoid drugs are contraindicated in pregnancy
Age-related macular degeneration (AMD)
- The AREDS2 formula substituted lutein/zeaxanthin for beta-carotene because of the lung-cancer signal in smokers and former smokers
- Isolated high-dose beta-carotene supplements carry the ATBC/CARET lung-cancer signal in smokers
- See Vision & Eye Health for full details
Cautions
- Teratogenicity in pregnancy — the most consequential warning. Preformed Vitamin A above about 10,000 international units (3,000 mcg RAE)/day in pregnancy, especially from supplements, was associated with birth defects of cranial-neural-crest origin (Rothman 1995). Provitamin A carotenoids are safe at any practical intake. See above for detail.
- Beta-carotene in current and former heavy smokers — ATBC and CARET trials documented increased lung cancer and overall mortality from isolated high-dose beta-carotene supplements (20-30 mg/day) in this population. Food-source beta-carotene appears safe; isolated supplements are not for this population. The AREDS2 formula substituted lutein/zeaxanthin for beta-carotene specifically because of this signal.
- Chronic hepatotoxicity from preformed Vitamin A — sustained intake above approximately 25,000 international units/day for months-to-years can cause liver injury ranging from elevated transaminases to overt cirrhosis. Patients on high-dose retinyl palmitate for medical indications (retinitis pigmentosa, severe ichthyosis) require periodic liver function monitoring.
- Bone loss with chronic high preformed Vitamin A intake — epidemiologic studies suggest sustained intake above 1,500 mcg RAE/day may be associated with reduced bone mineral density and increased hip fracture risk in older adults. Beta-carotene does not carry this signal.
- Acute hypervitaminosis A — single megadoses >500,000 international units in adults can cause headache, nausea, vomiting, increased intracranial pressure, peeling skin. Recovery typically complete with discontinuation.
- Drug interactions — orlistat, cholestyramine, mineral oil, sucralfate reduce Vitamin A absorption. Anticonvulsants accelerate retinol catabolism. Alcohol depletes hepatic stores.
- BCMO1 polymorphisms — common variants reduced conversion by 32-69% in a study of female volunteers. In vegetarians and vegans with marginal serum retinol despite high carotenoid intake, genetic testing can show these variants, and preformed retinol from animal sources or supplements does not depend on the enzyme.
- Iron deficiency — iron is a BCMO1 cofactor; iron deficiency impairs carotenoid-to-retinol conversion. Iron repletion can improve functional Vitamin A status even without separate Vitamin A intervention.
Key Research Papers
- Trumbo P, Yates AA, Schlicker S, Poos M (2001). Dietary reference intakes: vitamin A, vitamin K, arsenic, boron, chromium, copper, iodine, iron, manganese, molybdenum, nickel, silicon, vanadium, and zinc (summary of the Institute of Medicine report). Journal of the American Dietetic Association. — PubMed PMID: 11269606
- The Alpha-Tocopherol Beta Carotene Cancer Prevention Study Group (1994). The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. NEJM. — PubMed PMID: 8127329
- Omenn GS et al. (1996). Effects of a combination of beta carotene and vitamin A on lung cancer and cardiovascular disease (CARET). NEJM. — PubMed PMID: 8602180
- Leung WC et al. (2009). Two common single nucleotide polymorphisms in the gene encoding beta-carotene 15,15'-monoxygenase alter beta-carotene metabolism in female volunteers. FASEB Journal. — PubMed PMID: 19103647
- Lietz G et al. (2012). Single nucleotide polymorphisms upstream from the β-carotene 15,15'-monoxygenase gene influence provitamin A conversion efficiency in female volunteers. Journal of Nutrition. — PubMed PMID: 22113863
- Hickenbottom SJ et al. (2002). Variability in conversion of beta-carotene to vitamin A in men as measured by using a double-tracer study design. AJCN. — PubMed PMID: 11976165
- Rothman KJ et al. (1995). Teratogenicity of high vitamin A intake. NEJM. — PubMed PMID: 7477116
- Lammer EJ et al. (1985). Retinoic acid embryopathy. NEJM. — PubMed PMID: 3162101
- Melhus H et al. (1998). Excessive dietary intake of vitamin A is associated with reduced bone mineral density and increased risk for hip fracture. Annals of Internal Medicine. — PubMed PMID: 9841582
- Penniston KL, Tanumihardjo SA (2006). The acute and chronic toxic effects of vitamin A. AJCN. — PubMed PMID: 16469975
- Tanumihardjo SA (2011). Vitamin A: biomarkers of nutrition for development. AJCN. — PubMed PMID: 21715511
- Borel P, Desmarchelier C (2018). Bioavailability of fat-soluble vitamins and phytochemicals in humans: effects of genetic variation. Annual Review of Nutrition. — PubMed PMID: 30130464
- Harrison EH (2012). Mechanisms involved in the intestinal absorption of dietary vitamin A and provitamin A carotenoids. Biochimica et Biophysica Acta. — PubMed PMID: 21718801
PubMed Topic Searches
Connections
- All Vitamins
- Vitamin A Overview
- Vitamin A Benefits Hub
- Vitamin A for Vision
- Vitamin A for Immune Function
- Vitamin A for Skin
- Organ Meats (Beef Liver, Cod Liver Oil)
- Sweet Potatoes (Beta-Carotene)
- Kale (Mixed Carotenoids)
- Vitamin D3
- Vitamin E
- Vitamin K2
- Zinc (RBP Synthesis)
- Iron (BCMO1 Cofactor)
- Celiac Disease
- Crohn's Disease
- Deficiency
- Toxicity
- History
- Sources