Vitamin A — Benefits Deep Dive
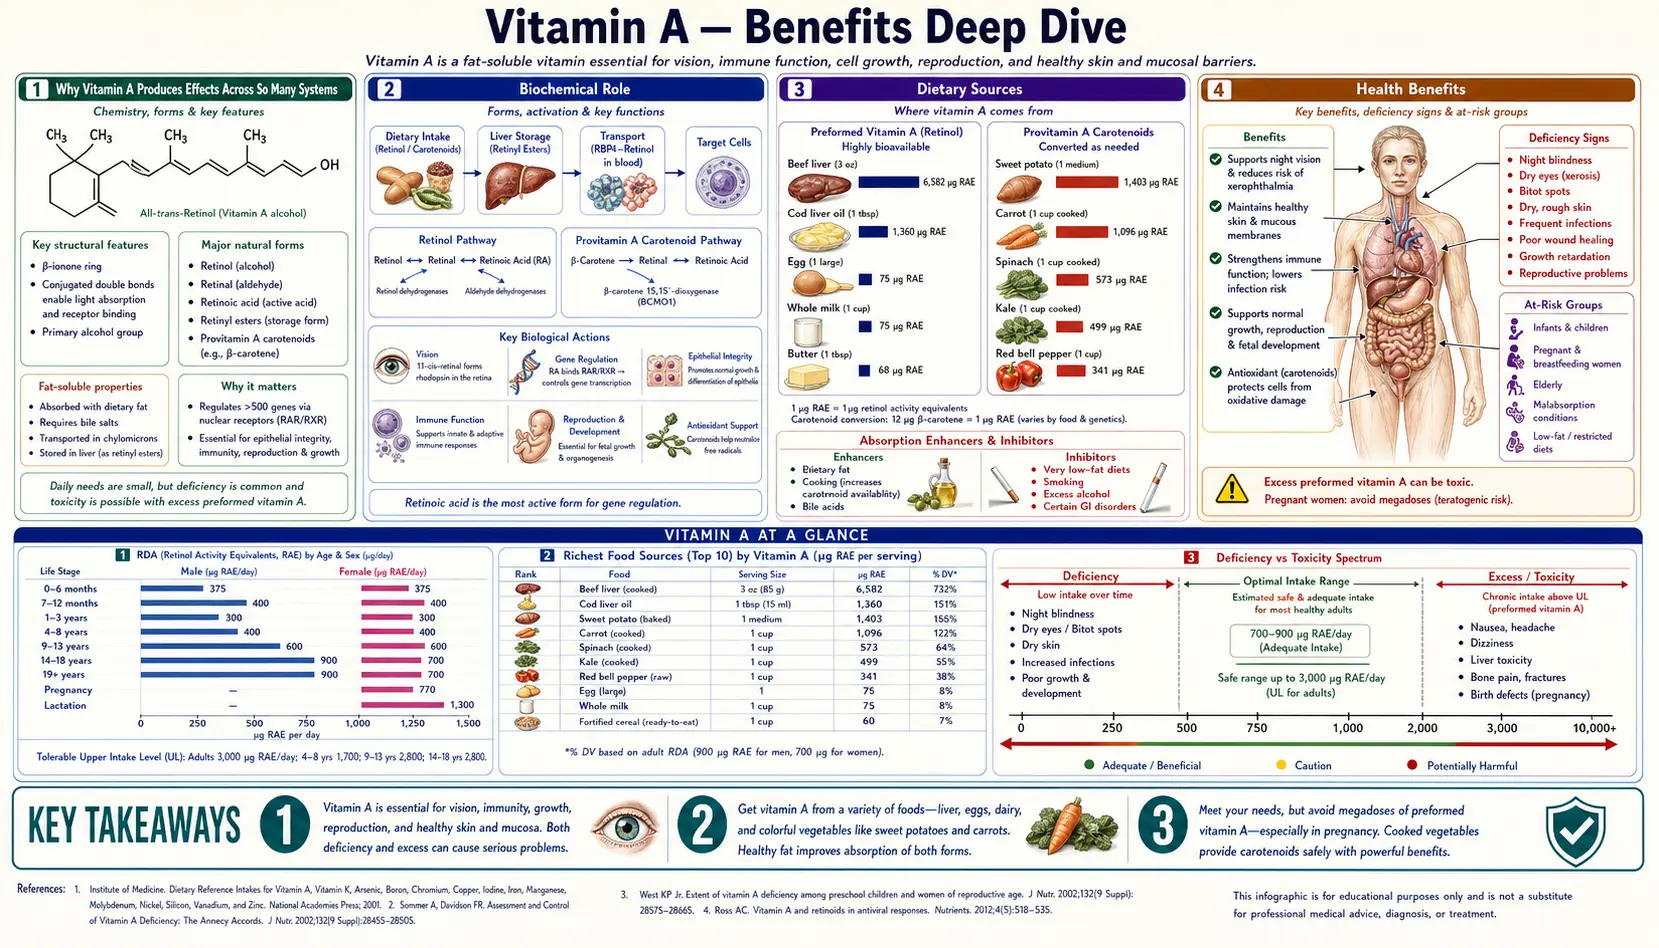
Vitamin A is the single fat-soluble vitamin most universally required across the major organ systems. It is the only molecule the human body uses both as a visual chromophore (11-cis-retinal in rhodopsin) and as a nuclear-receptor ligand (all-trans-retinoic acid binding the retinoic acid receptor (RAR), which pairs with the retinoid X receptor (RXR), to regulate hundreds of genes). Four benefit pages below explore the conditions where Vitamin A produces the largest clinical effect — preventable blindness, immune-mediated infection mortality, dermatology and cellular differentiation disorders, and the metabolism that shapes how much vitamin A a person gets from plant-source beta-carotene compared with animal-source retinol.
Deep-Dive Articles
Vision & Eye Health
The 11-cis-retinal rhodopsin cycle, night blindness (nyctalopia) as first deficiency sign, xerophthalmia and corneal melting in severe deficiency, Bitot's spots, the WHO finding that Vitamin A deficiency remains the leading preventable cause of childhood blindness, the AREDS / AREDS2 trials and the substitution of Lutein and Zeaxanthin for beta-carotene in the second-generation formulation.
Read the deep dive →Immune Function
Why Vitamin A is the original "anti-infective vitamin." T-cell maturation and the balance of T helper 17 and regulatory T cells (Th17/Treg) via retinoic acid signaling, mucosal immunity at the gut and respiratory epithelium, the WHO measles dose (200,000 international units (IU), or 100,000 IU in infants, each day for two days), for which a 2005 Cochrane review found no significant fall in deaths when all trials were pooled (relative risk 0.70, 95% CI 0.42 to 1.15) but fewer deaths in children under two given two 200,000 IU doses (relative risk 0.18), gut barrier integrity, and the deficiency-driven cascade that increases susceptibility to respiratory and diarrheal infection.
Read the deep dive →Skin & Cellular Differentiation
The retinoid mechanism in keratinocyte differentiation, topical tretinoin for acne and photoaging, oral isotretinoin for severe nodulocystic acne, acitretin for psoriasis, the gentler retinaldehyde alternative, retinyl esters in over-the-counter (OTC) cosmetics, and the strict pregnancy contraindication for oral retinoids due to teratogenicity.
Read the deep dive →Beta-Carotene vs Preformed Retinol
The BCMO1 (beta-carotene oxygenase 1) enzyme converts plant beta-carotene to retinol with highly variable efficiency — the Institute of Medicine counts 12 micrograms of dietary beta-carotene, or 24 of other provitamin A carotenoids, as equal to 1 microgram of retinol. In female volunteers, carriers of two common BCMO1 variants showed a conversion marker lower by 32% (379V) and 69% (267S + 379V). Why people who convert poorly are described as relying more on preformed retinol from animal sources, the Alpha-Tocopherol, Beta-Carotene Cancer Prevention (ATBC) and Beta-Carotene and Retinol Efficacy Trial (CARET) cautions for smokers (beta-carotene as pro-oxidant under high oxidative stress), upper-limit toxicity, liver storage kinetics, and teratogenicity.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Vitamin A Produces Effects Across So Many Systems
- Research Papers: Vision & Eye Health
- Research Papers: Immune Function
- Research Papers: Skin & Cellular Differentiation
- Research Papers: Forms, Conversion, and Toxicity
- Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- External Authoritative Resources
- Connections
- Featured Videos
Why Vitamin A Produces Effects Across So Many Systems
Most vitamins act through one principal mechanism (water-soluble cofactors typically donate a chemical group to a specific enzyme reaction). Vitamin A is unusual because it operates through two fundamentally different mechanisms in two different molecular forms, and a third role as substrate for the visual chromophore. Each of the three maps to a distinct category of clinical effect.
- Photochemistry (11-cis-retinal in rhodopsin) — the retinal isomer covalently bound to opsin in retinal rod cells absorbs a photon and isomerizes to all-trans-retinal, initiating the visual transduction cascade. This mechanism drives the eye-health effects: night blindness, xerophthalmia, and the dose-dependent reversibility of early deficiency-driven vision loss.
- Nuclear-receptor signaling (all-trans-retinoic acid binding RAR, which pairs with RXR) — retinoic acid binds to the retinoic acid receptor (RAR) family of nuclear transcription factors, which heterodimerize with retinoid X receptor (RXR) and bind retinoic acid response elements (RAREs) in promoter regions of hundreds of target genes. This is the mechanism behind epithelial differentiation, the topical and oral retinoid drug class, and the teratogenicity warning, and behind much of the immune-modulating effect on T-cell maturation and Th17/Treg balance.
- Mucosal epithelial maintenance — the same retinoic acid signaling that drives skin keratinocyte differentiation also maintains the mucosal epithelium of the gut, lungs, conjunctiva, and reproductive tract. Loss of mucosal integrity is the proposed mechanism linking Vitamin A deficiency to increased diarrheal infection mortality in deficient populations. In a 2022 Cochrane review, supplements lowered deaths from diarrhea (risk ratio 0.88, 95% CI 0.79 to 0.98) but showed no clear difference in deaths from respiratory disease (0.98, 0.86 to 1.12).
The largest review of vitamin A supplements for children aged 6 months to 5 years (Cochrane 2022; 47 studies, about 1.2 million children) found deaths from all causes 12% lower (risk ratio 0.88), diarrhea deaths 12% lower, night blindness about two-thirds lower (0.32) and Bitot's spots lower (0.42), with no clear change in deaths from respiratory disease or measles. Its authors put the number of children under five with vitamin A deficiency at 190 million.
The therapeutic complication is that the same molecule can produce two distinct toxicity syndromes: acute hypervitaminosis A (headache, nausea, increased intracranial pressure, peeling skin) from a single megadose, and chronic hypervitaminosis A (hepatotoxicity, bone loss, alopecia) from sustained high intake of preformed vitamin A. The adult Tolerable Upper Intake Level set by the Institute of Medicine is 3,000 micrograms a day of preformed vitamin A; that is an upper limit, not the toxicity threshold, and its liver-toxicity case reports include doses of 7,600 to 14,000 micrograms a day. In 2024 the European Food Safety Authority kept the same adult limit, including during pregnancy, with lower limits for children (600 for infants to 2,600 for ages 15-17). It wrote that European intakes are unlikely to exceed the limit if liver and offal are eaten once a month or less, and advises women planning pregnancy or pregnant not to consume liver products. Most consequentially, retinoic acid at high concentration is a known teratogen — the reason oral isotretinoin requires monthly pregnancy testing under the iPLEDGE program in the United States. The fourth deep-dive page explores why the form of Vitamin A matters as much as the dose: provitamin A carotenoids are converted to retinol on demand by the BCMO1 enzyme, with built-in regulatory feedback that prevents toxicity, while preformed retinol bypasses that feedback and accumulates in the liver. The Institute of Medicine also notes that ripe colored fruits and cooked yellow tubers are converted more efficiently than equal amounts of dark green leafy vegetables.
Research Papers: Vision & Eye Health
- WHO global prevalence of Vitamin A deficiency and childhood blindness — PubMed: WHO childhood blindness
- Sommer A, classic field trials on Vitamin A and child mortality (Indonesia) — PubMed: Sommer Indonesia trials
- 11-cis-retinal and the rhodopsin visual cycle — PubMed: 11-cis-retinal rhodopsin cycle
- Xerophthalmia classification and clinical staging (WHO X1A through XS) — PubMed: WHO xerophthalmia staging
- AREDS original trial (Age-Related Eye Disease Study, AREDS Research Group 2001) — PubMed: AREDS 2001
- AREDS2 trial (Lutein/Zeaxanthin substituted for beta-carotene) — PubMed: AREDS2
- Imdad A, Mayo-Wilson E, Haykal MR, Regan A, Sidhu J, Smith A, Bhutta ZA. Vitamin A supplementation for preventing morbidity and mortality in children from six months to five years of age. Cochrane Database Syst Rev. 2022;3(3):CD008524. — PubMed PMID: 35294044
- Night blindness (nyctalopia) as earliest sign of Vitamin A deficiency — PubMed: Nyctalopia and deficiency
- Vitamin A supplementation in pregnancy and maternal night blindness (Nepal trial) — PubMed: Nepal maternal trial
- Retinal pigment epithelium and the RPE65 enzyme in the visual cycle — PubMed: RPE65 visual cycle
Research Papers: Immune Function
- Huiming Y, Chaomin W, Meng M. Vitamin A for treating measles in children. Cochrane Database Syst Rev. 2005;2005(4):CD001479. — PubMed PMID: 16235283
- Hussey GD, Klein M. A randomized, controlled trial of vitamin A in children with severe measles. N Engl J Med. 1990;323(3):160-4. Of the 12 hospitalized children who died, 10 had been given placebo. — PubMed PMID: 2194128
- Retinoic acid and Th17 / Treg differentiation balance — PubMed: RA Th17/Treg balance
- Vitamin A and gut-associated lymphoid tissue (GALT) homing of T cells — PubMed: RA gut-homing T cells
- Vitamin A in respiratory infection: meta-analysis — PubMed: Respiratory infection meta-analysis
- Vitamin A and diarrheal disease mortality reduction — PubMed: Diarrheal disease mortality
- Mucosal IgA production and Vitamin A status — PubMed: Secretory IgA
- Retinoic acid and dendritic cell function in mucosal immunity — PubMed: RA dendritic cells
- Natural killer cell function and Vitamin A — PubMed: NK cells and Vitamin A
- Vitamin A deficiency and HIV mother-to-child transmission research — PubMed: HIV vertical transmission
Research Papers: Skin & Cellular Differentiation
- Tretinoin (all-trans-retinoic acid) for acne vulgaris — PubMed: Topical tretinoin for acne
- Isotretinoin for severe nodulocystic acne — PubMed: Isotretinoin for acne
- Acitretin and oral retinoids for psoriasis — PubMed: Acitretin for psoriasis
- Topical retinoid mechanism: RAR/RXR nuclear receptor signaling — PubMed: RAR/RXR keratinocyte signaling
- Tretinoin for photoaging: Kligman classic trial — PubMed: Kligman photoaging trial
- Retinaldehyde as a gentler alternative to tretinoin — PubMed: Retinaldehyde topical
- Retinyl palmitate and retinyl esters in cosmetic formulations — PubMed: Retinyl ester cosmetics
- iPLEDGE program and isotretinoin teratogenicity prevention — PubMed: iPLEDGE program
- Bexarotene (RXR-selective retinoid) for cutaneous T-cell lymphoma — PubMed: Bexarotene CTCL
- ATRA (all-trans-retinoic acid) for acute promyelocytic leukemia — PubMed: ATRA for APL
Research Papers: Forms, Conversion, and Toxicity
- BCMO1 (beta-carotene-15,15'-monooxygenase) and central cleavage mechanism — PubMed: BCMO1 central cleavage
- Leung WC, Hessel S, Méplan C, Flint J, Oberhauser V, Tourniaire F, Hesketh JE, von Lintig J, Lietz G. Two common single nucleotide polymorphisms in the gene encoding beta-carotene 15,15'-monoxygenase alter beta-carotene metabolism in female volunteers. FASEB J. 2009;23(4):1041-53. — PubMed PMID: 19103647
- Beta-carotene to retinol conversion ratio (12 micrograms of dietary beta-carotene; 24 micrograms of other provitamin A carotenoids, per 1 microgram of retinol) — PubMed: Conversion ratio
- ATBC trial (alpha-tocopherol beta-carotene cancer prevention study) — PubMed: ATBC trial
- CARET trial (beta-carotene and retinol efficacy trial in smokers) — PubMed: CARET trial
- Hypervitaminosis A and hepatotoxicity case series — PubMed: Hepatotoxicity
- Vitamin A teratogenicity (Lammer 1985 NEJM) — PubMed: Lammer NEJM 1985
- Retinyl palmitate vs retinyl acetate bioavailability — PubMed: Palmitate vs acetate
- Hepatic stellate cell storage of retinyl esters — PubMed: Stellate cell storage
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, Bohn T, Castenmiller J, et al. Scientific opinion on the tolerable upper intake level for preformed vitamin A and β-carotene. EFSA J. 2024;22(6):e8814. — PubMed PMID: 38846679
- Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc, chapter 4, Vitamin A. National Academies Press; 2001. — nap.edu chapter 4
- Vitamin A and bone loss / osteoporosis at high chronic intake — PubMed: Retinol and bone loss
Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- Retinol-binding protein (RBP4) and serum Vitamin A transport — PubMed: RBP4 transport
- Vitamin A status assessment: serum retinol limitations and relative dose response (RDR) — PubMed: Status assessment
- Vitamin A and zinc interaction (zinc required for RBP synthesis) — PubMed: A × zinc interaction
- Vitamin A and Vitamin D synergy / antagonism at the receptor level — PubMed: A × D receptor interaction
- Vitamin A, K2, and D triumvirate in calcium metabolism — PubMed: A/D/K2 triumvirate
- Fat malabsorption and Vitamin A deficiency (celiac, Crohn's, pancreatic insufficiency) — PubMed: Malabsorption
- Cystic fibrosis and fat-soluble vitamin deficiency — PubMed: CF and Vitamin A
- Vitamin A and thyroid hormone (T3 / RXR heterodimer signaling) — PubMed: A and thyroid
- Cod liver oil and combined Vitamins A and D historical evidence — PubMed: Cod liver oil history
- Linus Pauling Institute comprehensive Vitamin A review — PubMed: LPI review
External Authoritative Resources
- Linus Pauling Institute — Vitamin A Micronutrient Information Center
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Vitamin A Fact Sheet (Health Professionals)
- WHO — Vitamin A deficiency (Nutrition Landscape Information System) (global epidemiology, supplementation programs)
- MedlinePlus — Vitamin A
- PubMed — All research on Vitamin A / retinol (about 63,000 papers)
Connections
- All Vitamins
- Vitamin A (Main Page)
- Vitamin A for Vision & Eye Health
- Vitamin A for Immune Function
- Vitamin A for Skin & Cellular Differentiation
- Beta-Carotene vs Preformed Retinol
- Vitamin D3
- Vitamin K2
- Vitamin E
- Zinc
- Macular Degeneration
- Acne
- Organ Meats (Beef Liver)
- Immune Boosting
- Sweet Potatoes (Beta-Carotene)
- Kale
- Deficiency
- Toxicity
- History
- Sources