Immune Boosting — Sleep and Cortisol
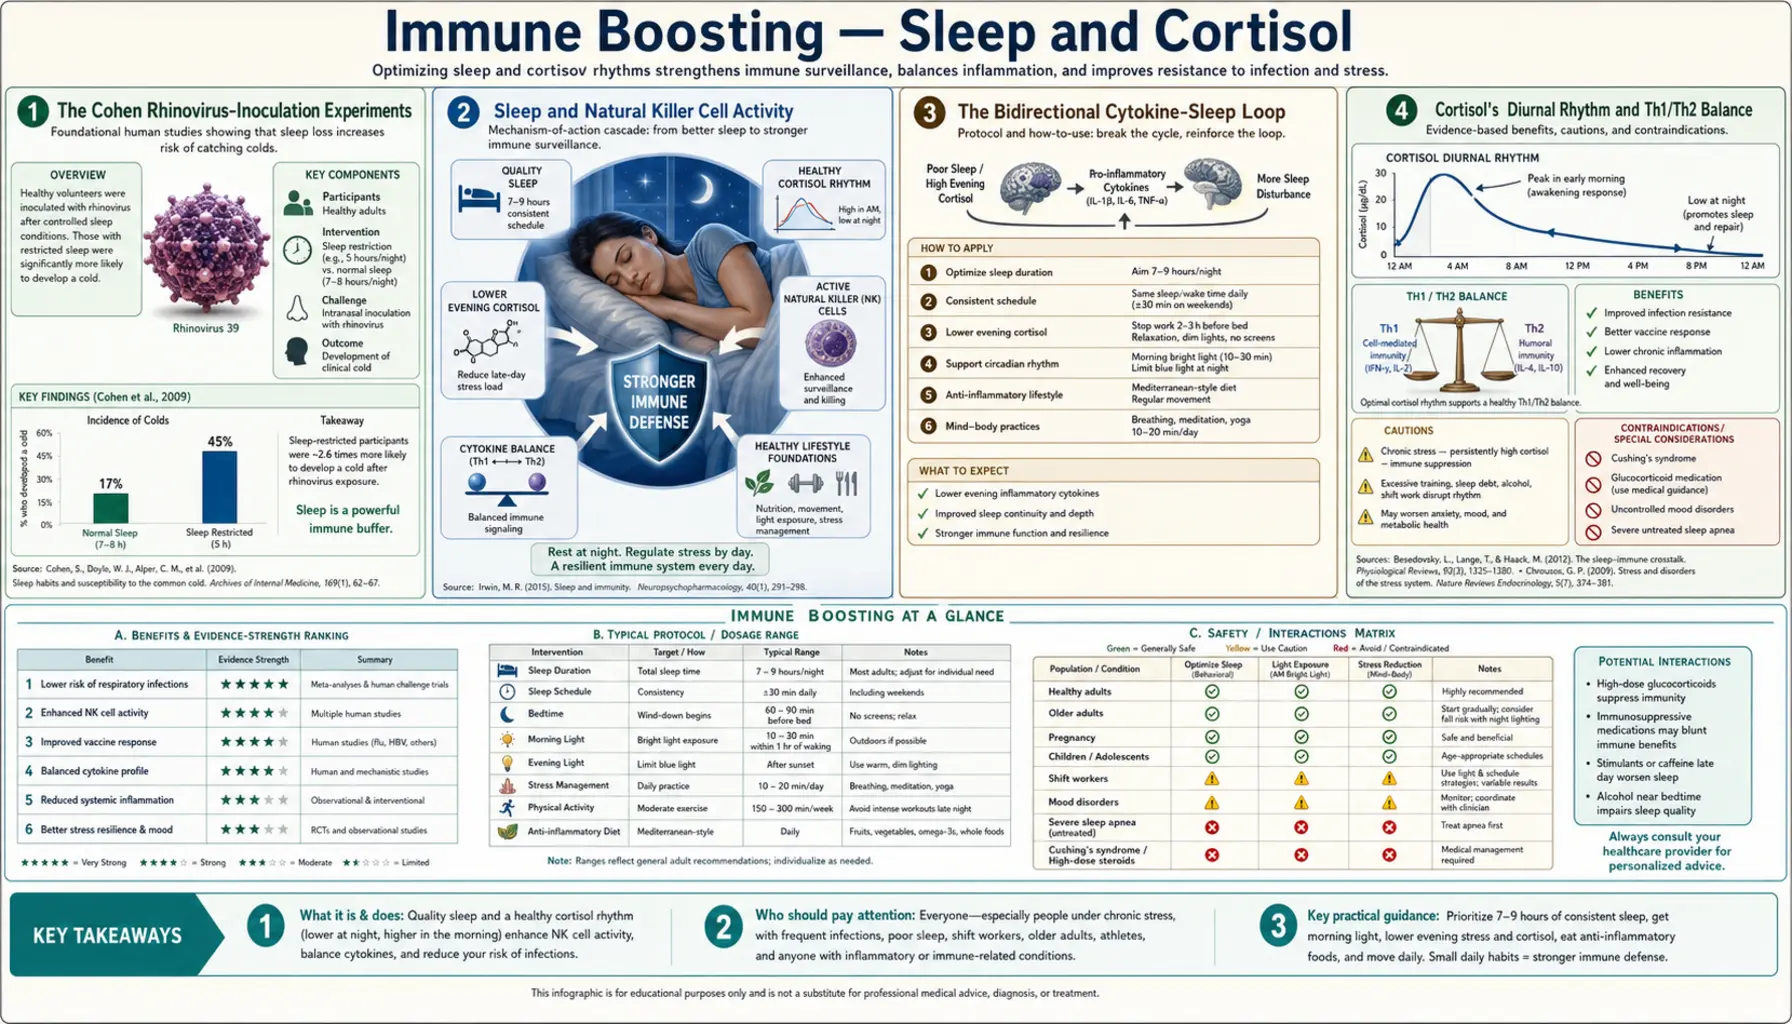
No supplement compensates for chronic sleep deprivation. A single night of partial sleep loss lowered natural killer cell activity to about 72% of its usual level in a 1994 study (Irwin 1994), and Sheldon Cohen's rhinovirus-inoculation experiments at Carnegie Mellon showed that habitual sleepers of less than 6 hours per night had roughly four times the odds of a clinical cold after standardized viral exposure compared to people sleeping more than 7 hours. Cortisol, sleep, and immunity form a tight three-way loop: cortisol's diurnal rhythm sets the daily Th1/Th2 balance, sleep architecture coordinates the nightly release of immune-priming cytokines like interleukin-1 (IL-1) and tumor necrosis factor-alpha, and chronic hypothalamic-pituitary-adrenal-axis activation suppresses lymphocyte function across the board. This deep-dive walks through the mechanism and the practical sleep-hygiene and cortisol-regulation regimen.
Table of Contents
- The Cohen Rhinovirus-Inoculation Experiments
- Sleep and Natural Killer Cell Activity
- The Bidirectional Cytokine-Sleep Loop
- Cortisol's Diurnal Rhythm and Th1/Th2 Balance
- Chronic Hypothalamic-Pituitary-Adrenal-Axis Activation
- Sleep and Vaccine Response
- Sleep Architecture: Deep Sleep and Immunity
- Practical Sleep Hygiene Protocol
- Cortisol Regulation Strategies
- Cautions and Special Populations
- Key Research Papers
- Connections
- Featured Videos
The Cohen Rhinovirus-Inoculation Experiments
The cleanest evidence that sleep affects infection risk comes from Sheldon Cohen's viral-challenge experiments at Carnegie Mellon University. The design was elegant: enroll healthy adults, measure their sleep habits over a baseline period (14 days of self-report in the 2009 study, 7 days of wrist actigraphy in the 2015 study), quarantine them in a research hotel, drop a standardized inoculum of rhinovirus directly into their nasal passages, then observe over the next 5 days which subjects developed clinical colds (defined by symptom score plus objective measures like nasal mucus weight).
The 2009 Cohen et al. paper in Archives of Internal Medicine reported the headline finding: among 153 healthy adults aged 21–55, those who had reported <7 hours of sleep per night were 2.94 times more likely to develop a clinical cold than those reporting ≥8 hours. Sleep efficiency (the fraction of time in bed actually spent asleep) was even more predictive: subjects with <92% sleep efficiency were 5.5 times more likely to develop a cold than those with ≥98% efficiency.
The 2015 Prather et al. follow-up replicated the finding with objective actigraphy measurement of sleep. Among 164 healthy adults aged 18–55 inoculated with rhinovirus, those with <5 hours of objectively measured sleep had 4.5 times the odds of a clinical cold (odds ratio 4.50) compared to those sleeping more than 7 hours, and those sleeping 5–6 hours had 4.24 times the odds; people sleeping 6–7 hours were at no clearly greater risk (odds ratio 1.66, not statistically significant). The link persisted after controlling for age, body composition, immune status (pre-challenge antibody titer to the inoculum virus), and stress measures.
These are among the strongest prospective studies of sleep and infection. The viral inoculum is controlled; the outcome (clinical infection) is binary and clinically meaningful; the sleep exposure was measured before inoculation, so the cold cannot have caused the poor sleep. Because the volunteers slept as they normally did rather than being assigned less sleep, both papers report the link as an association: shorter or less efficient sleep before exposure was associated with lower resistance to the cold virus.
Sleep and Natural Killer Cell Activity
The mechanistic link begins with natural killer cells. Natural killer (NK) cells are the innate-immunity sentinels that recognize and kill virally infected cells and transformed (tumor) cells. Natural killer cytotoxic activity is measurable in vitro by harvesting natural killer cells from a blood draw, mixing them with a standardized tumor cell line (typically K562 cells), and measuring the percentage of target cells killed.
Irwin et al. 1994 (Psychosomatic Medicine) kept 23 healthy men awake from 3 AM to 7 AM for one night; the next day natural killer cell activity fell in 18 of the 23, to an average of 72% of their usual level. Irwin et al. 1996 (FASEB Journal) kept 42 healthy men awake from 10 PM to 3 AM and found lower natural killer cell activity and lower production of the immune signal interleukin-2 (IL-2) the next day. The natural killer effect was rapidly reversible — in both studies one night of normal sleep returned natural killer activity to baseline, although in the 1996 study interleukin-2 production stayed low.
The mechanism is multilayered. Natural killer cells express receptors for both growth hormone (which surges during deep slow-wave sleep) and cortisol (which suppresses immune function and rises during sleep deprivation). The cortisol-to-growth-hormone ratio in the morning predicts natural killer cytotoxic activity that day. Sleep deprivation tilts the ratio toward cortisol dominance, suppressing the cells. Additionally, the diurnal trafficking of natural killer cells — the nightly migration from peripheral blood into lymphoid tissue and back — is disrupted by sleep loss, leaving fewer cells in the circulation where they encounter blood-borne pathogens.
The natural killer suppression mechanism is mechanistically connected to the Cohen rhinovirus findings. Natural killer cells are the first line of antiviral defense in the upper respiratory mucosa. Reduced natural killer activity at the moment of viral exposure means the virus establishes infection more readily, and the resulting clinical infection rate is higher in sleep-restricted subjects.
The Bidirectional Cytokine-Sleep Loop
Sleep and immunity are bidirectionally coupled through cytokines. Two of the most important sleep-regulating cytokines are interleukin-1 (IL-1) and tumor necrosis factor alpha (TNF-α), both of which are produced by macrophages in response to pathogen recognition and both of which act on the hypothalamic preoptic area to promote slow-wave sleep.
This is why infection makes you sleepy. The same cytokines the immune system uses to signal pathogen recognition and recruit other immune cells also directly induce sleep, creating an evolutionarily adaptive feedback: when fighting infection, the body forces rest. Conversely, sleep itself induces these cytokines as a normal part of nighttime physiology — cytokine levels rise in the early hours of sleep, contributing to deep slow-wave sleep architecture, and fall during waking hours.
Sleep deprivation disrupts this regulated cytokine cycling. Chronic short sleepers have elevated baseline interleukin-6 (IL-6) and tumor necrosis factor-alpha during the day — a low-grade inflammatory state — combined with blunted nighttime cytokine peaks. The result is the worst of both worlds: chronic background inflammation that contributes to metabolic disease and cardiovascular risk, plus impaired acute cytokine response when actually facing infection.
The Besedovsky et al. 2019 Physiological Reviews paper is the definitive review of this sleep-immune crosstalk. It catalogues the bidirectional pathway in detail and is the standard reference for clinicians and researchers in the field.
Cortisol's Diurnal Rhythm and Th1/Th2 Balance
Cortisol is the principal glucocorticoid in humans and the dominant immunoregulatory hormone of the hypothalamic-pituitary-adrenal (HPA) axis. Its secretion follows a characteristic diurnal rhythm: lowest at midnight, rises sharply in the early morning hours (the cortisol awakening response peaks 30–45 minutes after waking), then declines progressively through the afternoon and evening to the midnight nadir.
This rhythm gates immune function. High morning cortisol favors Th2 (humoral) immunity and suppresses Th1 (cellular) immunity. Low evening and nighttime cortisol releases this suppression, allowing Th1 cytokine production (interleukin-2 (IL-2), interferon-gamma (IFN-gamma)) to peak overnight — precisely when the body is asleep, the lymphocytes are migrating through lymphoid tissue, and the adaptive immune system is being primed for the next day's antigen encounters.
Several lines of evidence support the functional importance of this rhythm. Patients with adrenal insufficiency (Addison's disease, on hydrocortisone replacement) show altered Th1/Th2 balance and have characteristic infection susceptibility patterns. Patients on long-term high-dose glucocorticoid therapy (prednisone for autoimmune disease, asthma, or transplant) have profoundly suppressed cellular immunity and characteristic susceptibility to opportunistic infections (pneumocystis, mycobacteria, fungi). Shift workers, whose cortisol rhythm is desynchronized from environmental light cues, have measurably increased rates of infection, autoimmune disease, and cancer.
The Elenkov and Chrousos 1999 paper articulated this Th1/Th2 cortisol-shift model as a general explanation for stress-induced disease susceptibility. The model has held up well in subsequent decades of work.
Chronic Hypothalamic-Pituitary-Adrenal-Axis Activation
Acute cortisol elevation (the morning awakening response, the response to acute stress) is adaptive and immune-modulating, not immunosuppressive. Chronic hypothalamic-pituitary-adrenal-axis activation — sustained elevation of cortisol from chronic psychosocial stress, chronic pain, chronic insomnia, or chronic systemic illness — is a different physiologic state and is immunosuppressive.
Glaser and Kiecolt-Glaser's 2005 Nature Reviews Immunology review synthesized 30 years of research on chronic-stress effects on immunity. The summary findings:
- Caregivers of dementia patients have measurably reduced T-cell and natural killer function, reduced response to vaccines, and slower wound healing
- Depression is associated with reduced T-cell mitogen responses, reduced natural killer activity, and elevated baseline interleukin-6 and tumor necrosis factor-alpha
- Chronic interpersonal stress (the Whitehall studies of British civil servants) predicts increased respiratory infection rates and slower recovery
- Bereavement is associated with measurably suppressed lymphocyte function for weeks following the loss
- Chronic insomnia produces a chronic-stress immunologic phenotype indistinguishable from psychosocial-stress phenotypes
The clinical implication: addressing chronic psychosocial stress, chronic insomnia, and chronic pain is part of immune optimization. Supplement regimens that ignore the chronic-stress axis are missing the dominant variable.
Sleep and Vaccine Response
If sleep deprivation suppresses immune function in general, it should also reduce the antibody response to vaccination. This has been tested directly. Spiegel et al. 2002 (JAMA) restricted sleep to 4 hours per night for 6 nights in healthy young men, then administered influenza vaccine. The sleep-restricted group developed antibody titers less than half those of the well-rested controls 10 days post-vaccination.
Lange et al. 2003 found the same pattern for hepatitis A vaccine: among 19 healthy adults, those who slept normally on the night after vaccination had a nearly two-fold higher antibody level 4 weeks later than those kept awake that night. Later work found it for hepatitis B vaccine (below). For COVID-19 vaccines, made against severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2), the results are mixed: a 2023 study of 48 healthy adults linked longer device-measured sleep in the days after a booster dose with higher antibody levels (Izuhara 2023), while a study comparing night-shift and day workers found no link between sleep and the response to a first dose (Brouwers 2025). Where the effect appears, it is large enough to be clinically meaningful, particularly for vaccines like influenza where antibody titer correlates closely with protection.
Prather et al. 2012 followed 125 healthy adults aged 40–60 through the standard 3-dose hepatitis B vaccine series (an observational study). Shorter sleep measured by a wrist activity monitor (actigraphy) was linked to a lower antibody response, and shorter sleep also predicted a lower chance of being clinically protected 6 months after the last dose. How well people felt they slept made no difference.
A 2023 meta-analysis by Spiegel and colleagues pooled the sleep-and-vaccine studies in healthy adults. Short sleep measured objectively (by a device or in the sleep laboratory) was linked to a clearly weaker antibody response (effect size 0.79, 304 adults aged 18–60), while self-reported short sleep of under 6 hours a night did not reach statistical significance (effect size 0.29, 504 adults aged 18–85). The link was large in men (effect size 0.93) and not significant in women (0.42).
The authors of that meta-analysis suggest that enough sleep in the days surrounding vaccination may enhance and prolong the antibody response, and they state that large, well-controlled studies are still needed to define the window of time around vaccination when sleep matters most, the reasons for the difference between men and women, and how much sleep is needed. In the hepatitis A study, a single night without sleep right after vaccination was enough to weaken the response.
Sleep Architecture: Deep Sleep and Immunity
Sleep is not a homogeneous state. It is composed of cyclical stages alternating between non-rapid eye movement (non-REM) sleep (further divided into N1, N2, and N3 stages, where N3 is "slow-wave sleep" or "deep sleep") and rapid eye movement (REM) sleep. The architecture of a normal night cycles through approximately 4–6 of these cycles, with slow-wave sleep predominating in the first half of the night and REM predominating in the second half.
The immune-relevant phase is slow-wave sleep. Growth hormone secretion is sharply pulsatile and concentrated in the first slow-wave sleep cycle of the night. Prolactin, which has direct immune-modulating effects, also peaks during deep sleep. The migration of naive T cells from peripheral blood into lymphoid tissue, where they encounter antigen-presenting dendritic cells, is concentrated in the deep-sleep window.
Loss of slow-wave sleep specifically — not just shortened total sleep time — reduces these immune-priming processes. The Dimitrov et al. 2019 paper in the Journal of Experimental Medicine showed that sleep, compared with staying awake at night, increased the activation of integrins (adhesion molecules that let T cells grip their targets) on virus-specific T cells, and in laboratory tests stress hormones (adrenaline, noradrenaline), prostaglandins and adenosine blocked this activation. The study compared sleep with wakefulness; it did not test individual sleep stages.
Several common factors selectively reduce slow-wave sleep without necessarily reducing total time in bed: aging (slow-wave sleep declines from ~25% of sleep in adolescence to ~10% in the 60s), benzodiazepines and most non-benzodiazepine hypnotics (which produce sedation without normal sleep architecture), sleep apnea (arousals interrupt deep sleep), and chronic pain. Each of these reduces the immune-priming function of sleep even when total sleep time looks adequate on a sleep diary. Alcohol works differently: a 2013 review of studies in healthy volunteers found that evening alcohol increases slow-wave sleep in the first half of the night, then disrupts sleep in the second half, and delays (and at moderate and high doses reduces) REM sleep (Ebrahim 2013).
Practical Sleep Hygiene Protocol
The single most evidence-based set of interventions for sleep optimization in adults:
- Consistent sleep and wake times, including weekends — circadian regulation depends on consistency of the wake time more than the sleep time. This protocol sets a target of <30 minutes variation in wake time across the week.
- Morning bright-light exposure — 10–30 minutes of outdoor light (or 10,000-lux light therapy box) within the first hour of waking. This synchronizes the suprachiasmatic nucleus master clock and produces the proper evening melatonin surge 14–16 hours later.
- Evening dim-light protocol — dim household lighting in the 2–3 hours before bed, with fewer screens or warm-color/dim screen modes; some people use amber-tinted glasses when screens are unavoidable. Bright blue-spectrum light in the evening suppresses melatonin and delays sleep onset.
- Cool bedroom (60–67°F / 16–19°C) — sleep onset and slow-wave sleep depth depend on a falling core body temperature; cool ambient temperature facilitates this.
- No caffeine after early afternoon — caffeine has a 6-hour half-life; caffeine consumed at 3 PM is still pharmacologically active at 9 PM. This protocol places the last caffeine at noon to 2 PM.
- Evening alcohol — alcohol shortens the time it takes to fall asleep and deepens the first half of the night, but a 2013 review found it disrupts sleep in the second half of the night and delays (and at moderate and high doses reduces) REM sleep, producing the characteristic 3 AM awakening as it metabolizes.
- Last meal 3+ hours before bed — ongoing digestion raises core temperature and produces postprandial glucose excursions that fragment sleep.
- Bed for sleep and intimacy only — not for reading, work, television. The bed-bedroom association with sleep is a learned cue and is degraded by other activities.
- Wind-down routine — 30–60 minutes of dim-light, low-stimulation activity (reading, gentle stretching, hot bath) signals the brain to begin the sleep-onset process.
- Sleep apnea — snoring, witnessed pauses in breathing (apneas), morning headache, and persistent daytime sleepiness are signs of sleep apnea, which is diagnosed with a formal sleep study. Untreated sleep apnea fragments deep sleep and is independently immunosuppressive.
Cortisol Regulation Strategies
For hypothalamic-pituitary-adrenal-axis tone, the interventions overlap with sleep optimization but include additional layers:
- Morning sunlight exposure — entrains the cortisol awakening response to occur at the right time of day and at appropriate magnitude
- Regular moderate exercise (not late evening) — exercise transiently raises cortisol but improves the overall diurnal rhythm and lowers chronic baseline. Evening high-intensity exercise can disrupt sleep onset; morning or afternoon timing is preferred
- Meditation, yoga, breathwork — activate parasympathetic nervous system tone, reducing chronic sympathetic activation. The Mindfulness-Based Stress Reduction (MBSR) protocol has substantial clinical evidence for cortisol-rhythm normalization
- Social connection — psychosocial isolation is itself a chronic stressor; regular connection with family, friends, community modulates hypothalamic-pituitary-adrenal tone
- Adaptogenic herbs — particularly Ashwagandha (clinical trial evidence for cortisol reduction in chronically stressed adults; see our Herbal Adaptogens deep-dive)
- Phosphatidylserine — modest evidence for blunting cortisol response to acute stress at 100–300 mg/day; soy-derived phosphatidylserine is the most widely studied form
- L-theanine — 100–200 mg promotes alpha-wave brain activity and modest reduction in subjective stress; well-tolerated
Factors that work against cortisol regulation: chronic high-dose caffeine (potentiates the cortisol response to stress), nightly alcohol (suppresses parasympathetic tone in the second half of the night), and screen-based work in the last hour before bed (combines blue light melatonin suppression with cognitive activation).
Cautions and Special Populations
- Shift workers — night shift work is classed as probably carcinogenic to humans (International Agency for Research on Cancer (IARC) Group 2A, 2019), and circadian misalignment produces sustained immune suppression. Mitigation strategies (consistent rotation patterns, strategic light exposure, melatonin timing) help but do not fully restore normal physiology
- New parents, caregivers — chronic sleep fragmentation produces the same immune suppression as voluntary sleep restriction. Strategies used in this situation include napping, partners sharing night shifts, and set recovery time
- Untreated depression and anxiety — both are associated with disrupted sleep architecture and elevated cortisol; addressing the underlying mood condition is part of the immune intervention
- Chronic pain — fragments sleep and elevates hypothalamic-pituitary-adrenal tone; pain management is part of sleep optimization
- Menopause — estrogen withdrawal causes sleep fragmentation and disrupts deep-sleep architecture; night sweats and other menopausal symptoms are treated in several ways, hormone replacement therapy among them
- Cushing's syndrome and exogenous glucocorticoid therapy — chronically elevated cortisol from primary disease or prescribed steroids produces severe immune suppression. Sleep hygiene alone does not normalize immune function in these settings, because the excess cortisol comes from the disease or the medicine
- Sleep medications — benzodiazepines, Z-drugs (zolpidem, eszopiclone), and most over-the-counter "PM" formulations (diphenhydramine) produce sedation without normal sleep architecture. They restore sleep quantity but not necessarily sleep quality in the immune-priming sense
Key Research Papers
- Cohen S et al. (2009). Sleep habits and susceptibility to the common cold. Archives of Internal Medicine; 169(1):62-67. — PubMed PMID: 19139325
- Prather AA et al. (2015). Behaviorally assessed sleep and susceptibility to the common cold. Sleep; 38(9):1353-1359. — PubMed PMID: 26118561
- Irwin M et al. (1996). Partial night sleep deprivation reduces natural killer and cellular immune responses in humans. FASEB Journal; 10(5):643-653. — PubMed PMID: 8621064
- Besedovsky L et al. (2019). The sleep-immune crosstalk in health and disease. Physiological Reviews; 99(3):1325-1380. — PubMed PMID: 30920354
- Dhabhar FS (2014). Effects of stress on immune function: the good, the bad, and the beautiful. Immunologic Research; 58(2-3):193-210. — PubMed PMID: 24798553
- Glaser R, Kiecolt-Glaser JK (2005). Stress-induced immune dysfunction: implications for health. Nature Reviews Immunology; 5(3):243-251. — PubMed PMID: 15738954
- Lange T et al. (2010). Effects of sleep and circadian rhythm on the human immune system. Annals of the New York Academy of Sciences; 1193:48-59. — PubMed PMID: 20398008
- Spiegel K, Sheridan JF, Van Cauter E (2002). Effect of sleep deprivation on response to immunization. JAMA; 288(12):1471-1472. — PubMed PMID: 12243633
- Dimitrov S et al. (2019). Gαs-coupled receptor signaling and sleep regulate integrin activation of human antigen-specific T cells. Journal of Experimental Medicine; 216(3):517-526. — PubMed PMID: 30755455
- Elenkov IJ, Chrousos GP (1999). Stress hormones, Th1/Th2 patterns, pro/anti-inflammatory cytokines and susceptibility to disease. Trends in Endocrinology and Metabolism; 10(9):359-368. — PubMed PMID: 10511695
- Cohen S, Tyrrell DA, Smith AP (1991). Psychological stress and susceptibility to the common cold. NEJM; 325(9):606-612. — PubMed PMID: 1713648
- Irwin MR (2015). Why sleep is important for health: a psychoneuroimmunology perspective. Annual Review of Psychology; 66:143-172. — PubMed PMID: 25061767
- Irwin M, Mascovich A, Gillin JC, et al. (1994). Partial sleep deprivation reduces natural killer cell activity in humans. Psychosomatic Medicine; 56(6):493-498. — PubMed PMID: 7871104
- Lange T, Perras B, Fehm HL, Born J (2003). Sleep enhances the human antibody response to hepatitis A vaccination. Psychosomatic Medicine; 65(5):831-835. — PubMed PMID: 14508028
- Prather AA, Hall M, Fury JM, et al. (2012). Sleep and antibody response to hepatitis B vaccination. Sleep; 35(8):1063-1069. — PubMed PMID: 22851802
- Spiegel K, Rey AE, Cheylus A, et al. (2023). A meta-analysis of the associations between insufficient sleep duration and antibody response to vaccination. Current Biology; 33(5):998-1005.e2. — PubMed PMID: 36917932
- Izuhara M, Matsui K, Yoshiike T, et al. (2023). Association between sleep duration and antibody acquisition after mRNA vaccination against SARS-CoV-2. Frontiers in Immunology; 14:1242302. — PubMed PMID: 38149250
- Brouwers TMJ, Çobanoğlu ÜG, Geers D, et al. (2025). The effect of sleep and shift work on the primary immune response to messenger RNA-based COVID-19 vaccination. Journal of Sleep Research; 34(4):e14431. — PubMed PMID: 39658344
- Ebrahim IO, Shapiro CM, Williams AJ, Fenwick PB (2013). Alcohol and sleep I: effects on normal sleep. Alcoholism, Clinical and Experimental Research; 37(4):539-549. — PubMed PMID: 23347102
- IARC Monographs Vol 124 group (2019). Carcinogenicity of night shift work. Lancet Oncology; 20(8):1058-1059. — PubMed PMID: 31281097