⚠ Evidence warning: Clinical trials or other evidence do not support the claims that detox bottlenecks cause estrogen-dominance acne and multiple chemical sensitivity, and that castor oil packs drain lymph and stimulate bile flow. This page keeps it as a report of what people, websites or other media say.
Liver Cleansing — Benefits Deep Dive
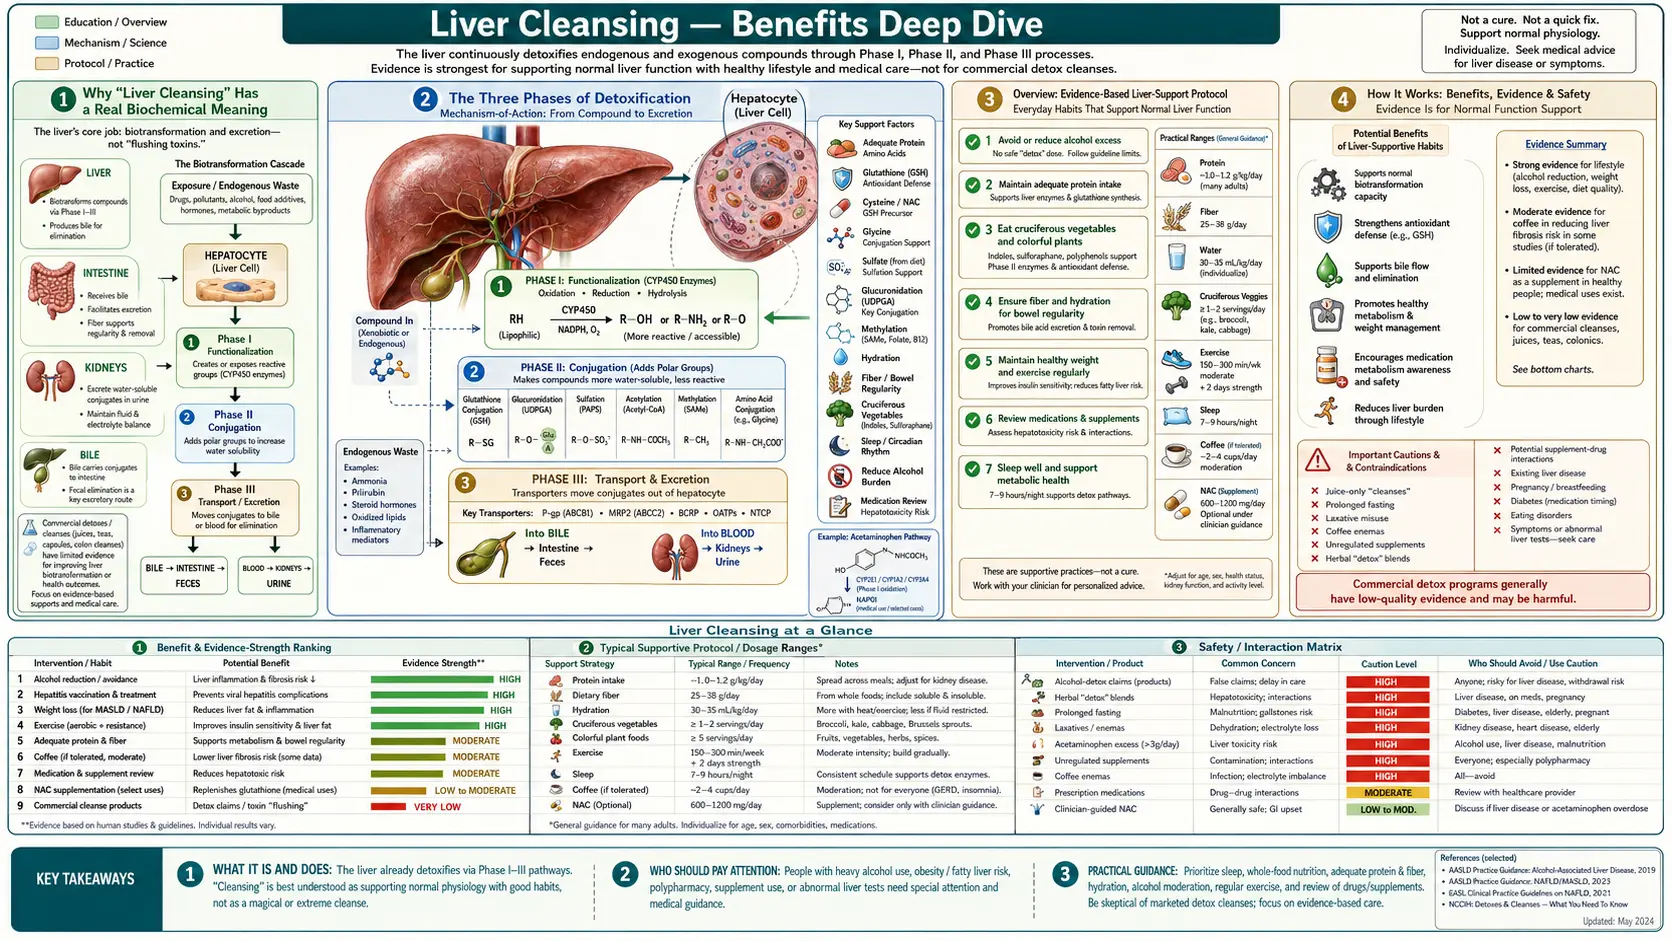
The liver is the body's primary site of biotransformation — the only organ capable of converting fat-soluble xenobiotics and endogenous hormones into water-soluble metabolites that can be excreted in bile and urine. "Liver cleansing" as a clinical concept is not the vague detox-tea marketing claim; it is a set of well-defined biochemical interventions that support Phase I (cytochrome P450) and Phase II (glucuronidation, sulfation, glutathione conjugation) detoxification pathways, restore bile flow, replenish glutathione, and reduce hepatic inflammation. The four deep-dive pages below explore the evidence-based interventions: tauroursodeoxycholic acid (TUDCA) and bile-flow normalization (the missing third phase of detoxification), castor oil packs (traditional; the one known mechanism of castor oil concerns oil taken by mouth), coffee's paradoxical hepatoprotective effects (lower cirrhosis, hepatocellular carcinoma (HCC, the main type of liver cancer), and alanine aminotransferase (ALT) documented across more than 30 cohort studies), and glutathione precursor strategies (N-acetylcysteine (NAC), glycine, whey, and the often-overlooked role of selenium and B-vitamins).
Deep-Dive Articles
Bile Flow and TUDCA
Why bile flow is the often-forgotten third phase of detoxification, the enterohepatic circulation and why constipated patients reabsorb their own conjugated toxins, tauroursodeoxycholic acid (TUDCA) for cholestasis and primary biliary cholangitis, ursodeoxycholic acid (UDCA) as the U.S. Food and Drug Administration-approved parent compound, bile acid composition shifts in liver disease, and the TUDCA doses practitioners describe (250-1000 mg/day) for sluggish bile flow and gallstone-prone gallbladders.
Read the deep dive →Castor Oil Packs
The traditional Edgar Cayce protocol and its modern reappraisal: ricinoleic acid from swallowed castor oil as a prostaglandin EP3 receptor agonist (the mechanism of its laxative effect, shown in mice), the lymphatic-drainage effects practitioners describe, a before-and-after study in elderly rest-home residents in which packs did not change the number of bowel movements but improved stool consistency, straining and the feeling of complete emptying, the transdermal delivery question (does it actually penetrate?), the contraindications (pregnancy, active gastrointestinal (GI) bleeding), and the method practitioners describe: cold-pressed hexane-free oil, organic cotton or wool flannel, low-heat application 60-90 minutes, 3-4 nights weekly.
Read the deep dive →Coffee and Liver
The paradox: coffee, often viewed as a stressor, is one of the most consistently hepatoprotective beverages on record. Meta-analyses of observational studies linking each extra two cups a day with a lower risk of cirrhosis (relative risk 0.56) and of hepatocellular carcinoma (relative risk 0.65; 0.86 for decaffeinated coffee), plus lower non-alcoholic fatty liver disease (NAFLD) progression and alanine aminotransferase/gamma-glutamyl transferase (GGT) levels — all of it observational, rated “very low” quality under the GRADE system in the liver-cancer analysis because there are no randomised trials; mechanism via cafestol/kahweol induction of Phase II enzymes, chlorogenic acid antioxidant effects, and adenosine receptor modulation; the filtered-versus-unfiltered question (cafestol cholesterol effect); and the intake practitioners commonly cite: 2-3 cups/day of filtered coffee for adults without contraindications.
Read the deep dive →Glutathione Support
Glutathione (reduced glutathione, GSH) is the master antioxidant and the obligate cofactor for Phase II conjugation of acetaminophen, aflatoxin, mercury, and lipid peroxides. Why oral reduced glutathione itself is poorly absorbed but precursors (N-acetylcysteine, glycine, glutamine) and cofactors (selenium, riboflavin) reliably restore tissue reduced glutathione; the GlyNAC pilot trial in aging adults, in which red-blood-cell reduced glutathione rose 200% after 24 weeks; the role of milk thistle (silymarin) as a glutathione-sparing agent; and a glutathione-restoration protocol practitioners describe: 600-1800 mg/day N-acetylcysteine + 3 g/day glycine + 200 mcg selenomethionine + B2/B6/B12.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why "Liver Cleansing" Has a Real Biochemical Meaning
- The Three Phases of Detoxification
- How Fatty Liver Disease Was Renamed in 2023
- Two Drug Trials in Fatty-Liver Inflammation
- Research Papers: Bile Flow & TUDCA
- Research Papers: Castor Oil Packs
- Research Papers: Coffee & Liver
- Research Papers: Glutathione Support
- Research Papers: Cross-Cutting (Phase I/II, NAFLD, Hepatoprotection)
- External Authoritative Resources
- Connections
- Featured Videos
Why "Liver Cleansing" Has a Real Biochemical Meaning
The phrase "liver cleanse" attracts justified skepticism because it has been hijacked by detox-tea marketing and the "liver flush" home remedies (large doses of olive oil and Epsom salts producing "stones" that are actually saponified bile-oil pellets, not gallstones). But a separate, legitimate clinical framework exists under the same name — the support of hepatic biotransformation, bile flow, and glutathione status in patients with documented sluggish detoxification, non-alcoholic fatty liver disease, environmental chemical burden, or recovery from acute hepatotoxic exposure.
The liver is the central organ of xenobiotic metabolism. Every drug, every environmental chemical, every endogenous steroid hormone, and every gut-derived metabolite ultimately passes through hepatic biotransformation. The system has three sequential phases — oxidation, conjugation, and excretion — and practitioners hold that a bottleneck at any phase produces clinical symptoms ranging from estrogen-dominance acne to multiple chemical sensitivity to drug-induced liver injury.
The four interventions explored in the deep-dive pages below each target a specific phase or substrate:
- TUDCA and bile flow — addresses the Phase III excretion bottleneck. Conjugated toxins leave the hepatocyte in bile; if bile flow is sluggish, conjugates back up into circulation.
- Castor oil packs — a traditional intervention that practitioners use for lymphatic drainage and bile-flow stimulation. The one mechanism shown in the laboratory concerns castor oil taken by mouth: ricinoleic acid released in the gut activates prostaglandin EP3 receptors on intestinal and uterine smooth muscle, causing its laxative effect and uterine contraction (Tunaru 2012, in mice). The lymph and bile effects of packs on the skin are traditional claims.
- Coffee — a dietary intervention with the largest population-scale evidence base for hepatoprotection, working through Phase II enzyme induction and anti-fibrotic effects.
- Glutathione precursor support — addresses the Phase II conjugation bottleneck. Glutathione is the limiting substrate for conjugation of many lipophilic toxins.
The Three Phases of Detoxification
Hepatic biotransformation is conventionally divided into three sequential phases. Each phase has its own enzymes, cofactors, substrate preferences, and clinically relevant bottlenecks.
Phase I — Functionalization (Cytochrome P450). The CYP450 enzyme superfamily (approximately 57 functional human enzymes; CYP3A4, CYP2D6, CYP2C9, CYP1A2 do most of the work) introduces or unmasks a polar functional group on the substrate (typically a hydroxyl). The reaction generates reactive intermediates that are more toxic than the parent compound in many cases — acetaminophen's N-acetyl-p-benzoquinone imine (NAPQI) metabolite, benzo[a]pyrene's diol-epoxide, and aflatoxin's 8,9-epoxide are all Phase I products more dangerous than their precursors. Phase I requires reduced nicotinamide adenine dinucleotide phosphate (NADPH) (from the pentose phosphate pathway), riboflavin (FAD), and iron (heme prosthetic group).
Phase II — Conjugation. The Phase II reactions attach a polar group (glucuronate, sulfate, glutathione, acetyl, methyl, glycine) to the Phase I product, converting the reactive intermediate to a water-soluble, biologically inert conjugate ready for excretion. The major Phase II pathways and their cofactors:
- Glucuronidation — UDP-glucuronosyltransferase (UGT) enzymes attach glucuronic acid from UDP-glucuronate. Requires intact glucose metabolism. Handles bilirubin, opioids, nonsteroidal anti-inflammatory drugs (NSAIDs), many drug metabolites.
- Sulfation — sulfotransferase (SULT) enzymes attach sulfate from PAPS (3'-phosphoadenosine-5'-phosphosulfate). Limited by dietary sulfur (cysteine, methionine, methylsulfonylmethane (MSM)). Handles many steroid hormones, phenols.
- Glutathione conjugation — glutathione S-transferase (GST) enzymes attach glutathione directly. Critical for acetaminophen detoxification, heavy metal binding, lipid peroxide cleanup. Discussed in depth in the glutathione deep-dive.
- Methylation — S-adenosylmethionine (SAM)-dependent transfer of methyl groups; depends on folate, B12, B6, betaine.
- Acetylation — N-acetyltransferase (NAT) enzymes; subject to fast/slow acetylator genetic polymorphism.
- Amino-acid conjugation — glycine and glutamine conjugation; depends on dietary glycine.
Phase III — Excretion. Conjugates must leave the hepatocyte. Active transport via multidrug resistance-associated protein 2 (MRP2), P-glycoprotein, and breast cancer resistance protein (BCRP) transporters carries conjugates into bile, which carries them to the gut for fecal excretion. If bile flow is sluggish (cholestasis, gallstones, gallbladder removal, opioid use), Phase II conjugates back up into the blood, get deconjugated by intestinal beta-glucuronidase, and recirculate via enterohepatic circulation. This is why bile-flow support matters as much as Phase I/II enzymes themselves.
How Fatty Liver Disease Was Renamed in 2023
In 2023 a consensus process led by three large international liver associations, with 236 experts and patient advocates from 56 countries, renamed non-alcoholic fatty liver disease (NAFLD) metabolic dysfunction-associated steatotic liver disease (MASLD). Seventy-four percent of respondents felt the old name was flawed enough to change, and the words “non-alcoholic” and “fatty” were felt to be stigmatising by 61% and 66% of respondents. “Steatotic liver disease” is now the umbrella term for fat build-up in the liver from any cause, and the new definition requires at least one of five cardiometabolic risk factors. A new category, metabolic and alcohol-related liver disease (MetALD), covers people with MASLD who also drink more alcohol (140–350 g a week for women, 210–420 g for men). The term steatohepatitis (fatty liver with inflammation) was kept. Older studies, including many in the research lists below, use the names NAFLD and NASH (non-alcoholic steatohepatitis).
Two Drug Trials in Fatty-Liver Inflammation
Vitamin E and pioglitazone (PIVENS, 2010). In this trial, 247 adults with non-alcoholic steatohepatitis and without diabetes took vitamin E 800 IU a day, the diabetes drug pioglitazone 30 mg a day, or placebo for 96 weeks. Liver biopsies improved in 43% on vitamin E versus 19% on placebo; the 34% on pioglitazone did not reach the trial’s threshold for significance. Both lowered liver enzymes, liver fat and inflammation, but neither improved scarring (fibrosis). People on pioglitazone gained more weight; other side effects were similar across the three groups.
Resmetirom (MAESTRO-NASH, 2024). In this phase 3 trial, 966 adults with biopsy-confirmed non-alcoholic steatohepatitis and liver scarring (fibrosis stage F1B to F3, short of cirrhosis) took resmetirom — a liver-directed drug that acts on the thyroid hormone receptor beta — at 80 mg or 100 mg once a day, or placebo. After 52 weeks the steatohepatitis resolved without worse scarring in 25.9% and 29.9% of people on the two doses versus 9.7% on placebo, and scarring improved by at least one stage in 24.2% and 25.9% versus 14.2%. LDL cholesterol fell by 13.6% and 16.3% at 24 weeks. Diarrhoea and nausea were more common on resmetirom; serious adverse events were similar across groups (10.9%, 12.7% and 11.5%). The trial report notes that the disease had no approved treatment before it; the trial was funded by the drug’s manufacturer.
Research Papers: Bile Flow & TUDCA
- TUDCA mechanism in cholestatic liver disease (Beuers et al.) — PubMed: TUDCA cholestasis mechanism
- Ursodeoxycholic acid (UDCA) for primary biliary cholangitis (PBC) — PubMed: UDCA for PBC
- Endoplasmic reticulum stress and TUDCA as a chemical chaperone — PubMed: TUDCA ER stress
- Bile acid composition shifts in liver disease (cholestasis, NAFLD) — PubMed: Bile acid pool
- Enterohepatic circulation and beta-glucuronidase deconjugation — PubMed: Enterohepatic deconjugation
- FXR (farnesoid X receptor) and bile acid signaling — PubMed: FXR signaling
- TGR5 (GPBAR1) receptor and bile acid metabolic effects — PubMed: TGR5 receptor
- Cholestasis-induced hepatocyte apoptosis and TUDCA cytoprotection — PubMed: Cholestasis apoptosis
- Post-cholecystectomy bile dynamics and digestive effects — PubMed: Post-cholecystectomy
- Bile acid sequestrants and serum bile acid pharmacology — PubMed: Bile acid sequestrants
Research Papers: Castor Oil Packs
- Tunaru S, Althoff TF, Nüsing RM, Diener M, Offermanns S (2012). Castor oil induces laxation and uterus contraction via ricinoleic acid activating prostaglandin EP3 receptors. Proceedings of the National Academy of Sciences of the United States of America 109(23):9179–84 — PubMed PMID: 22615395
- Arslan GG, Eşer I (2011). An examination of the effect of castor oil packs on constipation in the elderly. Complementary Therapies in Clinical Practice 17(1):58–62 (a before-and-after study in two rest homes, not a randomised trial) — PubMed PMID: 21168117
- Topical ricinoleic acid and anti-inflammatory effects — PubMed: Topical anti-inflammatory
- Lymphatic drainage and abdominal manual therapy — PubMed: Lymphatic drainage
- Vagal tone and parasympathetic activation in topical abdominal therapies — PubMed: Vagal tone
- Castor oil as ancient and traditional remedy historical review — PubMed: Historical castor oil
- Ricinus communis pharmacology and ricin toxicology — PubMed: Ricinus pharmacology
- Cold-pressed vs hexane-extracted oils, contaminant profile — PubMed: Cold-pressed oils
- Heat therapy and visceral blood flow — PubMed: Heat and visceral flow
- Skin absorption of fatty acids and topical penetration — PubMed: Skin penetration
Research Papers: Coffee & Liver
- Kennedy OJ, Roderick P, Buchanan R, Fallowfield JA, Hayes PC, Parkes J (2016). Systematic review with meta-analysis: coffee consumption and the risk of cirrhosis. Alimentary Pharmacology & Therapeutics 43(5):562–74 — PubMed PMID: 26806124
- Kennedy OJ, Roderick P, Buchanan R, Fallowfield JA, Hayes PC, Parkes J (2017). Coffee, including caffeinated and decaffeinated coffee, and the risk of hepatocellular carcinoma: a systematic review and dose-response meta-analysis. BMJ Open 7(5):e013739 — PubMed PMID: 28490552
- Coffee and NAFLD progression — PubMed: Coffee and NAFLD
- Coffee and serum ALT/GGT in epidemiologic studies — PubMed: Coffee and ALT/GGT
- Cafestol and kahweol induction of Phase II enzymes — PubMed: Cafestol/kahweol Phase II
- Chlorogenic acid and hepatic antioxidant effects — PubMed: Chlorogenic acid
- Filtered vs unfiltered coffee and serum cholesterol (cafestol effect) — PubMed: Cafestol cholesterol
- Caffeine adenosine receptor antagonism and hepatic stellate cells — PubMed: Caffeine and stellate cells
- Coffee and hepatic fibrosis in chronic hepatitis C — PubMed: Coffee and HCV fibrosis
- Coffee and gallstone disease risk — PubMed: Coffee and gallstones
Research Papers: Glutathione Support
- Kumar P, Liu C, Hsu JW, Chacko S, Minard C, Jahoor F, Sekhar RV (2021). Glycine and N-acetylcysteine (GlyNAC) supplementation in older adults improves glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, insulin resistance, endothelial dysfunction, genotoxicity, muscle strength, and cognition: Results of a pilot clinical trial. Clinical and Translational Medicine 11(3):e372 — PubMed PMID: 33783984
- N-acetylcysteine for acetaminophen overdose (FDA-approved) — PubMed: NAC for acetaminophen
- Glycine as the rate-limiting amino acid for glutathione synthesis — PubMed: Glycine and GSH synthesis
- Selenium and glutathione peroxidase enzyme activity — PubMed: Selenium and GPx
- Silymarin (milk thistle) and hepatic glutathione preservation — PubMed: Silymarin GSH
- Oral glutathione bioavailability and liposomal forms — PubMed: Oral GSH bioavailability
- Sublingual and intravenous glutathione pharmacokinetics — PubMed: GSH pharmacokinetics
- Glutathione depletion in NAFLD and chronic liver disease — PubMed: GSH depletion in liver disease
- NAC and idiosyncratic drug-induced liver injury (DILI) — PubMed: NAC and DILI
- Cysteine availability and rate-limiting role in GSH synthesis — PubMed: Cysteine and GSH
Research Papers: Cross-Cutting (Phase I/II, NAFLD, Hepatoprotection)
- Cytochrome P450 induction and inhibition by dietary phytochemicals — PubMed: CYP450 dietary
- Cruciferous vegetables and Phase II enzyme induction (sulforaphane) — PubMed: Sulforaphane and Nrf2
- Nrf2/Keap1 pathway as master regulator of antioxidant response — PubMed: Nrf2/Keap1
- NAFLD prevalence and current management guidelines — PubMed: NAFLD management
- Methionine cycle, SAM, homocysteine and hepatic methylation — PubMed: Methionine cycle
- Choline deficiency and fatty liver pathogenesis — PubMed: Choline and fatty liver
- Berberine for NAFLD and metabolic syndrome — PubMed: Berberine for NAFLD
- Sanyal AJ, Chalasani N, Kowdley KV, et al. (2010). Pioglitazone, vitamin E, or placebo for nonalcoholic steatohepatitis. New England Journal of Medicine 362(18):1675–85 (the PIVENS trial; vitamin E 800 IU daily) — PubMed PMID: 20427778
- Harrison SA, Bedossa P, Guy CD, et al. (2024). A Phase 3, Randomized, Controlled Trial of Resmetirom in NASH with Liver Fibrosis. New England Journal of Medicine 390(6):497–509 — PubMed PMID: 38324483
- Rinella ME, Lazarus JV, Ratziu V, et al. (2023). A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology 78(6):1966–1986 — PubMed PMID: 37363821
- Gut-liver axis: dysbiosis, lipopolysaccharide (LPS) endotoxemia, and hepatic inflammation — PubMed: Gut-liver axis
- Alcohol metabolism, aldehyde dehydrogenase 2 (ALDH2) polymorphism, and hepatic toxicity — PubMed: ALDH2 polymorphism
External Authoritative Resources
- AASLD — American Association for the Study of Liver Diseases Practice Guidelines
- NIDDK — Liver Disease Information
- Linus Pauling Institute — Phytochemicals and Detoxification
- LiverTox (U.S. National Institutes of Health, NIH) — Drug-Induced Liver Injury Database
- PubMed — Liver detoxification & hepatoprotection