⚠ Evidence warning: Clinical trials or other evidence do not support the claims that sibling-controlled and Mendelian randomization studies show the coffee-liver link is causal, that coffee is a low-cost liver-cancer adjunct with no drug equivalent for people with cirrhosis or chronic viral hepatitis, that enzyme effects are independent of alcohol, body mass index and viral hepatitis and appear within 8-12 weeks, and that specialty coffee has meaningfully higher polyphenol content. This page keeps it as a report of what people, websites or other media say.
Liver Cleansing — Coffee and Liver
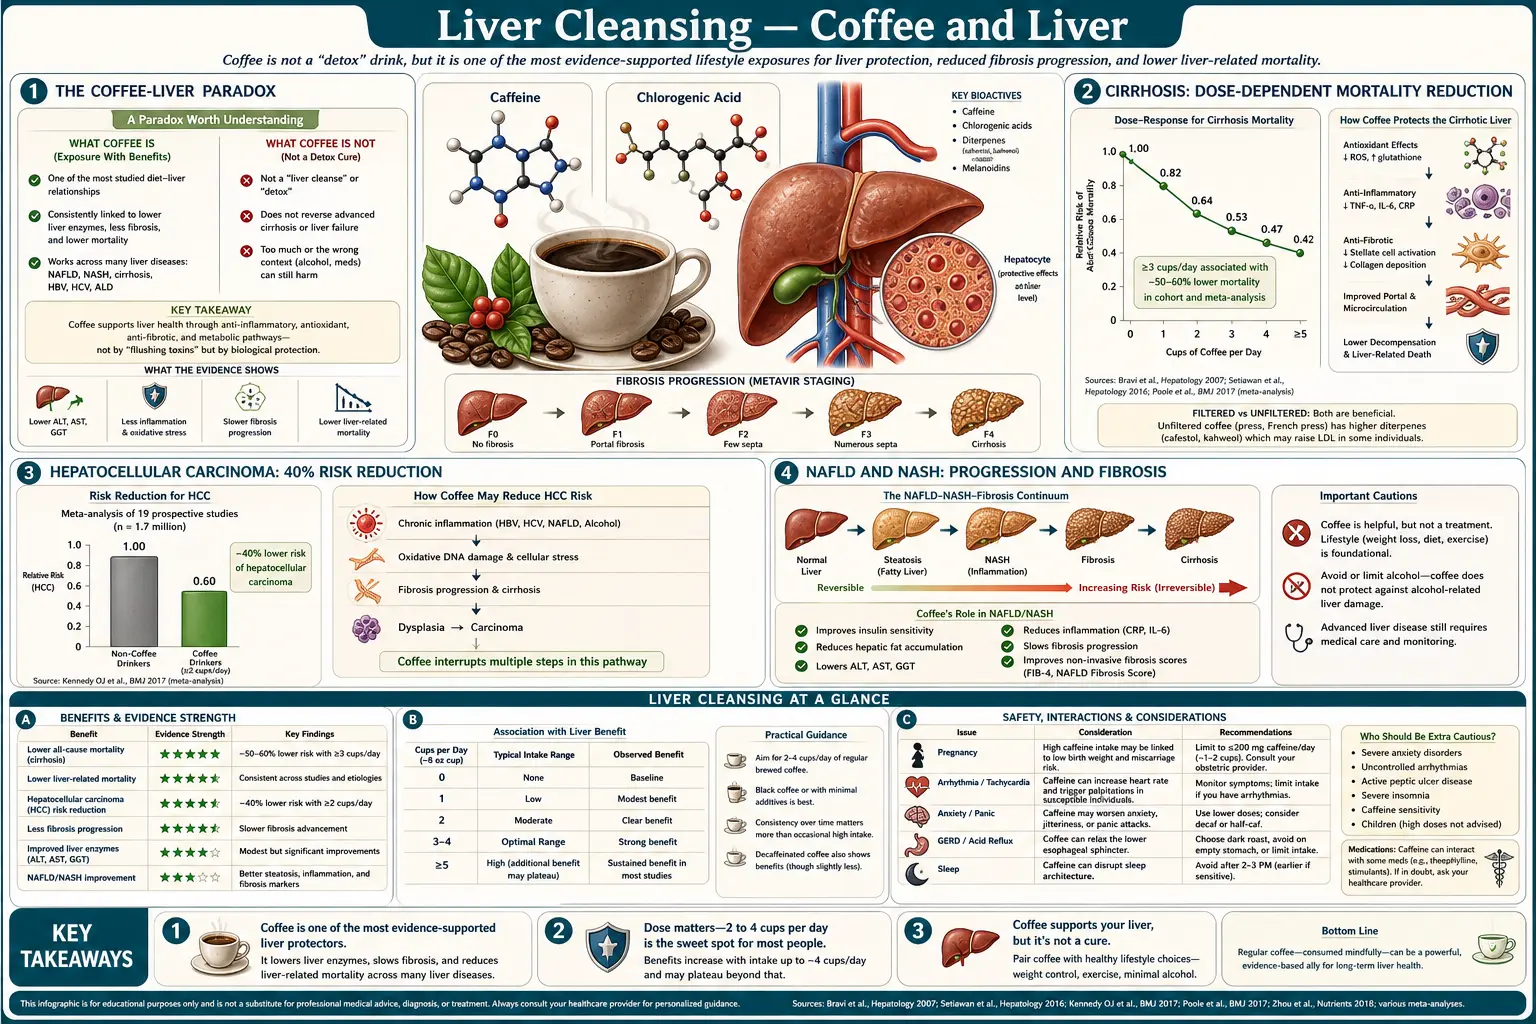
Coffee's relationship with the liver is one of the strongest and most reproducible findings in nutritional epidemiology, and a paradox for anyone who instinctively classifies coffee as a stressor. Across successive meta-analyses of observational studies, regular coffee drinking is associated with less cirrhosis (about 44% lower risk for every two extra cups a day in a 2016 meta-analysis), less hepatocellular carcinoma (about 40% lower risk in coffee drinkers than non-drinkers in a 2013 meta-analysis), non-alcoholic fatty liver disease (NAFLD) progression, hepatic fibrosis in chronic hepatitis B and C, and serum alanine aminotransferase (ALT) and gamma-glutamyl transferase (GGT) — the conventional biomarkers of hepatocellular injury. The 2024 guideline of the European Association for the Study of the Liver (EASL), written with the European diabetes and obesity associations, mentions coffee as a statement of the evidence, not as a recommendation: in adults with fatty liver disease, coffee “has been associated with improvements in liver damage and reduced liver-related clinical outcomes in observational studies” (level of evidence 4), with no number of cups given. The mechanisms span cafestol and kahweol's induction of Phase II conjugation enzymes, chlorogenic acid's antioxidant effect, caffeine's adenosine-receptor antagonism on hepatic stellate cells, and altered bile acid composition. This deep-dive walks through the epidemiology, the molecular mechanisms, the filtered-versus-unfiltered cholesterol controversy, and the amounts and brewing methods the studies describe.
Table of Contents
- The Coffee-Liver Paradox
- Cirrhosis: Dose-Dependent Mortality Reduction
- Hepatocellular Carcinoma: 40% Risk Reduction
- Non-Alcoholic Fatty Liver Disease and Non-Alcoholic Steatohepatitis: Progression and Fibrosis
- Serum Alanine Aminotransferase and Gamma-Glutamyl Transferase: Biomarker Evidence
- Mechanisms: Cafestol, Kahweol, Chlorogenic Acid, Caffeine
- Filtered vs Unfiltered: The Cholesterol Trade-Off
- Practical Dosing and Brewing Method
- Who the Research Raises Concerns For
- Key Research Papers
- Connections
- Featured Videos
The Coffee-Liver Paradox
Coffee is intuitively a stressor. It is the most widely consumed psychostimulant on the planet, raises sympathetic tone, increases cortisol, and produces tolerance and withdrawal patterns characteristic of an addictive substance. A reasonable first guess would be that habitual coffee consumption is hepatotoxic, particularly given that the liver is the site of caffeine metabolism (CYP1A2-mediated demethylation to paraxanthine, theobromine, and theophylline).
The data point the opposite direction. The first signals appeared in Japanese cohort studies in the 1980s and 1990s showing that coffee drinkers had lower serum gamma-glutamyl transpeptidase (gamma-glutamyl transferase) than non-drinkers, even after adjustment for alcohol intake. Successive cohorts confirmed lower alanine aminotransferase, lower alkaline phosphatase, and lower bilirubin in coffee drinkers. The signal was initially dismissed as confounding (perhaps coffee drinkers had healthier lifestyles overall, perhaps reverse causation explained the finding). Multivariate adjustment, sibling-controlled studies, and Mendelian randomization analyses using CYP1A2 polymorphisms as instrumental variables have substantially weakened these explanations — the coffee-liver association appears to be genuine and causal, not confounded. Later studies adjusted for many lifestyle factors, but the evidence is still observational, and reverse causation has not been ruled out: the 2013 Bravi meta-analysis of liver cancer noted that “the inverse association might partly or largely exist because patients with liver and digestive diseases reduce their coffee intake.”
What is not known. The cirrhosis, liver-cancer and fatty-liver figures on this page all come from observational studies — case-control and cohort studies that compare coffee drinkers with non-drinkers. They show an association, not proof that coffee causes the lower risk. People who are already ill may cut down on coffee, which can make coffee look protective. The meta-analyses cited here pooled observational studies, not randomized trials in which people were assigned to drink coffee or not.
The 2024 EASL-EASD-EASO Clinical Practice Guidelines (European Association for the Study of the Liver, with the European associations for the study of diabetes and of obesity) on metabolic dysfunction-associated steatotic liver disease (MASLD, the new name for non-alcoholic fatty liver disease) mention coffee once, as a statement rather than a recommendation: “In adults with MASLD, coffee consumption has been associated with improvements in liver damage and reduced liver-related clinical outcomes in observational studies” (level of evidence 4, strong consensus). The guideline gives no number of cups.
Cirrhosis: Dose-Dependent Mortality Reduction
The Kennedy 2016 meta-analysis pooled nine studies — five cohort studies and four case-control studies — with 432,133 participants and 1,990 cases of cirrhosis. For each two extra cups of coffee a day, the pooled relative risk of cirrhosis was 0.56 (about 44% lower); it was 0.58 in the cohort studies, 0.52 in the case-control studies, 0.62 for alcoholic cirrhosis and 0.55 for death from cirrhosis. The Klatsky 2006 Kaiser Permanente cohort of 125,580 adults (330 later diagnosed with cirrhosis) found the link mainly for alcoholic cirrhosis — relative risk 0.2 at four or more cups a day compared with none — while for the 131 people with non-alcoholic cirrhosis the results were not statistically significant (relative risk 0.7 at four or more cups, 95% confidence interval 0.4–1.3).
The mechanistic plausibility is strong. Hepatic fibrosis — the precursor to cirrhosis — is driven by activated hepatic stellate cells (HSCs), which transdifferentiate from quiescent vitamin-A-storing cells into proliferating myofibroblasts producing excess collagen. Caffeine antagonizes adenosine A1 and A2A receptors on hepatic stellate cells, reducing their activation. Chlorogenic acid has direct anti-fibrotic effects in animal models. Cafestol upregulates the Nrf2 antioxidant response, reducing the lipid peroxidation that drives chronic stellate cell activation. The combined effect is meaningful clinical fibrosis reduction in long-term coffee drinkers.
For people with established chronic liver disease (hepatitis B virus (HBV), hepatitis C virus (HCV), fatty liver disease, alcoholic liver disease), the 2024 EASL-EASD-EASO guideline sets no coffee amount; its one coffee statement covers adults with MASLD and rests on observational studies (level of evidence 4).
Hepatocellular Carcinoma: 40% Risk Reduction
Hepatocellular carcinoma (HCC) is the sixth most common cancer worldwide and the third leading cause of cancer death, typically arising on a background of chronic liver inflammation and cirrhosis. The Bravi 2013 meta-analysis pooled 16 studies (8 case-control, 8 cohort; 3,153 HCC cases): any coffee drinking was linked with a 40% lower risk of HCC than none (relative risk 0.60), with relative risks of 0.72 for low and 0.44 for high consumption, and 0.80 (about 20% lower) for each extra cup a day. A 2017 meta-analysis by the same group, limited to 12 prospective cohort studies (3,414 cases), found a relative risk of 0.85 (about 15% lower) for each extra daily cup and 0.50 for high consumption.
The 2017 analysis also covered chronic liver disease, in six cohort studies (1,463 cases): the risk was 0.35 times as high in heavy coffee drinkers as in non-drinkers, and 26% lower for each extra daily cup (relative risk 0.74).
The effect was consistent across:
- Underlying liver disease etiology — hepatitis B virus, hepatitis C virus, alcoholic liver disease, and non-alcoholic fatty liver disease-associated HCC all showed the inverse coffee-cancer association
- Geographic region — the effect appeared in European, North American, and East Asian cohorts
- Sex — consistent reduction in both men and women
- Coffee preparation — both filtered and unfiltered coffee showed protective effects, though most studies cannot distinguish brewing methods reliably
The mechanism is presumed to be a combination of (a) reduced underlying cirrhosis (HCC arises from cirrhotic liver in most cases), (b) anti-inflammatory and antioxidant effects of polyphenols, (c) direct chemopreventive effects of cafestol/kahweol on Phase II enzyme induction (these compounds upregulate glutathione S-transferase and UDP-glucuronosyltransferase activity, which clear pro-carcinogens), and (d) caffeine's effect on cell-cycle regulation and apoptosis in transformed hepatocytes.
For patients with established cirrhosis or chronic viral hepatitis on HCC surveillance, regular coffee consumption is a low-cost adjunct intervention with no equivalent pharmacologic chemoprevention available. For people with established cirrhosis or chronic viral hepatitis, these liver-cancer figures come from observational studies only; the meta-analyses pooled case-control and cohort studies, not trials in which coffee was given to prevent cancer.
Non-Alcoholic Fatty Liver Disease and Non-Alcoholic Steatohepatitis: Progression and Fibrosis
Non-alcoholic fatty liver disease (NAFLD) is the leading cause of chronic liver disease worldwide, affecting approximately 25% of the global adult population. The progressive form, non-alcoholic steatohepatitis (NASH), affects approximately 5% and is the fastest-growing indication for liver transplantation in the United States. Lifestyle intervention is the cornerstone of management; pharmacotherapy options are limited.
Coffee consumption is associated with:
- Lower prevalence of non-alcoholic fatty liver disease — in the Wijarnpreecha 2017 meta-analysis of five observational studies, coffee drinkers had a 29% lower risk of non-alcoholic fatty liver disease (pooled relative risk 0.71); the authors wrote that whether coffee could be considered a preventive measure “needs further investigations”
- Reduced progression from steatosis to non-alcoholic steatohepatitis — longitudinal cohorts suggest slower histologic progression in coffee drinkers
- Lower fibrosis stage on biopsy — in the same meta-analysis, non-alcoholic fatty liver disease patients who drank coffee regularly had about 30% lower risk of liver fibrosis (pooled relative risk 0.70)
- Improved insulin sensitivity — partially mediating effects on hepatic fat accumulation
- Better serum biomarker profile — lower alanine aminotransferase, lower gamma-glutamyl transferase, lower FibroScan stiffness measurements
The 2024 EASL-EASD-EASO Clinical Practice Guidelines on Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD, the renamed non-alcoholic fatty liver disease) mention coffee in a statement, not in their lifestyle recommendations: “In adults with MASLD, coffee consumption has been associated with improvements in liver damage and reduced liver-related clinical outcomes in observational studies” (level of evidence 4, strong consensus). The guideline gives no number of cups and no recommendation grade for coffee.
Serum Alanine Aminotransferase and Gamma-Glutamyl Transferase: Biomarker Evidence
The serum biomarker evidence is robust and dose-dependent. Klatsky 2006 compared enzyme levels at the start of its Kaiser Permanente cohort of 125,580 adults: people drinking four or more cups of coffee a day, compared with none, had lower odds of a high aspartate aminotransferase (AST) level (odds ratio 0.5) and of a high alanine aminotransferase level (odds ratio 0.6), with stronger inverse relations in people who drank large quantities of alcohol. These effects were independent of alcohol consumption, body mass index (BMI), and viral hepatitis status. The Honjo 2001 study in Japanese workers found similar dose-response relationships, with the largest effects in heavy alcohol consumers (suggesting coffee may attenuate alcohol-related hepatotoxicity).
The biomarker findings are corroborated by FibroScan measurements: regular coffee consumption is associated with lower liver stiffness measurements, consistent with reduced fibrosis. The Modi 2010 study of 177 patients undergoing liver biopsy (121 of them with chronic hepatitis C) found that caffeine intake above about 308 mg a day (roughly 2.25 cups of coffee) was linked with lower odds of advanced fibrosis (odds ratio 0.33; 0.25 after adjustment; 0.19 in the hepatitis C group); caffeine from other sources and decaffeinated coffee were not linked with less fibrosis.
Mildly raised liver enzymes (alanine aminotransferase 50-80 international units/L) with no obvious cause are the common picture of early non-alcoholic fatty liver disease. In the studies above, the lower enzyme levels and less fibrosis were seen at about two or more cups a day (above about 2.25 cups' worth of caffeine in Modi 2010; four or more cups in Klatsky 2006); these were observational comparisons, not trials of adding coffee. The biomarker response is typically visible within 8-12 weeks alongside weight loss and dietary improvements.
Mechanisms: Cafestol, Kahweol, Chlorogenic Acid, Caffeine
Coffee contains approximately 1,500 identified compounds. The major bioactive constituents relevant to liver protection:
- Cafestol (and its relative kahweol) — diterpene molecules in the oily fraction of coffee. In animal and cell-culture studies they induce the liver's Phase II detoxification (conjugating) enzymes — they upregulate glutathione S-transferase (GST), UDP-glucuronosyltransferase (UGT), and NAD(P)H:quinone oxidoreductase 1 (NQO1; NAD(P)H is nicotinamide adenine dinucleotide phosphate) by 2- to 4-fold in liver cells. In those animal and cell experiments, the effect reduced the DNA damage caused by aflatoxin B1, polycyclic aromatic hydrocarbons (PAHs, as from grilled meat), heterocyclic amines, and other dietary procarcinogens; human evidence comes from human liver cell lines. Cafestol and kahweol are largely removed by paper filtration; espresso, French press, and Scandinavian boiled coffee retain them.
- Chlorogenic acid (a family of esters of caffeic acid with quinic acid) — the dominant polyphenol in coffee, present at approximately 200-550 mg per cup. Powerful antioxidant, anti-inflammatory, and direct anti-fibrotic effects in hepatic stellate cells. Inhibits glucose-6-phosphatase, partially explaining improvements in hepatic insulin sensitivity. Survives filtration.
- Caffeine — antagonizes adenosine A1 and A2A receptors. In hepatic stellate cells, adenosine signaling promotes activation and fibrogenesis; caffeine's antagonism therefore has anti-fibrotic effects. Caffeine also induces autophagy in hepatocytes, clearing intracellular lipid droplets in fatty liver. The fibrosis-protective effect of coffee partially survives decaffeination but is attenuated — the caffeine contribution is real but not the whole story.
- Trigonelline — alkaloid present at approximately 1% of dry coffee weight; degraded to N-methylpyridinium during roasting. Modest effects on glucose metabolism and gene expression.
- Melanoidins — brown polymer products of the Maillard reaction during roasting. Antioxidant and prebiotic effects.
In animal studies, the cafestol/kahweol enzyme induction was seen in liver, intestinal and kidney tissue. The net Phase II induction by cafestol/kahweol is one of the largest food-driven enzyme inductions ever documented. Separately, coffee is one of the few beverages that achieves measurable changes in drug clearance — CYP1A2-substrate drugs (theophylline, clozapine, olanzapine, tizanidine) have measurably faster clearance in habitual coffee drinkers.
Filtered vs Unfiltered: The Cholesterol Trade-Off
The cafestol and kahweol that drive Phase II enzyme induction also have an unwanted effect: they raise serum low-density lipoprotein (LDL) cholesterol. The Urgert 1996 trial gave 46 healthy Dutch volunteers five to six strong cups (0.9 litres) a day of either cafetière (French press) or filtered coffee for 24 weeks: cafetière coffee raised low-density lipoprotein cholesterol by 9-14%, still 0.26 mmol/L above filtered coffee at 24 weeks. The mechanism is suppression of hepatic low-density lipoprotein receptor expression by cafestol, slowing low-density lipoprotein clearance.
Unfiltered coffee can also raise a liver enzyme. In the same 24-week trial, cafetière coffee raised alanine aminotransferase (ALT, an enzyme released by injured liver cells) by up to 80% above baseline compared with filtered coffee, and it was still 45% higher at 24 weeks. ALT rose above the upper limit of normal in 8 of the 22 people drinking cafetière coffee, to twice the limit in 3 of them. All the increases reversed after the trial coffee was stopped. The authors linked the effect to cafestol and kahweol, which a paper filter holds back.
Paper filtration removes essentially all cafestol and kahweol. Filtered drip coffee, pour-over, and coffee from capsule machines whose pods contain a paper filter deliver chlorogenic acid, caffeine, melanoidins, and trigonelline without the diterpenes. The result: most of the liver-protective effect is retained, while the cholesterol effect is eliminated.
French press, espresso, Turkish coffee, Scandinavian boiled coffee (stovetop or moka pot), and cloth-filter coffee deliver the full diterpene load. Espresso has the highest cafestol concentration per volume but small typical serving size, so the daily dose is modest at 1-2 shots. Heavy French-press drinking (4+ cups/day) is the lifestyle pattern most associated with cholesterol elevation.
On this evidence, filtered drip coffee or pour-over with a paper filter carries the liver-related compounds without the cholesterol-raising diterpenes, and 1-2 shots of espresso a day deliver a modest diterpene dose. The cholesterol concern from habitual heavy French-press or unfiltered coffee is greatest for people with elevated low-density lipoprotein, established cardiovascular disease, or familial hypercholesterolemia.
Practical Dosing and Brewing Method
The dose-response curves from epidemiology consistently show maximum hepatoprotective benefit between 2 and 4 cups per day. Above 4 cups the curve typically plateaus or slightly declines (potentially because heavy drinkers are dose-responding to lifestyle stressors that themselves harm the liver). The amounts and methods described:
- 2-3 cups daily of filtered drip coffee — the range most often linked with lower liver risk in the studies above
- Earlier in the day — caffeine half-life is approximately 5-6 hours, with substantial individual variation. Drinking coffee after 2 PM (or earlier for slow metabolizers) impairs sleep quality, which itself harms metabolic health.
- Milk or cream — protein binds polyphenols but does not eliminate the hepatoprotective effect; the Klatsky and Bravi cohorts included milk drinkers and observed the protective effect
- Sugar negates much of the metabolic benefit — the inverse association with non-alcoholic fatty liver disease weakens or reverses in heavy sugar-added coffee drinkers.
- Quality matters — freshly ground, recently roasted, properly extracted coffee retains more chlorogenic acid than stale grocery-store pre-ground coffee. Specialty third-wave coffee is not just snobbery; the polyphenol content is meaningfully higher.
- Decaf retains most of the benefit but not all — decaffeinated coffee retains chlorogenic acid, cafestol (in unfiltered form), and melanoidins. The caffeine contribution to stellate cell adenosine antagonism is lost. For caffeine-sensitive people (anxiety disorders, severe insomnia, atrial fibrillation), decaf removes the caffeine. In UK Biobank (494,585 adults followed for a median 10.7 years), coffee drinkers had a 21% lower risk of chronic liver disease (hazard ratio 0.79) and a 49% lower risk of dying from it (hazard ratio 0.51) than non-drinkers, and decaffeinated, instant and ground coffee each showed similar associations — whereas the smaller Modi 2010 biopsy study found no fibrosis link for decaf.
Who the Research Raises Concerns For
- Atrial fibrillation in active rhythm or with rate-control struggles — caffeine can trigger paroxysms in some patients. Habitual coffee drinkers with controlled AFib usually tolerate continued coffee; people with symptomatic AFib are the group in which caffeine-triggered episodes are the concern.
- Severe gastroesophageal reflux — coffee reduces lower esophageal sphincter pressure and is a common gastroesophageal reflux disease (GERD) trigger. Some patients tolerate cold-brew (lower acidity) better than hot brewed.
- Active peptic ulcer disease — coffee increases gastric acid secretion and can delay ulcer healing.
- Severe anxiety disorders, particularly panic disorder — caffeine can trigger panic attacks. Decaf removes the caffeine.
- Pregnancy — current guidance limits caffeine to approximately 200 mg/day (about 2 cups). Coffee's hepatoprotective effect in pregnancy is uncertain; the caffeine concerns dominate.
- Iron-deficiency anemia — coffee polyphenols substantially inhibit non-heme iron absorption (35-95% reduction depending on dose and timing). Coffee drunk at least one hour away from meals and iron supplements is the timing usually described for people with iron deficiency.
- Severe insomnia regardless of timing — even morning coffee can impair next-night sleep in some individuals with delayed caffeine metabolism (CYP1A2 slow metabolizers, approximately 30% of the population). Decaf removes the caffeine.
- Drug interactions — caffeine competes with theophylline, ciprofloxacin, clozapine, olanzapine, tizanidine, and other CYP1A2 substrates. Habitual coffee induces CYP1A2 over weeks, accelerating clearance of these drugs.
Key Research Papers
- Kennedy OJ, Roderick P, Buchanan R, Fallowfield JA, Hayes PC, Parkes J (2016). Systematic review with meta-analysis: coffee consumption and the risk of cirrhosis. Aliment Pharmacol Ther;43(5):562-574. — PubMed PMID: 26806124
- Bravi F, Bosetti C, Tavani A, Gallus S, La Vecchia C (2013). Coffee reduces risk for hepatocellular carcinoma: an updated meta-analysis. Clin Gastroenterol Hepatol;11(11):1413-1421. — PubMed PMID: 23660416
- Bravi F, Tavani A, Bosetti C, Boffetta P, La Vecchia C (2017). Coffee and the risk of hepatocellular carcinoma and chronic liver disease: a systematic review and meta-analysis of prospective studies. Eur J Cancer Prev;26(5):368-377. — PubMed PMID: 27111112
- Klatsky AL, Morton C, Udaltsova N, Friedman GD (2006). Coffee, cirrhosis, and transaminase enzymes. Arch Intern Med;166(11):1190-1195. — PubMed PMID: 16772246
- Wijarnpreecha K, Thongprayoon C, Ungprasert P (2017). Coffee consumption and risk of nonalcoholic fatty liver disease: a systematic review and meta-analysis. Eur J Gastroenterol Hepatol;29(2):e8-e12. — PubMed PMID: 27824642
- Modi AA, Feld JJ, Park Y, Kleiner DE, Everhart JE, Liang TJ, Hoofnagle JH (2010). Increased caffeine consumption is associated with reduced hepatic fibrosis. Hepatology;51(1):201-209. — PubMed PMID: 20034049
- Urgert R, Katan MB (1997). The cholesterol-raising factor from coffee beans. Annu Rev Nutr;17:305-324. (cafestol mechanism) — PubMed PMID: 9240930
- Urgert R, Meyboom S, Kuilman M, Rexwinkel H, Vissers MN, Klerk M, Katan MB (1996). Comparison of effect of cafetière and filtered coffee on serum concentrations of liver aminotransferases and lipids: six month randomised controlled trial. BMJ;313(7069):1362-1366. — PubMed PMID: 8956701
- Cavin C, Holzhaeuser D, Scharf G, Constable A, Huber WW, Schilter B (2002). Cafestol and kahweol, two coffee specific diterpenes with anticarcinogenic activity. Food Chem Toxicol;40(8):1155-1163. — PubMed PMID: 12067578
- European Association for the Study of the Liver (EASL); European Association for the Study of Diabetes (EASD); European Association for the Study of Obesity (EASO) (2024). EASL-EASD-EASO Clinical Practice Guidelines on the management of metabolic dysfunction-associated steatotic liver disease (MASLD). J Hepatol;81(3):492-542. — PubMed PMID: 38851997
- Kennedy OJ, Fallowfield JA, Poole R, Hayes PC, Parkes J, Roderick PJ (2021). All coffee types decrease the risk of adverse clinical outcomes in chronic liver disease: a UK Biobank study. BMC Public Health;21(1):970. — PubMed PMID: 34154561
- Honjo S et al. (2001). Coffee consumption and serum aminotransferases in middle-aged Japanese men. J Clin Epidemiol. — PubMed PMID: 11470392
- Salomone F et al. (2017). Molecular bases underlying the hepatoprotective effects of coffee. Nutrients. — PubMed PMID: 28124992
- Setiawan VW et al. (2015). Association of coffee intake with reduced incidence of liver cancer and death from chronic liver disease in the US Multiethnic Cohort. Gastroenterology. — PubMed PMID: 25305507
- Tverdal A et al. (2020). Coffee consumption and mortality from cardiovascular diseases and total mortality. Eur J Prev Cardiol. — PubMed PMID: 32320635