⚠ Evidence warning: Clinical trials or other evidence do not support the claim that intravenous glutathione helps Parkinson's disease, chronic fatigue and acute toxic exposures, and that the liver-cleansing protocol improves energy, sleep, skin and digestion. This page keeps it as a report of what people, websites or other media say.
Liver Cleansing — Glutathione Support
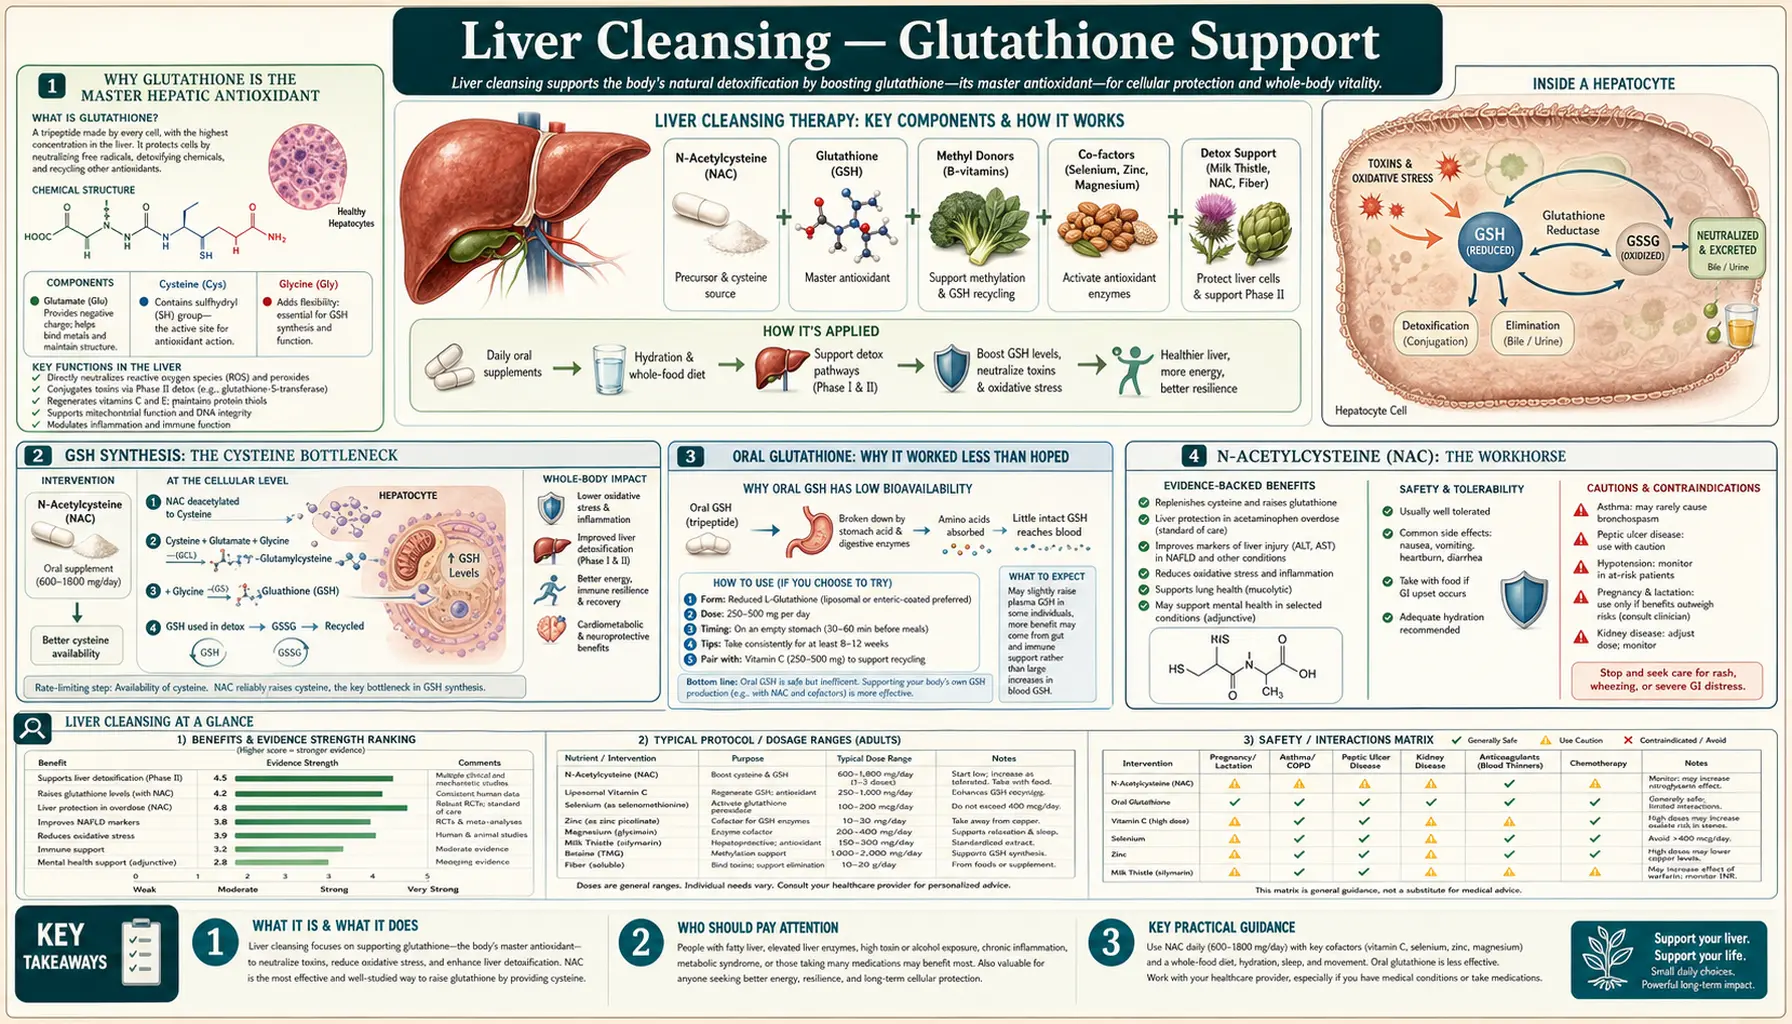
Glutathione (gamma-glutamyl-cysteinyl-glycine, reduced glutathione, GSH) is the master antioxidant and the obligate cofactor for Phase II conjugation of acetaminophen, aflatoxin, mercury, lipid peroxides, and many environmental electrophiles. The liver maintains the highest glutathione concentration of any organ (5-10 mM intracellularly), and depletion of hepatic glutathione is the central event in acetaminophen-induced acute liver failure, the leading cause of acute liver failure in the U.S. The classic finding that oral glutathione is poorly absorbed (it is hydrolyzed in the gut before reaching the portal circulation) is partially true but has been substantially revised by recent liposomal and sublingual formulation studies. The reliable approach is supplying precursors and cofactors: N-acetylcysteine (NAC) for the cysteine moiety (typically rate-limiting), glycine (rate-limiting in aging), and selenium for the glutathione peroxidase enzyme that uses reduced glutathione as substrate. In the 2021 GlyNAC pilot trial (eight older adults, no placebo group), 24 weeks of glycine plus N-acetylcysteine raised red-blood-cell glutathione by 200%; a 2023 randomized, placebo-controlled trial in 24 older adults found that glycine plus N-acetylcysteine, and not placebo, improved or corrected glutathione deficiency over 16 weeks.
Table of Contents
- Why Glutathione Is the Master Hepatic Antioxidant
- Reduced Glutathione Synthesis: The Cysteine Bottleneck
- Oral Glutathione: Why It Worked Less Than Hoped
- N-Acetylcysteine: The Workhorse
- The GlyNAC Trials: Glycine Plus N-Acetylcysteine in Older Adults
- Cofactors: Selenium, Riboflavin, B6, B12
- Milk Thistle (Silymarin) as Glutathione-Sparing
- Liposomal, Sublingual, and Intravenous Glutathione
- A Restoration Protocol Practitioners Describe
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Why Glutathione Is the Master Hepatic Antioxidant
Glutathione is a tripeptide of glutamate, cysteine, and glycine. The unusual gamma-glutamyl bond (rather than the standard peptide bond between glutamate's alpha-carboxyl and the next amino acid's amino group) makes glutathione resistant to most peptidases. It is synthesized intracellularly in nearly every human cell, with the liver as the primary biosynthetic site and net exporter to other tissues via the gamma-glutamyl cycle.
Glutathione's central role rests on its cysteine sulfhydryl (-SH) group. The thiol is a potent reducing agent (GSH/GSSG redox potential is -240 mV), making glutathione the dominant intracellular reductant in animal cells. The thiol participates in:
- Direct reduction of reactive oxygen species — hydrogen peroxide, organic hydroperoxides, and lipid peroxides are reduced to water or alcohol, with glutathione oxidized to GSSG (glutathione disulfide). The GSH/GSSG ratio (normally 100:1 in cytoplasm) is a sensitive index of oxidative stress.
- Phase II conjugation of electrophiles — glutathione S-transferase (GST) enzymes catalyze conjugation of glutathione with reactive electrophiles, neutralizing them. Acetaminophen's reactive metabolite NAPQI, aflatoxin B1's 8,9-epoxide, mercury, organophosphates, and many environmental chemicals are detoxified by this mechanism.
- Protein S-glutathionylation — reversible modification of cysteine residues on regulatory proteins, a major redox signaling mechanism
- Recycling of vitamin C and vitamin E — glutathione reduces oxidized ascorbate and tocopheryl radicals, regenerating the antioxidant pool
- Mercury and heavy-metal binding — glutathione-mercury complexes are the major export route for mercury via bile
The hepatic glutathione pool is approximately 5-10 mM intracellular concentration, with a total liver content of about 1-2 grams in an adult. Plasma glutathione concentrations are far lower (around 5 micromolar) because reduced glutathione is rapidly metabolized in extracellular space — this is why direct measurement of plasma glutathione is a poor indicator of tissue stores.
The fasting hepatic glutathione content is depleted by approximately 30% after an overnight fast and rapidly replenished with feeding. Hepatic glutathione is depleted by approximately 70-90% in acute acetaminophen overdose; depletion below 30% of normal triggers hepatocyte necrosis. This is the basis of N-acetylcysteine's use as the U.S. Food and Drug Administration-approved antidote for acetaminophen poisoning.
Reduced Glutathione Synthesis: The Cysteine Bottleneck
Glutathione is synthesized in two adenosine triphosphate-requiring steps:
- Glutamate + cysteine → gamma-glutamyl-cysteine — catalyzed by glutamate-cysteine ligase (GCL, formerly gamma-glutamylcysteine synthetase). This is the rate-limiting step, regulated by feedback inhibition from reduced glutathione itself and by substrate availability (cysteine is typically the limiting amino acid).
- Gamma-glutamyl-cysteine + glycine → glutathione — catalyzed by glutathione synthetase. Not normally rate-limiting in young adults but can become limiting in aging and in conditions with low glycine intake.
The cysteine bottleneck is the central practical issue in glutathione restoration. Cysteine is a sulfur-containing amino acid that can be either consumed directly in the diet (whey protein and animal protein sources) or synthesized from methionine via the transsulfuration pathway (methionine → SAM → SAH → homocysteine → cystathionine → cysteine, requiring vitamin B6 and serine). Free cysteine itself is unstable and somewhat cytotoxic; the body tightly regulates intracellular free cysteine concentration, which limits how much glutathione synthesis can be driven by simple cysteine supplementation.
N-acetylcysteine is the workaround — the N-acetyl group is removed inside the cell, releasing cysteine in a more regulated manner than free cysteine would provide. This is why N-acetylcysteine, not cysteine, is the standard precursor used in hepatic medicine.
The glycine arm is generally considered non-limiting in most adults, but the GlyNAC research has called this assumption into question for older adults, where glycine supplementation alongside N-acetylcysteine produces synergistic glutathione restoration that N-acetylcysteine alone does not.
The Sekhar 2011 study measured this directly. Eight older adults made red-blood-cell glutathione far more slowly than eight younger adults (absolute synthesis 0.55 versus 1.73 mmol/L of red cells per day) and had lower red-cell glycine, cysteine and glutathione. After 2 weeks of the precursors cysteine and glycine, the older adults' red-cell glutathione concentration was 94.6% higher and their absolute synthesis rate 230.9% higher, and these measures no longer differed from the younger group.
Oral Glutathione: Why It Worked Less Than Hoped
The conventional teaching for decades was that oral glutathione is useless because it is hydrolyzed in the gastrointestinal tract before reaching the portal circulation. This was based on early pharmacokinetic studies showing minimal increase in plasma glutathione after oral dosing of free reduced glutathione.
The more nuanced reality:
- Plasma glutathione is the wrong endpoint — plasma reduced glutathione is rapidly degraded by gamma-glutamyl transpeptidase (gamma-glutamyl transferase, GGT) on cell membranes, regardless of source. The relevant question is whether tissue glutathione (especially hepatic and red-blood-cell glutathione) increases.
- Tissue reduced glutathione does respond — Richie 2015 was a 6-month placebo-controlled trial in 54 non-smoking adults. At 1,000 mg/day of oral reduced glutathione, mean glutathione rose 30-35% in red blood cells (erythrocytes), plasma and lymphocytes and 260% in cheek (buccal) cells; at 250 mg/day it rose 17% in whole blood and 29% in red blood cells. Natural killer cell cytotoxicity more than doubled in the high-dose group versus placebo at 3 months. Levels returned to baseline one month after the supplement was stopped.
- Liposomal encapsulation substantially improves bioavailability — the reduced glutathione is protected from gastric hydrolysis and absorbed intact via lymphatic uptake. Sinha 2018, a 1-month pilot study in 12 healthy adults, found that liposomal reduced glutathione (500 or 1000 mg/day) raised glutathione by up to 40% in whole blood, 25% in red blood cells, 28% in plasma and 100% in peripheral blood mononuclear cells (a group of white blood cells) after 2 weeks; natural killer cell cytotoxicity rose by up to 400%.
- Sublingual reduced glutathione — bypasses gut hydrolysis. Available as troches and dissolvable tablets at 100-200 mg doses. Pharmacokinetic data are limited but suggest meaningful absorption.
- The precursor approach (N-acetylcysteine + glycine + cofactors) is still cheaper and more reliable — oral glutathione products are expensive ($30-60/month for liposomal). N-acetylcysteine + glycine + selenium produces comparable or superior tissue glutathione increases for under $20/month.
Oral glutathione is not useless, but it is generally not the most cost-effective route to higher tissue glutathione. Practitioners commonly treat the precursor strategy as the first-line approach.
N-Acetylcysteine: The Workhorse
N-acetylcysteine is the most extensively studied glutathione precursor and a U.S. Food and Drug Administration-approved drug (intravenous (IV) acetylcysteine for acetaminophen overdose; inhaled and oral acetylcysteine for mucolysis and various off-label uses). Mechanism: oral N-acetylcysteine is deacetylated in enterocytes and hepatocytes, releasing cysteine for glutathione synthesis.
Dosing for hepatic glutathione support:
- 600 mg twice daily — the standard "wellness" dose, well tolerated, modestly raises tissue glutathione over 4-8 weeks
- 1800 mg/day divided — higher-dose protocol used in some integrative medicine practices for active liver-cleansing or post-toxic-exposure recovery
- Acute acetaminophen overdose (in-hospital) — the FDA label gives a total of 300 mg/kg intravenously as either three doses over a total of 21 hours (a 150 mg/kg loading dose infused over 1 hour, then 50 mg/kg over 4 hours, then 100 mg/kg over 16 hours) or two doses over a total of 20 hours (200 mg/kg over 4 hours, then 100 mg/kg over 16 hours, for patients weighing 41 kg or more). This is the clinical pharmacology that demonstrated N-acetylcysteine's definitive efficacy.
N-acetylcysteine has documented benefits for:
- Acetaminophen overdose — U.S. Food and Drug Administration-approved indication, mortality reduction from approximately 5% to less than 1% when given within 8-10 hours of overdose
- Chronic obstructive pulmonary disease — reduces exacerbations as a mucolytic and antioxidant
- Polycystic ovary syndrome — improves insulin sensitivity and ovulation rates
- Obsessive-compulsive disorder and trichotillomania — modulates glutamatergic neurotransmission
- Non-alcoholic steatohepatitis — small trials show improvement in liver enzymes and histology
- Drug-induced liver injury — case-series evidence for drug-induced liver injury not caused by acetaminophen (anti-tuberculosis drugs, methotrexate)
Side effects are minimal at oral doses. For the intravenous form, the FDA label lists hypersensitivity (anaphylactoid) reaction rates from four published hospital series: 16%, 14%, 7% and 23% with the three-dose regimen, and 4%, 5%, 1% and 19% with the two-dose regimen; fatal anaphylaxis has been reported since approval. Oral N-acetylcysteine has a sulfur smell that some patients find off-putting; capsule formulations minimize this.
The two-dose (“two-bag”) drip is the newer, simpler option. A 2025 meta-analysis of six studies comparing it with the older three-bag drip for paracetamol (acetaminophen) poisoning found no difference in liver injury (odds ratio 0.88, 95% confidence interval 0.72-1.08) and a lower likelihood of non-allergic anaphylactoid reactions and other side effects (odds ratio 0.24, 95% confidence interval 0.17-0.35). The FDA label now lists both regimens.
The GlyNAC Trials: Glycine Plus N-Acetylcysteine in Older Adults
The most important glutathione restoration research in recent years is the GlyNAC work from Baylor College of Medicine. The first study, Kumar et al. 2021 in Clinical and Translational Medicine, was an open-label pilot trial with no placebo group: eight older adults (age 70-80) took glycine (1.33 mmol/kg/day) plus cysteine (0.81 mmol/kg/day, given as N-acetylcysteine) for 24 weeks, then stopped for 12 weeks.
Results in the 2021 pilot after 24 weeks of glycine plus N-acetylcysteine, compared with the same people before supplementation:
- Red blood cell glutathione increased by 200%
- Plasma oxidative stress markers (F2-isoprostanes) decreased by 74% (another marker, thiobarbituric acid reactive substances, fell 75%)
- Plasma inflammation markers (interleukin-6 (IL-6), tumor necrosis factor-alpha, C-reactive protein (CRP)) decreased significantly
- Insulin resistance (homeostatic model assessment of insulin resistance, HOMA-IR) was 59% lower
- Mitochondrial function (mitochondrial fuel oxidation) improved
- Endothelial function improved (blood markers of blood-vessel lining dysfunction, such as E-selectin, fell)
- Body composition improved (waist circumference decreased)
- Strength and gait speed improved
- Cognitive function improved (executive function tests)
The clinical effects beyond reduced glutathione itself — insulin sensitivity, inflammation, mitochondrial function, cognition — map onto the constellation of changes that characterize biological aging.
A randomized, placebo-controlled GlyNAC trial followed (Kumar et al. 2023, Journals of Gerontology Series A). Twenty-four older adults were randomly assigned to glycine plus N-acetylcysteine (12 people) or a placebo of the amino acid alanine (12 people) for 16 weeks. Glycine plus N-acetylcysteine, and not placebo, improved or corrected glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, insulin resistance and physical function. The trial was small; the authors reported the supplement as safe and well tolerated over the 16 weeks.
In the 2021 pilot, the gains faded once the supplement was stopped: after 12 weeks without glycine plus N-acetylcysteine, red-blood-cell glutathione fell by 67%, and the oxidative-damage markers thiobarbituric acid reactive substances and F2-isoprostanes rose by 219% and 26%. The authors concluded that continued supplementation may be required to keep the benefits.
The key insight from GlyNAC is that both glycine and N-acetylcysteine are needed. Earlier studies of N-acetylcysteine alone in aging produced modest reduced glutathione increases; earlier studies of glycine alone produced modest effects. The combination is synergistic because aging produces deficits in both the cysteine arm (driven by reduced dietary cysteine intake and reduced transsulfuration efficiency) and the glycine arm (driven by reduced dietary glycine intake; modern industrial diets are low in collagen and connective tissue, the main glycine sources).
The 2021 GlyNAC pilot used weight-based doses (glycine 1.33 mmol/kg/day and cysteine 0.81 mmol/kg/day given as N-acetylcysteine). Some practitioners describe a daily regimen of 1200-1800 mg N-acetylcysteine + 3-5 g glycine as an approximation of the GlyNAC protocol for adults over 60 with concerns about aging, recurrent illness, or compromised liver function. Cost is approximately $15-25 per month.
Cofactors: Selenium, Riboflavin, B6, B12
Glutathione without its supporting cofactors is incomplete. The key cofactors:
- Selenium — obligate cofactor for glutathione peroxidase (GPx), the enzyme that uses reduced glutathione to reduce hydrogen peroxide and lipid peroxides. Selenium is incorporated as selenocysteine into the GPx active site. Without adequate selenium, reduced glutathione cannot be deployed by GPx and accumulates uselessly while peroxide-driven oxidative stress continues. Dose: 100-200 mcg/day from selenomethionine or selenium yeast. The U.S. Recommended Dietary Allowance (RDA) is 55 mcg/day; functional repletion typically uses higher doses. The U.S. Tolerable Upper Intake Level for adults is 400 mcg/day.
- Riboflavin (vitamin B2) — cofactor for glutathione reductase, the enzyme that recycles GSSG back to reduced glutathione using reduced nicotinamide adenine dinucleotide phosphate (NADPH). Mild riboflavin deficiency reduces GSH/GSSG ratio. Dose: 25-50 mg/day. See our Vitamin B2 page.
- Vitamin B6 (pyridoxal 5-phosphate) — cofactor for cystathionine beta-synthase and cystathionase, the transsulfuration enzymes that produce cysteine from methionine. B6 deficiency can limit cysteine supply for glutathione synthesis.
- Vitamin B12 and folate — required for the methionine cycle that ultimately feeds the transsulfuration pathway. Functional B12 or folate deficiency impairs methionine availability and indirectly impairs cysteine and glutathione synthesis.
- Magnesium — cofactor for glutamate-cysteine ligase (GCL), the rate-limiting enzyme of reduced glutathione synthesis. Magnesium deficiency is associated with reduced hepatic reduced glutathione in animal models.
- Reduced nicotinamide adenine dinucleotide phosphate — the obligate electron donor for glutathione reductase, generated primarily by the pentose phosphate pathway. Reduced nicotinamide adenine dinucleotide phosphate availability depends on glucose-6-phosphate dehydrogenase activity and pentose phosphate pathway throughput.
The combined supplementation approach: N-acetylcysteine + glycine + 100-200 mcg selenomethionine + a B-complex providing 25-50 mg of B2/B6 and methylcobalamin/methylfolate addresses the full pathway in a way that any single supplement cannot.
Milk Thistle (Silymarin) as Glutathione-Sparing
Silymarin, the standardized extract of Silybum marianum, is the most-studied hepatoprotective herbal medicine. Its mechanism is multimodal — antioxidant, anti-fibrotic, membrane-stabilizing, and pro-regenerative — but one key mechanism is glutathione-sparing. Silymarin reduces the rate of glutathione consumption during oxidative stress by directly scavenging reactive species before they can react with reduced glutathione, and indirectly by stabilizing hepatocyte membranes and reducing the cellular damage that depletes reduced glutathione.
In animal models of carbon tetrachloride, acetaminophen, and ethanol-induced hepatotoxicity, silymarin pretreatment preserves hepatic glutathione despite ongoing toxicant exposure. In human studies of chronic hepatitis C and alcohol-related liver disease, silymarin reduces transaminase elevations and may slow fibrosis progression.
The standard dose is 420 mg/day of silymarin (typically delivered as 140 mg three times daily of a standardized extract containing approximately 80% silymarin). For practical clinical use, the combination of milk thistle + N-acetylcysteine + glycine + selenium provides multimodal coverage: the herb stabilizes hepatocyte membranes and scavenges reactive species; N-acetylcysteine and glycine replenish the precursor pool; selenium activates the deployable peroxidase. See our Milk Thistle page for the full pharmacology.
Liposomal, Sublingual, and Intravenous Glutathione
Beyond precursor supplementation, several direct glutathione delivery routes are available:
- Liposomal glutathione (oral) — reduced glutathione encapsulated in phosphatidylcholine liposomes that protect it from gastric hydrolysis and deliver it to enterocytes intact. The Sinha 2018 pilot study (1 month, 12 healthy adults, 500 or 1000 mg/day, no placebo group) found higher glutathione in peripheral blood mononuclear cells and other blood compartments, higher natural killer (NK) cell activity, and a 35% fall in plasma 8-isoprostane (8-iso-prostaglandin F2-alpha). Cost: $30-60/month. Practitioners describe it as an option for people who do not tolerate N-acetylcysteine.
- Sublingual glutathione — troches or rapidly dissolving tablets at 100-200 mg per dose. Bypasses gastric hydrolysis but absolute bioavailability is uncertain. Less expensive than liposomal.
- Intravenous glutathione — 600-2400 mg pushed slowly over 5-15 minutes. Bypasses absorption questions entirely. Used in some integrative practices for acute toxic exposures, Parkinson's disease, and chronic fatigue. Not U.S. Food and Drug Administration-approved for any indication; insurance does not cover. Cost: $50-150 per intravenous session.
- Inhaled glutathione — nebulized reduced glutathione (typically 600 mg) delivers reduced glutathione directly to the respiratory epithelium. Some evidence in cystic fibrosis and chronic respiratory inflammation. Off-label use.
- Transdermal glutathione — creams marketed for skin and systemic absorption. The skin penetration of intact reduced glutathione is minimal; these products are mostly marketing.
A Restoration Protocol Practitioners Describe
A consolidated regimen that integrative practitioners describe for adults aiming to restore hepatic glutathione and Phase II detoxification capacity:
- N-acetylcysteine 600 mg twice daily with meals — the foundation
- Glycine 3 grams twice daily — convenient as glycine powder dissolved in water; sweet-tasting and pleasant
- Selenomethionine 100-200 mcg/day — or 2-3 Brazil nuts daily as a food source (USDA FoodData Central lists 1,920 mcg of selenium per 100 g of dried Brazil nuts, but samples ranged from 136 to 2,740 mcg per 100 g)
- A high-quality B-complex daily — providing methylated B12, methylfolate, pyridoxal 5-phosphate (P5P, active B6), and riboflavin
- Milk thistle 420 mg/day — standardized silymarin extract, especially during periods of higher hepatic stress (alcohol exposure, medication, environmental exposure)
- Magnesium glycinate 400 mg at bedtime — supplies both the magnesium cofactor and additional glycine; promotes sleep, which itself supports glutathione recycling
- Whey protein concentrate (undenatured) 20-30 g/day — rich source of cysteine in the alpha-lactalbumin and bovine serum albumin fractions, plus a major source of glutamate. Whey is unusually effective at raising tissue glutathione in comparison to other protein sources.
- Cruciferous vegetables 1+ cups daily — sulforaphane induces Nrf2 and glutathione S-transferase expression, increasing the effective deployment of glutathione for conjugation. See Cruciferous Vegetables page.
- Filtered coffee 2-3 cups/day — included for liver support, as discussed in the Coffee deep-dive. The coffee compounds credited with Phase II enzyme induction, cafestol and kahweol, are retained by a paper filter, so filtered coffee contains little of them (Urgert and Katan 1997); in a 6-month trial, unfiltered cafetière coffee, which is rich in them, raised the liver enzyme alanine aminotransferase by up to 80% above baseline relative to filtered coffee (Urgert 1996).
- Reassessment at 8-12 weeks — practitioners describe judging the regimen by clinical improvement (energy, sleep, skin, digestion) and lab markers (alanine aminotransferase (ALT), gamma-glutamyl transferase, fasting glucose). Some clinicians measure red-blood-cell glutathione directly via specialty labs.
Cost of the full regimen: approximately $40-60 per month for the supplements. The whey protein, cruciferous vegetables, and coffee are food costs that overlap with general nutrition.
Cautions and Drug Interactions
- N-acetylcysteine and nitroglycerin — N-acetylcysteine potentiates nitroglycerin's vasodilatory effect and can produce severe hypotension and headache.
- N-acetylcysteine and asthma — rare paradoxical bronchospasm with nebulized N-acetylcysteine. Oral form generally well tolerated even in asthmatics.
- N-acetylcysteine and bleeding — N-acetylcysteine has mild antiplatelet effects at high doses; theoretical interaction with anticoagulants. Generally well tolerated even with warfarin or direct oral anticoagulants (DOACs) at the standard dose of 600 mg twice daily.
- Glycine and clozapine — high-dose glycine (20-30 g/day for schizophrenia research) reduces clozapine efficacy. Routine 3-5 g/day glycine for reduced glutathione support is unlikely to cause clinically significant interaction.
- Selenium upper limit — tolerable upper intake limit is 400 mcg/day. Chronic intake above 800-1000 mcg/day produces selenium toxicity (hair loss, nail brittleness, garlic breath, neuropathy). A selenium supplement and daily Brazil nuts add together toward that total intake.
- Liposomal reduced glutathione and shellfish allergy — some liposomal preparations use sunflower-derived phosphatidylcholine; others use soy or marine sources, so the source varies between products, which matters for people with severe soy or seafood allergies.
- Pregnancy — N-acetylcysteine has been used in pregnancy for acetaminophen overdose with apparent safety. Routine high-dose glutathione precursor supplementation in pregnancy lacks rigorous safety data. The FDA label for intravenous acetylcysteine states that published case reports and case series in pregnant women “are not sufficient to inform any drug associated risk”, that reproduction studies in rats and rabbits did not show adverse effects on the fetus, and that delaying treatment of an acetaminophen overdose may increase the risk of illness and death for mother and fetus.
- Acetaminophen overdose requires emergency care, not supplements — the intravenous N-acetylcysteine protocol gives its full mortality benefit when started within 8-10 hours of overdose ingestion. Hospitals treat suspected overdose as an emergency; it is not a home-supplement problem.
Key Research Papers
- Kumar P et al. (2021). Glycine and N-acetylcysteine (GlyNAC) supplementation in older adults improves glutathione deficiency, oxidative stress, mitochondrial dysfunction, inflammation, insulin resistance, endothelial dysfunction, genotoxicity, muscle strength, and cognition: Results of a pilot clinical trial. Clin Transl Med. — PubMed PMID: 33783984
- Kumar P et al. (2023). Supplementing Glycine and N-Acetylcysteine (GlyNAC) in Older Adults Improves Glutathione Deficiency, Oxidative Stress, Mitochondrial Dysfunction, Inflammation, Physical Function, and Aging Hallmarks: A Randomized Clinical Trial. J Gerontol A Biol Sci Med Sci. — PubMed PMID: 35975308
- Prescott LF et al. (1979). Intravenous N-acetylcystine: the treatment of choice for paracetamol poisoning. Br Med J. (classic protocol study) — PubMed PMID: 519312
- Richie JP Jr et al. (2015). Randomized controlled trial of oral glutathione supplementation on body stores of glutathione. Eur J Nutr. — PubMed PMID: 24791752
- Sinha R et al. (2018). Oral supplementation with liposomal glutathione elevates body stores of glutathione and markers of immune function. Eur J Clin Nutr. — PubMed PMID: 28853742
- Lu SC (2013). Glutathione synthesis. Biochim Biophys Acta. — PubMed PMID: 22995213
- Sekhar RV et al. (2011). Deficient synthesis of glutathione underlies oxidative stress in aging and can be corrected by dietary cysteine and glycine supplementation. Am J Clin Nutr. — PubMed PMID: 21795440
- Saller R, Meier R, Brignoli R (2001). The use of silymarin in the treatment of liver diseases. Drugs. — PubMed PMID: 11735632
- Brigelius-Flohé R (2006). Glutathione peroxidases and redox-regulated transcription factors. Biol Chem. (selenium-GPx mechanism) — PubMed PMID: 17081103
- Mischley LK et al. (2017). Phase IIb study of intranasal glutathione in Parkinson's disease. J Parkinsons Dis. — PubMed PMID: 28436395
- Atkuri KR et al. (2007). N-acetylcysteine — a safe antidote for cysteine/glutathione deficiency. Curr Opin Pharmacol. — PubMed PMID: 17602868
- Bunchorntavakul C, Reddy KR (2018). Acetaminophen (APAP or N-acetyl-p-aminophenol) and acute liver failure. Clin Liver Dis. — PubMed PMID: 29605069
- Dean O, Giorlando F, Berk M (2011). N-acetylcysteine in psychiatry: current therapeutic evidence and potential mechanisms of action. J Psychiatry Neurosci. — PubMed PMID: 21118657
- Nakatsu L et al. (2025). Comparison of two-bag and three-bag acetylcysteine regimens in the treatment of paracetamol poisoning: a systematic review and meta-analysis. Clin Toxicol (Phila). — PubMed PMID: 40013897
- Urgert R, Katan MB (1997). The cholesterol-raising factor from coffee beans. Annu Rev Nutr. — PubMed PMID: 9240930
- Urgert R et al. (1996). Comparison of effect of cafetière and filtered coffee on serum concentrations of liver aminotransferases and lipids: six month randomised controlled trial. BMJ. — PubMed PMID: 8956701
- U.S. National Library of Medicine, DailyMed. Acetylcysteine injection, for intravenous use: prescribing information (FDA label, revised 2025). — DailyMed label