⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a 72-hour fast regenerates stem cells and resets the immune system in healthy people, and that deep ketosis builds new mitochondria and brain-growth factor. This page keeps it as a report of what people, websites or other media say.
Extended Fasts 24 to 72 Hours — Deep Autophagy & Stem-Cell Renewal
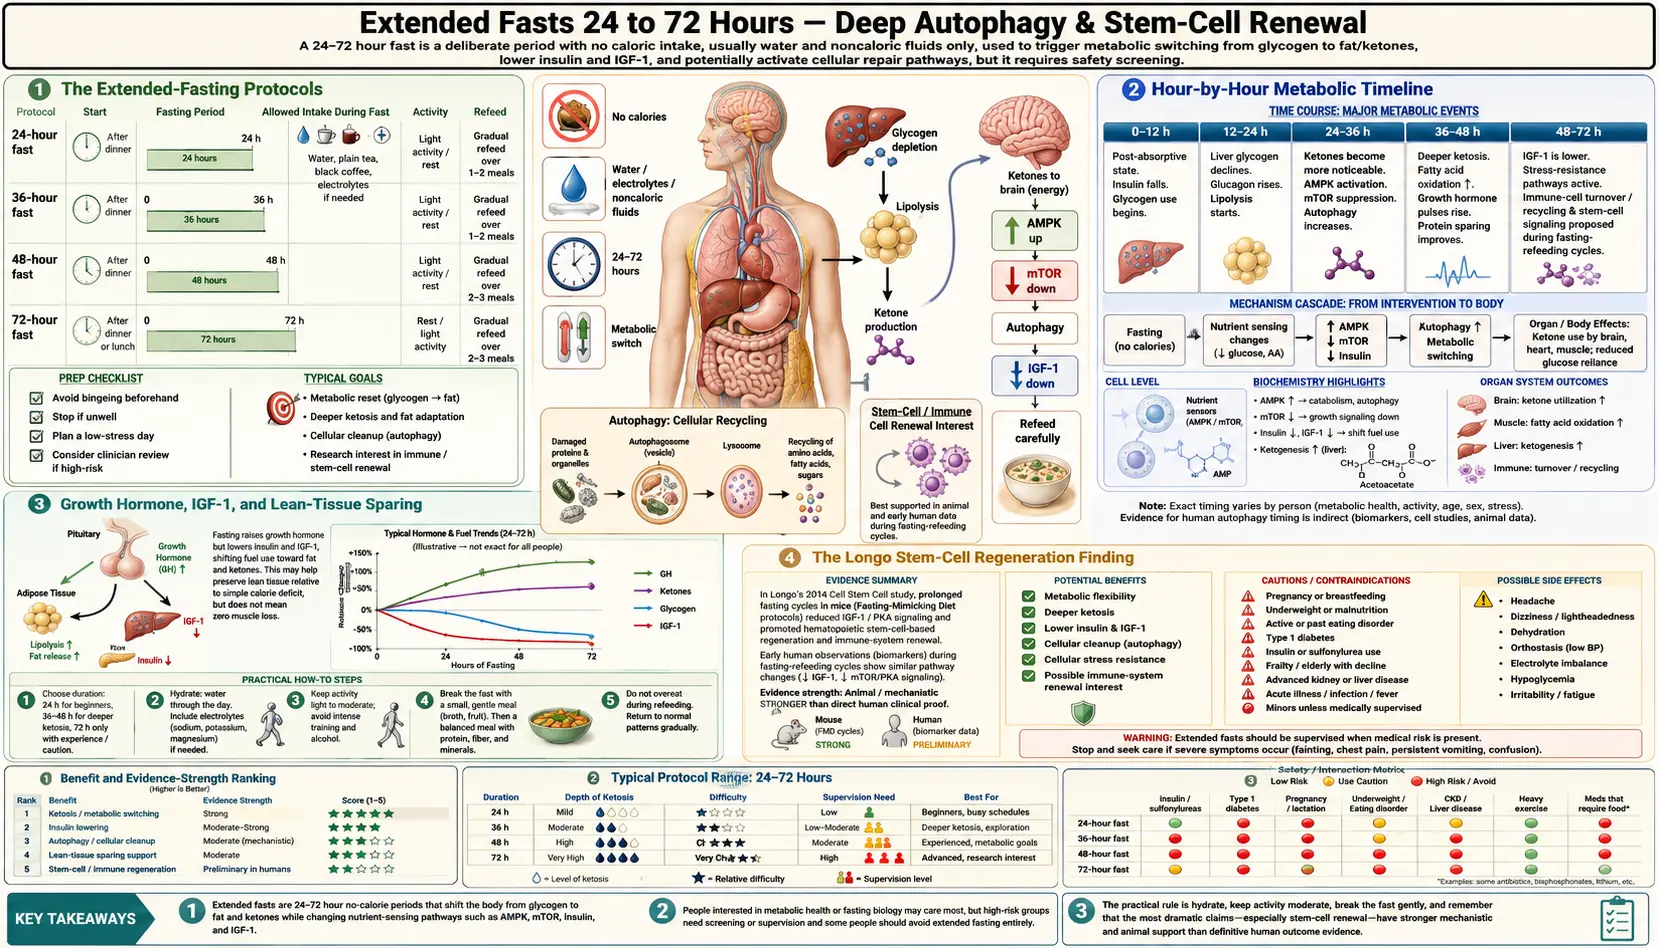
When the daily 16:8 protocol is the entry-level dose of fasting, extended fasts of 24, 36, 48, or 72 hours are where the dramatic metabolic, immune, and regenerative effects become measurable. Hepatic glycogen is exhausted by hour 18-24 in most adults, after which beta-hydroxybutyrate (BHB) climbs steadily — commonly reported as 1-2 mmol/L by 24 hours, 2-4 mmol/L by 48 hours, and 4-6 mmol/L by 72 hours. Growth hormone production was 5-fold higher on the second day of a fast in nine normal men (Hartman et al.), an evolved mechanism to spare lean tissue while mobilizing fat. Valter Longo's 2014 Cell Stem Cell paper reported that repeated 48-hour fasting cycles in mice triggered apparent regeneration of the hematopoietic stem cell compartment — the bone-marrow precursors that produce all blood and immune cells — alongside preliminary lymphocyte data from chemotherapy patients who fasted up to 72 hours. This page maps the dose-response curve from a single 24-hour skip to the 72-hour fast that practitioners commonly give as the upper limit of self-directed at-home practice.
Interactive Visualization Fat Burning & Ketosis — what actually happens Follow a fatty acid out of a fat cell to the mitochondrial gate and find it padlocked by insulin. Drop the carbs, open CPT1, and watch the liver start making ketones. Launch →
Table of Contents
- The Extended-Fasting Protocols
- Hour-by-Hour Metabolic Timeline
- Growth Hormone, Insulin-Like Growth Factor 1, and Lean-Tissue Sparing
- The Longo Stem-Cell Regeneration Finding
- The Fasting-Mimicking Diet (FMD)
- Deep Ketosis and the Beta-Hydroxybutyrate Signaling Cascade
- Cancer-Adjuvant Applications (Longo Differential Stress Resistance)
- Electrolyte and Hydration Protocol
- Cautions Specific to Extended Fasts
- Key Research Papers
- Connections
- Featured Videos
The Extended-Fasting Protocols
- 24-hour fast (Eat-Stop-Eat) — popularized by Brad Pilon. Eat normally on day 1, fast from dinner-to-dinner (e.g. 7 PM Monday to 7 PM Tuesday), then resume eating. Practiced 1-2 times per week. The lowest-friction entry point to extended fasting.
- 36-hour fast (alternate-day fasting, studied by Krista Varady) — alternate-day fasting in its strict form: eat normally on day 1, complete fast on day 2, eat normally on day 3, fast on day 4. The modified version permits about 500 calories on fasting days; a 2017 trial used 25% of energy needs on fast days, alternating with feast days (Trepanowski et al.). The 5:2 diet popularized by Michael Mosley is a different schedule: restricted intake on 2 days a week, tested in a 2011 trial at about 2,710 kJ a day on those days (Harvie et al.).
- 48-hour fast — the practical sweet spot for many practitioners: long enough to reach a reported 2-3 mmol/L beta-hydroxybutyrate, drive significant autophagy, and produce the 5-fold growth hormone surge measured on the second day of a fast; practitioners describe it as short enough to do at home, while the measured safety data on this page come from clinic and research settings.
- 72-hour fast — the upper bound of unsupervised at-home extended fasting as practitioners commonly describe it. Longo's 2014 stem-cell paper used 48-hour cycles in mice and a 24-72 hour fast in its small Phase I group of chemotherapy patients. Beyond 72 hours, the risk-benefit balance is commonly described as requiring supervision (a specialized fasting clinic, or a physician familiar with prolonged fasting).
- 5-day prolonged fast or fasting-mimicking diet (FMD) — the standard duration used in Longo's clinical trials. The full water-only 5-day fast is generally inferior to the calorie-restricted FMD (described below) because the FMD captures most of the metabolic benefit with much better tolerability and safety.
Hour-by-Hour Metabolic Timeline
The beta-hydroxybutyrate levels below are typical figures reported in fasting writing; they are not taken from a study cited on this page, and people vary.
- Hours 0-4 (postprandial) — circulating glucose and amino acids from the last meal are the dominant fuels. Insulin is elevated. Mechanistic target of rapamycin (mTOR) is active. Anabolic state.
- Hours 4-8 (early fast) — postprandial insulin declines. Hepatic glycogenolysis begins to supply blood glucose. Mechanistic target of rapamycin begins to descend. AMP-activated protein kinase (AMPK) begins to rise.
- Hours 8-12 — liver glycogen keeps falling and gluconeogenesis from lactate, glycerol, and glucogenic amino acids supplies a growing share of glucose. The shift is gradual, with no single hour-mark: in a 68-hour fast in humans, gluconeogenesis was 64% of glucose production over the first 22 hours, 82% over the next 14 hours and 96% over the next 18 hours (Rothman et al.). Fat oxidation accelerates.
- Hours 12-18 (the metabolic switch) — ketone bodies begin to appear in measurable concentration (0.2-0.5 mmol/L beta-hydroxybutyrate). Daily 16:8 practitioners typically reside in this zone.
- Hours 18-24 (entering moderate ketosis) — beta-hydroxybutyrate climbs to 1-2 mmol/L in a metabolically flexible person, slower in someone insulin-resistant. Hunger peaks then plateaus as ghrelin oscillates and beta-hydroxybutyrate suppresses appetite. Many practitioners report the hunger of hour 22-24 is the worst of any extended fast.
- Hours 24-36 (deepening ketosis, GH surge) — beta-hydroxybutyrate approaches 2-3 mmol/L. Growth hormone pulses amplify dramatically (Hartman finding: ~5-fold increase measured over the second day of a fast). Lipolysis is maximal. Autophagy markers (the autophagy protein LC3-II, autophagosome formation) increase substantially in animal models.
- Hours 36-48 — beta-hydroxybutyrate 3-4 mmol/L. Mental clarity and energy often improve as the brain adapts to ketone fuel. Ghrelin hunger has typically peaked and declined. The fasting practitioner often feels paradoxically better at hour 40 than at hour 24.
- Hours 48-72 — beta-hydroxybutyrate 4-6 mmol/L. Maximal autophagy in tissue studies. Protein kinase A pathway downregulation and insulin-like growth factor 1 (IGF-1) decline are described in prolonged fasting, although Hartman found IGF-1 unchanged after 56 hours in nine men. Longo's 2014 mouse work used 48-hour cycles; its 72-hour result was normal lymphocyte counts in a small Phase I chemotherapy group.
- Beyond 72 hours — diminishing returns on most metabolic markers, increasing risk of electrolyte derangement and refeeding-syndrome potential. The large safety record for fasts this long comes from clinic settings (see Cautions).
Day 3 in human blood. A 2024 study measured about 3,000 blood proteins daily in 12 volunteers on a 7-day water-only fast (average loss 5.7 kg). Body-wide protein changes appeared only after 3 days of no calories. The authors estimated both possibly helpful and possibly harmful effects from those protein changes (Pietzner et al.).
Autophagy in people is much less certain than in animals. A 2026 review reports that human studies mostly measure proxies in blood, and that where the turnover itself (flux) was measured, “findings are often negative or inconclusive” (Singh and Sargeant). A small 2026 randomized pilot of 30 healthy people on a fasting-mimicking diet found higher flux at the end of the 6-day diet, but not at all time points; it was sponsored by the diet's maker (Espinoza et al.).
Growth Hormone, Insulin-Like Growth Factor 1, and Lean-Tissue Sparing
The intuitive concern about extended fasting is muscle loss. The empirical reality is more interesting: fasting produces a coordinated hormonal response that preserves lean tissue while preferentially mobilizing fat.
Hartman et al. showed in nine normal men that 24-hour growth hormone (GH) production was approximately 5-fold higher on the second day of a fast than on a fed day. GH stimulates lipolysis (release of free fatty acids from adipose tissue) and antagonizes insulin's effects on glucose disposal. The metabolic logic is straightforward: fasting elevates GH to mobilize fat for fuel and to suppress protein breakdown that would otherwise be needed to maintain blood glucose via gluconeogenesis.
Simultaneously, insulin-like growth factor 1 (IGF-1) is described as declining during prolonged fasting — the opposite direction from GH — although in Hartman's own study it was unchanged after 56 hours. This apparent paradox reflects that fasted-state GH is acting primarily through its lipolytic and counter-regulatory effects, not its growth-promoting insulin-like growth factor 1-mediated effects. The decline in insulin-like growth factor 1 is one of the proposed mechanisms behind fasting's longevity signal — lower lifetime insulin-like growth factor 1 exposure is associated with reduced cancer incidence and extended lifespan in multiple animal models and human cohort observations.
The combination — high GH, low insulin-like growth factor 1, high lipolysis, suppressed insulin — produces a fuel-partition strategy that preserves muscle protein during reasonable-duration fasts. Cahill's classic 1970 New England Journal of Medicine work on prolonged starvation demonstrated that nitrogen excretion (a marker of protein breakdown) actually declines after the first 1-3 days of fasting as the body shifts increasingly to ketone fuel and reduces its glucose demand. The naive expectation that "you'll lose muscle if you don't eat protein every 4 hours" is not what these metabolic data show, although early protein loss is real.
Later studies put numbers on this. In a 10-day fast at 200-250 calories a day in 16 men with up to 3 hours of daily low-intensity activity, lean soft tissue fell by 3.53 kg, of which 42% was metabolically active lean tissue; the muscle-breakdown marker 3-methyl-histidine rose until day 5 and then fell, and strength was maintained or increased (Laurens et al.). In a 12-day fast at 250 calories a day in 32 people, half of them over 50, maximal strength and muscle energy use were preserved, and the 5.4% fall in calf muscle volume closely matched the expected loss of glycogen and water (Naëgel et al.; part-funded by a fasting-clinic company). Both were research studies of low-calorie fasts, so they do not describe water-only fasts at home.
The Longo Stem-Cell Regeneration Finding
Valter Longo and colleagues at USC Davis published a remarkable 2014 Cell Stem Cell paper (Cheng CW et al.) showing that repeated cycles of prolonged fasting (the paper describes prolonged fasting as 48-120 hours; its mice fasted 48 hours per cycle) produced apparent regeneration of the hematopoietic stem cell (HSC) compartment in the bone marrow of mice. In people the paper offers “preliminary data on the protection of lymphocytes from chemotoxicity in fasting patients”.
The mechanism: fasting reduces circulating insulin-like growth factor 1 and protein kinase A signaling. Lower protein kinase A in hematopoietic stem cells de-represses the transcription factor FOXO and reduces the activity of mTORC1. This combination appears to enable HSC self-renewal and produces a wave of new immune cell production during the refeeding phase after a prolonged fast.
Clinically the team analyzed cancer patients from a Phase I feasibility trial of a 24-72 hour fast combined with platinum-based chemotherapy: 72 but not 24 hours of fasting was associated with normal lymphocyte counts, results the authors call preliminary and in need of confirmation — suggesting that the stem-cell regeneration finding may have practical implications for protecting hematopoietic function during cytotoxic therapy. The work has not yet translated into routine clinical recommendations, but it is the basis for the active clinical trials of fasting-mimicking diet as a chemotherapy adjunct.
Some fasting practitioners extrapolate from this to healthy people: that a single annual or quarterly 72-hour fast may produce a similar wave of immune-cell turnover — conceptually analogous to factory-rebooting the immune compartment. That is an extrapolation from the mouse work. Mechanistic claims of "stem cell rejuvenation" require caution because the human data are limited and the long-term clinical outcomes are not yet established. But the mouse data are reproducible across multiple labs, and the biological plausibility is strong.
The Fasting-Mimicking Diet (FMD)
Recognizing that 5-day water-only fasts are difficult, often unsafe outside supervision, and require lengthy adaptation, the Longo lab developed the fasting-mimicking diet (FMD) — a 5-day low-calorie, low-protein, plant-based food regimen designed to produce the metabolic and hormonal signatures of fasting (low insulin-like growth factor 1, low glucose, elevated ketones, suppressed mechanistic target of rapamycin) while still providing some food intake to improve safety and tolerability.
The standard FMD protocol used in Longo's clinical trials:
- Day 1 — ~1100 calories: 11% protein, 46% fat, 43% carbohydrate. Plant-based.
- Days 2-5 — ~725 calories: 9% protein, 44% fat, 47% carbohydrate. Plant-based.
A commercial product packages this as soups, bars, and drinks. The DIY version is similar: vegetable broth, a small portion of nuts and olive oil, leafy greens, herbal teas, no animal protein, very limited carbohydrate.
Wei, Longo et al. (2017) randomized 100 generally healthy adults to three monthly cycles of the 5-day FMD versus control. In the randomized comparison, the FMD group showed reductions in body weight, trunk and total body fat, blood pressure, and insulin-like growth factor 1; fasting glucose, triglycerides, cholesterol and C-reactive protein (CRP) did not differ significantly between groups. A post hoc analysis found that glucose, triglycerides, cholesterol and CRP were more beneficially affected in participants at risk for disease. Of the 100 randomized, 71 completed three cycles. In a voluntary follow-up of 50 participants about 3 months after the last cycle, several of the effects were still present, some of them only in at-risk subgroups, and the authors note that this persistence may be affected by changes in diet or physical activity.
A 2024 secondary analysis of trial blood samples linked 3 monthly fasting-mimicking cycles with lower insulin resistance and liver fat and a 2.5-year drop in a calculated median biological age, independent of weight loss. The analysis was exploratory, and two authors hold an equity interest in the diet's maker (Brandhorst et al.).
The FMD is the practical translation of extended fasting for people who cannot tolerate or safely do a 5-day water-only fast — which is most people.
Deep Ketosis and the Beta-Hydroxybutyrate Signaling Cascade
The 16:8 page introduced beta-hydroxybutyrate as a signaling molecule, not just a fuel. In the deeper ketosis of extended fasting (beta-hydroxybutyrate 3-6 mmol/L), the signaling effects become substantially more pronounced:
- Histone deacetylase (HDAC) class I inhibition — at higher concentrations, beta-hydroxybutyrate more effectively inhibits histone deacetylases, allowing histone acetylation and de-repressed expression of antioxidant genes (FOXO3, MT2, catalase, superoxide dismutase)
- NLRP3 inflammasome suppression — the Youm 2015 mechanism becomes more clinically relevant at the higher beta-hydroxybutyrate levels of extended fasting
- GPR109A receptor activation — beta-hydroxybutyrate activates the GPR109A G-protein-coupled receptor (the same receptor activated by niacin), which produces anti-lipolytic effects in adipose tissue and may contribute to the appetite suppression of deep ketosis
- Brain-derived neurotrophic factor (BDNF) and neuroprotection — the deeper ketosis of extended fasting more strongly upregulates brain-derived neurotrophic factor in the hippocampus, the proposed mechanism for the cognitive clarity and mood elevation many extended-fast practitioners report by hour 36-48
- Mitochondrial biogenesis — ketosis upregulates PGC-1alpha, the master transcriptional coactivator for mitochondrial biogenesis, increasing mitochondrial density in tissues over repeated fasting cycles
The mitochondrial-biogenesis effect is one of the reasons practitioners often report sustained energy improvements over months of intermittent fasting practice — not just during the fast itself but in the fed state between fasts.
Cancer-Adjuvant Applications (Longo Differential Stress Resistance)
One of the more intriguing translational arms of Longo's work concerns fasting as an adjunct to cancer chemotherapy. The hypothesis — "differential stress resistance" (DSR) — is that normal cells, when starved of glucose and growth factors, downshift their metabolism, suppress mechanistic target of rapamycin, and become temporarily resistant to the toxic effects of chemotherapy. Cancer cells, with their characteristic constitutively-active growth signaling (oncogenic Ras, PI3K, mechanistic target of rapamycin), cannot downshift — they remain in growth mode regardless of the fasting signal, and are therefore differentially vulnerable to chemotherapy during the fasted state.
Raffaghello, Longo et al. demonstrated this differential vulnerability in cell-culture and mouse models. Small clinical pilot trials of short-term fasting around chemotherapy have reported fewer patient-reported side effects (nausea, fatigue, weakness) and trends toward improved immune-cell recovery. In one randomized crossover pilot, 34 patients with gynecological cancer fasted from 36 hours before to 24 hours after chemotherapy (60 hours), which appeared to improve quality of life and fatigue (Bauersfeld et al.).
The clinical translation is still preliminary — this is not yet standard-of-care, and these trials were run by oncology teams, with monitoring of the patients. The mechanism is biologically sound, and a randomized phase 2 trial has now reported.
In the DIRECT trial, 131 women with HER2-negative stage II/III breast cancer were randomized to a fasting-mimicking diet or their regular diet for 3 days before and during chemotherapy given before surgery. Toxicity did not differ, although the steroid dexamethasone was left out of the diet group. Tumor shrinkage seen on scans was more common with the diet (odds ratio 3.168, P=0.039), and major tumor-cell loss was more likely in the per-protocol analysis (odds ratio 4.109, P=0.016) (de Groot et al.).
Electrolyte and Hydration Protocol
The single most common reason extended fasts are abandoned prematurely is electrolyte deficiency — specifically sodium, magnesium, and potassium — manifesting as headache, fatigue, muscle cramps, palpitations, or orthostatic hypotension. These symptoms are often misattributed to "low blood sugar" but they are usually electrolyte-driven.
The reason: during the first 2-3 days of fasting, insulin falls substantially. Low insulin signals the kidneys to excrete sodium (the "natriuresis of fasting"). The lost sodium drags water and other electrolytes with it. Without active replacement, a fasting practitioner can lose 1-2 liters of fluid and several grams of sodium per day in urine alone.
Daily amounts commonly listed in fasting practitioners' guides for an extended fast (these figures do not come from a trial cited on this page):
- Water: 2-3 liters, sipped throughout the day. Practitioners link large boluses with dilutional symptoms.
- Sodium: 3-5 grams (1.5-2.5 tsp salt) — pinches of mineral salt dissolved in water across the day, or from broth.
- Potassium: 1-3 grams — "lite salt" (potassium chloride substitute) is the simplest source; vegetable broth provides smaller amounts. The US lisinopril label states that potassium-containing salt substitutes taken with this blood pressure drug may significantly raise blood potassium, that kidney disease and diabetes add to the risk, and that high potassium can cause serious, sometimes fatal, heart rhythm problems.
- Magnesium: 300-500 mg — magnesium glycinate or citrate. Magnesium is the most commonly underdosed electrolyte in fasting practitioners and is the usual cause of leg cramps and poor sleep during extended fasts.
Commercial electrolyte powders marketed for fasting package these minerals. Zero-calorie versions do not break the fast on any reasonable definition.
Cautions Specific to Extended Fasts
- All time-restricted eating (TRE) cautions apply with greater force — pregnancy, lactation, children, type 1 diabetes, eating disorder history, underweight, elderly with sarcopenia. Extended fasting is a more demanding intervention with smaller safety margins.
- Medications change the risk — insulin, sulfonylureas, blood pressure medications (especially diuretics, angiotensin-converting enzyme inhibitors (ACE inhibitors), angiotensin receptor blockers (ARBs)), and sodium-glucose cotransporter-2 (SGLT2) inhibitors all interact dangerously with extended fasting. The US glipizide label states that all sulfonylurea drugs can produce severe low blood sugar, and insulin lowers blood sugar whether or not food comes in. US empagliflozin labels list reduced caloric intake among the triggers of ketoacidosis. Doses of these drugs are set for normal eating, which is why physicians adjust them for a fast.
- Gout — fasting can precipitate gout flares due to elevated uric acid (lactate and beta-hydroxybutyrate share renal transporters with urate, blocking urate excretion). People with established gout are the group most exposed, and some continue allopurinol or febuxostat during the fast.
- Gallstones — rapid weight loss including from extended fasting can precipitate gallstone formation. People with known gallstones (cholelithiasis) are the group this concerns.
- Refeeding syndrome — the most serious complication of extended fasting, particularly after fasts > 5 days or in patients who began at low body weight. See the refeeding strategy page for the specific protocols to prevent it.
- Orthostatic hypotension — common in extended fasts, especially with inadequate sodium. Dizziness comes on when standing up, and severe symptoms are a common reason fasts are ended.
- Beyond 72 hours — the largest safety record comes from a specialized clinic: 1,422 people on 4-21 day fasts of 200-250 calories a day reported adverse effects in under 1% (Wilhelmi de Toledo et al.). That study was observational and clinic-based and does not describe water-only fasts at home.
Key Research Papers
- Cahill GF Jr. (1970). Starvation in man. New England Journal of Medicine. — PubMed PMID: 4915800
- Cheng CW et al. (Longo lab, 2014). Prolonged fasting reduces IGF-1/PKA to promote hematopoietic-stem-cell-based regeneration and reverse immunosuppression. Cell Stem Cell. — PubMed PMID: 24905167 — Erratum: Cell Stem Cell 2016;18(2):291-2.
- Wei M et al. (Longo lab, 2017). Fasting-mimicking diet and markers/risk factors for aging, diabetes, cancer, and cardiovascular disease. Science Translational Medicine. — PubMed PMID: 28202779
- Brandhorst S et al. (Longo lab, 2015). A periodic diet that mimics fasting promotes multi-system regeneration, enhanced cognitive performance, and healthspan. Cell Metabolism. — PubMed PMID: 26094889
- Hartman ML, Veldhuis JD, Johnson ML, Lee MM, Alberti KG, Samojlik E, Thorner MO (1992). Augmented growth hormone (GH) secretory burst frequency and amplitude mediate enhanced GH secretion during a two-day fast in normal men. The Journal of Clinical Endocrinology and Metabolism. 74(4):757-65. — PubMed PMID: 1548337
- Stekovic S et al. (2019). Alternate day fasting improves physiological and molecular markers of aging in healthy, non-obese humans. Cell Metabolism. — PubMed PMID: 31471173
- Trepanowski JF et al. (2017). Effect of alternate-day fasting on weight loss, weight maintenance, and cardioprotection. JAMA Internal Medicine. — PubMed PMID: 28459931
- Wilhelmi de Toledo F et al. (2019). Safety, health improvement and well-being during a 4 to 21-day fasting period in an observational study including 1422 subjects. PLoS ONE. — PubMed PMID: 30601864
- Raffaghello L et al. (Longo lab, 2008). Starvation-dependent differential stress resistance protects normal but not cancer cells against high-dose chemotherapy. PNAS. — PubMed PMID: 18378900
- Bauersfeld SP et al. (2018). The effects of short-term fasting on quality of life and tolerance to chemotherapy in patients with breast and ovarian cancer. BMC Cancer. — PubMed PMID: 29699509
- Catenacci VA et al. (2016). A randomized pilot study comparing zero-calorie alternate-day fasting to daily caloric restriction in adults with obesity. Obesity. — PubMed PMID: 27569118
- Furmli S et al. (2018). Therapeutic use of intermittent fasting for people with type 2 diabetes as an alternative to insulin. BMJ Case Reports. — PubMed PMID: 30301822
- Rothman DL et al. (1991). Quantitation of hepatic glycogenolysis and gluconeogenesis in fasting humans with 13C NMR. Science. — PubMed PMID: 1948033
- Harvie MN et al. (2011). The effects of intermittent or continuous energy restriction on weight loss and metabolic disease risk markers: a randomized trial in young overweight women. International Journal of Obesity. — PubMed PMID: 20921964
- Laurens C et al. (2021). Is muscle and protein loss relevant in long-term fasting in healthy men? A prospective trial on physiological adaptations. Journal of Cachexia, Sarcopenia and Muscle. — PubMed PMID: 34668663
- Naëgel A et al. (2025). Impact of Long-Term Fasting on Skeletal Muscle: Structure, Energy Metabolism and Function Using 31P/1H MRS and MRI. Journal of Cachexia, Sarcopenia and Muscle. — PubMed PMID: 40211897
- Pietzner M et al. (2024). Systemic proteome adaptions to 7-day complete caloric restriction in humans. Nature Metabolism. — PubMed PMID: 38429390
- Singh S, Sargeant TJ (2026). Increasing autophagy with fasting and diet: separating fact from fiction. Biochemical Society Transactions. — PubMed PMID: 42865256
- Espinoza SE et al. (2026). Effect of fasting-mimicking diet on markers of autophagy and metabolic health in human subjects. GeroScience. — PubMed PMID: 41372565
- Brandhorst S et al. (2024). Fasting-mimicking diet causes hepatic and blood markers changes indicating reduced biological age and disease risk. Nature Communications. — PubMed PMID: 38378685
- de Groot S et al. (2020). Fasting mimicking diet as an adjunct to neoadjuvant chemotherapy for breast cancer in the multicentre randomized phase 2 DIRECT trial. Nature Communications. — PubMed PMID: 32576828
PubMed Topic Searches
Connections
- All Remedies
- Fat Burning & Ketosis — interactive animation
- Fasting Benefits Hub
- Fasting Overview
- Time-Restricted Eating 16:8
- Autophagy & Mechanistic Target of Rapamycin
- Refeeding Strategy
- Type 2 Diabetes
- Obesity
- Metabolic Syndrome
- Fatty Liver Disease
- Oncology
- Magnesium (Fasting Electrolyte)
- Potassium (Fasting Electrolyte)
- Sodium (Fasting Electrolyte)
- Bone Broth