⚠ Evidence warning: Clinical trials or other evidence do not support the reports that silicon supplements ease osteoarthritis joint discomfort. This page keeps it as a report of what people, websites or other media say.
Silicon for Connective Tissue
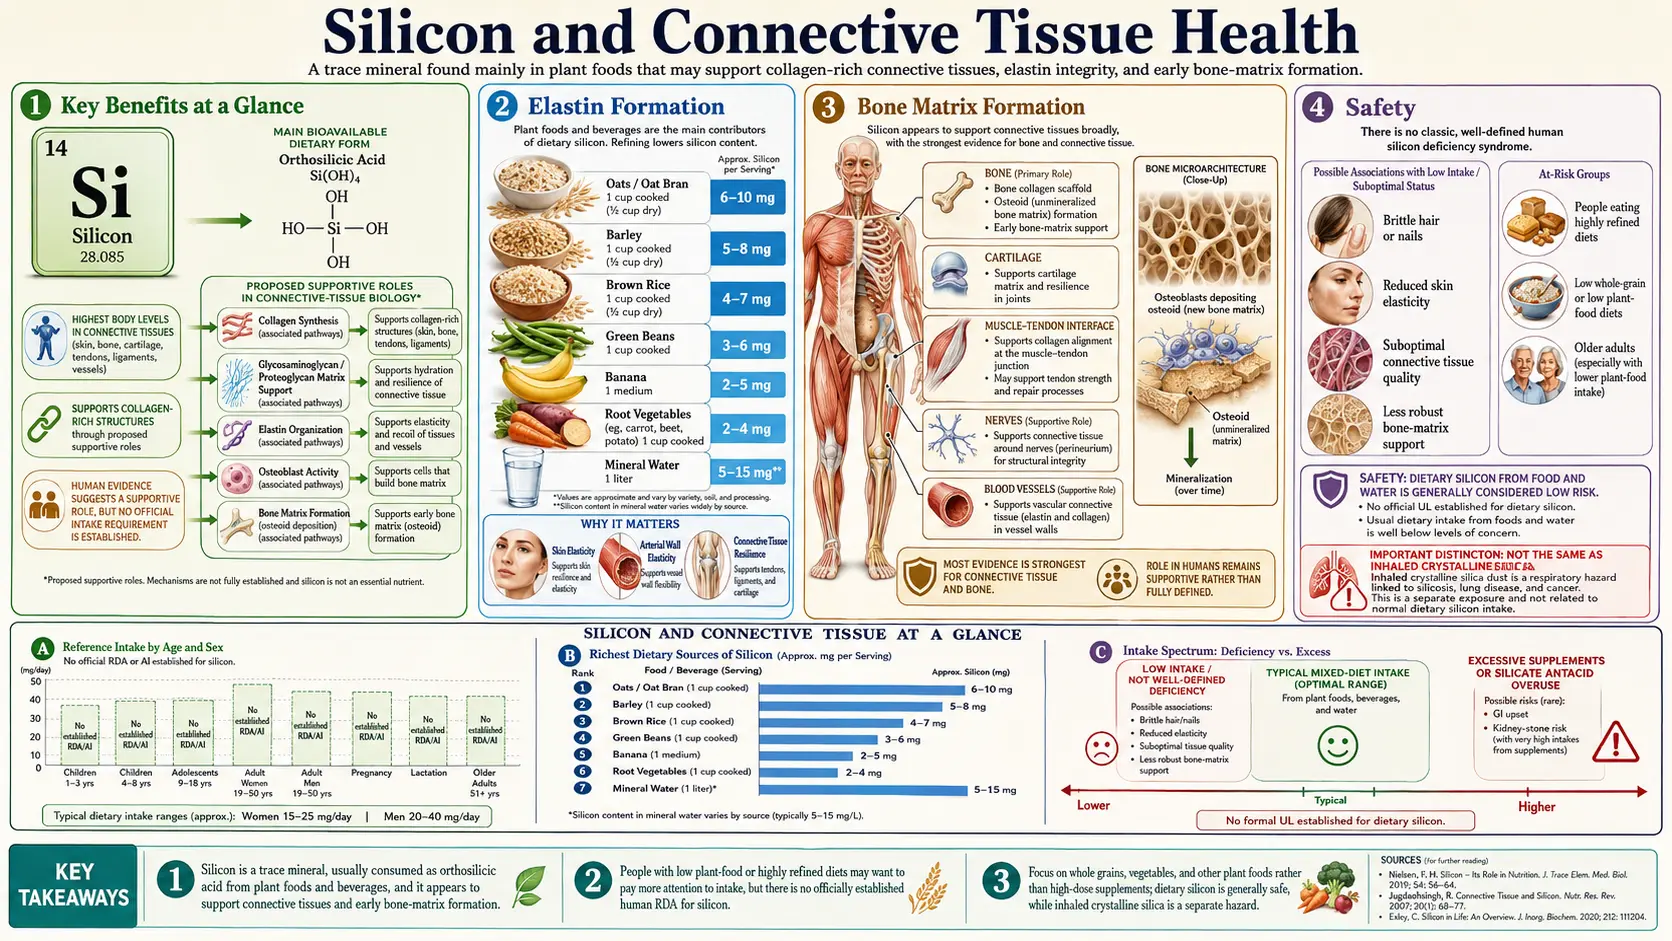
Silicon is a trace element increasingly recognized for its central role in connective tissue biology. Found in highest concentrations in the aorta, trachea, tendons, bone, and skin, silicon is intimately involved in the synthesis and structural integrity of collagen, elastin, and glycosaminoglycans — the three macromolecular families that give connective tissues their tensile strength, elastic recoil, and hydrated resilience. A proposed molecular pivot is a single enzyme: prolyl hydroxylase. Without its established cofactors vitamin C and iron, the proline residues in nascent collagen fail to hydroxylate, the triple helix is thermally unstable, and every downstream connective tissue suffers in proportion. Silicon is proposed as an additional factor at this step: in a lab study of human bone-forming cells, silicon’s boost to collagen production disappeared when prolyl hydroxylase was blocked (Reffitt 2003).
Table of Contents
Key Benefits at a Glance
- Supports collagen biosynthesis – In human bone-forming (osteoblast-like) cells in the lab, orthosilicic acid raised type I collagen production but not collagen gene expression; the effect disappeared when prolyl hydroxylase was blocked.
- Elastin integrity – Concentrated in the aorta and elastic fibers; deficiency reduces arterial elastin content.
- Glycosaminoglycan (GAG) cross-linking – Forms ether linkages between polysaccharide chains and proteins in the extracellular matrix.
- Bone mineral density – Framingham Offspring data showed positive association between dietary silicon and hip bone mineral density (BMD) in men and premenopausal women.
- Skin elasticity – Choline-stabilized orthosilicic acid improved skin roughness and elasticity in a 20-week randomized controlled trial (RCT).
- Hair and nails – Supplementation studies report improvements in hair tensile strength and nail brittleness.
Prolyl Hydroxylase Activation
Prolyl hydroxylase is the enzyme responsible for converting proline residues to hydroxyproline within nascent collagen polypeptide chains. Hydroxyproline is essential for the formation of stable inter-chain hydrogen bonds that hold the collagen triple helix together. Without adequate proline hydroxylation, the procollagen chains cannot fold into a thermally stable triple helix at body temperature, the molecule is degraded intracellularly, and no functional collagen reaches the extracellular space. This is the molecular failure point in scurvy — vitamin C deficiency stops hydroxylation cold, and within weeks the existing collagen fails (gum bleeding, joint pain, perifollicular hemorrhage). A lab study suggests that silicon’s effect on collagen runs through the same enzymatic step (Reffitt 2003).
- Ascorbate (vitamin C) and iron are the established cofactors for prolyl hydroxylase, but silicon appears to act as an additional activating factor, possibly by stabilizing the enzyme-substrate complex or influencing the local redox environment at the catalytic site.
- Hydroxylation of proline at the 4-position is thermodynamically critical: collagen molecules lacking adequate hydroxyproline are thermally unstable at body temperature and cannot form functional fibrils. If silicon supports this hydroxylation step in the body as it does in lab cells, that would tie it directly to connective tissue integrity.
- Lysyl hydroxylase, which hydroxylates lysine residues needed for collagen cross-linking, may also be influenced by silicon availability, though this relationship is less well characterized than the effect on prolyl hydroxylase.
- The silicon-vitamin C-iron triad means that any deficiency of one tends to amplify the effect of marginal status in the others.
Collagen Synthesis
- Silicon is concentrated at active calcification and growth sites in bone and cartilage, where collagen synthesis rates are highest. Studies using electron microprobe analysis have detected silicon bound to the organic matrix of developing bone at sites of active osteoid formation.
- Fibroblast stimulation by silicon has been demonstrated in cell culture studies, where orthosilicic acid (the bioavailable form of silicon) raised type I collagen production 1.45- to 1.8-fold at 10–20 µM in human bone-forming (osteoblast-like) cells, without any change in collagen gene expression (Reffitt 2003). That study did not test skin fibroblasts.
- Cross-linking of collagen fibrils may be facilitated by silicon, which can form bridges between polysaccharide chains and proteins in the extracellular matrix. These cross-links contribute to the tensile strength and mechanical stability of connective tissues.
- Wound healing is accelerated in the presence of adequate silicon, consistent with its role in stimulating collagen deposition. Animal studies have shown improved tensile strength at wound sites in silicon-supplemented groups compared to controls.
- Type I, II, and III collagen — the three structural collagens that compose roughly 90% of all human collagen — are all dependent on the same prolyl-hydroxylation step, so silicon's effect propagates from bone (type I) to cartilage (type II) to vessel walls and reticulin networks (type III) simultaneously.
Elastin Formation
- Elastin is the protein responsible for the elastic recoil of tissues such as arterial walls, lungs, skin, and ligaments. Silicon has been found at high concentrations in elastin-rich tissues, particularly the aorta, where it is bound to the elastic fiber network.
- Tropoelastin, the soluble precursor of elastin, undergoes extensive cross-linking by lysyl oxidase to form mature insoluble elastin fibers. Silicon may facilitate this process by contributing to the structural organization of the microfibrillar scaffold (fibrillin-1) upon which elastin is deposited.
- Arterial elastin content decreases with age, and this decline correlates with decreasing tissue silicon levels. Animal studies have shown that silicon deficiency leads to reduced elastin content in the aorta and other major arteries, resulting in decreased vascular compliance and increased pulse-wave velocity.
- Desmosine and isodesmosine, the unique cross-linking amino acids of mature elastin, are formed through lysyl oxidase-mediated reactions. Silicon's presence in the extracellular matrix environment where these cross-links form suggests a facilitative role in elastin maturation.
- The elastin half-life is unusually long — roughly 70 years for aortic elastin — which means the elastin you make during childhood and adolescence largely has to last a lifetime. This has led to the suggestion that silicon status during the growth years could matter disproportionately for arterial compliance late in life; that is an extrapolation, not a measured finding.
Glycosaminoglycan Production
- Glycosaminoglycans (GAGs) including hyaluronic acid, chondroitin sulfate, dermatan sulfate, and keratan sulfate are long unbranched polysaccharide chains that attract and retain water in the extracellular matrix, providing tissue hydration, cushioning, and lubrication. Silicon is structurally associated with GAGs in connective tissues.
- Silicon forms ether linkages with carbohydrate hydroxyl groups in GAG chains, serving as a structural cross-linking agent between individual polysaccharide molecules and between GAGs and the protein components of proteoglycans (Schwarz 1973).
- Hyaluronic acid synthesis appears to be stimulated by silicon in in vitro studies. Given hyaluronic acid's role in maintaining skin hydration, joint lubrication, and tissue repair, this effect has significant implications for connective tissue health across multiple organ systems.
- Proteoglycan architecture in cartilage depends on the proper assembly and spacing of GAG chains along core proteins. Silicon's cross-linking function contributes to the highly organized, brush-like structure of aggrecan that gives cartilage its compressive resistance.
- Synovial fluid viscosity, the viscoelastic property that lubricates joint surfaces, depends on high-molecular-weight hyaluronic acid produced by synoviocytes. Silicon is proposed to support this synthesis, and some people who take silicon supplements report easier osteoarthritic joint comfort; this is a reported effect and a proposed mechanism.
Skin Aging Prevention
- Skin silicon content declines with age, paralleling the loss of collagen, elastin, and GAGs that characterizes chronological skin aging. The dermis, which provides structural support to the skin, is particularly affected by diminishing silicon levels.
- Wrinkle formation results from the degradation of dermal collagen and elastin networks. By supporting the synthesis of both these proteins, silicon may help maintain the structural integrity of the dermis and delay the appearance of fine lines and deep wrinkles.
- Skin elasticity and hydration have been improved in clinical supplementation studies. A randomized, double-blind trial by Barel and colleagues (2005) using choline-stabilized orthosilicic acid showed significant improvements in skin roughness and elasticity after 20 weeks of supplementation in women with photodamaged facial skin.
- Hair and nail strength are also influenced by silicon status. Keratin, the structural protein of hair and nails, benefits from silicon's role in cross-linking and structural organization (covered in depth on the Hair and Nails page).
- Photoaging protection may be an additional benefit, as silicon-supported antioxidant defense mechanisms in the skin help mitigate ultraviolet-induced damage to collagen and elastin fibers in the dermis.
Bone Matrix Formation
- Silicon is found at the mineralization front of active bone formation, where osteoid (unmineralized bone matrix) transitions to mature mineralized bone. Its concentration is highest in young, actively forming bone and decreases as mineralization progresses (Carlisle 1970).
- Osteoblast differentiation is stimulated by orthosilicic acid, which promotes the expression of osteogenic markers including alkaline phosphatase, osteocalcin, and bone morphogenetic protein-2 (BMP-2) in bone marrow stromal cells.
- The Framingham Offspring cohort study (Jugdaohsingh, Tucker et al. 2004) found a positive association between dietary silicon intake and bone mineral density (BMD) at the hip in men and premenopausal women, providing epidemiological support for silicon's role in human bone health — covered in depth on the Bone Density page.
- The Aberdeen study (Macdonald 2012) of 3,198 Scottish women aged 50–62 found hip (femoral neck) bone density 2% lower in the quarter of women eating the least silicon (about 16 mg a day) than in the quarter eating the most (about 31.5 mg a day). The link held only in women with oestrogen — late premenopausal women and women on hormone replacement therapy (HRT) — matching the Framingham finding, where it was absent after menopause.
- Hydroxyapatite nucleation, the initial step in bone mineralization, may be facilitated by silicon-containing compounds in the organic matrix. Silicon could provide nucleation sites that attract calcium and phosphate ions to initiate crystal formation.
- Silicon-substituted calcium phosphate bioceramics are used in orthopedic and dental implant surgery, demonstrating enhanced osteoconductivity and bone regeneration compared to conventional hydroxyapatite, further supporting silicon's role in bone biology.
Clinical Evidence
- Dietary silicon is found in whole grains, cereals, vegetables, beer, and mineral water. Bioavailability varies depending on the food source. In a study using urine silicon as a stand-in for absorption, silicon was “readily available from foods”: on average 41% of the silicon eaten in solid foods was passed in the urine, and foods richer in silicon gave more urinary silicon (Jugdaohsingh 2002).
- No official recommended daily intake has been established for silicon, but estimates of adequate intake range from 25 to 50 mg per day based on dietary surveys and balance studies. Average Western diets typically provide 20 to 50 mg per day, with cereal grains and beer as the dominant contributors. In the Framingham cohorts, men ate on average 30–33 mg a day and women 24–25 mg, intake fell with age, and the top sources were beer and bananas in men and bananas and string beans in women (Jugdaohsingh 2002).
- Supplementation with choline-stabilized orthosilicic acid (ch-OSA) has been the most commonly studied form in clinical trials. One 12-month trial in osteopenic women (Spector 2008; 136 of 184 women completed it, all also taking calcium and vitamin D3) found that only the collagen-formation marker (serum procollagen type I N-terminal propeptide, PINP) rose significantly, at 6 and 12 mg silicon a day and without a clear dose response; lumbar spine bone density did not change significantly.
- Skin, nail, and hair benefits in randomized controlled trials — two ch-OSA trials at 10 mg elemental silicon per day have reported statistically significant effects. In 50 women with sun-damaged skin over 20 weeks (Barel 2005), skin roughness and skin mechanical properties improved compared with placebo, and hair and nail brittleness scores fell compared with the start. In 48 women with fine hair over 9 months (Wickett 2007), hair lost less elasticity and break strength than on placebo and became thicker. Neither trial measured dermal collagen.
- Safety profile of dietary and supplemental silicon is generally favorable. Silicon is efficiently excreted by the kidneys, and toxicity from oral intake has not been reported in clinical studies. However, chronic inhalation of crystalline silica dust causes silicosis, a distinct occupational lung disease unrelated to dietary silicon metabolism.
- Future research directions include determining the precise molecular mechanisms of silicon's biological activity, establishing formal dietary reference intakes, and conducting larger randomized controlled trials to evaluate silicon supplementation for osteoporosis and connective tissue disorders.
Dosing and Dietary Sources
- Adequate Intake estimate – 25–50 mg/day (no formal Dietary Reference Intake (DRI) established in the US).
- Whole grains – Oats, brown rice, barley, whole wheat.
- Vegetables – Green beans, leafy greens, bell peppers.
- Beverages – Beer (from hops and barley, highly bioavailable), mineral water, coffee.
- Herbs – Horsetail (Equisetum arvense) is a traditional silicon-rich botanical.
- Supplement forms – Choline-stabilized orthosilicic acid (ch-OSA) has the best clinical evidence; colloidal silicic acid and monomethylsilanetriol are also used.
- Typical supplement dose – 5–10 mg/day elemental silicon as ch-OSA.
Safety
- Oral silicon is generally safe; excess is excreted renally with no reported toxicity in clinical trials.
- Silicosis is an occupational disease of inhaled crystalline silica dust — unrelated to dietary silicon.
- Kidney impairment – Silicon is cleared by the kidneys, so clearance is reduced in advanced kidney disease and silicon from supplements can build up.
- Horsetail contains thiaminase; prolonged high-dose use may deplete thiamin (vitamin B1).
- Drug interactions – Data on interactions between silicon supplements and medicines are limited.
This content is provided for informational purposes only and does not constitute medical advice.
Key Research Papers
- Jugdaohsingh R, Anderson SH, Tucker KL et al. (2002). Dietary silicon intake and absorption. American Journal of Clinical Nutrition. — PubMed PMID: 11976163
- Jugdaohsingh R, Tucker KL, Qiao N et al. (2004). Dietary silicon intake is positively associated with bone mineral density in men and premenopausal women of the Framingham Offspring cohort. Journal of Bone and Mineral Research. — PubMed PMID: 14969400
- Reffitt DM, Ogston N, Jugdaohsingh R et al. (2003). Orthosilicic acid stimulates collagen type 1 synthesis and osteoblastic differentiation in human osteoblast-like cells in vitro. Bone. — PubMed PMID: 12633784
- Barel A, Calomme M, Timchenko A et al. (2005). Effect of oral intake of choline-stabilized orthosilicic acid on skin, nails and hair in women with photodamaged skin. Archives of Dermatological Research. 297(4):147-53 (erratum 2006;297(10):481, dosage error in article text). — PubMed PMID: 16205932
- Wickett RR, Kossmann E, Barel A, Demeester N, Clarys P, Vanden Berghe D, Calomme M (2007). Effect of oral intake of choline-stabilized orthosilicic acid on hair tensile strength and morphology in women with fine hair. Archives of Dermatological Research. 299(10):499-505. — PubMed PMID: 17960402
- Spector TD, Calomme MR, Anderson SH et al. (2008). Choline-stabilized orthosilicic acid supplementation as an adjunct to calcium/vitamin D3 stimulates markers of bone formation in osteopenic females. BMC Musculoskeletal Disorders. — PubMed PMID: 18547426
- Macdonald HM, Hardcastle AC, Jugdaohsingh R, Fraser WD, Reid DM, Powell JJ (2012). Dietary silicon interacts with oestrogen to influence bone health. Bone. — PubMed PMID: 22173054
- Martin KR (2007). The chemistry of silica and its potential health benefits. Journal of Nutrition, Health & Aging. — PubMed PMID: 17435951
- Carlisle EM (1970). Silicon: a possible factor in bone calcification. Science. — PubMed PMID: 5410261
- Carlisle EM (1981). Silicon: a requirement in bone formation independent of vitamin D1. Calcified Tissue International. — PubMed PMID: 6257332
- Schwarz K (1973). A bound form of silicon in glycosaminoglycans and polyuronides. Proceedings of the National Academy of Sciences. — PubMed PMID: 4268099
- Eisinger J, Clairet D (1993). Effects of silicon, fluoride, etidronate and magnesium on bone mineral density: a retrospective study. Magnesium Research. — PubMed PMID: 8292498
- Price CT, Koval KJ, Langford JR (2013). Silicon: a review of its potential role in the prevention and treatment of postmenopausal osteoporosis. International Journal of Endocrinology. — PubMed PMID: 23762049