⚠ Evidence warning: Clinical trials or other evidence do not support the claims that silicon supplementation at 10 mg/day improves hair strength, hair thickness, hair fragility, nail thickness, nail brittleness and nail splitting, and that biotin at 1000-5000 mcg/day benefits nails and hair. This page keeps it as a report of what people, websites or other media say.
Silicon for Hair and Nails
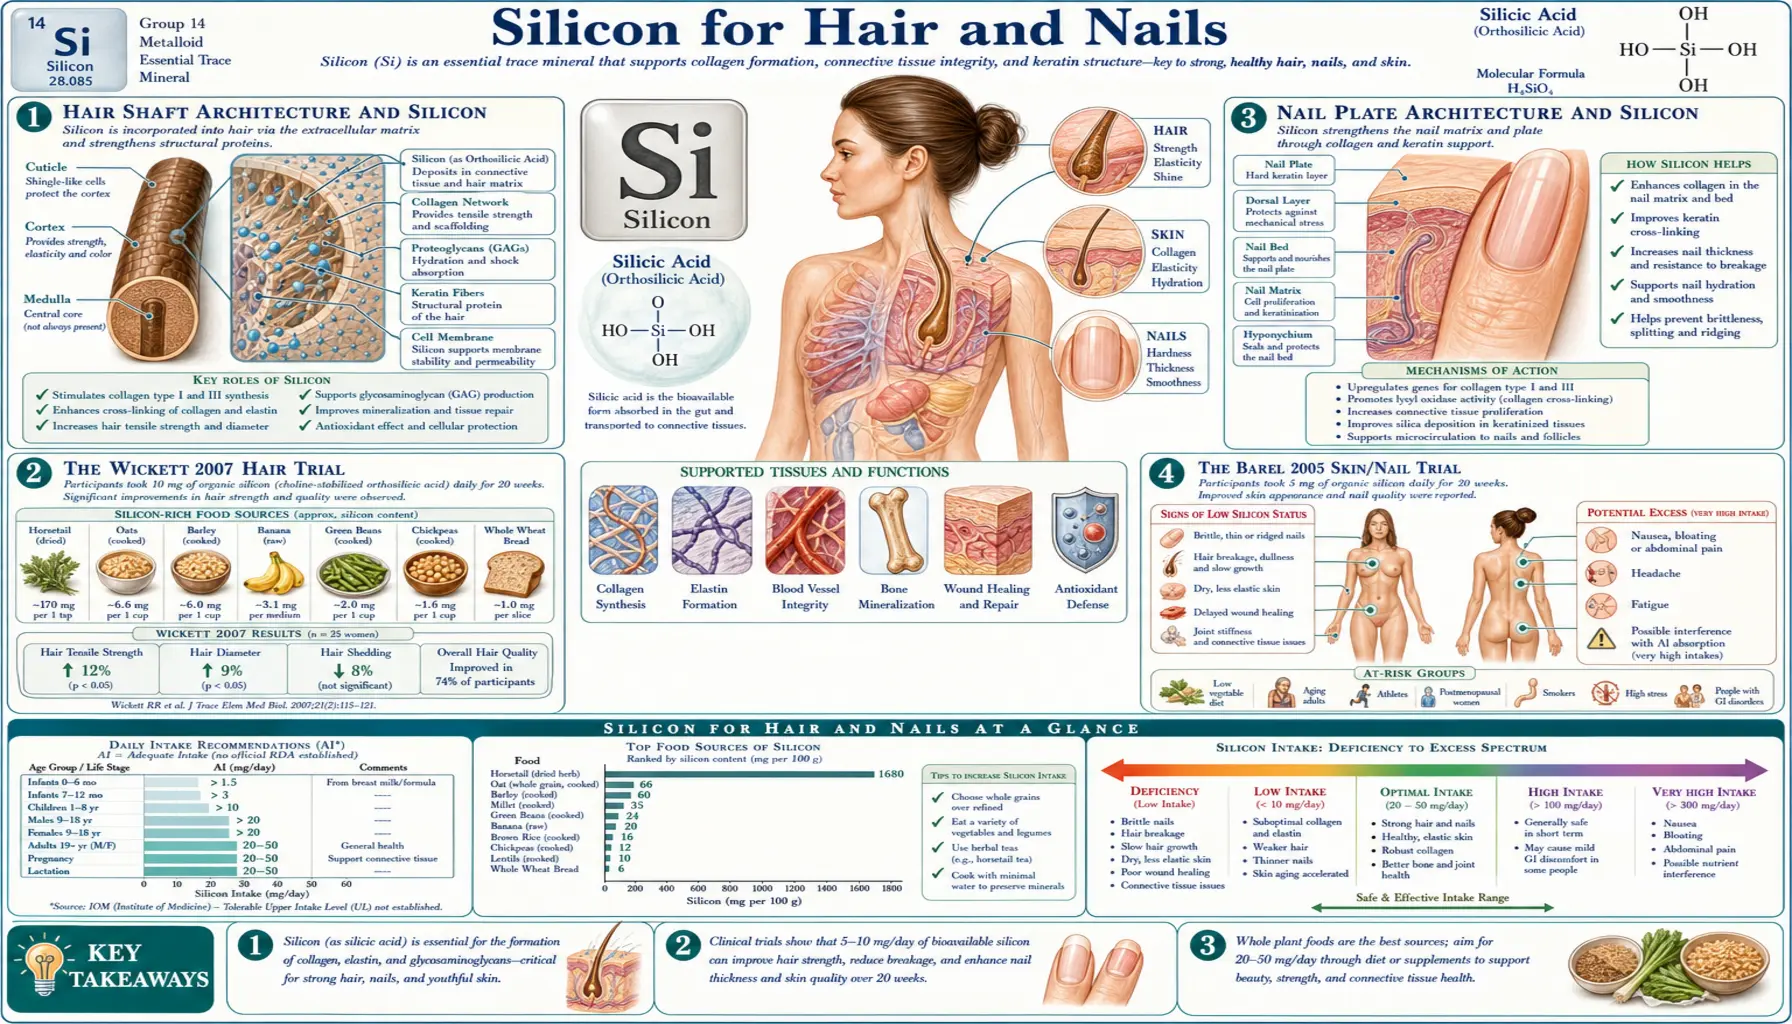
The two best-controlled silicon trials in human biology — Wickett 2007 (48 women, 9 months, hair) and Barel 2005 (50 women, 20 weeks, skin and nails) — both used the same compound: choline-stabilized orthosilicic acid (ch-OSA). At a modest 10 mg/day elemental silicon dose, Wickett found that hair lost less of its stretch and break strength than on placebo and that hair grew thicker than at the start, while Barel found that the women rated their nails and hair as less brittle than at the start of the study. Silicon supplementation improves hair tensile strength, hair shaft diameter, nail thickness, and nail brittleness at a modest 10 mg/day elemental silicon dose. The mechanism is mechanical, not cosmetic: keratin fibers in hair and nail share the same protein chemistry as collagen in skin and bone, and the same collagen-and-glycosaminoglycan scaffold of the hair follicle and nail matrix that determines how the keratin is laid down. Stronger scaffold, stronger keratin. This page walks through how ch-OSA compares with silica gel and horsetail extracts on absorption, the specific endpoints the trials measured, and the doses and time frames the trials used.
Table of Contents
- Hair Shaft Architecture and Silicon
- The Wickett 2007 Hair Trial
- Nail Plate Architecture and Silicon
- The Barel 2005 Skin/Nail Trial
- The Choline-Stabilized Orthosilicic Acid Advantage
- Horsetail (Equisetum) as Dietary Silica Source
- Mechanism: Collagen and GAG Synthesis in Follicle and Nail Matrix
- Trial Doses, Cofactors and Food Sources
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Hair Shaft Architecture and Silicon
A hair shaft is not a homogenous fiber. It is a three-layer composite. The outermost cuticle is a translucent overlapping-scale layer (six to ten cells thick) that protects the underlying structure and gives healthy hair its shine. Beneath the cuticle is the cortex, the bulk of the shaft, composed of densely packed keratin macrofibrils embedded in a matrix of cysteine-rich proteins. At the center of thicker hair shafts is the medulla, a hollow or cell-filled core whose presence and dimension vary among individuals.
Silicon is incorporated into all three layers but is most abundant in the cuticle and cortex. The mechanism is not fully resolved, but two roles are well-supported:
- Cross-linking within the cortex — silicon may participate in siloxane (Si−O−Si) bridge formation between cysteine-poor regions of the keratin chain, supplementing the well-known cystine disulfide cross-links that give hair its tensile strength. This is the silicon analog of the cross-linking it performs in skin collagen.
- Cuticle integrity — the cuticle scales are bound together by a lipid-protein cement called the cell membrane complex. Silicon-rich diets correlate with thicker, more intact cuticle layers, less cuticle lifting (the cause of "frizz" and dullness), and reduced breakage at the hair-shaft mid-length.
The hair shaft itself is metabolically dead once it leaves the follicle, so silicon's effect must be exerted upstream — in the actively growing hair bulb at the base of the follicle, where matrix keratinocytes are synthesizing new keratin and pulling silicon from the dermal papilla blood supply.
The Wickett 2007 Hair Trial
The landmark hair trial was conducted by R. Randall Wickett and colleagues at the University of Cincinnati College of Pharmacy, in cooperation with researchers from Antwerp. The protocol was a 9-month, randomized, double-blind, placebo-controlled study in 48 women with fine hair, randomized 1:1 to 10 mg/day elemental silicon as ch-OSA (10 mg silicon as choline-stabilized orthosilicic acid) or matching placebo.
The trial measured hair shape and tensile (stretch-and-break) properties of hair fibers before and after the 9 months:
- Elasticity (elastic gradient) — fell in both groups over the 9 months, but significantly less with ch-OSA (−4.52%) than with placebo (−11.9%).
- Break load (the force needed to snap a hair) — fell significantly in the placebo group (−10.8%) but not in the ch-OSA group (−2.20%). Break stress and elastic modulus fell in both groups, less so with ch-OSA.
- Hair thickness (cross-sectional area) — increased significantly from baseline after 9 months in the ch-OSA group but not in the placebo group.
- Urine silicon — rose significantly with ch-OSA but not with placebo, and the rise in urine silicon was significantly correlated with the rise in hair thickness.
- Hair break rate measured by 100-stroke combing protocol — ch-OSA group showed reduced fragility.
What is not known: this is a single trial of 48 women, all with fine hair; it did not test men, other hair types or people with hair loss.
The trial was published as Wickett, Kossmann, Barel et al. (2007) in Archives of Dermatological Research. It remains the most rigorous controlled trial of silicon supplementation for hair to date. The 9-month duration was important: a single anagen (growth) phase of a scalp follicle takes 2 to 7 years, but the visible portion of any given hair fiber typically reflects 6 to 24 months of recent metabolic input, so a 9-month study captures the relevant signal.
Nail Plate Architecture and Silicon
The nail plate is a hard, translucent, keratinized structure produced by the nail matrix (the proliferative cell zone under the proximal nail fold and the lunula). Like hair, the nail plate is a three-layer structure: dorsal, intermediate (the thickest layer), and ventral. The intermediate layer is the mechanically dominant layer and is produced primarily by the more proximal portion of the nail matrix.
Nail plate keratin is biochemically distinct from hair keratin but shares the same cysteine-rich, cross-linked architecture. Nail keratin includes higher proportions of K1, K10, K17 and is harder and less elastic than hair keratin. The nail plate also contains roughly 7% to 12% water (compared to hair's ~10%), and water content is the dominant determinant of nail flexibility. Onycholysis, splitting, peeling, and brittleness all reflect failures in either keratin synthesis or interkeratin cement integrity.
Silicon's role in nail health appears to be twofold:
- Improved keratin cross-linking in the nail matrix — analogous to the hair effect, silicon supports the structural integrity of newly synthesized nail keratin.
- Improved dermal and matrix collagen — the nail matrix sits on a bed of dermal collagen and is fed by capillaries within that collagen scaffold. A healthier collagen substrate produces a healthier nail matrix, which in turn produces healthier nail plate.
Lateral splitting (onychoschizia) reports decreased substantially with ch-OSA.
The Barel 2005 Skin/Nail Trial
Andre Barel and colleagues at the Free University of Brussels conducted the 50-woman, 20-week, placebo-controlled trial of ch-OSA at 10 mg/day elemental silicon in women with photodamaged facial skin. Skin roughness and hydration (forearm) and skin mechanical properties (forehead) were measured with instruments; hair and nail brittleness were rated by the women themselves.
The findings:
- Nail and hair brittleness — the women rated it themselves on a scale from 0 (none) to 3 (severe). Scores were significantly lower after 20 weeks in the ch-OSA group than at the start; the abstract reports this against the group's own starting scores, not as a difference from placebo.
- Blood silicon — serum silicon was significantly higher after 20 weeks with ch-OSA than with placebo.
- Skin roughness — roughness measures rose 6–11% on placebo and fell 8–19% on ch-OSA.
What is not known: the trial did not measure nail thickness or nail splitting, and no clinician scored the nails. The paper also carries a published correction for a dosage error in the article text.
The trial was published as Barel, Calomme, Timchenko et al. (2005) in Archives of Dermatological Research. Together with the Wickett 2007 trial, these two studies form the controlled-trial evidence base for choline-stabilized orthosilicic acid supplements.
A 2025 review of nail supplements by two nail specialists from Paris and Brussels (Zaraa and Richert, published online in 2024) lists choline-stabilized orthosilicic acid with biotin, collagen peptides and solubilized keratin among the supplements that "have been shown to improve the clinical appearance of nails, strength, and brittleness". The same review notes a lack of regulation of these supplements by health authorities and that manufacturers are not required to carry out efficacy and safety studies before marketing them.
Both trials gave 10 mg/day elemental silicon, roughly a third of what ordinary diets supplied in the Framingham studies (about 24–25 mg/day in women and 30–33 mg/day in men), and well below any plausible toxicity threshold. The trials gave it as pellets (Barel) and beadlets (Wickett); it is also sold as drops of choline-stabilized concentrate added to water or juice.
The Choline-Stabilized Orthosilicic Acid Advantage
Orthosilicic acid (Si(OH)4) is the bioavailable form of silicon — the form actually absorbed across the small intestinal epithelium, transported in plasma, and incorporated into tissue. Unfortunately, orthosilicic acid is intrinsically unstable in concentrated solution: above approximately 2 millimolar, it spontaneously polymerizes into oligomers and eventually into colloidal silica gel, which is essentially non-absorbable.
A 2016 review (Araújo and colleagues) reports that absorption from silicon supplements ranges from below 1% to close to 50% depending on the chemical form: orthosilicic acid is absorbed best, and the other forms are absorbed less the more polymerized they are. The same review notes that clinical studies of safety and efficacy are still lacking. Silica gel ("silicon dioxide") at the levels found in capsule fillers and many supplements is mostly excreted unabsorbed. Colloidal silicic acid is somewhat better but still tends to oligomerize during shelf storage. Horsetail extract delivers some absorbable silicon but with high inter-individual variability and a thiaminase contamination problem.
The choline-stabilized formulation solves the polymerization problem chemically: choline cations associate with the silicate hydroxyl groups and physically prevent the silicate molecules from polymerizing during shelf storage. When the formulation is diluted in stomach contents, the choline-silicate complex dissociates and the orthosilicic acid is absorbed. In a 1997 study in calves, Calomme and Vanden Berghe found that raising total dietary silicon by only 4.9% with stabilized orthosilicic acid raised blood silicon by 70% after 23 weeks, which the authors read as high bioavailability.
The practical implication is that 10 mg/day elemental silicon as ch-OSA may deliver more bioavailable silicon than 100 mg/day of horsetail extract or commodity silica supplements. The ch-OSA price premium is real (typical retail $25-40/month) but reflects the actual delivered dose.
Horsetail (Equisetum) as Dietary Silica Source
Equisetum arvense (common horsetail) is the traditional botanical source of silica in Western herbalism. Field horsetail can contain up to 10% silica by dry weight, far higher than any food crop, and was historically used in folk medicine for "weak hair and brittle nails" centuries before the biochemistry was understood. Modern dried horsetail preparations typically deliver 5 to 8 mg elemental silicon per gram of dried herb.
The horsetail story has two caveats:
- Variable absorption — most of the silicon in raw horsetail is bound as polymerized silica in the plant cell wall, in non-absorbable form. Tea preparation and extraction conditions affect how much is converted to absorbable orthosilicic acid. Studies of horsetail tea have measured 25 to 50% release of elemental silicon depending on brewing time and temperature.
- Thiaminase content — horsetail contains the enzyme thiaminase, which destroys vitamin B1 (thiamin). Horsetail thiaminase poisoning is documented mainly in livestock; in people, thiamin deficiency from prolonged high-dose use is a reported concern, particularly for individuals with marginal B1 status (chronic alcohol use, severe malabsorption, advanced age). Commercial horsetail products are usually heat-treated to denature the thiaminase; the concern applies mainly to raw or under-extracted preparations taken long-term.
Traditional horsetail use: a standard tea (1 tsp dried herb in 1 cup boiling water, steeped 10 minutes, 1-2 cups per day) is described as delivering roughly 3 to 6 mg elemental silicon per cup. It is a botanical source of silicon, with a less predictable dose than ch-OSA.
Mechanism: Collagen and GAG Synthesis in Follicle and Nail Matrix
The unified mechanism underlying silicon's effects on both hair and nails is the same as its mechanism in connective tissue more broadly: support for prolyl hydroxylase activity in collagen synthesis, and support for glycosaminoglycan (GAG) cross-linking in the extracellular matrix.
- Hair follicle dermal papilla is a specialized cluster of dermal collagen and proteoglycan at the base of each hair follicle, surrounded by capillaries that supply nutrients to the matrix keratinocytes. The dermal papilla is essentially a tiny piece of organized connective tissue whose health determines the rate, diameter, and quality of hair growth from that follicle. Silicon-deficient dermal papillae produce thinner, weaker hair shafts — the same effect silicon deficiency has on dermal collagen generally.
- Hyaluronic acid in the dermal papilla creates the hydrated matrix that allows the follicle to expand and contract through the hair cycle. Silicon supports hyaluronic acid synthesis throughout the body; the follicle is no exception.
- Nail matrix bed collagen — the nail matrix sits on a collagen-rich connective tissue bed. Healthier collagen substrate equals healthier matrix equals healthier nail plate. The silicon effect on nail growth is largely an indirect effect mediated through the underlying dermal collagen.
- Keratin assembly — once silicon has supported the production of a healthy follicle or matrix, the actual keratin synthesis is performed by specialized epithelial cells (matrix keratinocytes for hair, nail matrix cells for nails). These cells may themselves incorporate some silicon into the keratin product, but most of the structural benefit comes upstream of keratin assembly, in the support of the connective tissue scaffold.
This mechanism explains why silicon supplementation typically takes 3 to 6 months to show visible hair and nail benefits: that is the time required for the dermal papilla and nail matrix to respond to improved silicon status and for the resulting healthier keratin output to grow out to a visible length. The trials measured results at 20 weeks (Barel) and 9 months (Wickett); neither reported results at 4 to 6 weeks.
Trial Doses, Cofactors and Food Sources
- Trial dose — Wickett 2007 and Barel 2005 both gave ch-OSA (choline-stabilized orthosilicic acid) at 10 mg/day elemental silicon. Typical commercial liquid preparations are taken as 5 to 6 drops in a glass of water or juice, twice per day, with meals.
- Co-factors — silicon depends on vitamin C and iron as enzymatic cofactors for prolyl hydroxylase. Practitioners commonly describe vitamin C intakes of 90-200 mg/day from food or supplements and, for hair, a ferritin above 50 ng/mL, with iron status of particular concern in menstruating women.
- Dietary support — whole oats and barley are the richest dietary silicon sources commonly consumed. A daily bowl of unprocessed oatmeal delivers 6 to 10 mg of elemental silicon. Drinking water is a variable source, with some mineral waters relatively high in silicon (Powell 2005); a daily glass of a high-silica mineral water is described as adding another 8 to 15 mg.
- Ordinary diets — in the Framingham studies, ordinary diets supplied about 24–25 mg of silicon a day in women and 30–33 mg in men, mainly from beer and bananas in men and bananas and string beans in women. On average 41% of the silicon eaten in food appeared in the urine, a sign that it was absorbed. Everyday food therefore already supplied two to three times the 10 mg used in the trials (Jugdaohsingh 2002).
- Protein adequacy — hair and nail keratin require sufficient sulfur amino acids (cysteine, methionine). Adequate dietary protein (0.8 to 1.2 g/kg body weight) is foundational; eggs are a particularly good source of cysteine.
- Time horizon — the trials measured change at 20 weeks (skin, nails) and 9 months (hair).
- Biotin — biotin is widely sold for hair and nails, often in 1000-5000 mcg/day doses. 1000-5000 mcg/day biotin has independent evidence for nail and hair benefit; the combination of silicon and biotin is well-tolerated and addresses two distinct mechanisms. A 2017 systematic review (Patel and colleagues) found 18 reported cases of improvement with biotin, all in people with an underlying cause of poor hair or nail growth, and concluded that there is not enough evidence for biotin supplements in healthy people. Trüeb 2016 found biotin deficiency in 38% of women complaining of hair loss and wrote that treating such women with biotin indiscriminately “is to be rejected” unless deficiency has been shown.
Cautions
- Kidney impairment — silicon is cleared by the kidneys, so people with advanced chronic kidney disease clear supplemental silicon less well; none of the trials cited here included people with kidney disease.
- Horsetail thiaminase — heat treatment denatures horsetail's thiaminase, which is why commercial products are usually heat-treated; the thiamin (vitamin B1) concern is greatest with raw preparations and prolonged high-dose use.
- Biotin lab interference — high-dose biotin (10,000 mcg or more per day) interferes with several common immunoassays including thyroid panels and troponin and can give falsely high or low results; a 72-hour pause before blood work is the interval commonly given.
- Slow onset — the trials that report silicon's benefit ran 20 weeks (skin/nail) and 9 months (hair). A 4-to-6-week period falls well short of that biological time scale.
- Hair loss with non-nutritional causes — alopecia areata, androgenetic alopecia, telogen effluvium from severe stress or postpartum, scalp inflammation, and thyroid dysfunction all have specific mechanisms that silicon does not address.
- Drug interactions — limited data. Separating doses by at least 2 hours from levothyroxine and tetracycline-family antibiotics is a general precaution applied to mineral supplements, not one drawn from silicon studies.
This content is provided for informational purposes only and does not constitute medical advice. None of the trials cited here studied silicon supplements in pregnancy, breastfeeding or chronic disease.
Key Research Papers
- Wickett RR, Kossmann E, Barel A et al. (2007). Effect of oral intake of choline-stabilized orthosilicic acid on hair tensile strength and morphology in women with fine hair. Archives of Dermatological Research. — PubMed PMID: 17960402
- Barel A, Calomme M, Timchenko A et al. (2005). Effect of oral intake of choline-stabilized orthosilicic acid on skin, nails and hair in women with photodamaged skin. Archives of Dermatological Research. — PubMed PMID: 16205932
- Calomme MR, Vanden Berghe DA (1997). Supplementation of calves with stabilized orthosilicic acid. Effect on the Si, Ca, Mg, and P concentrations in serum and the collagen concentration in skin and cartilage. Biological Trace Element Research. — PubMed PMID: 9164661
- Jugdaohsingh R (2007). Silicon and bone health. Journal of Nutrition, Health & Aging. — PubMed PMID: 17435952
- Araujo LA, Addor F, Campos PMBGM (2016). Use of silicon for skin and hair care: an approach of chemical forms available and efficacy. Anais Brasileiros de Dermatologia. — PubMed PMID: 27438201
- Lassus A (1993). Colloidal silicic acid for oral and topical treatment of aged skin, fragile hair and brittle nails in females. Journal of International Medical Research. — PubMed PMID: 8112478
- Sripanyakorn S, Jugdaohsingh R, Elliott H et al. (2004). The silicon content of beer and its bioavailability in healthy volunteers. British Journal of Nutrition. — PubMed PMID: 15005826
- Powell JJ, McNaughton SA, Jugdaohsingh R et al. (2005). A provisional database for the silicon content of foods in the United Kingdom. British Journal of Nutrition. — PubMed PMID: 16277785
- Carlisle EM (1986). Silicon. In Mertz W (ed), Trace Elements in Human and Animal Nutrition, 5th edition, Academic Press. — PubMed
- Reffitt DM, Ogston N, Jugdaohsingh R et al. (2003). Orthosilicic acid stimulates collagen type 1 synthesis and osteoblastic differentiation in human osteoblast-like cells in vitro. Bone. — PubMed PMID: 12633784
- Trueb RM (2016). Serum biotin levels in women complaining of hair loss. International Journal of Trichology. — PubMed PMID: 27601860
- Jugdaohsingh R, Anderson SH, Tucker KL et al. (2002). Dietary silicon intake and absorption. American Journal of Clinical Nutrition. — PubMed PMID: 11976163
- Patel DP, Swink SM, Castelo-Soccio L (2017). A Review of the Use of Biotin for Hair Loss. Skin Appendage Disorders. — PubMed PMID: 28879195
- Zaraa I, Richert B (2025). Nail Supplements: When, How, and Why? Skin Appendage Disorders. — PubMed PMID: 40176998
PubMed Topic Searches
Connections
- All Minerals
- Silicon Overview
- Silicon Benefits Hub
- Silicon for Connective Tissue
- Silicon for Bone Density
- Silicon for Cardiovascular Health
- Collagen
- Vitamin C (Prolyl Hydroxylase Cofactor)
- Biotin (Hair and Nail Synergist)
- Zinc (Keratin Synthesis)
- Iron (Hair Cycle)
- Proline
- Cysteine
- Horsetail (Equisetum arvense)
- Oats (Dietary Silicon)
- Choline
- Deficiency
- Toxicity
- History