Amylase and Lipase
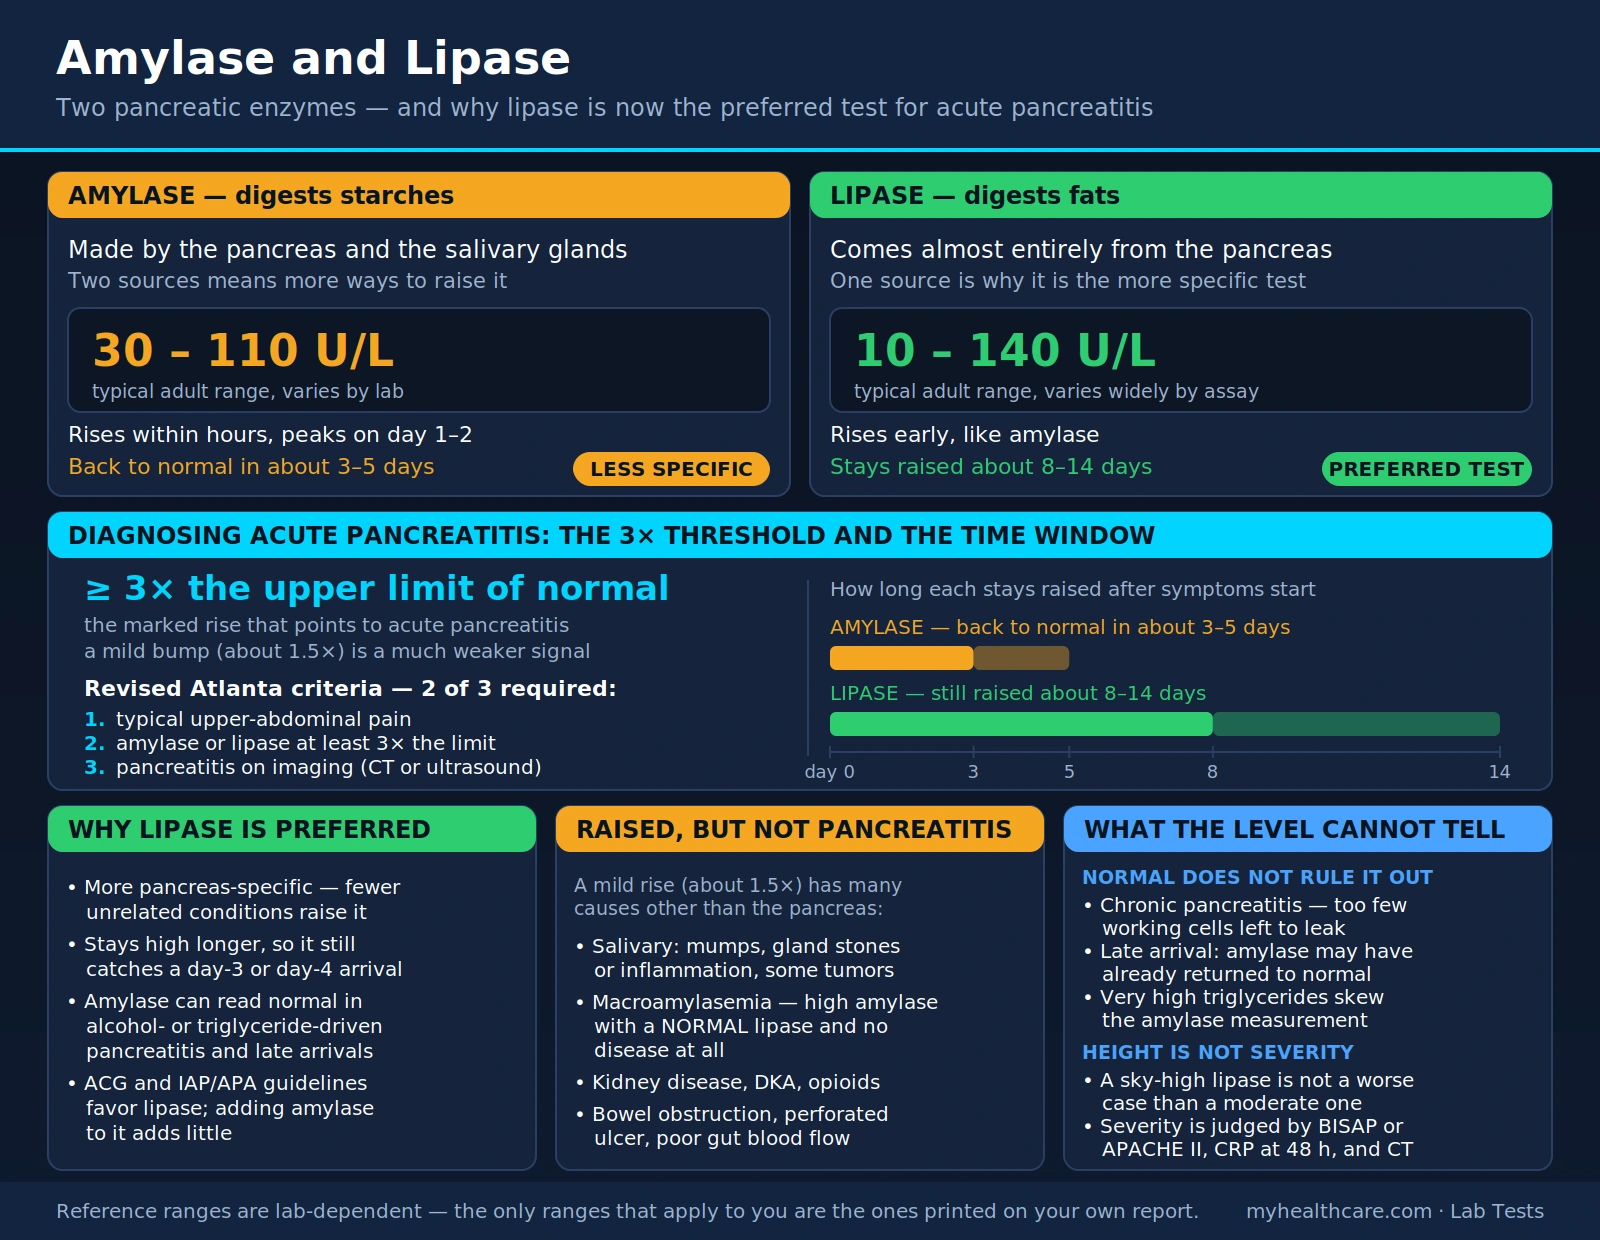
Amylase and lipase are two digestive enzymes, and their levels in the blood are a classic laboratory clue to acute pancreatitis — sudden inflammation of the pancreas. When the pancreas is inflamed or injured, these enzymes leak into the bloodstream and their levels rise, and an enzyme level at least three times the upper limit of normal is one of the three criteria used to diagnose the condition. This page explains what each enzyme does, why the tests are ordered, and how the two compare: the 2024 American College of Gastroenterology (ACG) guideline states that serum amylase alone cannot be used reliably for the diagnosis and that serum lipase is preferred. Lipase’s advantage is clearest for sensitivity and for how long it stays raised; on specificity the evidence is mixed, and a 2017 Cochrane review found similar pooled specificities for the two tests and could not compare them formally. The page also covers the tests’ limits — other conditions can raise these enzymes, a normal result does not always rule pancreatitis out, and the height of the number does not show how severe the illness is.
Table of Contents
- What Amylase and Lipase Are
- Why These Tests Are Ordered
- Lipase vs. Amylase: Which Is Better?
- How the Levels Behave Over Time
- Normal Ranges and the "3× Upper Limit" Threshold
- What Elevated Levels Mean
- What Normal Levels Do Not Rule Out
- Enzyme Levels Do Not Measure Severity
- Related Tests and Finding the Cause
- How Acute Pancreatitis Presents
- Key Research Papers
- Connections
- Featured Videos
What Amylase and Lipase Are
Amylase and lipase are digestive enzymes — proteins that speed up the breakdown of food so your body can absorb it. They do different jobs:
- Amylase digests starches. According to a 2015 review, it acts mainly on starch, glycogen and related polysaccharides. It is made in separate forms by the salivary glands (salivary or S-type amylase) and by the pancreas (pancreatic or P-type isoamylase). Almost all laboratories measure total amylase, which includes both forms, and the review notes that up to 60% of total serum amylase comes from non-pancreatic sources; the pancreatic form is not routinely measured in most laboratories.
- Lipase digests fats. Pancreatic triglyceride lipase, working with its cofactor colipase, is required for efficient digestion of dietary triglycerides (Lowe 2002). The 2015 review states that the concentration of lipase in pancreatic tissue is about 100-fold higher than in other tissues such as the duodenum, stomach, fat and lung, which is part of why it is used as a pancreas test.
In normal digestion, pancreatic enzymes are released into the pancreatic duct, which drains into the small intestine, and only small amounts circulate in the blood. When the pancreas becomes inflamed or injured, enzymes leak into the bloodstream and blood levels rise. Measuring that rise is the point of the amylase and lipase blood tests.
Why These Tests Are Ordered
By far the most common reason to order amylase and lipase is to help diagnose acute pancreatitis. The 2024 ACG guideline describes the typical pain as epigastric or left-upper-quadrant pain, usually constant, radiating to the back, chest or flank. The two most common causes are gallstones and alcohol, which the guideline puts at 40–70% and 25–35% of cases. It describes other causes — certain medications, infections, and metabolic causes such as high blood calcium and very high triglycerides — as rare and more often wrongly blamed, and the 2013 ACG guideline addresses pancreatitis that follows the procedure called ERCP.
Acute pancreatitis is not diagnosed on the blood test alone. The 2024 ACG guideline, citing the revised Atlanta classification, states that the diagnosis is most often established by two of three findings: (1) abdominal pain consistent with the disease, (2) serum amylase and/or lipase greater than three times the upper limit of normal, and (3) characteristic findings on abdominal imaging. A 2015 review names abdominal ultrasound for the imaging, with CT or MRI considered when the diagnosis is uncertain. So the enzymes are one of three pillars — powerful when they line up with the pain, but interpreted in context.
Beyond that headline use, these tests are ordered as part of the general workup of unexplained abdominal pain (to help sort a pancreatic cause from the many other reasons a belly can hurt) and occasionally to help evaluate the pancreas in other settings. They are less useful in chronic pancreatitis: the 2015 review states that in an acute flare of chronic pancreatitis, neither enzyme may be elevated.
Lipase vs. Amylase: Which Is Better?
For diagnosing acute pancreatitis, the 2024 ACG guideline states that serum amylase alone cannot be used reliably, because of limits on its sensitivity and negative predictive value, and that serum lipase is preferred; the 2015 review likewise states that lipase has replaced amylase as the biochemical test of choice. The evidence behind that preference is strongest for sensitivity and for how long each enzyme stays raised. On specificity the studies disagree:
- Sensitivity. In a 2005 study of 10,931 hospital patients, lipase identified 90.3% of acute pancreatitis cases at its diagnostic threshold, compared with 76.8% for amylase, and on the first emergency-department measurement 18.8% of patients with pancreatitis had a normal amylase, compared with 2.9% for lipase. The 2017 Cochrane review of ten emergency-department studies found pooled sensitivities of 0.79 for lipase and 0.72 for amylase at more than three times normal.
- Specificity. The 2024 ACG guideline states that lipase seems to be more specific, and the 2015 review states that lipase’s specificity was higher than amylase’s in several studies. But the 2017 Cochrane review found pooled specificities of 0.89 for lipase and 0.93 for amylase, with wide confidence intervals, and could not compare the tests formally because the data were sparse. In the 2005 study the two were almost identical (93% and 92.6%), and a 2002 review notes that non-specific lipase rises have been reported in almost as many disorders as amylase rises.
- How long each stays raised. The 2024 ACG guideline states that amylase returns to normal within 3–5 days, and the 2015 review states that lipase stays elevated for 8–14 days. In a 1998 study of 253 patients with abdominal pain, the two enzymes performed similarly on days 0–1, but on days 2–3 lipase was notably better: at a sensitivity of 85%, specificity was 82% for lipase and 68% for amylase.
- Particular causes. The ACG guideline notes that amylase may be normal in alcohol-induced pancreatitis and in pancreatitis caused by high triglycerides, and the 2015 review states that lipase has greater sensitivity in alcohol-related pancreatitis.
On ordering both tests together, the 2015 review states that most guidelines do not advocate it because the gain in sensitivity over a single test is only marginal and not cost-effective; a 2002 review found that measuring both does not improve accuracy; and a 2017 review concluded that co-ordering adds little to no diagnostic sensitivity or specificity, so testing lipase alone can reduce unnecessary testing. Not every study agrees: the 1998 study found that measuring both marginally improved diagnosis, and the authors of a 1999 case series of 25 patients with a high lipase but normal amylase recommended measuring both enzymes. In all of these sources the enzyme result is read alongside the patient’s symptoms and, when needed, imaging.
How the Levels Behave Over Time
The timing helps explain why lipase is preferred and why a normal result can mislead. In acute pancreatitis, both enzymes begin rising within hours of the pain starting:
- Amylase rises within 3–6 hours of symptom onset and may stay elevated for up to five days, according to the 2015 review, which adds that its half-life of about 12 hours means its level can normalise within 24 hours. The 2024 ACG guideline states that it returns to normal within 3–5 days and may already be within the normal range on admission in as many as one-fifth of patients.
- Lipase also rises 3–6 hours after onset, usually peaks at 24 hours, and stays elevated for 8–14 days, which the 2015 review attributes to reabsorption of lipase in the kidney tubules.
The time between the start of symptoms and the blood draw therefore changes the result. The 2015 review describes lipase as far more useful than amylase when presentation or testing has been delayed by more than 24 hours, and the 2017 Cochrane review found that the tests’ accuracy falls further as time passes from symptom onset.
Normal Ranges and the "3× Upper Limit" Threshold
Reference ranges for these enzymes are lab-dependent, so the range that applies to a result is the one printed beside it on the report. The 2015 review gives a typical serum amylase reference range of 20–300 U/L that varies with age, sex and laboratory, and notes that lipase reference ranges also vary and that the best diagnostic cut-off is debated. The 2024 ACG guideline adds that a Japanese consensus conference could not agree on appropriate upper limits of normal for amylase and lipase.
The diagnostic criterion is not simply “above normal”: it is an amylase or lipase at least three times the upper limit of normal. The cut-off is debated. The 2015 review states that most guidelines suggest 2–4 times the upper limit as optimal for amylase and 2–3 times for lipase, and the 2024 ACG guideline notes that some people without acute pancreatitis have levels above three times normal, that a cut-off of more than 3–5 times may be needed in some groups such as people with diabetes, and that without abdominal pain consistent with the disease, raised amylase and lipase do not predict acute pancreatitis.
What Elevated Levels Mean
A markedly elevated lipase or amylase (at or above three times the upper limit) in someone with the characteristic upper-abdominal pain meets two of the three diagnostic criteria for acute pancreatitis. But both enzymes can rise for other reasons. The 2015 review’s table of causes and the 2024 ACG guideline list, among others:
- Kidney disease. The review lists renal failure as raising both enzymes, and the ACG guideline lists a decreased glomerular filtration rate among the causes of a falsely raised amylase.
- Other abdominal conditions. The review lists perforated viscus, intestinal infarction and obstruction, peritonitis, acute cholecystitis, appendicitis, hepatitis and abdominal aortic aneurysm as raising both enzymes. The ACG guideline notes that when doubt about the diagnosis exists, abdominal imaging may assist.
- Salivary and gynecologic sources. Both sources list salivary gland disease as raising amylase. The review lists ruptured ectopic pregnancy and fallopian and ovarian cysts under amylase only, and lists mumps among the causes of raised lipase.
- Macroamylasemia. The ACG guideline describes a syndrome in which amylase forms large complexes with abnormal immunoglobulins, falsely raising serum amylase; the 2015 review describes it as uncommon and caused by reduced clearance of amylase.
- Ketoacidosis. The review lists ketoacidosis as raising both enzymes.
- Certain medications. The review lists many drugs as raising one or both enzymes, including opioids (listed under lipase), and marks most of them as drugs that can cause acute pancreatitis but can also raise the enzymes without it.
Lipase is not immune: a 2002 review notes that non-specific lipase rises have been reported in almost as many disorders as amylase rises, and a 2015 review of intensive-care patients states that neither amylase nor lipase is specific for pancreatitis. This is why the number is read alongside the clinical picture.
What Normal Levels Do Not Rule Out
A normal amylase and lipase does not completely exclude pancreatic disease. The 2017 Cochrane review found that about a quarter of people with acute pancreatitis were not identified by the tests it evaluated. The reviews describe several situations in which the enzymes can look normal despite real illness:
- Chronic pancreatitis. The 2015 review states that in an acute flare of chronic pancreatitis, neither enzyme may be elevated.
- Late presentation. Amylase returns to normal within 3–5 days (ACG 2024) and lipase stays elevated for 8–14 days (2015 review), so a test taken late can be normal; amylase’s shorter window is one reason lipase is preferred.
- Very high triglycerides. In pancreatitis caused by high triglycerides, the 2015 review states that serum amylase can be normal in up to 50% of cases, because a circulating inhibitor or the fatty blood itself interferes with the assay.
The Cochrane reviewers concluded that a low threshold to admit and treat is warranted when symptoms suggest acute pancreatitis, even if these tests are normal. In these cases the symptoms and imaging carry the diagnosis, not the enzyme number alone.
Enzyme Levels Do Not Measure Severity
This point is often misunderstood: how high the amylase or lipase goes does not show how severe the pancreatitis is. The 2024 ACG guideline states that once the diagnosis is established, there is no reason to follow amylase or lipase, because the levels bear no relationship to severity or prognosis and do not guide decisions on refeeding or discharge. A 2002 review found that no enzyme assay predicts severity or cause, and the 2015 review states that neither enzyme predicts severity in adults (it notes that in children lipase may be related to severity). The enzymes help answer “is this pancreatitis?” — not “how bad is it?”
Severity is judged with other tools. The 2015 review lists scoring systems that combine clinical and laboratory criteria (Ranson, BISAP, APACHE and Glasgow) and describes a C-reactive protein above 150 mg/L measured 48 hours after symptoms begin as the best single laboratory predictor of severity. The 2024 ACG guideline describes CT or MRI to assess local complications such as pancreatic necrosis in patients who fail to improve after 48–72 hours. The revised Atlanta classification grades an episode as mild, moderately severe or severe by organ failure and local or systemic complications, not by the enzyme level.
Related Tests and Finding the Cause
Amylase and lipase are rarely ordered alone. The guidelines and reviews describe other tests used to find why the pancreas became inflamed and how serious the episode is:
- Liver tests. A 2006 review states that a serum alanine transaminase (ALT) above 150 IU/l together with jaundice suggests gallstones as the cause.
- Abdominal ultrasound. The 2024 ACG guideline calls for abdominal ultrasound in all patients with acute pancreatitis to look for gallstones, with a repeat ultrasound if the first is inconclusive.
- Triglycerides. The ACG guideline lists a triglyceride level when there are no gallstones and no significant history of alcohol use; triglycerides are considered the cause when they rise above 1,000 mg/dL.
- Calcium. The 2006 review lists serum calcium, together with triglycerides, for pancreatitis of unclear cause; the ACG guideline describes high calcium as a rare cause.
- CT or MRI/MRCP. The 2013 ACG guideline reserves contrast-enhanced CT and/or MRI for patients whose diagnosis is unclear or who fail to improve, and the 2024 guideline includes MRCP in the work-up of pancreatitis with no cause found.
- Severity scores. These combine clinical findings with routine laboratory results; the 2024 ACG guideline notes that they typically require 48 hours to become accurate.
Together these turn a single enzyme number into a full picture: what is wrong, how serious it is, and what caused it.
How Acute Pancreatitis Presents
The 2024 ACG guideline describes the pain of acute pancreatitis as epigastric or left-upper-quadrant pain, usually constant and radiating to the back, chest or flank. It states that while most patients have symptoms lasting a few days, almost one-fifth go on to complications such as pancreatic necrosis or organ failure, at times requiring prolonged hospital care, intensive care or intervention, and it describes early management as essential.
An enzyme result on its own does not settle whether a person with this kind of pain has pancreatitis. The 2017 Cochrane review found that the tests miss about a quarter of cases and may wrongly flag about 1 in 10 people without the disease, and its authors concluded that a low threshold to admit and treat is warranted when symptoms suggest acute pancreatitis, even if the tests are normal. The 2013 ACG guideline states that early aggressive intravenous hydration is most beneficial within the first 12–24 hours. Decisions about symptoms like these belong with a clinician.
Key Research Papers
- Tenner S, Baillie J, DeWitt J, Vege SS. American College of Gastroenterology Guideline: Management of Acute Pancreatitis. American Journal of Gastroenterology. 2013;108(9):1400-1415. — the 2013 ACG guideline; cited by a 2015 review for the two-of-three diagnostic criteria and for lipase having replaced amylase as the test of choice. — doi:10.1038/ajg.2013.218
- Banks PA, Bollen TL, Dervenis C, et al. Classification of acute pancreatitis—2012: revision of the Atlanta classification and definitions by international consensus. Gut. 2013;62(1):102-111. — the revised Atlanta classification, cited by the 2024 ACG guideline for the two-of-three diagnostic rule; grades severity as mild, moderately severe or severe. — doi:10.1136/gutjnl-2012-302779
- Working Group IAP/APA Acute Pancreatitis Guidelines. IAP/APA evidence-based guidelines for the management of acute pancreatitis. Pancreatology. 2013;13(4 Suppl 2):e1-e15. — 38 GRADE-rated international recommendations across 12 topics, beginning with diagnosis and etiology. — doi:10.1016/j.pan.2013.07.063
- Ismail OZ, Bhayana V. Lipase or amylase for the diagnosis of acute pancreatitis? Clinical Biochemistry. 2017;50(18):1275-1280. — a review finding lipase more sensitive than amylase, with a longer diagnostic window, and that co-ordering both adds little to no diagnostic sensitivity or specificity. — doi:10.1016/j.clinbiochem.2017.07.003
- Rompianesi G, Hann A, Komolafe O, Pereira SP, Davidson BR, Gurusamy KS. Serum amylase and lipase and urinary trypsinogen and amylase for diagnosis of acute pancreatitis. Cochrane Database of Systematic Reviews. 2017;(4):CD012010. — ten emergency-department studies; at more than three times normal, pooled sensitivity 0.79 (lipase) and 0.72 (amylase), specificity 0.89 and 0.93; the tests could not be compared formally because the data were sparse. — doi:10.1002/14651858.CD012010.pub2
- Keim V, Teich N, Fiedler F, Hartig W, Thiele G, Mössner J. A Comparison of Lipase and Amylase in the Diagnosis of Acute Pancreatitis in Patients with Abdominal Pain. Pancreas. 1998;16(1):45-49. — 253 patients with abdominal pain; similar accuracy on days 0–1, lipase notably better on days 2–3, and measuring both improved diagnosis only marginally. — doi:10.1097/00006676-199801000-00008
- Yadav D, Agarwal N, Pitchumoni CS. A critical evaluation of laboratory tests in acute pancreatitis. American Journal of Gastroenterology. 2002;97(6):1309-1318. — reviews the strengths and pitfalls of amylase and lipase in real practice. — doi:10.1111/j.1572-0241.2002.05766.x
- Smith RC, Southwell-Keely J, Chesher D. Should serum pancreatic lipase replace serum amylase as a biomarker of acute pancreatitis? ANZ Journal of Surgery. 2005;75(6):399-404. — 10,931 hospital patients; lipase was the more accurate biomarker (area under the curve 0.948 versus 0.906). — doi:10.1111/j.1445-2197.2005.03391.x
- Frank B, Gottlieb K. Amylase Normal, Lipase Elevated: Is It Pancreatitis? A Case Series and Review of the Literature. American Journal of Gastroenterology. 1999;94(2):463-469. — 25 patients with lipase at least three times normal but a normal amylase; the authors linked many of these to non-pancreatic causes or delayed blood sampling and recommended measuring both enzymes. — doi:10.1111/j.1572-0241.1999.878_g.x
- Muniraj T, Dang S, Pitchumoni CS. Pancreatitis or not? — Elevated lipase and amylase in ICU patients. Journal of Critical Care. 2015;30(6):1370-1375. — catalogs the many non-pancreatic reasons these enzymes rise, especially in sick patients. — doi:10.1016/j.jcrc.2015.08.020
- Crockett SD, Wani S, Gardner TB, Falck-Ytter Y, Barkun AN. American Gastroenterological Association Institute Guideline on Initial Management of Acute Pancreatitis. Gastroenterology. 2018;154(4):1096-1101. — the AGA guideline on early management; cited by the 2024 ACG guideline among guidelines that emphasize the advantage of serum lipase. — doi:10.1053/j.gastro.2018.01.032
- Tenner S, Vege SS, Sheth SG, Sauer B, Yang A, Conwell DL, Yadlapati RH, Gardner TB. American College of Gastroenterology Guidelines: Management of Acute Pancreatitis. American Journal of Gastroenterology. 2024;119(3):419-437. — states that serum amylase alone cannot be used reliably for diagnosis and that serum lipase is preferred; amylase returns to normal within 3–5 days. — doi:10.14309/ajg.0000000000002645
- Basnayake C, Ratnam D. Blood tests for acute pancreatitis. Australian Prescriber. 2015;38(4):128-130. — timing of both enzymes, the table of non-pancreatic causes, and why lipase is now the preferred test. — doi:10.18773/austprescr.2015.043
- Matull WR, Pereira SP, O'Donohue JW. Biochemical markers of acute pancreatitis. Journal of Clinical Pathology. 2006;59(4):340-344. — ALT above 150 IU/l with jaundice suggests gallstones; calcium and triglycerides for unclear causes. — doi:10.1136/jcp.2002.002923
- Lowe ME. The triglyceride lipases of the pancreas. Journal of Lipid Research. 2002;43(12):2007-2016. — pancreatic triglyceride lipase and colipase are required for efficient dietary triglyceride digestion. — doi:10.1194/jlr.r200012-jlr200