Feverfew: How Parthenolide Works
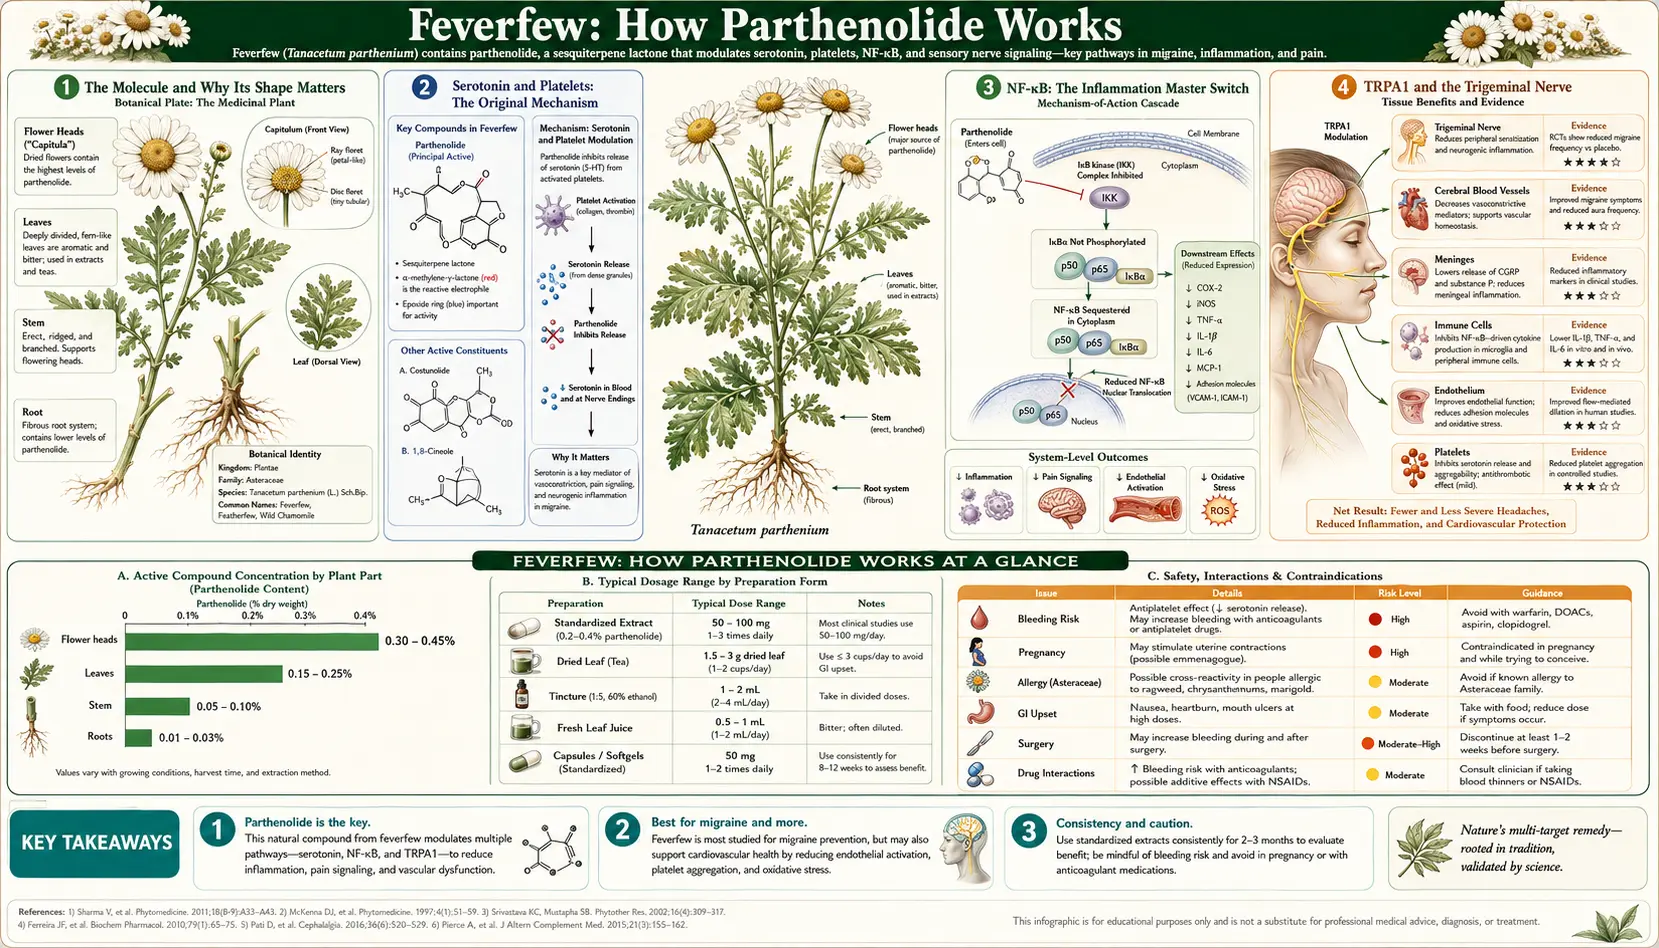
Feverfew's supposed active compound is parthenolide, a sesquiterpene lactone that makes up a fraction of a percent of the dried leaf. Almost everything you will read about how feverfew works is really about parthenolide, and almost every product that claims to be standardised is standardised to it.
The pharmacology is real. Parthenolide is not a vague “plant compound with antioxidant properties” it has a specific chemical reactivity, a known molecular target in inflammation, and a documented action on the exact nerve population that generates migraine pain. It is one of the better-characterised natural products in the literature.
There is also a problem sitting underneath all of it, and this page does not bury it: when researchers gave people oral parthenolide and measured their blood, they could not detect any. That single finding constrains how much of the mechanism story can plausibly explain what happens when someone swallows a feverfew capsule. We will get there.
Table of Contents
- The Molecule and Why Its Shape Matters
- Serotonin and Platelets: The Original Mechanism
- NF-κB: The Inflammation Master Switch
- TRPA1 and the Trigeminal Nerve
- Prostaglandins and Other Inflammatory Enzymes
- The Bioavailability Problem
- How Much of the Effect Comes From Parthenolide
- How Well Each Mechanism Fits Migraine
- Parthenolide Outside Feverfew
- What Would Actually Settle This
- What the Mechanism Implies for Safety
- Key Research Papers
- Connections
- Featured Videos
The Molecule and Why Its Shape Matters
Parthenolide is a germacranolide sesquiterpene lactone: fifteen carbons arranged in a ten-membered ring, fused to a five-membered lactone ring, with an epoxide bridge on the large ring. Formula C15H20O3, molecular weight about 248. It is concentrated in the leaves, flowering tops and seeds, and scarce in stalks and roots (Heptinstall 1992).
One structural feature explains most of its biology: the α-methylene-γ-lactone. That is a carbon-carbon double bond sitting next to the lactone's carbonyl group, and it makes the molecule an electrophile — chemically hungry for electrons. In practical terms it acts as a Michael acceptor: it reacts with sulphur-containing thiol (–SH) groups, particularly the cysteine residues in proteins, and forms a covalent bond.
Once you know that, several apparently unrelated observations line up:
- It inhibits proteins with a critical cysteine. Parthenolide does not have to fit a receptor pocket; it chemically modifies its target. That is why its targets are diverse.
- It is a contact allergen. Covalently modifying skin proteins creates new antigens, which is the textbook route to sesquiterpene lactone contact dermatitis. Parthenolide is a recognised Compositae sensitiser (Paulsen 2010) — the same chemistry that gives feverfew its pharmacology gives it its allergy problem.
- It is unstable. A reactive molecule degrades. Parthenolide levels fall during storage of powdered leaf (Heptinstall 1992), and in one dermatology study a feverfew-containing cream re-analysed two years later had no detectable parthenolide left (Paulsen 2010).
Chemical reactivity is simultaneously the reason parthenolide does anything, the reason it can sensitise skin, and the reason it will not sit in a bottle indefinitely. Those three facts are one fact.
Serotonin and Platelets: The Original Mechanism
The first mechanistic work came in 1985, when researchers showed that feverfew extracts inhibit secretory activity in blood platelets and in polymorphonuclear leucocytes (a type of white blood cell) — published in The Lancet alongside the emerging clinical interest (Heptinstall 1985).
The details are more specific than the summary suggests:
- Release of serotonin (5-HT) from platelets was inhibited when triggered by ADP, adrenaline, sodium arachidonate, collagen and the thromboxane analogue U46619 — a broad range of triggers.
- Platelet aggregation was consistently inhibited, but thromboxane synthesis was not. That distinguishes feverfew from aspirin, which works by blocking thromboxane production.
- Release of vitamin B12-binding protein from white cells was also inhibited.
- Crucially, feverfew did not inhibit secretion triggered by the calcium ionophore A23187 — meaning it acts upstream of the final calcium-driven step, not on the machinery of secretion itself.
Follow-up work identified the likely mechanism as neutralisation of sulphydryl groups on platelet proteins (Heptinstall 1987; Heptinstall 1988) — exactly the Michael-acceptor chemistry described above, arrived at independently from the pharmacology side. A later comparison confirmed that parthenolide alone reproduces the antisecretory effect of whole feverfew extract on human platelets (Groenewegen 1990).
Why this was thought to matter for migraine: serotonin is central to migraine biology, platelets are a major reservoir of circulating serotonin, and one long-standing theory held that platelet serotonin release helps initiate attacks. Damping that release is a coherent idea.
It also has a practical consequence that has nothing to do with headaches. A small study in 1982 found altered platelet aggregation responses in people taking feverfew for migraine (Biggs 1982). Feverfew is mildly antiplatelet, which is why the safety advice about anticoagulants and surgery is not theoretical hand-waving — it comes straight from this mechanism.
NF-κB: The Inflammation Master Switch
The best-characterised molecular action of parthenolide has nothing specifically to do with migraine — it is general anti-inflammatory pharmacology.
NF-κB is a transcription factor that sits inactive in the cytoplasm, held there by an inhibitor protein called IκB. When a cell receives an inflammatory signal — tumor necrosis factor-α, bacterial products, oxidative stress — an enzyme complex called IκB kinase (IKK) tags IκB for destruction. NF-κB is released, moves into the nucleus, and switches on dozens of inflammatory genes: cytokines, adhesion molecules, cyclooxygenase-2 (COX-2), inducible nitric oxide synthase. It is the closest thing inflammation has to a master switch.
In 1999, a study showed that parthenolide inhibits NF-κB by targeting the IκB kinase complex — blocking the switch rather than the downstream genes (Hehner 1999). Two years later, a chemical-biology study went further and showed parthenolide binds directly to IKK, with the effect traced to a specific cysteine residue in the kinase — the covalent chemistry made concrete (Kwok 2001).
This is genuinely good science and it is the reason parthenolide appears in thousands of papers across immunology and oncology. What it does not do by itself is explain migraine. NF-κB inhibition is a plausible contributor to the “neurogenic inflammation” component of a migraine attack — the sterile inflammatory response around meningeal vessels — but no trial has connected the two in humans, and the concentrations used in these cell studies are far above anything a capsule produces (see bioavailability).
TRPA1 and the Trigeminal Nerve
The most migraine-specific mechanism is also the most recent, and it is worth understanding because it explains something the older theories do not.
Migraine pain is generated by the trigeminovascular system: branches of the trigeminal nerve that supply the meninges and their blood vessels. When these fibres fire, they release CGRP (calcitonin gene-related peptide), which dilates meningeal vessels and sensitises pain pathways. CGRP is now such an established migraine mechanism that an entire modern drug class — the gepants and the anti-CGRP antibodies — targets it.
Those trigeminal fibres carry TRPA1, an ion channel that detects chemical irritants. TRPA1 is the sensor for the pungency of mustard oil, garlic, cinnamaldehyde and formalin, and it is activated by reactive electrophiles — it works by having reactive cysteines in its structure. Several known migraine triggers, including cigarette smoke and certain environmental chemicals, are TRPA1 agonists.
Parthenolide is an electrophile. So what happens when it meets TRPA1?
A 2013 study in Pain answered this (Materazzi 2013). In transfected cells and in rat and mouse trigeminal neurons, parthenolide stimulates TRPA1 — but only as a partial agonist. After that initial stimulation it desensitises the channel and renders the peptidergic nerve terminals unresponsive to any subsequent stimulus. The consequences in rodents: nociceptive responses to trigeminal stimulation were abolished, CGRP release from trigeminal neurons was inhibited, and CGRP-mediated meningeal vasodilatation was blocked — whether it had been triggered by TRPA1 agonists or by unrelated stimuli.
The authors call this “nociceptor defunctionalisation.” It is the same pharmacological logic as capsaicin: a compound that first excites a nerve ending and then leaves it silent. It is an elegant explanation for how a daily preventive might blunt the trigger-to-attack pathway rather than block pain directly.
The honest caveats: this is rodent and cell work, not human. Concentrations in a dish are controlled in a way that oral dosing is not. And a partial agonist that first activates pain fibres raises an obvious question about the initial dose, which the study does not resolve in a human context.
Prostaglandins and Other Inflammatory Enzymes
Beyond NF-κB, feverfew extracts have been reported to inhibit a spread of inflammatory enzymes and mediators in laboratory systems: prostaglandin production, 5-lipoxygenase, phosphodiesterases 3 and 4, and the release of nitric oxide, PGE2 and tumor necrosis factor-α from macrophages (Sur 2009). One systematic review flagged feverfew's cyclooxygenase-2 inhibiting effects as a theoretical concern for very long-term use in people with coronary disease — a reasonable caution given what is known about selective cyclooxygenase-2 inhibition, though there is no clinical evidence of harm from feverfew specifically (Saranitzky 2009).
A 2020 study of a commercial feverfew water extract found anti-inflammatory and neuromodulatory activity in isolated tissue (Recinella 2020). In isolated mouse cortex the extract reduced PGE2 release and IL-1β gene expression and raised IL-10 and brain-derived neurotrophic factor (BDNF) gene expression; in rat hypothalamic cells it lowered extracellular dopamine and raised gene expression of the dopamine transporter (DAT). The authors identified parthenolide in the extract by mass spectrometry and linked the dopamine effect to “the direct interaction of parthenolide with the DAT”, writing that it “could be related, at least in part, to the presence of parthenolide in the extract”. The extract's effect on serotonin turnover in isolated cortex comes from the same authors' earlier study, which this paper cites. The result comes up again in the next section.
The Bioavailability Problem
Here is the finding that every discussion of feverfew's mechanism ought to include and almost none do.
In 2004, oncology researchers ran a phase I dose-escalation trial of feverfew in cancer patients, specifically to characterise parthenolide's pharmacokinetics — something that had never been done despite decades of use. Patients took a commercial feverfew tablet daily on a 28-day cycle, escalating from 1 mg to 2, 3 and 4 mg of parthenolide per day. Plasma parthenolide was measured by solid-phase extraction and mass spectrometry, with a detection limit of 0.5 ng/mL.
The result: at doses up to 4 mg daily there was no detectable parthenolide in plasma at all. The pharmacokinetic analysis could not be completed because there was nothing to measure. The authors concluded that purified parthenolide at higher doses would be needed for any therapeutic use (Curry 2004).
The trial also found no significant toxicity and never reached a maximum tolerated dose — useful safety information in its own right.
What to make of this. It is one small trial with one assay in cancer patients, and undetectable is not the same as absent: 0.5 ng/mL is a real but not extraordinary detection limit, and a compound can act locally — in the gut wall, on platelets in the portal circulation, on nerve endings — without reaching a measurable systemic concentration. A covalent binder can also do its work and disappear from plasma quickly, since it becomes attached to protein.
But it does place a hard constraint on the story. Cell studies of NF-κB inhibition typically use micromolar parthenolide. The gap between micromolar in a dish and undetectable in blood is several orders of magnitude. Any explanation of how a feverfew capsule prevents migraine has to work at concentrations far below the ones used to discover the mechanism. That does not make the mechanism wrong. It does mean the confident chain of reasoning — parthenolide blocks NF-κB, NF-κB drives neurogenic inflammation, therefore feverfew prevents migraine — has a missing link in the middle, and this page says so.
How Much of the Effect Comes From Parthenolide
The evidence points both ways, which matters for products standardised to parthenolide content.
For parthenolide being the active principle:
- The 1992 analytical study found that three physicochemical assays and a platelet bioassay gave consistent results, and concluded that “parthenolide appears to be mainly responsible for the antisecretory effects of extracts of feverfew” (Heptinstall 1992).
- Purified parthenolide reproduces whole-extract effects on platelets (Groenewegen 1990).
- It has a defined molecular target in IKK (Hehner 1999; Kwok 2001) and a defined action on trigeminal TRPA1 (Materazzi 2013).
Against parthenolide being the whole story:
- A parthenolide-depleted feverfew extract, developed specifically to remove the skin sensitiser, retained substantial anti-inflammatory activity: it inhibited 5-lipoxygenase, phosphodiesterase-3 and -4, and the release of nitric oxide, PGE2, tumor necrosis factor-α, IL-2, IFN-γ and IL-4, and reduced dermatitis in animal models. Notably it did not inhibit tumor necrosis factor-induced NF-κB activity — confirming the depletion had worked — yet was still active by other routes, and in one model was more potent than whole feverfew. The same paper reports that its efficacy was “confirmed clinically by a reduction in erythema in a methyl nicotinate-induced vasodilation model” — less skin redness in a human test (Sur 2009).
- The 2020 water-extract study does not separate parthenolide from the rest of the plant: the authors identified parthenolide in the extract and linked part of its dopamine effect to it (Recinella 2020).
- Feverfew contains dozens of other sesquiterpene lactones plus flavonoids and essential-oil components, few of which have been tested individually.
- Oral parthenolide is undetectable in plasma (Curry 2004), which sits awkwardly with it being the sole mediator of a systemic effect.
Depletion did not remove all allergy risk. Seven feverfew-allergic patients were patch-tested with two creams containing the parthenolide-depleted extract. “Four of the patients tested positive to one of the creams”, and those reactions went with positive reactions to parthenolide itself (Paulsen 2010).
The practical reading: parthenolide is the best available quality marker — it tells you the material is real feverfew, harvested from the right plant parts, not degraded by age or heat, and processed in a way that preserves chemistry. That has real value as a quality check. It is a weaker claim to say a stated parthenolide percentage guarantees clinical effect. Standardisation works as a proxy for manufacturing care, not as a guarantee of efficacy.
How Well Each Mechanism Fits Migraine
Scoring each mechanism against what we know about migraine:
| Mechanism | Evidence level | Fit with migraine biology |
|---|---|---|
| TRPA1 partial agonism then desensitisation, blocking CGRP release | Rodent and cell (Materazzi 2013) | Strong. Targets the exact nerve population and the exact peptide that modern migraine drugs target |
| Inhibition of platelet serotonin release | Human platelets ex vivo (Heptinstall 1985; Groenewegen 1990) | Moderate. Serotonin matters in migraine, but the platelet-serotonin theory of attack initiation has weakened over time |
| NF-κB / IKK inhibition | Cell culture (Hehner 1999; Kwok 2001) | Moderate. Neurogenic inflammation is real, but the concentrations used are far above plausible in vivo levels |
| Prostaglandin, 5-LOX and PDE inhibition | Cell and animal (Sur 2009) | Weak and non-specific. Would predict acute analgesia, which feverfew does not reliably show |
| Antiplatelet / anti-aggregation | Human, including in feverfew users (Biggs 1982) | Weak for benefit — but the best-supported mechanism for a side effect |
The TRPA1 work is the most satisfying because it explains the clinical shape of feverfew's use. A defunctionalising agent would need repeated daily dosing to keep nerve terminals quiet, would prevent attacks rather than abort them, would take weeks to show its full effect, and might produce a rebound when withdrawn as nerve terminals recover their sensitivity. That is precisely how feverfew behaves clinically, including the withdrawal reaction. It is a hypothesis rather than a proof, but it is an unusually good one.
What the pooled trials show. A 2025 meta-analysis of nine double-masked, placebo-controlled trials with 899 participants found feverfew reduced migraine attack frequency (effect estimate −1.11, p < 0.00001) and migraine duration (p = 0.007), with only “a non-significant trend towards reduced pain severity” (p = 0.14) and no significant effect on nausea, vomiting, light sensitivity (photophobia) or sound sensitivity (phonophobia). The authors note that heterogeneity and risks of selection and attrition bias limited the quality of the evidence (Nelaturi 2025). Fewer attacks with no clear effect on pain severity is the pattern the table predicts: a preventive mechanism working, and the non-specific painkilling routes contributing little.
Parthenolide with salicin, in rats. A 2026 rat study combined low doses of parthenolide (2.5 mg/kg) with salicin (5 mg/kg) — salicin is the main active component of white willow, not of feverfew — in a migraine model made by applying an inflammatory mixture to the dura (the membrane around the brain). A single dose of the combination prevented acute head hypersensitivity only in females; given daily, it prevented chronic head hypersensitivity and the rise in calcitonin gene-related peptide (CGRP) in the trigeminocervical complex in both sexes (Shrivastava 2026). This is rodent work only.
Parthenolide Outside Feverfew
Parthenolide has a substantial research life that has nothing to do with headaches, and it needs a clear boundary drawn around it, because the abstracts are exciting and the clinical reality is not.
Because NF-κB keeps cancer cells alive under stress, parthenolide attracted attention as an anti-cancer agent, particularly against leukaemia stem cells, which appear unusually dependent on NF-κB. Laboratory results have been striking, and a large literature has followed.
The clinical reality is the phase I trial described above: feverfew tablets delivering up to 4 mg of parthenolide daily produced no detectable plasma level, so the pharmacokinetic study could not even be completed (Curry 2004). Work since has focused on synthetic, water-soluble analogues such as dimethylamino-parthenolide, which is a different molecule, not something you can buy.
Feverfew is not a cancer treatment, and no responsible reading of this literature suggests otherwise. During cancer treatment, feverfew's antiplatelet activity (in the 1985 study, “Platelet aggregation was consistently inhibited”) matters when platelet counts are low (thrombocytopenia) and around surgery, and none of the studies cited here tested feverfew together with chemotherapy.
What Would Actually Settle This
Three studies, none of them done:
- A proper pharmacokinetic study with a modern assay at doses people actually take, ideally measuring parthenolide-protein adducts rather than free parthenolide — a covalent binder may simply be invisible to a free-drug assay.
- A head-to-head trial of standardised versus non-standardised feverfew in the same population. If product variability is the explanation for the mixed trial results, this settles it directly. If both arms perform identically, the standardisation story collapses.
- A CGRP-linked human study — measuring whether feverfew or parthenolide affects CGRP release or trigeminal sensitisation in people, which would test the TRPA1 hypothesis where it counts.
Until then, feverfew's mechanism is a well-supported hypothesis with a documented gap between the concentrations that produce the effects in the laboratory and the concentrations a capsule delivers.
What the Mechanism Implies for Safety
The pharmacology predicts the safety profile rather neatly, which is a point in its favour:
- Antiplatelet effect → bleeding caution. Documented in human platelets (“Platelet aggregation was consistently inhibited”, Heptinstall 1985) and in feverfew users. The concern applies alongside warfarin, aspirin, clopidogrel and direct oral anticoagulants (DOACs), and around surgery.
- Covalent protein binding → contact allergy. Parthenolide is a recognised Compositae sensitiser; cross-reactivity with ragweed, chrysanthemum, marigold and chamomile is expected, not surprising.
- Chemical reactivity → mucosal irritation. The mouth ulcers associated with chewing fresh leaves are the local version of the same chemistry.
- Nerve defunctionalisation → rebound on withdrawal. A plausible mechanistic account of post-feverfew syndrome, covered in Side Effects and Post-Feverfew Syndrome.
- Reactive electrophile → pregnancy concern. The only experimental reproductive screen, in rats dosed with 839 mg/kg feverfew daily, found that fetuses exposed on gestation days 8–15 “were smaller than ethanol controls”, and feverfew was toxic to embryos in culture; the authors concluded that a comprehensive reproductive study “is warranted” (Yao 2006). Feverfew is traditionally contraindicated in pregnancy.
Key Research Papers
Every identifier was verified live against NCBI E-utilities before being written here.
Platelets, serotonin and the sulphydryl mechanism
- Heptinstall S, White A, Williamson L, Mitchell JR. Extracts of feverfew inhibit granule secretion in blood platelets and polymorphonuclear leucocytes. The Lancet. 1985;1(8437):1071–1074. — PubMed PMID: 2860288
- Heptinstall S, Groenewegen WA, Spangenberg P, Lösche W. Extracts of feverfew may inhibit platelet behaviour via neutralization of sulphydryl groups. Journal of Pharmacy and Pharmacology. 1987;39(6):459–465. — PubMed PMID: 2886604
- Heptinstall S, Groenewegen WA, Spangenberg P, Lösche W. Inhibition of platelet behaviour by feverfew: a mechanism of action involving sulphydryl groups. Folia Haematologica. 1988;115(4):447–449. — PubMed PMID: 2465950
- Groenewegen WA, Heptinstall S. A comparison of the effects of an extract of feverfew and parthenolide, a component of feverfew, on human platelet activity in-vitro. Journal of Pharmacy and Pharmacology. 1990;42(8):553–557. — PubMed PMID: 1981582
- Biggs MJ, Johnson ES, Persaud NP, Ratcliffe DM. Platelet aggregation in patients using feverfew for migraine. The Lancet. 1982;2(8301):776. — PubMed PMID: 6125851
NF-κB and inflammatory signalling
- Hehner SP, Hofmann TG, Dröge W, Schmitz ML. The antiinflammatory sesquiterpene lactone parthenolide inhibits NF-κB by targeting the IκB kinase complex. The Journal of Immunology. 1999;163(10):5617–5623. — PubMed PMID: 10553091
- Kwok BH, Koh B, Ndubuisi MI, Elofsson M, Crews CM. The anti-inflammatory natural product parthenolide from the medicinal herb feverfew directly binds to and inhibits IκB kinase. Chemistry & Biology. 2001;8(8):759–766. — PubMed PMID: 11514225
- Sur R, Martin K, Liebel F, Lyte P, Shapiro S, Southall M. Anti-inflammatory activity of parthenolide-depleted feverfew (Tanacetum parthenium). Inflammopharmacology. 2009;17(1):42–49 — PubMed PMID: 19112586 — The study showing activity survives removal of parthenolide.
- Recinella L, Chiavaroli A, di Giacomo V, et al. Anti-inflammatory and neuromodulatory effects induced by Tanacetum parthenium water extract: results from in silico, in vitro and ex vivo studies. Molecules. 2020;26(1). — PubMed PMID: 33374525
Trigeminal nerves, TRPA1 and CGRP
- Materazzi S, Benemei S, Fusi C, et al. Parthenolide inhibits nociception and neurogenic vasodilatation in the trigeminovascular system by targeting the TRPA1 channel. Pain. 2013;154(12):2750–2758 — PubMed PMID: 23933184 — The central modern mechanism paper — rodent and cell work.
- Shrivastava R, Ginisty A, Da Silva Borges G, Descheemaeker A, Dallel R, Monconduit L. Association of parthenolide and salicin as a preventive treatment on a migraine model induced by dural inflammatory soup application. Pain. 2026;167(2):297–307 — PubMed PMID: 41512309 — Rodent work.
Pharmacokinetics, chemistry and quality
- Curry EA 3rd, Murry DJ, Yoder C, et al. Phase I dose escalation trial of feverfew with standardized doses of parthenolide in patients with cancer. Investigational New Drugs. 2004;22(3):299–305 — PubMed PMID: 15122077 — No detectable plasma parthenolide at up to 4 mg/day.
- Heptinstall S, Awang DV, Dawson BA, Kindack D, Knight DW, May J. Parthenolide content and bioactivity of feverfew: estimation of commercial and authenticated feverfew products. Journal of Pharmacy and Pharmacology. 1992;44(5):391–395. — PubMed PMID: 1359053
- Jin P, Madieh S, Augsburger LL. Selected physical and chemical properties of feverfew (Tanacetum parthenium) extracts important for formulated product quality and performance. AAPS PharmSciTech. 2008;9(1):22–30. — PubMed PMID: 18446457
- Brown AM, Edwards CM, Davey MR, Power JB, Lowe KC. Pharmacological activity of feverfew (Tanacetum parthenium (L.) Schultz-Bip.): assessment by inhibition of human polymorphonuclear leukocyte chemiluminescence in-vitro. Journal of Pharmacy and Pharmacology. 1997;49(5):558–561. — PubMed PMID: 9178194
Allergy, reproduction and reviews
- Paulsen E, Christensen LP, Fretté XC, Andersen KE. Patch test reactivity to feverfew-containing creams in feverfew-allergic patients. Contact Dermatitis. 2010;63(3):146–150 — PubMed PMID: 20690937 — Also documents parthenolide degradation over two years.
- Yao M, Ritchie HE, Brown-Woodman PD. A reproductive screening test of feverfew: is a full reproductive study warranted? Reproductive Toxicology. 2006;22(4):688–693. — PubMed PMID: 16781113
- Saranitzky E, White CM, Baker EL, Baker WL, Coleman CI. Feverfew for migraine prophylaxis: a systematic review. Journal of Dietary Supplements. 2009;6(2):91–103 — PubMed PMID: 22435410 — Raises the COX-2 inhibition concern for long-term use.
- Nelaturi V, Viswanatha GL, Shenoy RR, Khanna S, Krishnadas N. Systematic review and meta-analysis of Tanacetum parthenium: evaluating its efficacy in migraine relief. Natural Product Research. 2025:1–8 — PubMed PMID: 41422534 — Nine trials, 899 participants.
- Pareek A, Suthar M, Rathore GS, Bansal V. Feverfew (Tanacetum parthenium L.): a systematic review. Pharmacognosy Reviews. 2011;5(9):103–110. — PubMed PMID: 22096324
PubMed Topic Searches
- PubMed: Parthenolide mechanism of action
- PubMed: Parthenolide, NF-κB and IKK
- PubMed: TRPA1, CGRP and trigeminal migraine
- PubMed: Sesquiterpene lactones as Michael acceptors
- PubMed: Parthenolide pharmacokinetics
- PubMed: DMAPT, the soluble parthenolide analogue
- PubMed: Feverfew and platelet serotonin release
- PubMed: Neurogenic inflammation in migraine
Connections
- All Herbs
- Feverfew Benefits — hub
- Migraine Prevention — what the trials found
- Choosing a Product and Dosing
- Side Effects and Post-Feverfew Syndrome
- Feverfew — the main herb page
- Migraine
- Neurology
- Butterbur — isopetasin acts on the same TRPA1 pathway
- Chamomile — another Asteraceae herb with sesquiterpene chemistry