Migraine Prevention
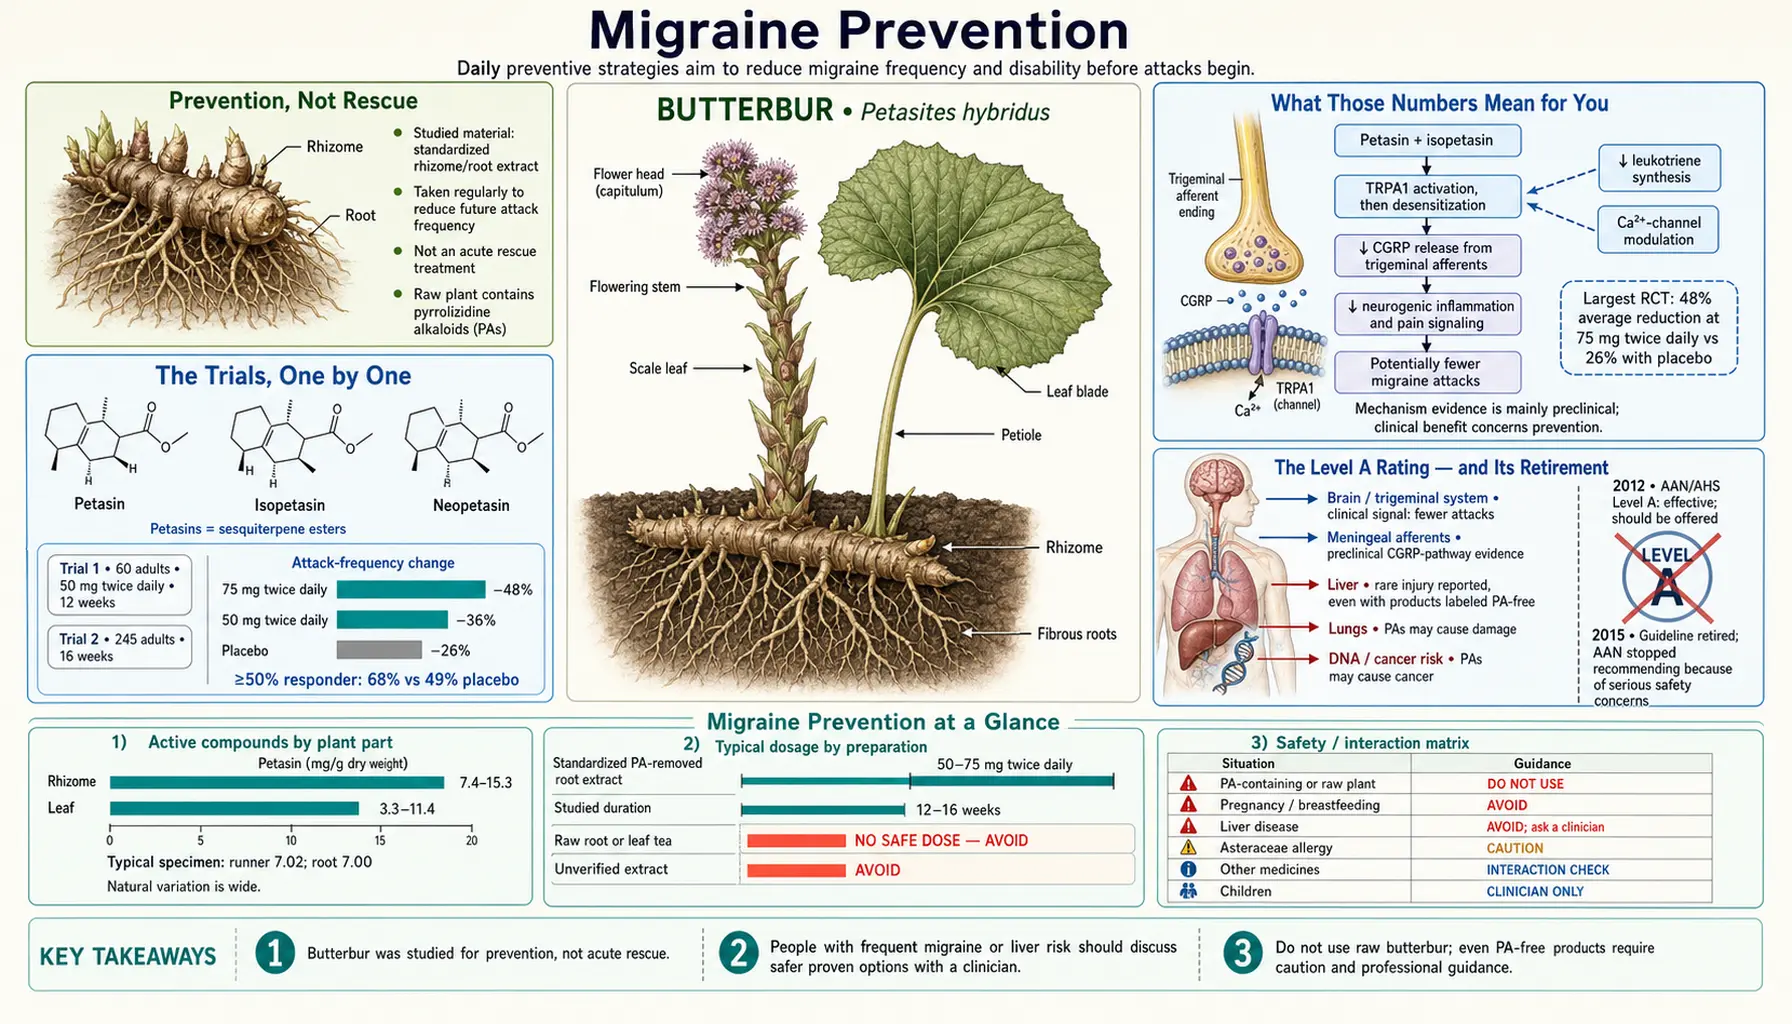
If you have migraine, you have probably been handed a list of “natural” suggestions with no evidence behind any of them. Butterbur is different, and it is worth knowing exactly how different. A standardised extract of Petasites hybridus root has been tested in randomised, placebo-controlled trials, cut attack frequency by roughly half at the effective dose, and in 2012 was rated Level A — established as effective by the American Academy of Neurology. No other herb has ever achieved that.
And then that rating was withdrawn. Not because the trials collapsed, but because butterbur’s raw material contains liver-toxic pyrrolizidine alkaloids and nobody could guarantee that a given bottle was free of them. This article gives you the efficacy data in full, the withdrawal story in full, and the practical consequences of both.
Table of Contents
- Prevention, Not Rescue
- The Trials, One by One
- What Those Numbers Mean for You
- The Level A Rating — and Its Retirement
- How Petasin Might Prevent a Migraine
- Children and Adolescents: How Weak the Evidence Is
- Dose, Timing and How Long
- What Butterbur Is Competing Against
- Cautions, Interactions and Who the Research Raises Concerns For
- The Honest Verdict
- Key Research Papers
- Connections
- Featured Videos
Prevention, Not Rescue
The single most common misunderstanding about butterbur is what it is for. Butterbur is a preventive — a daily medicine taken whether or not you have a headache, with the goal of having fewer attacks over the following months. It is not a rescue treatment. Taking a butterbur capsule at the first flicker of aura will do nothing useful; it takes weeks to build an effect, and the trials measured attacks per month, not relief per attack.
That distinction shapes everything else on this page. A preventive has to be worth taking every day for months, which means the safety bar is much higher than for something you swallow six times a year. A drug you take twice a month can get away with a small risk. A capsule you take twice a day for four months cannot. That is the reason this herb ended up where it did.
Migraine prevention is usually considered when attacks are frequent enough to disrupt life — commonly four or more headache days a month, or fewer if attacks are severe or acute treatments are failing. The realistic goal is not zero attacks. A conventionally successful preventive halves attack frequency in about half the people who try it, and that is genuinely life-changing when your baseline is eight migraine days a month.
The Trials, One by One
There are three placebo-controlled publications in adults, and it matters that they are not three independent trials.
1. Grossmann and Schmidramsl, 2000 — the first placebo-controlled trial
Published in the International Journal of Clinical Pharmacology and Therapeutics, this was a randomised, placebo-controlled study of the standardised root extract at 50 mg twice daily for 12 weeks. It enrolled 60 patients, each taking two 25 mg capsules twice daily after a four-week run-in. Attack frequency fell by up to 60% from baseline, significantly more than on placebo, and no adverse events were reported in that time frame. It is a small, early trial, and it set the direction rather than settling the question.
2. Diener, Rahlfs and Danesch, 2004 — a reanalysis, not a second trial
This paper in European Neurology is frequently miscounted as an independent replication. It is not. It is a reanalysis of the same 2000 dataset using different efficacy criteria, confirming the original conclusion on the reworked endpoints. A reanalysis of an existing trial adds interpretive confidence, not new evidence. Anyone counting “three positive trials” is really counting two.
3. Lipton and colleagues, 2004 — the pivotal trial
This is the study that carried butterbur into the guidelines. Published in Neurology, it randomised 245 people with migraine to one of three arms for four months: the standardised extract at 75 mg twice daily, the same extract at 50 mg twice daily, or placebo.
- At 75 mg twice daily, migraine attack frequency fell by about 48% from baseline (per-protocol analysis, p = 0.0012 against placebo).
- On placebo, attack frequency fell by about 26%.
- The 50 mg twice daily arm fell by about 36%, which did not separate significantly from placebo (p = 0.127) — an important detail, because 50 mg twice daily is a dose some products still sell.
- After four months, 68% of people on 75 mg twice daily had their attacks at least halved, against 49% on placebo. The commonest side effects were mild stomach and gut complaints, mainly burping.
The trial was double-blind and placebo-controlled, which is the right design, and 245 participants is a respectable size for a preventive trial. Two caveats belong alongside the result. First, all of this evidence concerns one proprietary extract; it is manufacturer evidence, and several of the pivotal papers were co-authored by people connected to that manufacturer. That is common in botanical research and is not by itself disqualifying, but it is part of the record. Second, there has been no large independent replication in the two decades since — and the reason is not scientific indifference, it is that the safety controversy stopped the research programme.
The systematic review
Agosti and colleagues reviewed the randomised evidence in Phytomedicine in 2006. They found two trials (60 and 233 patients), both using the same proprietary root extract, and judged that there was moderate evidence of effectiveness for the higher dose only (150 mg a day). They added that further rigorous studies were needed to confirm effectiveness and safety in long-term use before the extract could be recommended as an option for migraine prevention. That is a fair summary: consistent, but narrow.
A 2026 real-world study
A 2026 study from a single headache centre looked back at the records of 120 consecutive adults (72 with episodic and 48 with chronic migraine) given a butterbur root extract free of pyrrolizidine alkaloids. After 12 weeks, headache days fell from 6.0 to 2.6 a month in episodic migraine and from 26.3 to 12.7 a month in chronic migraine, and 59.2% of patients had their headache attacks cut by more than half. Side effects were reported by 28.3% — a bitter taste in the mouth and/or burping, lasting 2 to 14 days. The study had no placebo group, so it cannot show how much of the improvement came from the extract itself.
What Those Numbers Mean for You
“48% versus 26%” is easy to quote and easy to misread. Here is the plain-language translation.
Suppose you start with eight migraine days a month. Over four months of the trial:
- On placebo, you would expect to drop to about six migraine days.
- On butterbur at 75 mg twice daily, you would expect to drop to about four.
The net gain attributable to the herb is therefore about two migraine days a month — roughly one working week of migraine recovered per year. That is a real, meaningful benefit, and it is also considerably less impressive than “cuts migraines in half” makes it sound. Note how much of the improvement is the placebo arm: 26% of people got better on a dummy capsule. Migraine fluctuates, people enrol in trials when they are having a bad spell, and things drift back toward average on their own. This is precisely why uncontrolled studies of migraine treatments are worthless, and why the paediatric butterbur data (below) do not carry weight.
For context, that effect size is broadly in the same territory as riboflavin, magnesium and coenzyme Q10, and somewhat below the modern prescription preventives. Butterbur was not a miracle. It was a decent preventive with an unusually good evidence base for a plant.
The Level A Rating — and Its Retirement
In April 2012, the American Academy of Neurology and the American Headache Society published an evidence-based guideline update on nonsteroidal anti-inflammatory drugs (NSAIDs) and complementary treatments for episodic migraine prevention. Petasites was assigned Level A: established as effective, and appropriate to offer to patients. Riboflavin, magnesium and feverfew came in at Level B. Butterbur stood alone at the top of the botanical list.
That guideline has since been retired. The published record now carries a “[RETIRED]” designation, and in 2015 the Academy acted to ensure clinicians and patients were aware of the hepatotoxicity concern attached to butterbur products.
The reason matters enormously, so let us be precise about it:
- No trial was retracted. The Lipton data still say what they said.
- No new negative trial appeared. There was no failed replication that pulled the rug out.
- What accumulated instead were reports of liver injury in people taking commercial butterbur, regulatory restrictions abroad, and a growing recognition that in the United States nobody checks before sale whether a given bottle actually contains the alkaloids it claims not to.
A guideline recommendation is a bet that a named intervention, obtained normally by a normal patient, will do more good than harm. Butterbur’s efficacy side of that bet held. The “obtained normally by a normal patient” side did not. That is the honest reason a Level A rating disappeared, and it is a manufacturing failure much more than a scientific one.
You will find websites that still cite the Level A rating without mentioning the retirement, and others that treat the retirement as proof butterbur never worked. Both leave out half of the record.
The US National Center for Complementary and Integrative Health (NCCIH) states that the American Academy of Neurology stopped recommending butterbur in 2015 “because of serious concerns about its safety.” It also states that several studies, including studies of children and adolescents, reported that butterbur products free of pyrrolizidine alkaloids (PA-free) seem to be safe by mouth for up to 16 weeks, but that there have been rare cases of liver injury with products that were reported to be PA-free.
A 2025 review of supplements for headache reached the same split verdict a decade after the retirement: butterbur preparations “have strong evidence for efficacy and concern for hepatotoxicity” (liver toxicity), and the review points readers to the NCCIH butterbur page for current guidance.
How Petasin Might Prevent a Migraine
Butterbur’s active constituents are sesquiterpene esters: petasin, isopetasin and oxopetasin. Standardised extracts are labelled by petasin content. Two mechanisms are proposed for the migraine effect, and both come from the laboratory rather than from people.
Calcium-channel blockade
S-petasin inhibited L-type calcium current in a neuronal cell line. Calcium entry through these channels is what triggers neurotransmitter release and smooth-muscle contraction; blocking them relaxes vessels and quiets excitable neurons. Prescription calcium-channel blockers such as flunarizine and verapamil are used for migraine prevention in some countries, so the analogy is not far-fetched. Two honest caveats: the study used a compound from the related species Petasites formosanus, and it used a neuroblastoma–glioma hybrid cell line, not human neurons.
Leukotriene inhibition and neurogenic inflammation
Petasin suppresses leukotriene production in human inflammatory cells. Migraine involves sterile neurogenic inflammation around the trigeminal nerve endings and meningeal vessels, so an anti-inflammatory action on that pathway is a plausible contributor. A 2022 narrative review, which includes its authors’ own new laboratory data, reports that petasins desensitise the TRPA1 and TRPV1 pain channels on sensory nerves and block the release of calcitonin gene-related peptide (CGRP) from the nerves of the brain’s coverings (the meninges) during migraine attacks — CGRP is the same messenger that several modern migraine drugs target. The same review reports that in rats no adverse effect was seen at 15 times the maximum human dose, while bile-duct overgrowth appeared at 45 to 90 times that dose. These are laboratory and animal findings, not results in people.
All of this is hypothesis. It is genuinely useful to know that butterbur has a mechanism that could work, because a plausible mechanism makes a clinical result less likely to be a fluke. But no one has demonstrated that petasin prevents migraine in humans by either route. The trials, not the mechanism, are the reason anyone takes this herb.
Children and Adolescents: How Weak the Evidence Is
Paediatric migraine is common, disruptive and under-treated, so it is unsurprising that butterbur was tried in children. The results are weak, and the safety concern is greater.
- Pothmann and Danesch, 2005 — an open study of 108 children and adolescents given the butterbur extract over four months, reporting a large proportion with a substantial fall in attack frequency. There was no control group. In paediatric migraine, placebo response rates are famously enormous — often more than half of children improve markedly on a dummy capsule. An uncontrolled paediatric migraine study cannot distinguish a working drug from a working ritual.
- Oelkers-Ax and colleagues, 2008 — a small explorative randomised study in 58 primary-school children given butterbur root extract (19 children), music therapy (20) or a placebo (19) for 12 weeks, all on top of headache education. Right after treatment, only music therapy beat placebo (p = 0.005); at the six-month follow-up, both music therapy and butterbur did (p = 0.018 and p = 0.044). All three groups had already improved a lot during the eight-week baseline period, before any treatment began. The authors themselves framed it as explorative, and it is too small to settle anything.
- Utterback and colleagues, 2014 — a retrospective chart review, not a trial. Chart reviews describe what happened to people who were already given a treatment; they cannot control for who was selected to receive it or what else changed.
So: one uncontrolled study, one small explorative trial, one chart review. That is not an evidence base. Set against it is the fact that pyrrolizidine alkaloids are cumulative liver toxins and probable carcinogens, and a child has decades of life left for a genotoxic exposure to matter. The research therefore raises a particular concern for children. The other approaches used for children’s migraine — sleep regularity, hydration, trigger identification, magnesium, riboflavin, and prescription options — do not carry this alkaloid risk, although a 2025 review notes that riboflavin’s benefit has not been proven in children.
Dose, Timing and How Long
These are the regimens the research actually used; the safety article covers the liver risk in full. This is information, not a recommendation.
| Element | What the trials used | Notes |
|---|---|---|
| Preparation | A standardised CO2 extract of the rhizome, certified free of pyrrolizidine alkaloids | Nothing else has been tested. Raw root, leaf tea and tinctures are not this |
| Effective dose | 75 mg twice daily (150 mg/day) | The dose that separated from placebo in the 2004 trial |
| Lower dose | 50 mg twice daily | Used in the 2000 trial; did not clearly beat placebo in the 2004 three-arm study |
| Time to effect | Weeks, not days | Trials measured over 12–16 weeks. Judging it after a fortnight is meaningless |
| Trial duration | 3–4 months | There is no long-term safety data beyond this. Open-ended daily use has never been studied |
| Monitoring | Not standardised in the trials | The trials set no liver-test schedule; the liver-injury reports came later |
Points that follow from that table. Mild stomach upset and burping are the commonest side effects reported in the trials. The trials counted attacks against a baseline recorded before treatment (a headache diary); without a baseline, memory is unreliable about pain. The trials judged the effect over three to four months at 75 mg twice daily; where there is no meaningful reduction in migraine days by then, longer use adds exposure with no measured return.
The duration limit matters. The evidence covers roughly four months, and NCCIH describes PA-free products as seeming safe by mouth for up to 16 weeks. Beyond that you are in territory where neither the benefit nor the cumulative liver exposure has been characterised.
What Butterbur Is Competing Against
Butterbur does not exist in a vacuum. For migraine prevention, several options have comparable evidence and a much cleaner safety record. Set side by side, the options differ far more in safety than in evidence.
| Option | Evidence | Safety profile |
|---|---|---|
| Magnesium | Multiple randomised trials; a standard guideline option | Very good. Loose stools at higher doses; caution in kidney disease |
| Riboflavin (vitamin B2) | Randomised trials at high dose (typically 400 mg/day) | Excellent. Turns urine bright yellow, which is harmless |
| Coenzyme Q10 | Small randomised trials | Good. Expensive relative to benefit |
| Feverfew | Mixed randomised evidence; guideline Level B | Moderate. Mouth ulcers, rebound on stopping, same Asteraceae allergy issue, a concern in pregnancy |
| Butterbur | Randomised placebo-controlled trials; formerly Level A | The problem. Liver toxicity risk; guideline rating retired |
| Prescription preventives | Large trials; the strongest evidence available | Variable and well-characterised, with a prescriber monitoring you |
Common migraine triggers — sleep, hydration, meal regularity, caffeine and medication-overuse headache — sit outside this table. Butterbur’s trial evidence comes from a certified PA-free extract used for a defined three-to-four month period, and its guideline rating was withdrawn over the liver risk.
Cautions, Interactions and Who the Research Raises Concerns For
The full account is in Pyrrolizidine Alkaloids and Liver Safety. This is the migraine-specific short version.
Groups for whom the research raises the strongest concern
- Pregnancy and breastfeeding. Pyrrolizidine alkaloids cross the placenta and appear in breast milk. Liver injury in an infant from PA-containing herbal tea is documented. Migraine often improves in pregnancy anyway. NCCIH states that butterbur products containing pyrrolizidine alkaloids may cause birth defects or liver damage, and that little is known about the safety of PA-free products in pregnancy or breastfeeding.
- Children and adolescents, for the reasons set out above.
- Any existing liver disease — hepatitis, fatty liver disease, cirrhosis, prior drug-induced liver injury.
- Any product that is not certified PA-free. NCCIH states: “Only butterbur products that have been processed to remove PAs and are labeled or certified as PA-free should be considered for use” — and that rare liver injury has been reported even with products reported to be PA-free.
Interactions and cautions
- Other liver-loading medicines. Methotrexate, isoniazid, amiodarone, high or frequent paracetamol/acetaminophen, and regular alcohol all add to the same burden. So do other herbal products — and comfrey, borage and coltsfoot contain pyrrolizidine alkaloids of their own, so the exposures stack.
- Blood-pressure medicines and calcium-channel blockers. Petasin’s calcium-channel activity is a theoretical reason for additive blood-pressure lowering. Lightheadedness would be the expected sign of additive lowering in people taking blood-pressure medicines (antihypertensives).
- Asteraceae (daisy family) allergy. People who react to ragweed, chrysanthemum, marigold, chamomile, echinacea or feverfew may also react to butterbur (cross-reactivity).
- Common side effects are gastrointestinal: burping (distinctly and unpleasantly of butterbur), nausea, stomach upset, sometimes headache or drowsiness.
Signs of liver injury
Yellowing of the skin or the whites of the eyes, unusually dark urine, pale stools, persistent nausea or vomiting, pain under the right ribs, unexplained itching, or profound fatigue. These are signs of liver injury, which hospitals treat as urgent.
The Honest Verdict
Butterbur for migraine prevention is a real treatment with a real problem, and the temptation is to resolve the tension by picking a side. The record supports neither side alone.
- It works, modestly. A standardised extract at 75 mg twice daily beat placebo in a properly designed 245-person trial, cutting attack frequency by about 48% against 26%. Very few botanicals have anything comparable.
- The evidence is narrower than it looks. Two independent placebo-controlled datasets, one proprietary extract, manufacturer involvement, no large independent replication, and a lower dose that did not work.
- The safety liability is genuine and it is about manufacturing. The plant contains hepatotoxic, genotoxic alkaloids; liver injuries have been reported with commercial products; regulators restricted them; the Level A rating was retired over exactly this.
- What the research used: a certified PA-free standardised extract, 75 mg twice daily, for a defined three-to-four month period, with attacks counted against a baseline headache diary. No trial tested longer use, and the research raises the strongest concern in pregnancy, breastfeeding, childhood and liver disease.
The net gain in the main trial was about two fewer migraine days a month, and the American Academy of Neurology stopped recommending butterbur in 2015 because of serious concerns about its safety. Magnesium and riboflavin, the other options in the table, carry a much cleaner safety record.
Key Research Papers
Each identifier below was checked live against the NCBI PubMed database — title, first author, journal and year all had to match before it was published here. Study type is stated for every entry.
The placebo-controlled trials
- Lipton RB, Göbel H, Einhäupl KM, Wilks K, Mauskop A. Petasites hybridus root (butterbur) is an effective preventive treatment for migraine. Neurology. 2004;63(12):2240–2244 — PubMed PMID: 15623680 — Randomised, double-blind, placebo-controlled human trial; 245 participants; three arms; 75 mg twice daily reduced attack frequency about 48% versus 26% on placebo, while 50 mg twice daily did not clearly separate.
- Grossmann M, Schmidramsl H. An extract of Petasites hybridus is effective in the prophylaxis of migraine. International Journal of Clinical Pharmacology and Therapeutics. 2000;38(9):430–435 — PubMed PMID: 11020030 — The first randomised placebo-controlled trial, at 50 mg twice daily over 12 weeks.
- Diener HC, Rahlfs VW, Danesch U. The first placebo-controlled trial of a special butterbur root extract for the prevention of migraine: reanalysis of efficacy criteria. European Neurology. 2004;51(2):89–97 — PubMed PMID: 14752215 — A reanalysis of the 2000 dataset — not an independent replication.
- Agosti R, Duke RK, Chrubasik JE, Chrubasik S. Effectiveness of Petasites hybridus preparations in the prophylaxis of migraine: a systematic review. Phytomedicine. 2006;13(9–10):743–746 — PubMed PMID: 16987643 — Systematic review of two trials; moderate evidence at the higher dose only, with longer safety studies called for; both trials used one proprietary extract.
- Silva-Néto RP. Efficacy of Petasites hybridus in migraine prophylaxis: the first real-world study. Frontiers in Neurology. 2026;17:1784624 — PubMed PMID: 41908273 — Retrospective, uncontrolled, single-centre study of 120 adults; no placebo group.
Guidelines and the safety reassessment
- Holland S, Silberstein SD, Freitag F, Dodick DW, Argoff C, Ashman E. Evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention in adults. Neurology. 2012;78(17):1346–1353 — PubMed PMID: 22529203 — The AAN/AHS guideline that rated Petasites Level A; the published record now carries a [RETIRED] designation.
- Sutherland A, Sweet BV. Butterbur: an alternative therapy for migraine prevention. American Journal of Health-System Pharmacy. 2010;67(9):705–711 — PubMed PMID: 20410544 — Pharmacy review weighing the efficacy data against the alkaloid problem.
- Borlak J, Diener HC, Kleeberg-Hartmann J, Messlinger K, Silberstein S. Petasites for migraine prevention: new data on mode of action, pharmacology and safety. A narrative review. Frontiers in Neurology. 2022;13:864689 — PubMed PMID: 35585841 — Narrative review arguing the hepatic signal has been overstated; a minority position worth reading against the regulatory record.
- Anderson N, Borlak J. Hepatobiliary events in migraine therapy with herbs — the case of Petadolex, a Petasites hybridus extract. Journal of Clinical Medicine. 2019;8(5) — PubMed PMID: 31083451 — Detailed analysis of the reported liver events with the standardised migraine extract.
- Tepper SJ, Tepper K. Nutraceuticals and Headache 2024: Riboflavin, Coenzyme Q10, Feverfew, Magnesium, Melatonin, and Butterbur. Current Pain and Headache Reports. 2025;29(1):33 — PubMed PMID: 39853578 — Review: butterbur has strong evidence for efficacy and a concern for liver toxicity.
- National Center for Complementary and Integrative Health (NIH). Butterbur. Last updated November 2024 — nccih.nih.gov/health/butterbur — US government fact sheet: the 2015 withdrawal of the neurology recommendation, PA-free products and rare liver injury.
Children and adolescents — the weaker evidence
- Pothmann R, Danesch U. Migraine prevention in children and adolescents: results of an open study with a special butterbur root extract. Headache. 2005;45(3):196–203 — PubMed PMID: 15836592 — Open, uncontrolled study in 108 young people — no placebo arm, and paediatric migraine has a very large placebo response.
- Oelkers-Ax R, Leins A, Parzer P, et al. Butterbur root extract and music therapy in the prevention of childhood migraine: an explorative study. European Journal of Pain. 2008;12(3):301–313 — PubMed PMID: 17659990 — Small explorative randomised study; presented by its own authors as exploratory rather than confirmatory.
- Utterback G, Zacharias R, Timraz S, Mershman D. Butterbur extract: prophylactic treatment for childhood migraines. Complementary Therapies in Clinical Practice. 2014;20(1):61–64 — PubMed PMID: 24439647 — Retrospective chart review — descriptive only, not a controlled comparison.
Pharmacology
- Wu SN, Chen H, Lin YL. The mechanism of inhibitory actions of S-petasin, a sesquiterpene of Petasites formosanus, on L-type calcium current in NG108-15 neuronal cells. Planta Medica. 2003;69(2):118–124 — PubMed PMID: 12624815 — Cell-culture study, and in a related species — the source of the calcium-channel hypothesis.
- Thomet OA, Wiesmann UN, Schapowal A, Bizer C, Simon HU. Role of petasin in the potential anti-inflammatory activity of a plant extract of Petasites hybridus. Biochemical Pharmacology. 2001;61(8):1041–1047 — PubMed PMID: 11286996 — Laboratory study identifying petasin as the principal anti-inflammatory constituent.
- Aydın AA, Zerbes V, Parlar H, Letzel T. The medical plant butterbur (Petasites): analytical and physiological (re)view. Journal of Pharmaceutical and Biomedical Analysis. 2013;75:220–229 — PubMed PMID: 23277154 — Review of the plant’s chemistry and the analytical problem at its centre.
PubMed Topic Searches
Connections
- All Herbs
- Butterbur Benefits — hub
- Pyrrolizidine Alkaloids and Liver Safety
- Choosing a PA-Free Product
- Allergic Rhinitis and Hay Fever
- Butterbur
- Feverfew — the other migraine herb
- Migraine
- Neurology
- Magnesium, Riboflavin and Supplements for Migraine
- Magnesium
- Vitamin B2 (Riboflavin)
- Liver Function Tests
- Comfrey