⚠ Evidence warning: Clinical trials or other evidence do not support the claim that chanca piedra helps a kidney stone pass at home and relaxes the ureter (the one placebo-controlled trial found no difference in stone passage or pain relief, the lithotripsy study found a significant benefit only for stones in the lower part of the kidney, and no trial has measured ureter relaxation). This page keeps it as a report of what people, websites or other media say.
Chanca Piedra Kidney-Stone Protocol
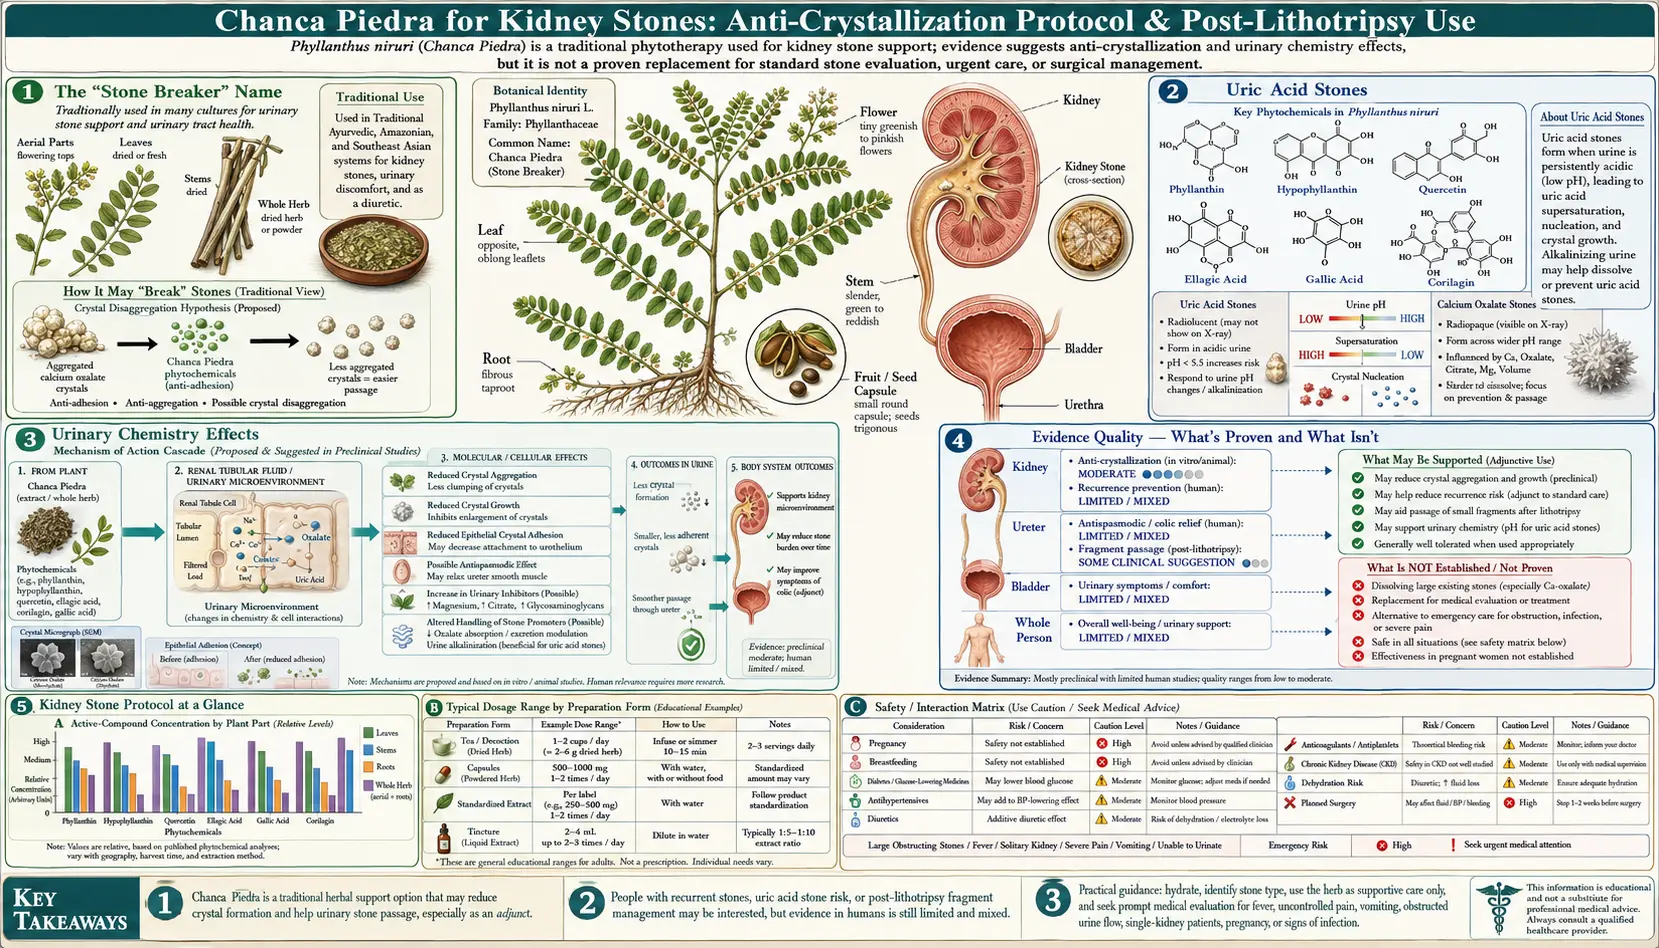
The Spanish name chanca piedra means “stone breaker” (in Brazil the plant is called quebra-pedra, Portuguese for the same thing), and the Spanish-speaking Amazon has used Phyllanthus niruri for urolithiasis for at least four centuries. This page describes the step-by-step home protocol that practitioners and patients use: who it is described for, how the herb is combined with hydration and pH management, the timelines reported, how it fits with conventional urology (lithotripsy, ureteroscopy, nephrology follow-up), and the warning signs that hospitals treat as emergencies. The companion Kidney Stones Benefits page reviews the underlying clinical-trial evidence; this page describes the practice. It does not replace a urologist’s assessment of a specific stone — it lays out the structured framework the practice follows.
Table of Contents
- Overview — What the Protocol Is and Who It Is Described For
- Stone Types and Mechanism of Action
- Pre-Protocol Assessment
- Daily Protocol — Step by Step (Acute Phase)
- Maintenance Phase — Recurrence Prevention
- Combining with Conventional Care
- Expected Timeline and Signs of Progress
- Drug Interactions and Cautions During Protocol
- Red Flags — Signs Hospitals Treat as Emergencies
- Key Research Papers
- Connections
- Featured Videos
Overview — What the Protocol Is and Who It Is Described For
As practitioners describe it, this protocol is a structured 2- to 4-week home regimen intended to (a) reduce crystal aggregation in the renal pelvis and ureter, (b) relax ureteral smooth muscle to ease stone passage, and (c) increase urine flow rate so existing stones move and new ones don’t form. It is built around standardized Phyllanthus niruri extract, aggressive but controlled hydration, dietary pH management, and ureteric symptom tracking. It is not a stand-alone cure: it is the patient-facing scaffolding around a urology workup.
Who practitioners describe the protocol for:
- Imaging-confirmed kidney or upper-ureteral stone, single, under 7 mm in greatest diameter, with no proximal hydronephrosis severe enough to require intervention
- Recurrent stone formers in a quiescent phase, using the herb adjunctively to reduce recurrence between episodes
- Patients with multiple small (under 4 mm) calcium-oxalate fragments after extracorporeal shock-wave lithotripsy (ESWL) or ureteroscopy with laser lithotripsy, where the fragments need to clear the lower urinary tract
- Adults with no contraindication to the herb (see Safety) and reliable access to oral hydration
- Patients who can return for urology re-imaging in 2–4 weeks if symptoms persist
Who practitioners exclude from the protocol:
- Anyone with a stone over 7 mm, a staghorn calculus, or bilateral obstructing stones — described as needing intervention
- Pregnant patients (Chanca Piedra is not established as safe in pregnancy, and obstructing stones in pregnancy are managed jointly by urology and obstetrics)
- Single-functioning kidney (any obstruction is an urgency, even of a small stone)
- Suspected infected obstruction — fever, chills, dysuria with flank pain is a urologic emergency
- Severe hydronephrosis on imaging or a creatinine that has bumped upward during the current episode
- Children and adolescents (different stone biology, different evidence base, urology referral)
- People taking lithium, warfarin, tacrolimus, or cyclosporine — drugs with a narrow safe range whose levels or effects the herb is reported to change (see Drug Interactions below)
Practitioners present the protocol as a structured way to give an in-the-window stone a fair chance to pass spontaneously alongside contact with a urology team, not as a substitute for imaging or for clinical follow-up.
Stone Types and Mechanism of Action
Kidney stones are not a single disease. Composition drives everything: dietary changes, urinary pH targets, the antibiotic question, and the herb’s likely usefulness. The major types in adults:
- Calcium oxalate (CaOx) — about 70% of stones. Forms in acidic-to-neutral urine. Driven by hypercalciuria, hyperoxaluria, hypocitraturia, low fluid intake. Chanca Piedra has its strongest mechanistic and clinical evidence for this stone type.
- Calcium phosphate (CaP) — about 15%, often mixed with CaOx. Forms in alkaline urine. Driven by hypercalciuria, alkaline urine (renal tubular acidosis), urinary tract infection-related alkalinization. Acidifying dietary measures may help; over-alkalinization with citrate can worsen this stone type.
- Uric acid — about 10%. Forms in acidic urine (pH under 5.5) regardless of serum urate. Driven by metabolic syndrome, insulin resistance, low urine volume. Highly amenable to medical dissolution by alkalinizing the urine to pH 6.5–7.0 with potassium citrate.
- Struvite (magnesium ammonium phosphate) — about 5%. Forms only in the presence of urea-splitting bacterial infection (Proteus, Klebsiella, Pseudomonas). Cannot be passed conservatively; requires antibiotic-plus-stone-removal management.
- Cystine — under 1%. Genetic; autosomal recessive cystinuria. Forms recurrent staghorn calculi; requires specialty management.
How Chanca Piedra is proposed to work against calcium-oxalate stones — what the studies found:
- Smaller, less clumped crystals (in a dish). When Barros and colleagues (2003) added an aqueous P. niruri extract to urine samples from healthy people and from rats and then triggered calcium oxalate crystal formation, the extract did not stop crystals forming — even more crystals appeared — but they were significantly smaller, and crystal clumping (aggregation) 24 hours later was reduced. The authors suggested the herb may interfere with the early stages of stone formation. This was a test-tube result, not urine from people taking the herb.
- Slower stone growth, with glycosaminoglycans moving into the stones (rats). In a 42-day rat study (Freitas 2002), P. niruri strongly slowed the growth of a bladder stone seeded with calcium oxalate and reduced the number of satellite stones; the stones were eliminated or dissolved in 3 of 22 treated rats. Urinary glycosaminoglycans (GAGs, natural inhibitors of crystallization) were lower in the treated rats (5.64 vs 11.78 mg per gram of creatinine), while the GAG content of the stones was higher (48.0 vs 16.6), so the authors linked the effect to more GAGs being built into the stones rather than to more GAGs in the urine. Urinary citrate and magnesium did not change. In a separate cell study, the extract strongly reduced the uptake of calcium oxalate crystals by dog kidney tubular cells grown in a dish (Campos 1999).
- Smooth-muscle relaxation of the ureter. Practitioners attribute to the herb’s lignans (phyllanthin, hypophyllanthin) and ellagitannins (geraniin, corilagin) a mild calcium-channel-blocker-like effect on ureteral smooth muscle, reducing the spasm component of renal colic and easing transit; a 2010 review by the Brazilian research group also named ureteral relaxation as one possible explanation for the herb’s clinical effects (Boim 2010). Patients on Chanca Piedra report a less crampy passage experience.
- Mild diuresis. Practitioners describe an increase in urine output by a measurable but modest amount, helping clear small stones and fragments. The diuresis is not driven by potent salt-wasting; it is a soft, sustained effect.
- Geraniin to urolithins. The ellagitannin geraniin is metabolized by gut microbiota into urolithins, which are proposed to provide systemic anti-inflammatory cover during the irritation phase of stone passage. This is the same urolithin pathway active for pomegranate ellagitannins.
- Lower urinary calcium in people with high urinary calcium. In a placebo-controlled trial (Nishiura 2004), 69 calcium stone formers took P. niruri 450 mg capsules three times daily or placebo for 3 months. Overall, 24-hour urine chemistry did not change, apart from a slight fall in urinary magnesium that stayed within the normal range; in the subgroup with high urinary calcium (hypercalciuria), urinary calcium fell from 4.8 to 3.4 mg/kg per 24 hours. Over this short follow-up there were no significant differences in stone passage or pain relief between the herb and placebo groups.
For uric-acid stones, the dominant intervention is urinary alkalinization with potassium citrate — Chanca Piedra is at best secondary. For struvite, the dominant intervention is antibiotic eradication of the urea-splitting infection plus mechanical stone clearance — Chanca Piedra is not described as having a role.
Pre-Protocol Assessment
Practitioners describe a minimum workup before the herb is used for a current episode:
Imaging confirmation:
- Non-contrast computed tomography (CT) of the abdomen and pelvis (low-dose stone protocol) is the gold standard. It confirms presence, position, and greatest diameter to the nearest millimeter, identifies hydronephrosis, and reveals second stones.
- Renal ultrasound is the radiation-free alternative for follow-up or for the first imaging in younger patients and pregnancy. Less sensitive for ureteral stones in the mid-ureter, but adequate for proximal and distal stones and for grading hydronephrosis.
- Kidneys, ureters and bladder (KUB) plain X-ray film is now mostly used for follow-up of known radio-opaque stones to track migration; insufficient as the primary diagnostic.
What the imaging shows that bears on the protocol:
- Stone size — under 4 mm: high spontaneous passage probability (around 80%); 4–6 mm: moderate (around 60%); 6–7 mm: borderline (around 30%); over 7 mm: low (under 20%) and increasingly likely to need intervention
- Stone location — lower-ureteral stones pass more readily than mid- or proximal-ureteral stones of equivalent size; renal-pelvis stones must first transit through the ureteropelvic junction
- Hydronephrosis grade — mild (grade 1–2) is acceptable for outpatient management; moderate-to-severe (grade 3–4) is an indication for prompt urology involvement
- Single versus bilateral — bilateral obstructing stones is a urologic urgency
- Second-functioning kidney confirmed (a known solitary kidney is managed by urology in real time, since any obstruction there is urgent)
Labs to baseline:
- Serum creatinine, estimated glomerular filtration rate (eGFR), blood urea nitrogen (BUN) — baseline renal function
- Complete blood count — to detect infection (leukocytosis)
- Urinalysis with microscopy — pH, specific gravity, blood, leukocyte esterase, nitrite, crystal type if seen
- Urine culture — standard if any infectious symptoms, leukocyte esterase positive, or nitrite positive
- Serum calcium, uric acid, phosphorus, sodium, potassium, chloride, bicarbonate — metabolic baseline
- 24-hour urine for calcium, oxalate, citrate, uric acid, sodium, magnesium, creatinine, volume (the standard recurrent-stone workup, done at least two weeks after the acute episode resolves)
- If a stone is retrieved, stone composition analysis by infrared spectroscopy or X-ray diffraction is the single most useful piece of data for long-term recurrence prevention
Hard contraindications — situations in which practitioners do not use herb-assisted passage:
- Stone over 7 mm
- Stone in a single functioning kidney
- Bilateral obstructing stones
- Fever, sepsis signs, or any suggestion of infected obstruction (white blood cells in urine plus stone is an emergency)
- Moderate-to-severe hydronephrosis (grade 3 or 4)
- Creatinine rise from baseline during the current episode
- Pregnancy
- Inability to maintain oral hydration (vomiting refractory to anti-emetics)
- Anatomical urinary tract abnormality (horseshoe kidney, ureteropelvic junction obstruction, ureterocele) without urology guidance
Daily Protocol — Step by Step (Acute Phase)
The acute phase runs for 2–4 weeks from the start of symptoms or from a recent procedure. The goal is spontaneous passage of the index stone (or post-procedure fragments) while supporting symptom control.
Hydration
Hydration is described as the single most important variable. The usual target is at least 2.5 to 3.5 liters of urine output per 24 hours, which usually takes 3–4 liters of fluid intake spread evenly across waking hours plus 250–500 mL on waking after a night of getting up.
- Practitioners describe steady drinking rather than surges, about 250–350 mL every waking hour.
- Water is the base. Plain low-calcium mineral waters with moderate-to-high bicarbonate are described as useful for both CaOx and uric-acid stones; the alkalinizing effect is a small bonus on top of the volume.
- Fresh lemon juice (juice of half a lemon per 500 mL) adds citrate — citrate is the body’s natural inhibitor of CaOx and CaP crystallization.
- Soda, sweetened drinks, and concentrated fruit juices carry a fructose load that increases urinary uric acid and oxalate.
- Coffee in moderation may be slightly protective; the Coffee page covers the evidence.
- Alcohol during acute passage brings rebound dehydration overnight, the opposite of the hydration goal.
Urine output and color. Urine color tracks hydration loosely: pale straw is the target, dark amber means fluid intake is behind, clear-and-frequent is fine. Passing urine less often than every 2–3 hours during the day is a sign of too little fluid.
Chanca Piedra dosing — acute phase
- Capsule, standardized extract — practitioners describe 400–500 mg of standardized P. niruri aerial-parts extract, taken three times daily with meals. This is the most reproducible dose form and close to the dose in the Nishiura trial (450 mg capsules three times daily for 3 months); the Micali lithotripsy study used a different regimen, 2 g of extract daily for at least 3 months.
- Liquid extract / tincture — herbal practice describes 2–3 mL (about 40–60 drops) of a 1:5 hydroalcoholic tincture, three times daily, diluted in 100 mL water with meals.
- Traditional decoction (tea) — 1 tablespoon dried herb simmered in 1 L water for 10 minutes, drunk over the day in three or four portions. Extraction is less reproducible than with capsules; practitioners use it alongside capsule dosing partly for its hydration value.
What is in the bag. DNA testing of herbal teas sold in Brazil as quebra-pedra (Inglis 2018) found that the packaged dried herb from three suppliers was a different species, Phyllanthus tenellus, one of them also mixed with alfalfa, and that a fourth supplier’s product was a mixture of Desmodium barbatum and P. niruri. The authors note that of the four Phyllanthus species used for kidney stones in Brazilian folk medicine, only P. niruri has been shown to be effective in a clinical setting.
The Forms, Dosing and Standardization page covers the full dosing matrix, product notes, and shelf-life considerations.
Timing: practitioners describe taking it with meals; the meal-protein context helps stabilize gastric tolerance and the lignans absorb well in a mixed-meal matrix. Black or green tea within an hour is described as reducing absorption (tannins compete).
Urine pH targeting
pH matters more than people realize. Practitioners describe pH test strips (range 4.5 to 8.0) used on first-morning urine and one mid-afternoon void daily for the first week.
- Calcium-oxalate stones — the target described is 6.5 to 7.0; above 7.2 raises the risk of calcium phosphate (CaP) crystallization, and below 6.0 encourages CaOx aggregation.
- Calcium-phosphate stones — the target described is narrower: 6.0 to 6.5, slightly more acidic; aggressive alkalinization raises the risk for this stone type.
- Uric-acid stones — the target described is 6.5 to 7.0 with potassium citrate, prescribed by urology; many uric-acid stones literally dissolve at sustained urine pH above 6.5 over 2–6 weeks. Chanca Piedra is described as an adjunct here, not the primary intervention.
- Struvite stones — pH targeting is irrelevant; antibiotic + surgical clearance.
Gentle alkalinization for CaOx or uric-acid stones comes from lemon juice (above), potassium-rich plant foods and alkaline mineral waters. For a stronger effect, urology often prescribes potassium citrate 10–20 mEq three times daily; high-dose oral alkali affects blood potassium and the body’s acid-base balance, which is why it is given on prescription and checked with blood tests.
Diet during acute passage
- Adequate dietary calcium (around 1000–1200 mg/day from food, especially with meals) — low-calcium diets paradoxically increase CaOx stone risk because dietary calcium binds dietary oxalate in the gut
- Practitioners describe cutting back high-oxalate foods during an acute episode: spinach, beets, rhubarb, almonds, peanuts, chocolate, sweet potato, soy
- Dietary sodium under 2300 mg/day is the usual target — sodium drives calciuria
- Animal protein of roughly 0.8–1.0 g/kg body weight is the usual target — high animal protein raises urinary calcium and uric acid and lowers citrate
- Whole fruit rather than juice — juices concentrate fructose without the fiber buffering
- Magnesium-rich foods (pumpkin seeds, leafy greens that are not high-oxalate, avocado) — magnesium competes with calcium for oxalate binding
Urine straining
Practitioners describe straining every void during acute passage, with a stone-collection strainer from a pharmacy or a coffee filter over a clean container. Once a stone is caught, the usual steps are:
- It is rinsed with water and dried on a tissue.
- It is photographed next to a millimeter ruler.
- It goes into a clean dry container (a small zip bag works), labelled with date and time.
- It goes to the urologist for composition analysis, the single most useful piece of data for preventing the next stone.
Symptom control
- Nonsteroidal anti-inflammatory drugs (ibuprofen 600 mg every 6–8 hours with food, or ketorolac if prescribed) are first-line for renal colic. They reduce ureteral edema and pain in parallel.
- Acetaminophen 1000 mg every 6 hours adds analgesia without nonsteroidal anti-inflammatory drug (NSAID) overlap.
- Tamsulosin 0.4 mg at bedtime is widely prescribed as medical expulsive therapy for distal-ureteral stones 5–10 mm; evidence is mixed but the safety profile is acceptable and it’s standard practice in many urology guidelines.
- Antiemetics (ondansetron 4–8 mg every 8 hours) if nausea is the limiter on hydration.
- Patients describe a warm shower or a warm compress on the costovertebral angle (the back, just below the ribs) as easing refractory crampy pain.
Maintenance Phase — Recurrence Prevention
About half of all first-time stone formers will form another stone within 5–10 years if no preventive measures are adopted. The maintenance phase is where practitioners place most of Chanca Piedra’s use, based on the anti-aggregation findings above.
Maintenance dosing described by practitioners — structured cycling:
- Continuous low-dose — 250–400 mg standardized extract once daily, ongoing. Described for high-recurrence patients with documented hypercalciuria or hypocitraturia who have tolerated the herb well.
- Cycled dosing — 400 mg three times daily for 2 weeks every 8–12 weeks (a quarterly “tune-up” that gives plasma levels of the lignans periodic peaks without continuous exposure). The traditional Amazonian dosing approximates this rhythm.
- Trigger-event dosing — full acute-phase dose during periods of higher recurrence risk: travel, extreme heat exposure, illness with prolonged antibiotics, periods of dietary lapse.
Lifestyle priorities for sustained prevention:
- Fluid — at least 2.5 L urine output / 24 h, every day, long term. The single most evidence-based prevention measure for all stone types.
- Dietary calcium intake of 1000–1200 mg/day from food, not supplements — supplemental calcium taken outside meals worsens CaOx stones; food calcium with meals reduces them
- Dietary sodium under 2300 mg/day
- Moderate animal-protein intake
- Lemon water habitually — the citrate is durable, daily, low-cost recurrence prevention
- Magnesium intake — the Magnesium page covers the dietary and supplemental options; magnesium glycinate is reported as well tolerated and non-laxative at moderate doses
- A repeat 24-hour urine workup once or twice during the first year and annually thereafter is standard for high-recurrence patients
- If a uric-acid stone was identified: dietary purine moderation, weight management if obesity-associated, urinary alkalinization habit (urology may prescribe long-term potassium citrate)
- If a struvite stone was identified: prompt antibiotic management of any urinary tract infection (UTI); mechanical stone clearance is required and the herb has no role
Follow-up imaging — renal ultrasound annually is common for high-recurrence patients; non-contrast computed tomography is reserved for symptomatic episodes or unusual presentations to limit radiation exposure.
Combining with Conventional Care
Herbal-assisted passage and modern urology are not opposites. The clearest positive result in the published studies came from using the herb alongside lithotripsy.
As an adjunct to extracorporeal shock-wave lithotripsy (ESWL)
This is the best-studied indication. In the randomized study of P. niruri after lithotripsy (Micali 2006), 150 patients with calcium oxalate kidney stones up to 25 mm had 1 to 3 ESWL sessions; 78 then took a P. niruri extract (2 g daily) for at least 3 months and 72 served as controls. At 180 days the stone-free rate (no stone, or fragments under 3 mm) was 93.5% with the herb and 83.3% without, a difference that was not statistically significant (p = 0.48); for stones in the lower part of the kidney (lower calyx, 56 patients) it was 93.7% versus 70.8% (p = 0.01). Re-treatment was needed in 39.7% versus 43.3%, and no side effects were recorded. Pucci and colleagues (2018) studied a different question, without a placebo group: in 56 patients with kidney stones under 10 mm who drank P. niruri infusion (tea) for 12 weeks, urinary potassium and the magnesium-to-creatinine ratio rose, urinary oxalate fell from 59.0 to 28.8 mg per 24 hours in those with high urinary oxalate, urinary uric acid fell in those with high urinary uric acid, and the number of stones per patient fell from 3.2 to 2.0. The proposed mechanism for the lithotripsy result is the combination of anti-aggregation (preventing fragment re-cohesion) plus mild diuresis (washing fragments through the ureter) plus ureteral smooth-muscle relaxation (easing transit through the ureterovesical junction).
In practice, the question comes up for people in the “fragment clearance” phase after ESWL on a renal-pelvis or upper-ureteral stone. The lithotripsy study used 2 g of extract daily for at least 3 months, not the 400 mg three times daily for 4–8 weeks often described in practice. Many urologists are open to the herb for adherent, motivated patients; some are skeptical of the evidence.
What reviews of the evidence conclude
A 2020 meta-analysis (Dhawan and Olweny) found only two controlled human studies reporting stone size and number. Pooled, P. niruri reduced mean stone size (standardized mean difference −0.39) and stone number (−0.38), and the authors concluded that limited clinical evidence supports modest efficacy, pending further study. A 2025 systematic review of 16 human and rat studies (Iregui-Parra and colleagues) reported that serial measurements of blood electrolytes and liver function consistently supported the herb’s long-term safety, and that as an add-on after shock-wave lithotripsy it showed benefit for stones in the lower pole of the kidney.
As an adjunct to ureteroscopy (URS)
Less studied than ESWL adjunct. Practitioners consider it plausibly useful for the same reasons (residual fragment clearance, ureteral relaxation around the stent), but the evidence base is thinner. A double-J (JJ) ureteral stent left in place after URS commonly causes bladder irritation; the herb is not described as easing stent pain, while anticholinergics or alpha-blockers are used for it.
Medical expulsive therapy (MET) overlap
Tamsulosin is widely prescribed for ureteral stones in the 5–10 mm range. Chanca Piedra is mechanistically additive, not redundant: tamsulosin is an alpha-1 antagonist (ureteral and lower-urinary-tract effect), Chanca Piedra works partly through general smooth-muscle relaxation. There is no published interaction between the two; clinicians and patients combining them have not reported a problem.
Situations that involve nephrology and urology
- For any stone >5 mm, urology practice is a documented decision about expectant versus interventional management
- Recurrent stone formers (two or more stones) are usually offered a metabolic workup with a nephrologist or a urologist who runs a stone clinic
- Any cystinuria, primary hyperoxaluria, or distal renal tubular acidosis case is specialty management territory
- Some medicines can themselves promote stones (high-dose vitamin C, indinavir, topiramate, acetazolamide, calcium plus vitamin D supplementation)
Expected Timeline and Signs of Progress
Realistic expectations matter. Stone-passage timing depends mostly on stone size and location at the moment the protocol begins.
- Stones under 4 mm in the lower ureter — usually pass within 1–2 weeks of starting hydration and the herb. Most patients pass within 7 days.
- Stones 4–6 mm in the lower ureter — 2–4 weeks. Some pass quickly; some take the full month. Persistent pain past 4 weeks is the trigger for re-imaging.
- Stones 4–7 mm in the mid- or proximal ureter — 3–6 weeks; some need intervention even within the window of acceptable size, especially proximal stones
- Renal-pelvis stones — may sit for weeks before mobilizing into the ureter. The Chanca Piedra protocol is most useful here as a chronic-low-dose anti-aggregation prevention rather than acute expectation
- Post-ESWL fragments — 4–12 weeks for complete clearance; the herb’s proposed role is to keep the fragments from re-coalescing and to ease them out
Signs of progress (good news):
- Pain pattern shifts downward: flank pain transitions to lower abdomen and inguinal area as the stone moves into the distal ureter, then to suprapubic and urethral as it reaches the bladder
- Pain becomes intermittent rather than sustained — ureteral spasm relaxes
- Mild hematuria (pink to tea-colored urine) on and off — expected as the stone abrades the urothelium
- Brief intense pain followed by relief, often with the sensation of needing to urinate, often with stone in the strainer afterward
- Resolution of nausea
- Imaging at week 2 or 4 showing stone migration distally or absent
Signs of no progress (decision point):
- Same pain in the same location at week 2 — the usual point for re-imaging
- Worsening flank pain rather than improving — a reason for re-imaging and a creatinine check
- Gross hematuria that does not abate, or large blood clots
- New or worsening hydronephrosis on follow-up ultrasound
- Creatinine rise from baseline — a sign of kidney strain that urology treats as urgent
Hematuria interpretation: mild discoloration of urine for several days during acute passage is normal. Frank red blood, large clots, or hematuria that persists more than 7–10 days after the stone has clearly passed is a finding urologists investigate.
Drug Interactions and Cautions During Protocol
A condensed version is here; the full list lives on the Safety, Drug Interactions and Cautions page.
- Lithium — P. niruri’s mild diuresis can reduce renal lithium clearance and lift serum lithium levels. A rise in serum lithium can cause lithium toxicity (tremor, vomiting, diarrhea, confusion, unsteadiness).
- Antihypertensives — Chanca Piedra has mild blood-pressure-lowering activity through ACE-inhibition-like mechanisms in the geraniin / corilagin fraction. Patients on angiotensin-converting enzyme inhibitors (ACE inhibitors), angiotensin receptor blockers (ARBs), beta-blockers, or calcium channel blockers may see modest additive lowering. Practitioners describe home blood pressure (BP) checks during the first 2 weeks.
- Anticoagulants (warfarin) and antiplatelet agents — the tannin fraction has shown mild antiplatelet activity in vitro. With warfarin, practitioners describe more frequent international normalized ratio (INR) checks during the first month. The concern is greatest alongside full-dose dual antiplatelet therapy, where any added antiplatelet activity adds to bleeding risk.
- Diabetes medications — Chanca Piedra has modest blood-glucose-lowering activity; for insulin and sulfonylurea users this raises a risk of low blood sugar (hypoglycemia), especially during the higher-dose acute phase.
- Cytochrome P450 3A4 (CYP3A4) substrates — the herb mildly inhibits CYP3A4 and CYP2C9. Narrow-therapeutic-window substrates (tacrolimus, cyclosporine, certain statins, ergot alkaloids, several immunosuppressants, certain antiarrhythmics) can reach toxic blood levels when their breakdown is slowed.
- Vitamin C in high doses — over 1000 mg/day of ascorbate increases urinary oxalate in some patients and may negate the anti-stone benefits. Practitioners keep supplemental vitamin C modest during the acute phase for this reason.
- Diuretics (thiazide / loop) — thiazide diuretics are themselves anti-stone (they reduce urinary calcium) and combine reasonably with Chanca Piedra. Loop diuretics increase urinary calcium and are generally not chosen for stone formers.
Pregnancy: not established as safe; there is no good safety data in pregnancy.
Breastfeeding: insufficient data; standard guidance advises against use while breastfeeding.
Pre-operative discontinuation: the usual practice is stopping Chanca Piedra at least 2 weeks before any planned surgery (cytochrome P450 3A4 and antiplatelet considerations).
Red Flags — Signs Hospitals Treat as Emergencies
The following are signs that hospitals treat as emergencies, or as needing urgent evaluation, during stone passage; practitioners stop the protocol when any of them appears:
- Fever (over 38.0°C / 100.4°F) with flank or back pain, with or without chills — infected obstructed kidney is a true emergency; sepsis can develop in hours
- Rigors / shaking chills with flank pain — same; rigors can come before a fever appears
- Anuria (no urine output for over 8 hours) in a patient who has been hydrating — suggests bilateral obstruction or obstruction in a single functioning kidney
- Unilateral severe flank pain that does not respond to nonsteroidal anti-inflammatory drug plus acetaminophen at over 6 hours — pain that breaks through full outpatient analgesia is severe colic; intervention may be needed
- Confusion, lethargy, or marked weakness with stone symptoms — signs of urosepsis
- Persistent vomiting that prevents oral hydration for more than 12 hours — intravenous (IV) fluids and antiemetics are needed; ongoing dehydration worsens stone-passage prospects
- Gross hematuria with passing of large clots — uncommon but warrants urgent evaluation
- Hypotension or syncope with stone symptoms — could be severe pain plus dehydration or could be early sepsis; hospitals evaluate this urgently
- New rash, marked liver-area discomfort, jaundice, or marked fatigue — rare hepatic reactions to the herb have been reported; these are signs of liver injury that hospitals treat as urgent, checked with liver-function tests
- Pregnancy onset during the protocol — the herb is not established as safe in pregnancy, and kidney stones in pregnancy are managed jointly by obstetrics and urology
- Severe abdominal pain that is no longer typical of renal colic — it can come from other emergencies (aortic, appendiceal, gynecologic, biliary)
Three sentinel symptoms deserve special emphasis because patients dismiss them too readily:
- Fever plus stone symptoms is an emergency. Not a “wait and see” situation. Infected obstruction can progress to urosepsis in hours.
- Not urinating is an emergency. Not normal at any point in the protocol.
- Pain that breaks through full-dose nonsteroidal anti-inflammatory drug plus tamsulosin plus the herb is an indication that the protocol is failing. Either the stone has not moved or it is causing damage; this is the point for re-imaging.
The protocol exists to give an in-the-window stone a fair chance to pass at home. It does not exist to replace urgent or emergent urologic care.
Key Research Papers
- Barros ME, Schor N, Boim MA. Effects of an aqueous extract from Phyllanthus niruri on calcium oxalate crystallization in vitro. Urol Res 2003;30(6):374-9. — PubMed PMID: 12599017 · doi:10.1007/s00240-002-0285-y
- Nishiura JL, Campos AH, Boim MA, Heilberg IP, Schor N. Phyllanthus niruri normalizes elevated urinary calcium levels in calcium stone forming (CSF) patients. Urol Res 2004;32(5):362-6. — PubMed PMID: 15221244 · doi:10.1007/s00240-004-0432-8
- Micali S, Sighinolfi MC, Celia A, et al. Can Phyllanthus niruri affect the efficacy of extracorporeal shock wave lithotripsy for renal stones? A randomized, prospective, long-term study. J Urol 2006;176(3):1020-2. — PubMed PMID: 16890682 · doi:10.1016/j.juro.2006.04.010
- Pucci ND, Marchini GS, Mazzucchi E, et al. Effect of Phyllanthus niruri on metabolic parameters of patients with kidney stone: a perspective for disease prevention. Int Braz J Urol 2018;44(4):758-764. — PubMed PMID: 29617079 · doi:10.1590/S1677-5538.IBJU.2017.0521
- Freitas AM, Schor N, Boim MA. The effect of Phyllanthus niruri on urinary inhibitors of calcium oxalate crystallization and other factors associated with renal stone formation. BJU Int 2002;89(9):829-34. — PubMed PMID: 12010223 · doi:10.1046/j.1464-410x.2002.02794.x
- Campos AH, Schor N. Phyllanthus niruri inhibits calcium oxalate endocytosis by renal tubular cells: its role in urolithiasis. Nephron 1999;81(4):393-7. — PubMed PMID: 10095174 · doi:10.1159/000045322
- Boim MA, Heilberg IP, Schor N. Phyllanthus niruri as a promising alternative treatment for nephrolithiasis. Int Braz J Urol 2010;36(6):657-64; discussion 664. — PubMed PMID: 21176271 · doi:10.1590/s1677-55382010000600002
- Calixto JB, Santos AR, Cechinel Filho V, Yunes RA. A review of the plants of the genus Phyllanthus: their chemistry, pharmacology, and therapeutic potential. Med Res Rev 1998;18(4):225-58. — PubMed PMID: 9664291 · doi:10.1002/(sici)1098-1128(199807)18:4<225::aid-med2>3.0.co;2-x
- Patel JR, Tripathi P, Sharma V, Chauhan NS, Dixit VK. Phyllanthus amarus: ethnomedicinal uses, phytochemistry and pharmacology: a review. J Ethnopharmacol 2011;138(2):286-313. — PubMed PMID: 21982793 · doi:10.1016/j.jep.2011.09.040
- Devarbhavi H, Aithal G, Treeprasertsuk S, et al. Drug-induced liver injury: Asia Pacific Association of Study of Liver consensus guidelines. Hepatol Int 2021;15(2):258-282. — PubMed PMID: 33641080 · doi:10.1007/s12072-021-10144-3
- Curhan GC, Willett WC, Speizer FE, Spiegelman D, Stampfer MJ. Comparison of dietary calcium with supplemental calcium and other nutrients as factors affecting the risk for kidney stones in women. Ann Intern Med 1997;126(7):497-504. — PubMed PMID: 9092314 · doi:10.7326/0003-4819-126-7-199704010-00001
- Borghi L, Schianchi T, Meschi T, et al. Comparison of two diets for the prevention of recurrent stones in idiopathic hypercalciuria. N Engl J Med 2002;346(2):77-84. — PubMed PMID: 11784873 · doi:10.1056/NEJMoa010369
- Dhawan S, Olweny EO. Phyllanthus niruri (stone breaker) herbal therapy for kidney stones; a systematic review and meta-analysis of clinical efficacy, and Google Trends analysis of public interest. Can J Urol 2020;27(2):10162-10166. — PubMed PMID: 32333735
- Iregui-Parra J, Rojas Ossa V, Arias Salazar CM, et al. Phyllanthus niruri in the management of nephrolithiasis: A systematic review of the literature. Actas Urol Esp (Engl Ed) 2025;49(6):501791. — PubMed PMID: 40480426 · doi:10.1016/j.acuroe.2025.501791
- Inglis PW, Mata LR, da Silva MJ, et al. DNA Barcoding for the Identification of Phyllanthus Taxa Used Medicinally in Brazil. Planta Med 2018;84(17):1300-1310. — PubMed PMID: 29929208 · doi:10.1055/a-0644-2688
PubMed Topic Searches
Connections
- All Herbs
- Chanca Piedra Overview
- Chanca Piedra Benefits Hub
- Uric Acid, Gout and Hypertension
- Kidney Stones
- Magnesium
- Vitamin B12
- Coffee
- Morley Robbins Protocol
- Uric Acid (Lab Test)
- Vitamin K
- Milk Thistle
- Calcium — adequate dietary calcium taken with meals binds oxalate in the gut, so restricting it paradoxically raises calcium-oxalate stone risk.