Bitter Melon for Diabetes Complications
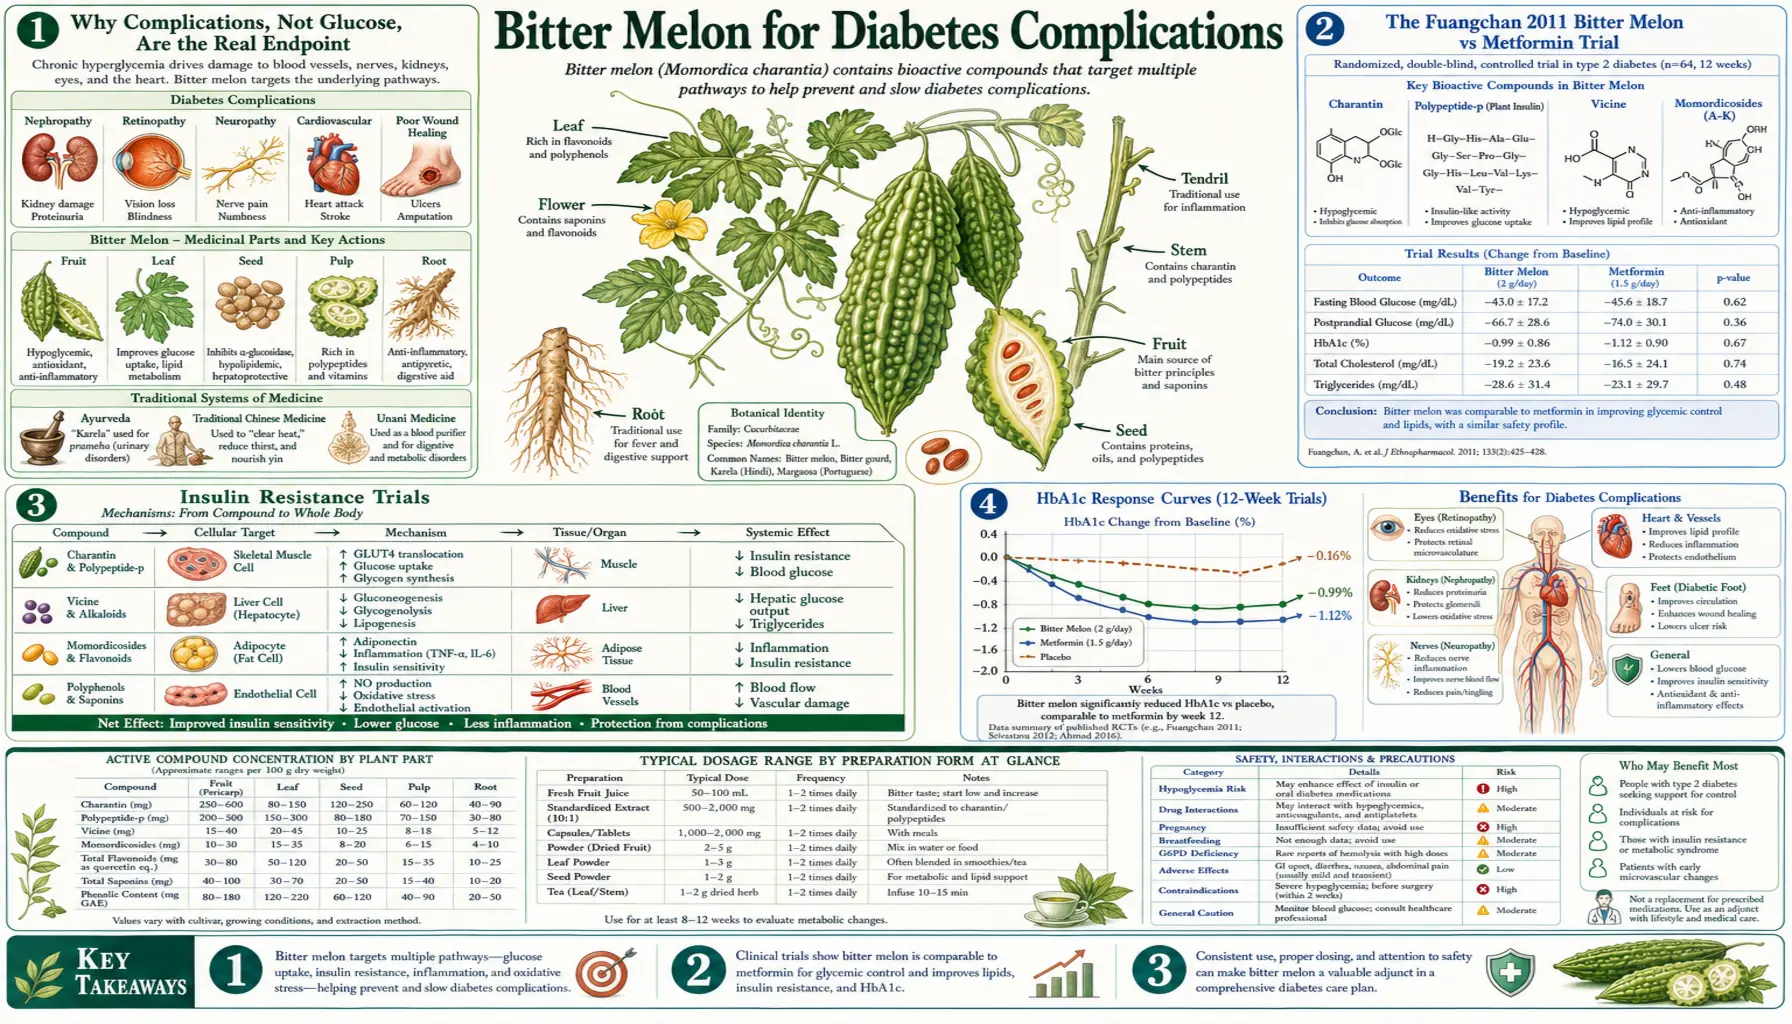
The case for bitter melon shifts when we move past simple glycemic control and into the broader question of preventing or slowing the downstream microvascular and macrovascular complications of long-standing diabetes — retinopathy, nephropathy, neuropathy, atherosclerosis, and the foot ulcers that can spiral into amputation. Here the clinical data are weaker and the comparative story is unflattering: the seminal Fuangchan et al. 2011 head-to-head randomized trial of bitter melon versus pharmaceutical metformin in newly diagnosed type 2 diabetics in Thailand found that over four weeks bitter melon 2,000 mg/day lowered fructosamine (a short-term blood-sugar marker) less than metformin 1,000 mg/day. The honest read of the comparative literature is that bitter melon does not match pharmaceutical metformin in glycemic potency, and therefore by extension does not match it for prevention of microvascular complications — which depend on cumulative hemoglobin A1c (HbA1c) exposure (the UKPDS and DCCT trials are the foundational evidence). Where bitter melon does have a legitimate place is as an early-stage adjunct in prediabetes and well-controlled type 2 diabetes, as a vehicle for the insulin-sensitizing effect that reduces the dose of pharmaceutical agents required, and as part of a comprehensive metabolic plan that includes diet, exercise, and pharmaceutical therapy together rather than as alternatives.
Table of Contents
- Why Complications, Not Glucose, Are the Real Endpoint
- The Fuangchan 2011 Bitter Melon vs Metformin Trial
- Insulin Resistance Trials
- Hemoglobin A1c Response Curves
- Indian Charantia Trials in Newly Diagnosed Type 2 Diabetes
- Retinopathy: The Eye Complication
- Nephropathy: The Kidney Complication
- Neuropathy: The Nerve Complication
- Macrovascular Disease and Cardiovascular Risk
- Bitter Melon as an Adjunct, Not a Substitute
- Cautions and Safety Facts
- Key Research Papers
- Connections
- Featured Videos
Why Complications, Not Glucose, Are the Real Endpoint
Glucose is a surrogate marker. The reason we worry about elevated glucose is not because the number on a meter is large; it is because chronic hyperglycemia damages tissues through several well-characterized molecular pathways — the formation of advanced glycation end products (AGEs), oxidative stress from mitochondrial superoxide overproduction in vascular endothelium, polyol pathway activation, and protein kinase C pathway dysregulation. These molecular insults, accumulated over years, produce the microvascular complications (retinopathy, nephropathy, neuropathy) and macrovascular complications (atherosclerosis, myocardial infarction, stroke) that cause the morbidity and mortality of diabetes.
The two foundational trials of glycemic control and complication prevention are the United Kingdom Prospective Diabetes Study (UKPDS) for type 2 diabetes and the Diabetes Control and Complications Trial (DCCT) for type 1 diabetes. Both trials demonstrated that tight glycemic control significantly reduces microvascular complications, with the effect approximately linear in cumulative hemoglobin A1c exposure over time — an effect sometimes called “metabolic memory” because it persists for years after a period of better control.
The implication for bitter melon: any agent that meaningfully lowers hemoglobin A1c will, over time, reduce microvascular complication risk in proportion to the magnitude of hemoglobin A1c reduction. The Yin 2014 meta-analysis (4 trials, 208 people with type 2 diabetes) found that bitter melon did not significantly lower hemoglobin A1c (pooled difference -0.13%, 95% CI -0.41 to 0.16); later meta-analyses report small falls of 0.26 and 0.38 percentage points (see Hemoglobin A1c Response Curves). A fall of that size translates to a measurable but modest reduction in projected complication risk. The larger hemoglobin A1c reduction typical of pharmaceutical metformin (or insulin in advanced disease) translates to a much larger reduction. The relative magnitudes matter for clinical decision-making.
The Fuangchan 2011 Bitter Melon vs Metformin Trial
The most important head-to-head comparison is Fuangchan A, Sonthisombat P, Seubnukarn T, et al., “Hypoglycemic effect of bitter melon compared with metformin in newly diagnosed type 2 diabetes patients,” published in Journal of Ethnopharmacology in 2011. It was a 4-week, multicenter, randomized, double-blind trial led from the Faculty of Pharmaceutical Sciences at Naresuan University in Phitsanulok, Thailand, in patients with newly diagnosed type 2 diabetes.
Patients were randomized to one of four arms:
- Bitter melon 500 mg/day (low dose)
- Bitter melon 1,000 mg/day (mid dose)
- Bitter melon 2,000 mg/day (high dose)
- Metformin 1,000 mg/day (reference arm)
The primary endpoint was the change in fructosamine (a 2-3 week glycemic marker, used because the trial was only 4 weeks) from baseline. Results:
- Bitter melon 2,000 mg/day — small but statistically significant fructosamine reduction from baseline: -10.2 µmol/L (95% CI -19.1 to -1.3)
- Bitter melon 500 mg/day and 1,000 mg/day — no statistically significant effect (-3.5 and -10.3 µmol/L, with confidence intervals crossing zero)
- Metformin 1,000 mg/day — the largest fructosamine reduction: -16.8 µmol/L (95% CI -31.2 to -2.4); the authors concluded that the glucose-lowering effect of bitter melon was less than that of metformin 1,000 mg/day
The Fuangchan trial is the most-cited comparative clinical study of bitter melon and is the source of the now-standard statement in the integrative-medicine literature that “bitter melon is less effective than 1 g/day metformin.” The trial has been criticized for short duration (4 weeks may not capture maximal bitter melon effect) and for using a relatively low metformin reference dose (most diabetics on metformin take 1,500-2,000 mg/day, not 1,000 mg/day). But even with those caveats, no follow-up trial has reversed the authors' conclusion: pharmaceutical metformin is the more potent agent.
What the trial shows: in newly diagnosed type 2 diabetes, metformin 1,000 mg/day lowered blood sugar more than bitter melon at any of the three doses tested, so the trial does not support bitter melon as a replacement for metformin. Bitter melon has also been studied as an add-on to standard treatment and by people who decline or cannot tolerate metformin; the add-on trials are described below.
Insulin Resistance Trials
The bitter melon literature includes a smaller set of trials focused specifically on insulin resistance — the underlying metabolic disturbance that precedes overt type 2 diabetes by years to decades. Insulin resistance is typically quantified by the Homeostatic Model Assessment of Insulin Resistance (HOMA-IR) index, calculated from fasting glucose and fasting insulin.
Bitter melon trials measuring homeostatic model assessment of insulin resistance have generally shown 10-20% reductions over 8-12 weeks of standardized extract supplementation, comparable in magnitude to lifestyle interventions and to lower-dose metformin. The mechanism is the AMP-activated protein kinase (AMPK) activation discussed in the Blood Sugar deep-dive — AMP-activated protein kinase activation increases insulin-independent glucose uptake into muscle, suppresses hepatic glucose output, and over time improves insulin signaling at the receptor level.
For patients with prediabetes (fasting glucose 100-125 mg/dL, hemoglobin A1c 5.7-6.4%, or impaired glucose tolerance on an oral glucose tolerance test (OGTT)), bitter melon is one option discussed as part of a broader insulin-sensitizing plan, which typically includes:
- Carbohydrate moderation, particularly reduction of refined-carbohydrate and added-sugar intake
- Regular aerobic and resistance exercise (both directly activate AMP-activated protein kinase)
- Adequate sleep (insufficient sleep is independently insulin-desensitizing)
- Stress management (chronic cortisol elevation drives insulin resistance)
- Often berberine or pharmaceutical metformin if metabolic markers do not improve with lifestyle alone
Two newer studies looked at insulin resistance directly. In a 2025 Dutch study of people with prediabetes, 12 weeks of freeze-dried whole bitter gourd (3.6 g/day, 38 people) lowered fasting glucose and HOMA-IR more than a cucumber-based placebo, while a second, 4-week crossover trial in the same report with freeze-dried bitter gourd juice (2.4 g/day, 30 people) found no significant difference from placebo; neither study found side effects or signs of health risk. A 2025 meta-analysis of 25 randomized trials in prediabetes and type 2 diabetes found that bitter melon lowered fasting glucose, hemoglobin A1c, insulin and HOMA-IR, but did not change HOMA-beta, a measure of how well the insulin-producing beta cells work.
For the broader picture of insulin resistance management, see our Insulin Resistance page.
Hemoglobin A1c Response Curves
Across the bitter melon randomized controlled trial (RCT) literature, the hemoglobin A1c response shows characteristic features that are useful to understand for setting realistic patient expectations:
- Onset — measurable hemoglobin A1c change typically requires 8-12 weeks. The shorter Fuangchan trial used fructosamine because 4 weeks is too brief for hemoglobin A1c to fully respond (red cell turnover takes ~120 days, so hemoglobin A1c reflects roughly the past 3 months).
- Magnitude — the Yin 2014 meta-analysis (4 trials, 208 people, 4-12 weeks) found no significant fall in hemoglobin A1c compared with no treatment (pooled difference -0.13%, 95% CI -0.41 to 0.16). Later meta-analyses with more trials report falls of 0.26 percentage points (2019) and 0.38 percentage points (2024), described below. Both are smaller than the typical response to metformin (1.0-1.5 percentage points).
- Plateau — effect appears to plateau at 3-6 months. Continued use sustains the reduction but does not produce further gains.
- Dose-response — weakly dose-dependent up to about 2,000 mg/day of standardized extract; higher doses do not appear to produce proportionally larger effects and may increase gastrointestinal adverse events.
- Baseline-dependent — larger absolute hemoglobin A1c reduction in patients with higher baseline hemoglobin A1c (a common finding in glycemic-control studies because there is more “room to fall”). Patients with hemoglobin A1c above 8.5% see proportionally larger reductions than patients near the diabetes diagnostic threshold of 6.5%.
A 2019 meta-analysis of 10 studies (1,045 people with type 2 diabetes, followed 4-16 weeks) found that single-herb bitter melon preparations, compared with placebo, lowered fasting glucose by 0.72 mmol/L, after-meal glucose by 1.43 mmol/L and hemoglobin A1c by 0.26 percentage points; the authors rated the evidence for these outcomes low to very low quality, and no serious side effects were reported. A 2024 meta-analysis of 8 randomized trials (423 people with type 2 diabetes) found that bitter melon lowered hemoglobin A1c by 0.38 percentage points, fasting glucose by 0.85 mmol/L, after-meal glucose by 2.28 mmol/L and total cholesterol by 0.38 mmol/L more than the control groups; triglycerides, high-density lipoprotein and low-density lipoprotein cholesterol did not change significantly.
The Philippine placebo-controlled trial shows how hard a small effect is to detect. At the Philippine General Hospital, 40 people with type 2 diabetes (hemoglobin A1c 7-9%) took bitter melon capsules or placebo on top of their standard therapy for 3 months. The difference in hemoglobin A1c change was 0.22% in favor of bitter melon (95% CI -0.40 to 0.84, p=0.48), with no significant effect on fasting blood sugar, total cholesterol or weight. The investigators had planned the trial to detect a 1% fall; with the smaller fall seen, its achieved power was only 11%, so they could not reach a definite conclusion.
For the deeper interpretation of hemoglobin A1c and its relationship to projected complication risk, see our hemoglobin A1c page and the hemoglobin A1c, Fructosamine, and Glycation Markers deep-dive.
Indian Charantia Trials in Newly Diagnosed Type 2 Diabetes
A substantial fraction of the bitter melon clinical trial literature comes from the Indian subcontinent, where bitter melon (karela) has been a staple of both Ayurvedic and modern integrative diabetes practice for generations. These trials are conducted at Indian medical schools and Ayurvedic research centers, and they are sometimes overlooked in Western reviews because of journal-indexing and language considerations — but they constitute an important body of evidence.
Representative trials include:
- Ahmad et al. (1999, Bangladesh) — drinking a homogenized suspension of bitter melon pulp significantly reduced both fasting and postprandial (2 hours after a 75 g glucose drink) glucose in 100 NIDDM (non-insulin-dependent diabetes mellitus) patients (p < 0.001)
- Srivastava et al. (1993) — bitter melon juice produced modest reductions in fasting glucose and glycosylated hemoglobin in type 2 diabetic patients
- Multiple Indian studies of standardized Momordica extracts — consistently showing modest fasting glucose and hemoglobin A1c reductions
The Indian trial literature is generally consistent with the broader meta-analytic findings — bitter melon is a real but modest hypoglycemic agent, well-tolerated at typical doses, and studied mainly as an adjunct in early-stage type 2 diabetes management. Where Indian trials sometimes diverge from Western trials is in the formulation: many Indian trials use fresh juice or unprocessed fruit powder, while many Western trials use standardized extracts. The fresh-juice trials tend to report somewhat larger acute glycemic effects (consistent with the Welihinda 1986 OGTT findings), while the extract trials show more consistent but smaller chronic hemoglobin A1c effects.
Retinopathy: The Eye Complication
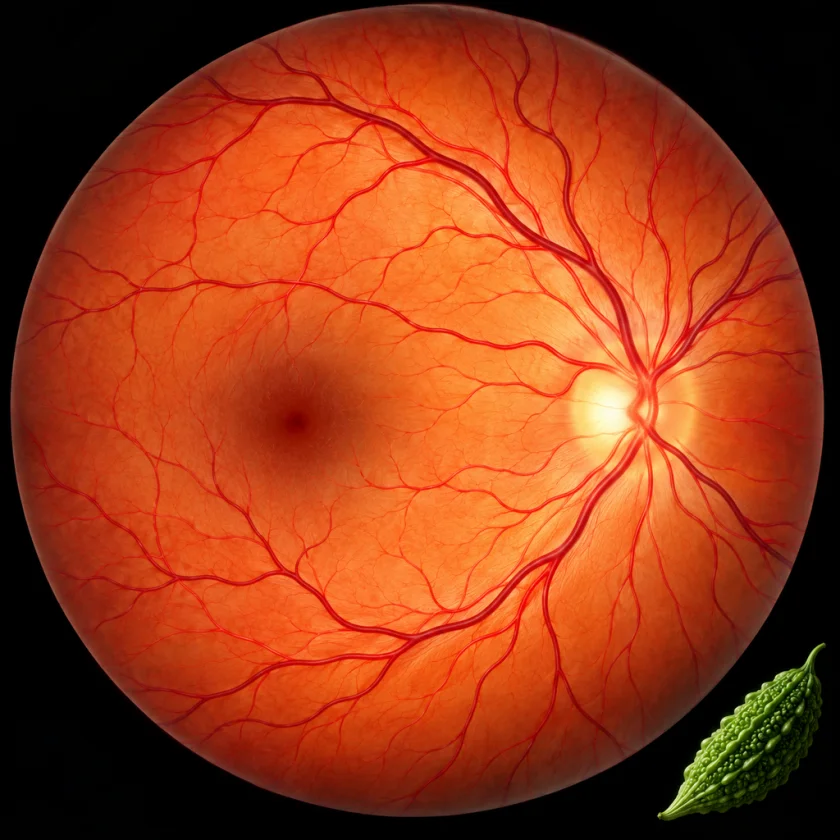
Diabetic retinopathy is the leading cause of new-onset blindness in working-age adults in the developed world. Chronic hyperglycemia damages retinal capillaries through the AGE, oxidative-stress, and polyol-pathway mechanisms discussed above, producing microaneurysms, hemorrhages, exudates, neovascularization (proliferative diabetic retinopathy), and eventually retinal detachment or vitreous hemorrhage.
There are no large randomized controlled trials of bitter melon for retinopathy prevention. The reasonable extrapolation is that whatever hemoglobin A1c reduction bitter melon produces will translate to a proportional reduction in retinopathy risk over time — in the UKPDS 35 analysis of 3,642 people with type 2 diabetes, each 1 percentage point lower updated mean hemoglobin A1c was associated with a 37% lower risk of microvascular complications (mostly retinal laser treatment), a 21% lower risk of any diabetes-related end point and a 14% lower risk of heart attack. This is an observational association between blood-sugar levels and complications, not the measured effect of a particular treatment.
Any such benefit from bitter melon's small hemoglobin A1c effect would be small relative to what metformin or insulin can deliver in patients with higher baseline hemoglobin A1c. In the UKPDS, lower complication risk followed better overall glycemic control; bitter melon may contribute a small part of that overall control. For deeper exploration of the retinopathy mechanism, see the Complications: Retinopathy, Nephropathy, Neuropathy deep-dive.
Nephropathy: The Kidney Complication
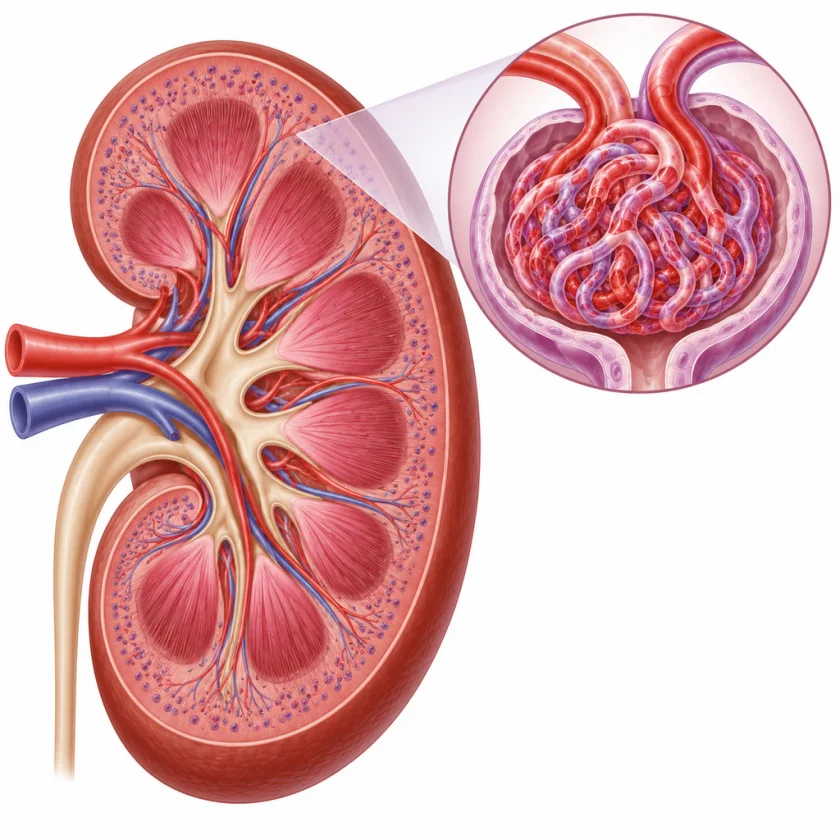
Diabetic nephropathy is the leading cause of end-stage renal disease in the United States and most of the developed world. It begins with hyperfiltration and glomerular hypertrophy, progresses through microalbuminuria (30-300 mg/g creatinine), then macroalbuminuria (above 300 mg/g), and eventually to falling glomerular filtration rate and need for dialysis or transplantation.
Animal-model studies of bitter melon in diabetic nephropathy have shown reductions in proteinuria and improvements in renal histology, attributable to the underlying glucose reduction plus possible direct effects of bitter melon polyphenols on glomerular oxidative stress. Human trials are sparse and small.
A practical caveat: bitter melon's effect on renal function in humans with advanced chronic kidney disease is not well-characterized. For people with chronic kidney disease (CKD) stage 3 or worse there is no safety data: most bitter melon supplements have not been formally evaluated for renal safety, and in chronic kidney disease, where insulin and sulfonylurea levels in the blood are less predictable, an added glucose-lowering effect raises the risk of dangerously low blood sugar (hypoglycemia).
The first-line renoprotective interventions for diabetic nephropathy remain angiotensin-converting enzyme inhibitors (ACE inhibitors) or angiotensin receptor blockers (ARBs), sodium-glucose cotransporter-2 (SGLT2) inhibitors (which have substantial outcome trial evidence for renal protection independent of glucose lowering), and aggressive blood pressure and hemoglobin A1c control. Bitter melon is not a renoprotective drug in the sense that sodium-glucose cotransporter-2 inhibitors are; it is a glucose-lowering plant that may contribute incrementally to the underlying glycemic control upon which renoprotection depends. See the Cardio-Renal Protection: sodium-glucose cotransporter-2 and glucagon-like peptide-1 (GLP-1) deep-dive for the modern pharmacological renoprotective strategy.
Neuropathy: The Nerve Complication
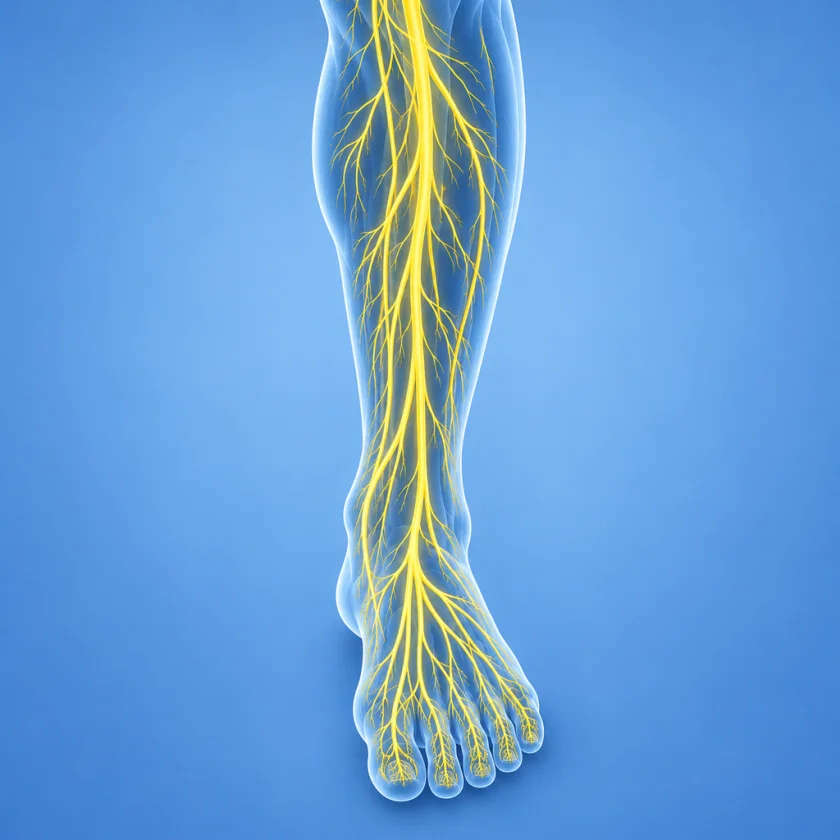
Diabetic peripheral neuropathy affects approximately 50% of patients with long-standing diabetes and is a leading cause of foot ulcers, falls, chronic neuropathic pain, and lower-extremity amputation. The pathology involves damage to small unmyelinated nerve fibers from the same hyperglycemia-driven mechanisms (AGE formation, oxidative stress, polyol pathway) that damage retinal and renal microvasculature.
Bitter melon has not been studied as a primary intervention for established diabetic neuropathy. The reasonable expectation is that whatever hemoglobin A1c reduction bitter melon provides will, over years, slow the progression of neuropathy in patients who do not yet have advanced disease — the same general logic as for retinopathy and nephropathy.
For patients with established diabetic neuropathy, more directly evidence-based interventions include:
- Alpha-lipoic acid (600-1,800 mg/day) — the most studied neuroprotective antioxidant, with the German ALADIN, ORPIL, and SYDNEY trials supporting symptomatic and possibly disease-modifying effect
- Benfotiamine (fat-soluble vitamin B1 derivative) — reduces AGE formation and shows symptomatic benefit in clinical trials
- Vitamin B12 (especially methylcobalamin) — particularly important for patients on long-term metformin, which depletes B12 stores
- Standard pharmacological options — gabapentin, pregabalin, duloxetine for symptomatic neuropathic pain
Bitter melon's role in the neuropathy story is upstream — reducing the chronic hyperglycemic exposure that drives nerve damage in the first place — rather than treating established neuropathy directly.
Macrovascular Disease and Cardiovascular Risk
The macrovascular complications of diabetes — coronary artery disease, cerebrovascular disease, peripheral arterial disease — are statistically the leading cause of death in patients with type 2 diabetes. The mechanism is accelerated atherosclerosis, driven by the combination of hyperglycemia, insulin resistance, dyslipidemia (the diabetic triad of elevated triglycerides, low high-density lipoprotein (HDL), and small-dense low-density lipoprotein (LDL)), hypertension, and the prothrombotic state of poorly controlled diabetes.
Bitter melon has been studied for its lipid-modifying effects, with most trials reporting modest improvements in total cholesterol, low-density lipoprotein, and triglycerides, plus modest increases in high-density lipoprotein, over 8-12 weeks of supplementation. The mechanism is partly attributed to the seed-derived conjugated linolenic acids, which activate peroxisome proliferator-activated receptor alpha and gamma (PPAR-alpha and PPAR-gamma), the same nuclear receptors targeted by the fibrate and thiazolidinedione drug classes.
The cardiovascular outcome trial data — the gold standard evidence for whether an intervention actually prevents heart attacks and strokes — do not exist for bitter melon. The realistic interpretation is that bitter melon contributes to a more favorable metabolic profile (modestly lower glucose, modestly better lipids, modest improvement in insulin sensitivity), which over years would be expected to translate to incrementally reduced macrovascular risk, but the magnitude is modest. The interventions with proven cardiovascular outcome benefit in type 2 diabetes are pharmaceutical: sodium-glucose cotransporter-2 inhibitors (empagliflozin, dapagliflozin, canagliflozin), glucagon-like peptide-1 agonists (semaglutide, liraglutide), and aggressive treatment of hypertension and dyslipidemia.
Bitter Melon as an Adjunct, Not a Substitute
The unifying theme across all of these complication categories is that bitter melon has been studied as an adjunct within a comprehensive metabolic management plan; the trials above tested it either against metformin, where it was weaker, or as an add-on, and none showed it can replace evidence-based pharmaceutical therapy in patients who need it. How the evidence applies to different patient groups:
- Prediabetes (fasting glucose 100-125 mg/dL, hemoglobin A1c 5.7-6.4%) — bitter melon is used as a lifestyle-tier measure alongside dietary modification and exercise; many patients normalize metabolic markers with this combination and do not progress to overt diabetes. Berberine is a more potent alternative in this category and is often chosen by people who want a single-agent botanical with greater potency.
- Newly diagnosed type 2 diabetes (hemoglobin A1c 6.5-7.5%, no complications) — metformin is the usual first-line pharmaceutical agent (cheap, effective, well-tolerated, cardioprotective). Bitter melon is used as a complementary measure when hemoglobin A1c is not at target on metformin alone, or by people who decline metformin and attempt an intensive lifestyle plus botanical strategy with close glucose monitoring.
- Established type 2 diabetes on multiple agents — bitter melon is used as an add-on but is unlikely to substantively change the medication regimen. Modest hemoglobin A1c reduction may permit modest reduction in some medication doses; on several glucose-lowering medicines, an extra fall in blood sugar raises the risk of hypoglycemia, and medication doses are set by the prescribing physician.
- Type 1 diabetes — bitter melon cannot replace insulin. The pancreatic beta cells are absent or destroyed; no oral hypoglycemic agent (botanical or pharmaceutical) addresses that. Bitter melon may modestly reduce insulin requirements through the peripheral mechanisms (glucose transporter type 4 (GLUT4), AMP-activated protein kinase) but is not a substitute for insulin therapy.
- Established microvascular or macrovascular complications — the treatments with evidence for the complications themselves are intensive therapies targeting the specific complication (angiotensin-converting enzyme inhibitor (ACE inhibitor)/angiotensin receptor blocker (ARB) and sodium-glucose cotransporter-2 inhibitor for nephropathy, alpha-lipoic acid and pharmacological pain management for neuropathy, ophthalmology referral and intravitreal therapy for proliferative retinopathy, statin and antihypertensive for macrovascular risk). Bitter melon is an upstream adjunct, not a treatment for the complications themselves.
Cautions and Safety Facts
- Glucose-6-phosphate dehydrogenase (G6PD) deficiency — absolute contraindication for the seeds (vicine content); G6PD deficiency is most common in people of Mediterranean, African, Middle Eastern, or South/Southeast Asian ancestry and is detected by a blood test
- Pregnancy — absolute contraindication; uterine-stimulating activity
- Combination with sulfonylureas, insulin, meglitinides — additive hypoglycemic effect; blood sugar can fall too low, which is why glucose is checked closely and medication doses are sometimes lowered by the prescriber
- Combination with metformin — mild additive effect; usually well-tolerated, with glucose commonly watched for the first 2-4 weeks
- Chronic kidney disease stage 3 or worse — bitter melon's renal safety in advanced chronic kidney disease is not well-characterized, and an added glucose-lowering effect raises the risk of hypoglycemia when insulin and sulfonylurea levels are less predictable
- Not a metformin substitute — in Fuangchan 2011, bitter melon lowered fructosamine less than metformin 1,000 mg/day; the research describes it as an adjunct, not an alternative
- Not a treatment for established complications — retinopathy, advanced nephropathy, and symptomatic neuropathy are treated with condition-specific therapies that have their own evidence base
Key Research Papers
- Fuangchan A, Sonthisombat P, Seubnukarn T, Chanouan R, Chotchaisuwat P, Sirigulsatien V, Ingkaninan K, Plianbangchang P, Haines ST (2011). Hypoglycemic effect of bitter melon compared with metformin in newly diagnosed type 2 diabetes patients. Journal of Ethnopharmacology 134(2):422-428. — PubMed PMID: 21211558
- Yin RV, Lee NC, Hirpara H, Phung OJ (2014). The effect of bitter melon (Mormordica charantia) in patients with diabetes mellitus: a systematic review and meta-analysis. Nutrition & Diabetes 4(12):e145. — PubMed PMID: 25504465
- UK Prospective Diabetes Study (UKPDS) Group (1998). Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). The Lancet 352(9131):837-853. — PubMed PMID: 9742976
- Diabetes Control and Complications Trial Research Group (1993). The effect of intensive treatment of diabetes on the development and progression of long-term complications in insulin-dependent diabetes mellitus. New England Journal of Medicine 329(14):977-986. — PubMed PMID: 8366922
- Stratton IM, Adler AI, Neil HA, Matthews DR, Manley SE, Cull CA, Hadden D, Turner RC, Holman RR (2000). Association of glycaemia with macrovascular and microvascular complications of type 2 diabetes (UKPDS 35): prospective observational study. BMJ 321(7258):405-412. — PubMed PMID: 10938048
- Welihinda J, Karunanayake EH, Sheriff MH, Jayasinghe KS (1986). Effect of Momordica charantia on the glucose tolerance in maturity onset diabetes. Journal of Ethnopharmacology 17(3):277-282. — PubMed PMID: 3807390
- Ahmad N, Hassan MR, Halder H, Bennoor KS (1999). Effect of Momordica charantia (Karolla) extracts on fasting and postprandial serum glucose levels in NIDDM patients. Bangladesh Medical Research Council Bulletin 25(1):11-13. — PubMed PMID: 10758656
- Srivastava Y, Venkatakrishna-Bhatt H, Verma Y, Venkaiah K, Raval BH (1993). Antidiabetic and adaptogenic properties of Momordica charantia extract: an experimental and clinical evaluation. Phytotherapy Research 7(4):285-289. — doi:10.1002/ptr.2650070405
- Tongia A, Tongia SK, Dave M (2004). Phytochemical determination and extraction of Momordica charantia fruit and its hypoglycemic potentiation of oral hypoglycemic drugs in diabetes mellitus (NIDDM). Indian Journal of Physiology and Pharmacology 48(2):241-244. — PubMed PMID: 15521566
- Dans AM, Villarruz MV, Jimeno CA, Javelosa MA, Chua J, Bautista R, Velez GG (2007). The effect of Momordica charantia capsule preparation on glycemic control in type 2 diabetes mellitus needs further studies. Journal of Clinical Epidemiology 60(6):554-559. — PubMed PMID: 17493509
- John AJ, Cherian R, Subhash HS, Cherian AM (2003). Evaluation of the efficacy of bitter gourd (Momordica charantia) as an oral hypoglycemic agent — a randomized controlled clinical trial. Indian Journal of Physiology and Pharmacology 47(3):363-365. — PubMed PMID: 14723327
- Inayat-ur-Rahman, Malik SA, Bashir M, Khan R, Iqbal M (2009). Serum sialic acid changes in non-insulin-dependant diabetes mellitus (NIDDM) patients following bitter melon (Momordica charantia) and rosiglitazone (Avandia) treatment. Phytomedicine 16(5):401-405. — PubMed PMID: 19362455
- Peter EL, Kasali FM, Deyno S, Mtewa A, Nagendrappa PB, Tolo CU, Ogwang PE, Sesaazi D (2019). Momordica charantia L. lowers elevated glycaemia in type 2 diabetes mellitus patients: systematic review and meta-analysis. Journal of Ethnopharmacology 231:311-324. — PubMed PMID: 30385422
- Zhang X, Zhao Y, Song Y, Miao M (2024). Effects of Momordica charantia L. supplementation on glycemic control and lipid profile in type 2 diabetes mellitus patients: a systematic review and meta-analysis of randomized controlled trials. Heliyon 10(10):e31126. — PubMed PMID: 38784554
- Mes JJ, van den Belt M, van der Haar S, Oosterink E, Luijendijk T, Manusama K, van Dam L, de Bie T, Witkamp R, Esser D (2025). Bitter gourd (Momordica charantia L.) supplementation for twelve weeks improves biomarkers of glucose homeostasis in a prediabetic population. Journal of Ethnopharmacology 347:119756. — PubMed PMID: 40199408
- Mkhize SAL, Phoswa WN, Ngubane PS, Mokgalaboni K (2025). Efficacy of Momordica charantia in glycaemic control and insulin resistance among patients with prediabetes and type 2 diabetes. A GRADE-adherent meta-analysis of randomised controlled trials. Metabolism Open 28:100407. — PubMed PMID: 41280283
PubMed Topic Searches
Connections
- All Herbs
- Bitter Melon (Main Page)
- Bitter Melon Benefits Hub
- Bitter Melon for Blood Sugar
- Bitter Melon for Weight Loss
- Bitter Melon Cancer Cell Studies
- Berberine
- Gymnema
- Diabetes
- Insulin Resistance
- Diabetes Complications: Retinopathy, Nephropathy, Neuropathy
- Cardio-Renal Protection: Sodium-Glucose Cotransporter-2 and Glucagon-Like Peptide-1
- Hemoglobin A1c, Fructosamine, and Glycation Markers
- Peripheral Neuropathy
- Alpha-Lipoic Acid for Diabetic Neuropathy
- Benfotiamine for Diabetic Neuropathy
- Hemoglobin A1c
- Fasting Insulin
- Blood Sugar Management
- Metformin — the pharmaceutical comparator that beat every bitter melon dose in the Fuangchan 2011 head-to-head trial.
Featured Videos