⚠ Evidence warning: Clinical trials or other evidence do not support the claim that berberine is an anti-aging caloric restriction mimetic with the strongest combined profile of such agents, that it preferentially removes visceral fat, and that berberine plus lifestyle change can let people stop prescription drugs. This page keeps it as a report of what people, websites or other media say.
Berberine, AMP-Activated Protein Kinase (AMPK) & Metabolic Syndrome
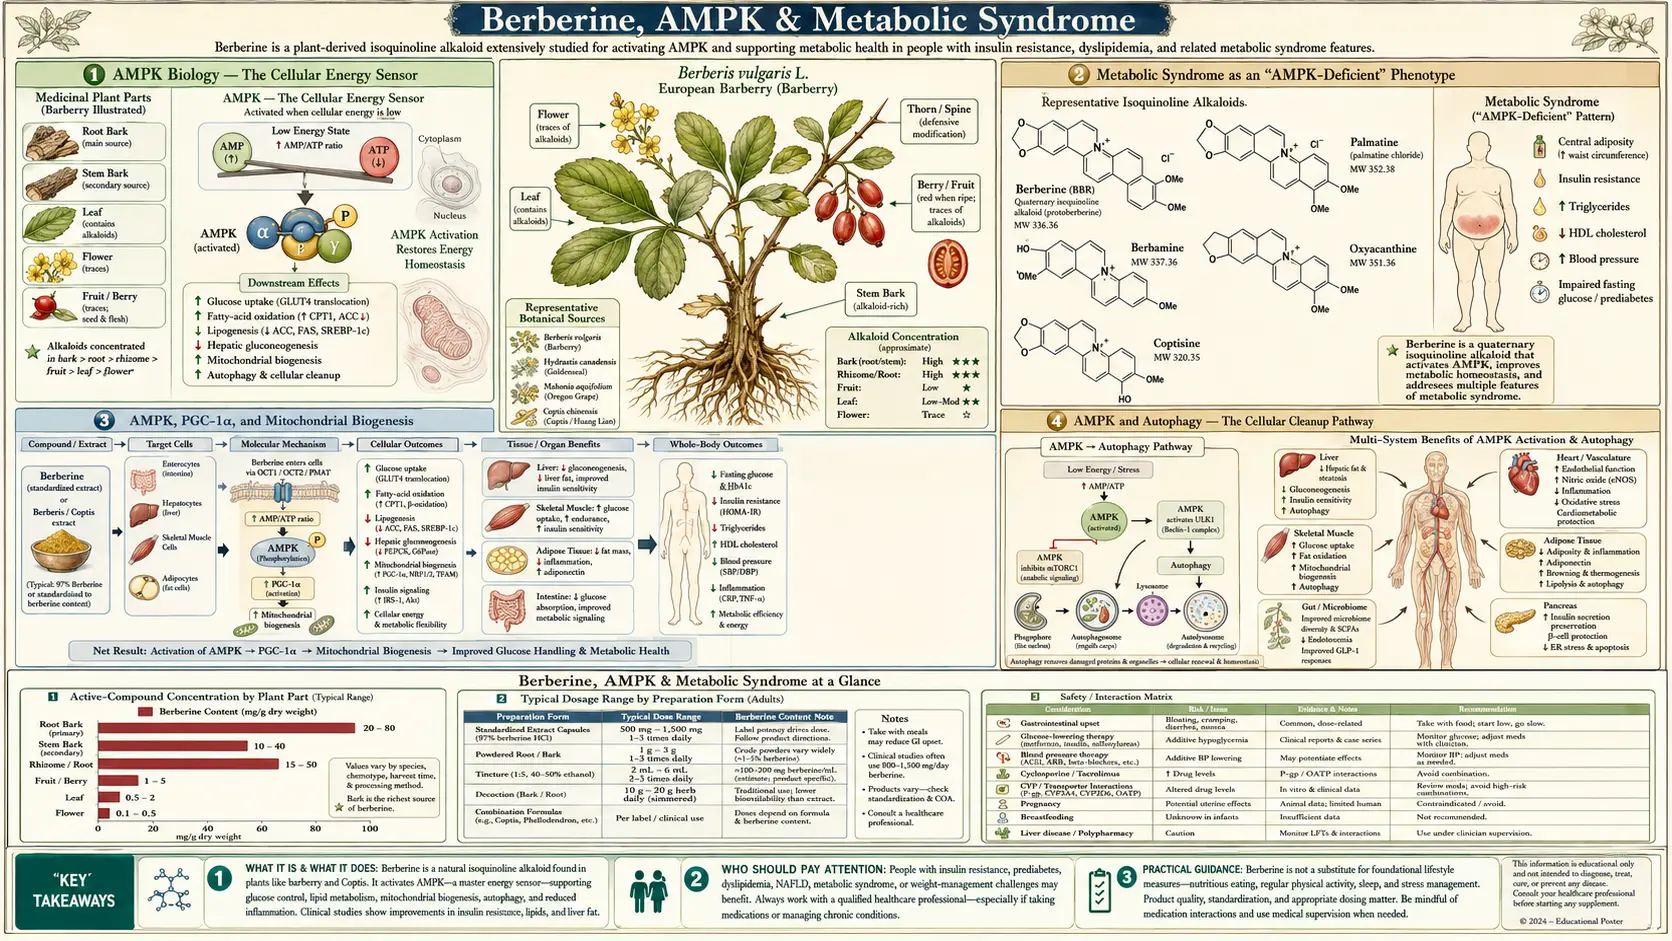
AMP-activated protein kinase (AMPK) is the cellular master switch that decides whether a cell builds or burns. When energy is abundant (high adenosine triphosphate (ATP), low AMP), AMPK is quiet and the cell builds — synthesizes fat, protein, glycogen, cholesterol. When energy is scarce (low adenosine triphosphate, high AMP), AMPK is activated and the cell burns — oxidizes fat, takes up glucose, makes new mitochondria, turns on autophagy. The reason berberine produces simultaneous improvements in glucose, lipids, weight, blood pressure, hepatic steatosis, and polycystic ovary syndrome (PCOS) is that all of these conditions share a common upstream driver: a cellular metabolic state stuck in the "build" mode despite already being energy-replete. Berberine flips the master switch back toward "burn" by activating AMP-activated protein kinase indirectly, through the cell's energy state. This is the same target as metformin and the same effect as caloric restriction and exercise — which is why berberine is sometimes called a "caloric restriction mimetic" in addition to a "metformin mimetic." The Wei 2012 trial in European Journal of Endocrinology found that berberine reduced waist size, waist-to-hip ratio and blood fats and raised sex hormone-binding globulin (SHBG) more than metformin in women with polycystic ovary syndrome and insulin resistance who were also taking an oral contraceptive. This deep-dive walks through the AMP-activated protein kinase biology, the metabolic syndrome cluster as a single AMP-activated protein kinase-deficient phenotype, the polycystic ovary syndrome evidence, the non-alcoholic fatty liver disease (NAFLD) application, the visceral adiposity data, and the practical case for berberine as a multi-target metabolic intervention.
Table of Contents
- AMP-Activated Protein Kinase Biology — The Cellular Energy Sensor
- Metabolic Syndrome as an "AMP-Activated Protein Kinase-Deficient" Phenotype
- AMP-Activated Protein Kinase, PGC-1α, and Mitochondrial Biogenesis
- AMP-Activated Protein Kinase and Autophagy — The Cellular Cleanup Pathway
- The Wei 2012 Polycystic Ovary Syndrome Trial
- Berberine for Polycystic Ovary Syndrome — Beyond the Wei Trial
- Berberine for Non-Alcoholic Fatty Liver Disease (NAFLD)
- Visceral Adipose and Waist Circumference
- Blood Pressure and Endothelial Function
- Inflammation — High-Sensitivity C-Reactive Protein, NF-kappaB, and the Metabolic Inflammasome
- Berberine as a Caloric Restriction Mimetic
- How Berberine Fits Into Metabolic Syndrome Care
- Key Research Papers
- Connections
- Featured Videos
AMP-Activated Protein Kinase Biology — The Cellular Energy Sensor
AMP-activated protein kinase (AMPK) is a heterotrimeric enzyme complex composed of three subunits: an alpha (catalytic) subunit and beta and gamma (regulatory) subunits. The gamma subunit contains four cystathionine-beta-synthase (CBS) domains that bind adenine nucleotides — ATP, ADP, or AMP. The relative occupancy of these binding sites by adenosine triphosphate versus AMP is the cellular energy sensor.
When cellular energy is plentiful (adenosine triphosphate >> AMP), the gamma subunit binds adenosine triphosphate, AMP-activated protein kinase is dephosphorylated and inactive. When cellular energy is scarce (AMP rising relative to adenosine triphosphate, typically because of muscle contraction, hypoxia, glucose deprivation, or mitochondrial inhibition), AMP displaces adenosine triphosphate at the gamma subunit. This conformational change exposes the activating phosphorylation site on the alpha subunit, allowing upstream kinases (LKB1, CaMKKβ) to phosphorylate Thr172. Phosphorylated AMP-activated protein kinase is the active form, with approximately 1,000× greater catalytic activity than the unphosphorylated form.
Once active, AMP-activated protein kinase phosphorylates dozens of downstream substrates to coordinate a global shift from anabolism (building) to catabolism (breaking down):
- Glucose — AMP-activated protein kinase phosphorylates TBC1D1 and TBC1D4 to trigger GLUT4 translocation from intracellular vesicles to the plasma membrane in skeletal muscle, increasing glucose uptake without requiring insulin
- Fatty acids — AMP-activated protein kinase phosphorylates and inhibits acetyl-CoA carboxylase (ACC), reducing malonyl-CoA production, which removes the brake on CPT1-mediated fatty acid transport into mitochondria for oxidation
- Cholesterol — AMP-activated protein kinase phosphorylates and inhibits HMG-CoA reductase, the rate-limiting enzyme of cholesterol synthesis. This is a partial overlap with the statin mechanism (see the cholesterol deep-dive).
- Glycogen — AMP-activated protein kinase inhibits glycogen synthase (reducing glycogen storage) and activates glycogen phosphorylase (releasing stored glucose)
- Protein synthesis — AMP-activated protein kinase inhibits mTORC1, which is the central regulator of protein synthesis. This is the mechanism by which AMP-activated protein kinase activation overlaps with the longevity-extending effects of caloric restriction and rapamycin.
- Hepatic gluconeogenesis — AMP-activated protein kinase inhibits the transcriptional coactivators (CRTC2/TORC2, CREB) that drive expression of the gluconeogenic enzymes PEPCK and G6Pase. This is the principal mechanism by which AMP-activated protein kinase reduces hepatic glucose output and is a major contributor to the glycemic effects of both metformin and berberine.
The net cellular phenotype of AMP-activated protein kinase activation is exactly what is needed in metabolic syndrome: more glucose uptake, more fat burning, less fat storage, less cholesterol synthesis, less hepatic glucose output, less protein synthesis (less anabolic muscle growth in the short term, but more cellular cleanup and longevity signaling in the long term).
Metabolic Syndrome as an "AMP-Activated Protein Kinase-Deficient" Phenotype
Metabolic syndrome is the constellation of central obesity (waist circumference >40 inches in men, >35 inches in women), elevated triglycerides (>150 mg/dL), low high-density lipoprotein (HDL) (<40 in men, <50 in women), elevated blood pressure (>130/85), and elevated fasting glucose (>100 mg/dL). Three of these five criteria diagnose the syndrome.
The mechanistic unification of these seemingly disparate features comes through insulin resistance and the metabolic state that drives it. The visceral adipocyte under conditions of chronic energy surplus accumulates large amounts of triglyceride, becomes dysfunctional, secretes inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, MCP-1), and exports free fatty acids and adipokines that drive insulin resistance in liver and muscle. The liver, receiving the portal-vein flood of free fatty acids and fructose, accumulates triglyceride (the non-alcoholic fatty liver disease phenotype), becomes insulin resistant, and continues to produce glucose despite elevated insulin (the hyperglycemia of insulin resistance). The skeletal muscle, also insulin resistant, fails to take up post-prandial glucose. The pancreatic beta cells compensate by secreting more insulin (the hyperinsulinemia phase), then progressively fail (the diabetes phase).
What ties all of this together is that AMP-activated protein kinase activity is suppressed in the metabolic syndrome state. Studies in adipose tissue, liver, and skeletal muscle from metabolic syndrome patients consistently show reduced AMP-activated protein kinase phosphorylation and reduced AMP-activated protein kinase activity compared to lean insulin-sensitive controls. The reason for this is partly direct (high cellular adenosine triphosphate from the chronic energy surplus, reduced AMP) and partly indirect (inflammatory cytokines suppress AMP-activated protein kinase activity; ceramide accumulation from fatty acid spillover suppresses AMP-activated protein kinase).
The implication drawn from this is that any intervention that activates AMP-activated protein kinase would be expected to reverse the underlying metabolic dysfunction simultaneously across all the manifestations:
- Caloric restriction does this — chronically reduces caloric intake, raises cellular AMP:ATP, activates AMP-activated protein kinase
- Exercise does this — acutely raises AMP:ATP during contraction, chronically improves AMP-activated protein kinase responsiveness
- Metformin does this — pharmacologically activates AMP-activated protein kinase through mitochondrial complex I inhibition
- Berberine does this — activates AMP-activated protein kinase indirectly, through the same kind of mitochondrial complex I inhibition as metformin; a 2008 study found this activation did not depend on LKB1
How berberine switches on AMP-activated protein kinase, in plain words: berberine slows the first step of the cell's power-plant chain inside the mitochondria (respiratory complex I). The cell then makes less energy, senses an energy shortfall, and AMP-activated protein kinase turns on. In a 2008 study in muscle cells, isolated mitochondria and high-fat-fed rodents, Turner and colleagues found that berberine inhibited complex I in a way similar to metformin and rosiglitazone, and that its activation of AMP-activated protein kinase did not rely on either of the upstream kinases LKB1 or CaMKKβ. Berberine therefore does not act on AMP-activated protein kinase directly; it works through the cell's energy state.
This is why berberine produces simultaneous improvement in glucose, lipids, blood pressure, weight, and inflammation — the apparent multi-target effect is actually a single-target effect on AMP-activated protein kinase propagating through the entire metabolic syndrome cluster.
A 2025 meta-analysis of randomized placebo-controlled trials in metabolic syndrome (Liu and colleagues, Frontiers in Pharmacology) found that berberine lowered triglycerides (by about 0.37 mmol/L), fasting blood glucose (about 0.52 mmol/L), waist size (about 3.3 cm) and low-density lipoprotein (LDL) cholesterol (about 0.50 mmol/L) compared with placebo. It found no significant effect on high-density lipoprotein (HDL) cholesterol or on systolic or diastolic blood pressure, and side effects did not differ between berberine and placebo.
AMP-Activated Protein Kinase, PGC-1α, and Mitochondrial Biogenesis
Beyond the immediate metabolic shifts, AMP-activated protein kinase activation triggers mitochondrial biogenesis — the production of new mitochondria. The pathway is: AMP-activated protein kinase phosphorylates and activates PGC-1α (peroxisome proliferator-activated receptor gamma coactivator-1 alpha), the master transcriptional coactivator for mitochondrial biogenesis. PGC-1α then coactivates a network of transcription factors (NRF1, NRF2, TFAM, ERR-alpha) that drive expression of both the nuclear-encoded mitochondrial proteins and the mitochondrial-DNA-encoded ones, leading to assembly of new mitochondria.
More mitochondria per cell means more oxidative capacity, more fatty acid oxidation potential, less dependence on glycolysis for adenosine triphosphate, and improved aerobic capacity. This is the molecular basis for the exercise-adaptation phenotype — trained skeletal muscle has 50-100% more mitochondria per cell than untrained muscle, with proportionally improved fat-burning capacity.
Berberine's AMP-activated protein kinase activation drives the same mitochondrial biogenesis program. Studies in cultured cells and in rodent models have shown that chronic berberine treatment increases mitochondrial density and oxidative capacity in skeletal muscle, brown adipose tissue, and liver. The clinical translation in humans is less directly measured but is implied by the improvements in exercise tolerance, the reduction in resting fatigue, and the improvement in aerobic fitness measures reported in some clinical trials.
For metabolic syndrome patients, the mitochondrial biogenesis effect is therapeutically important because metabolic syndrome is associated with reduced mitochondrial density and function (the "mitochondrial dysfunction hypothesis" of insulin resistance). Restoring mitochondrial number and function via AMP-activated protein kinase activation addresses one of the root drivers of the syndrome rather than just managing the downstream lab abnormalities.
AMP-Activated Protein Kinase and Autophagy — The Cellular Cleanup Pathway
Autophagy is the cellular process by which damaged organelles, misfolded proteins, and other cellular debris are sequestered in double-membrane autophagosomes and delivered to lysosomes for degradation. The breakdown products (amino acids, lipids, nucleotides) are recycled for new biosynthesis. Autophagy is most active during fasting, exercise, and other low-energy states — it is the cell's way of generating substrates from internal stores when external substrates are unavailable.
AMP-activated protein kinase is one of the principal upstream activators of autophagy. AMP-activated protein kinase phosphorylates and activates ULK1 (the mammalian homolog of yeast Atg1), the kinase that initiates autophagosome formation. AMP-activated protein kinase also inhibits mTORC1, which is normally suppressive of autophagy — so AMP-activated protein kinase activates autophagy by two converging mechanisms.
The implications for metabolic disease and longevity:
- Damaged mitochondria (a feature of metabolic syndrome) are cleared via mitophagy, a specialized form of autophagy. AMP-activated protein kinase activation enhances mitophagy and removes the dysfunctional mitochondria that otherwise contribute to insulin resistance and oxidative stress.
- Misfolded protein aggregates (a feature of aging and neurodegeneration) are cleared via aggrephagy. AMP-activated protein kinase activation by berberine, metformin, or caloric restriction has been investigated for potential cognitive benefits through this pathway.
- Excess lipid droplets in hepatocytes (the non-alcoholic fatty liver disease phenotype) are cleared via lipophagy, a specialized autophagy that delivers lipid droplets to lysosomes for breakdown by lysosomal acid lipase. AMP-activated protein kinase activation by berberine enhances hepatocyte lipophagy and is one mechanism for its effects on non-alcoholic fatty liver disease.
- Senescent cells (a hallmark of aging) accumulate at higher rates when autophagy is impaired; AMP-activated protein kinase activation may slow senescence accumulation.
The autophagy effects of berberine are mostly inferred from the AMP-activated protein kinase pathway and from animal-model evidence rather than directly measured in humans, but they form part of the rationale for berberine in age-related metabolic decline and as a "caloric restriction mimetic."
The Wei 2012 Polycystic Ovary Syndrome Trial
The 2012 Wei, Zhao, Wang, et al. trial published in European Journal of Endocrinology is the foundational clinical evidence for berberine in polycystic ovary syndrome (PCOS). The investigators randomized 89 women with polycystic ovary syndrome and insulin resistance to three groups; every group also took compound cyproterone acetate (an oral contraceptive):
- Berberine 500 mg three times daily plus compound cyproterone acetate for 3 months (31 women)
- Metformin 500 mg three times daily plus compound cyproterone acetate for 3 months (30 women)
- Placebo plus compound cyproterone acetate for 3 months (28 women)
Outcomes were measured at 3 months and included body measurements, lipid profile, glucose and insulin (homeostatic model assessment of insulin resistance, HOMA-IR), and sex hormone-binding globulin. Key findings reported by the trial:
- Waist circumference and waist-to-hip ratio reduction: berberine produced larger reduction than metformin (statistically significant)
- Lipid profile: berberine produced larger improvements in total cholesterol, low-density lipoprotein (LDL), triglycerides, and high-density lipoprotein than metformin
- Homeostatic model assessment of insulin resistance: berberine lowered it significantly compared with placebo; the trial reported no advantage of berberine over metformin on this measure
- Fasting blood glucose and fasting insulin: berberine lowered both compared with placebo; the trial reported no advantage of berberine over metformin on these measures
- SHBG (sex hormone binding globulin): berberine produced greater increase than metformin and than placebo
A later trial (An 2014, Clinical Endocrinology) randomized 150 infertile women with polycystic ovary syndrome to berberine, metformin or placebo for 3 months before ovarian stimulation for IVF. Both berberine and metformin raised the pregnancy rate and lowered the rate of severe ovarian hyperstimulation syndrome compared with placebo. Compared with metformin, berberine was associated with lower body mass index, lower blood fats, a lower total follicle-stimulating hormone (FSH) requirement, a higher live birth rate and fewer gastrointestinal side effects; the authors concluded that berberine "achieved more live births with fewer side effects than metformin."
On the measures it reported, berberine outperformed metformin on waist size, waist-to-hip ratio, blood fats and SHBG. The Wei trial was not designed as a non-inferiority trial; its authors concluded that berberine "improved some of the metabolic and hormonal derangements" in the Chinese women they treated and that further controlled studies are needed.
Berberine for Polycystic Ovary Syndrome — Beyond the Wei Trial
Polycystic ovary syndrome is the most common endocrine disorder in reproductive-age women, affecting approximately 5-10% of the population. The pathophysiology is dominated by insulin resistance — the same metabolic-syndrome cluster discussed above, but with the addition of androgen excess driven by insulin's direct stimulation of ovarian theca-cell androgen production. The result is a phenotype of:
- Menstrual irregularity or amenorrhea (anovulation)
- Hyperandrogenism (acne, hirsutism, male-pattern hair loss)
- Polycystic ovarian morphology on ultrasound
- Insulin resistance (often with frank acanthosis nigricans)
- Central obesity, dyslipidemia, increased cardiovascular risk
- Infertility from anovulation
- Increased risk of type 2 diabetes (40-50% lifetime risk), endometrial hyperplasia, and gestational diabetes
The conventional pharmacotherapy is metformin (for the insulin resistance), oral contraceptives (for the androgen excess and endometrial protection), spironolactone (for hirsutism), and letrozole or clomiphene (for ovulation induction in patients seeking pregnancy). The combination is effective but the pill burden is substantial and the long-term safety of multi-decade contraceptive use in this population is debated.
Berberine's appeal in polycystic ovary syndrome:
- Addresses the insulin resistance directly (same mechanism as metformin)
- Reduces visceral adiposity (the Wei 2012 waist-to-hip ratio benefit)
- Improves lipid profile simultaneously
- Increases SHBG, which reduces free androgens
- Improves menstrual regularity and ovulation rates
- Single agent producing improvements across multiple polycystic ovary syndrome dimensions
- Safety profile favorable for younger reproductive-age women, with the critical exception that berberine is regarded as contraindicated in pregnancy (kernicterus risk in the fetus), which is why practitioner protocols stop it before attempted conception
The regimen practitioners describe for polycystic ovary syndrome:
- Berberine, usually described at 500 mg three times daily with meals, as the primary metabolic agent
- Often combined with inositol (myo-inositol 2 g + D-chiro-inositol 50 mg, twice daily) — the inositol literature in polycystic ovary syndrome is independently strong; the combination is mechanistically complementary. See the Inositol page.
- Lifestyle change (Mediterranean or low-glycemic diet, 150 minutes/week of activity, weight loss of 5-10% in people with a body mass index (BMI) >25)
- Spironolactone, used for hirsutism
- Oral contraceptives, which this approach reserves for when hormonal contraception is needed anyway rather than using them as the primary polycystic ovary syndrome therapy
- Berberine stopped 1-2 menstrual cycles before attempted conception and resumed after delivery and breastfeeding
For more on polycystic ovary syndrome, see the polycystic ovary syndrome main page.
Berberine for Non-Alcoholic Fatty Liver Disease (NAFLD)
Non-alcoholic fatty liver disease (NAFLD), now called metabolic dysfunction-associated steatotic liver disease (MASLD) after a 2023 multisociety consensus, is the most common chronic liver disease worldwide, affecting approximately 25% of the global adult population. The pathophysiology is hepatic insulin resistance driving de novo lipogenesis (the liver synthesizes triglycerides from carbohydrate substrates), combined with reduced fatty acid oxidation (impaired mitochondrial function). The accumulated triglyceride forms lipid droplets that crowd hepatocyte cytoplasm and impair function.
Berberine's mechanisms address non-alcoholic fatty liver disease on multiple fronts:
- AMP-activated protein kinase activation — inhibits ACC, reducing de novo lipogenesis; increases fatty acid oxidation via CPT1 release
- Low-density lipoprotein-receptor upregulation — pulls cholesterol-containing lipoproteins out of circulation, reducing the substrate pool for further hepatic triglyceride synthesis
- Lipophagy — AMP-activated protein kinase-mediated autophagy of intrahepatocyte lipid droplets
- Reduced metabolic endotoxemia — gut-microbiome modulation reduces circulating lipopolysaccharide (LPS), which would otherwise drive Kupffer-cell inflammation and progression toward non-alcoholic steatohepatitis (NASH)
- Mitochondrial biogenesis — new mitochondria restore oxidative capacity and reduce reliance on glycolysis
Clinical trials of berberine in non-alcoholic fatty liver disease have shown:
- Hepatic steatosis reduction measured by proton magnetic resonance spectroscopy (1H MRS): in the Yan 2015 trial (184 patients, 16 weeks), liver fat content fell by 52.7% with berberine 0.5 g three times daily plus lifestyle change, versus 36.4% with lifestyle change alone (p=0.008)
- Transaminase (alanine aminotransferase (ALT), aspartate aminotransferase (AST)) reductions: a 2024 meta-analysis of 10 randomized trials with 811 patients found lower ALT, AST and gamma-glutamyl transferase (GGT) with berberine
- Improvements in homeostatic model assessment of insulin resistance and metabolic syndrome criteria: the same meta-analysis found lower HOMA-IR, triglycerides and total cholesterol, and Yan 2015 found greater improvement in HOMA-IR and blood fats than lifestyle change alone
- Modest weight loss: in Yan 2015, weight fell by 4.29 kg with berberine plus lifestyle change versus 1.99 kg with lifestyle change alone, and waist size by 4.84 cm versus 2.14 cm, over 16 weeks
- Favorable safety profile in patients with mild-to-moderate steatosis: side effects in Yan 2015 were mild and mainly digestive, and the 2024 meta-analysis reported only mild gastrointestinal side effects
Not every trial agrees. The larger BRAVO trial (2026; 337 adults with obesity and fatty liver but no diabetes, berberine 1 g a day for 6 months) found no reduction in liver fat on computed tomography (CT) scans compared with placebo; its findings are described in the visceral fat section below and on the Berberine and Fatty Liver Disease page.
The use case practitioners describe is people with confirmed non-alcoholic fatty liver disease (an elevated controlled attenuation parameter (CAP) on vibration-controlled transient elastography, a liver stiffness scan, or a raised MRI proton density fat fraction (MRI-PDFF)), no significant fibrosis (liver stiffness <8 kPa), and the metabolic syndrome cluster as the underlying driver. The Yan 2015 trial tested berberine 0.5 g three times daily plus lifestyle change for 16 weeks in this kind of patient. With significant fibrosis (liver stiffness >8 kPa, F2 or higher) the disease is more advanced; prescription treatments (resmetirom, vitamin E in people without diabetes) plus lifestyle change are the main options at that stage, and berberine is described as an add-on rather than the primary treatment.
Prescription options for the inflamed, scarred stage now have phase 3 data. In the MAESTRO-NASH trial (2024; 966 adults with biopsy-confirmed steatohepatitis and fibrosis), resmetirom 80 mg or 100 mg once daily resolved the steatohepatitis without worsening fibrosis in 25.9% and 29.9% of patients versus 9.7% on placebo at 52 weeks, and improved fibrosis by at least one stage in 24.2% and 25.9% versus 14.2%. In the ESSENCE trial (2025; first 800 of 1,197 patients with metabolic dysfunction-associated steatohepatitis (MASH) and moderate or advanced scarring, fibrosis stage 2 or 3), once-weekly semaglutide 2.4 mg resolved the steatohepatitis without worsening fibrosis in 62.9% versus 34.3% on placebo, and reduced fibrosis in 36.8% versus 22.4% at week 72. Gastrointestinal side effects were more common with both drugs than with placebo.
For more on non-alcoholic fatty liver disease, see the Non-Alcoholic Fatty Liver Disease page.
Visceral Adipose and Waist Circumference
Visceral adipose tissue (VAT) — the fat stored within the abdominal cavity around internal organs, distinct from subcutaneous fat — is the metabolically dangerous fat depot. Visceral fat secretes pro-inflammatory cytokines (tumor necrosis factor-alpha and interleukin-6 (IL-6)) into the portal venous drainage that goes directly to the liver, drives hepatic insulin resistance, and contributes to the metabolic syndrome cluster.
Findings on berberine and visceral adiposity are mixed. Reported effects include:
- Waist circumference reductions of 2-5 cm over 3-6 months at standard dosing
- Waist-to-hip ratio improvements (the Wei 2012 polycystic ovary syndrome trial showed this clearly)
- Magnetic resonance imaging- or computed tomography-measured visceral fat area reductions reported in several trials
- A disproportionate effect on visceral vs subcutaneous fat, as some sources describe it — that berberine preferentially reduces VAT while sparing subcutaneous depots
The largest placebo-controlled trial so far, BRAVO (published January 2026 in JAMA Network Open), enrolled 337 adults with obesity and fatty liver (MASLD) but no diabetes at 11 hospitals in China. Berberine 1 g a day for 6 months did not reduce visceral fat area or liver fat content on computed tomography scans compared with placebo. Berberine did lower low-density lipoprotein cholesterol (by about 7.7 mg/dL), apolipoprotein B (by about 3.4 mg/dL) and high-sensitivity C-reactive protein (by about 0.07 mg/dL) more than placebo, and adverse events were about as common in both groups.
The mechanism involves both the direct AMP-activated protein kinase-mediated increase in fatty acid oxidation in adipocytes and the indirect effect through improved insulin sensitivity (insulin normally suppresses lipolysis; in insulin-resistant adipocytes, lipolysis is uninhibited and contributes to the free fatty acid spillover that drives hepatic and muscle insulin resistance). Restoring insulin sensitivity in adipocytes via AMP-activated protein kinase activation re-establishes appropriate lipolytic control.
On this reasoning, berberine is described as producing modest weight loss (2-4 kg over 3-6 months) with a favorable body composition shift (loss of visceral fat, relative preservation of muscle mass). This is similar in magnitude to the weight loss seen with metformin but smaller than with glucagon-like peptide-1 (GLP-1) receptor agonists (semaglutide, tirzepatide), which produced about 15-21% weight loss in their main trials (semaglutide 14.9% at 68 weeks in STEP 1; tirzepatide 15.0-20.9% at 72 weeks in SURMOUNT-1) but at substantially higher cost and with their own side-effect profile.
Blood Pressure and Endothelial Function
Berberine produces modest reductions in blood pressure in hypertensive patients and improves endothelial function (measured by flow-mediated dilation of the brachial artery) in metabolic syndrome patients. The Lan 2015 meta-analysis (27 randomized trials, 2,569 patients) included blood pressure as an endpoint and reported that berberine with lifestyle change tended to lower blood pressure more than lifestyle change alone or placebo, and that berberine added to blood-pressure drugs tended to lower it more than the same drugs alone. A 2025 meta-analysis of placebo-controlled trials in metabolic syndrome found no significant effect of berberine on systolic or diastolic blood pressure.
The mechanisms appear to be:
- Improved endothelial nitric oxide synthase (eNOS) activity, increasing NO production and vasodilation
- Reduced oxidative stress in the vascular wall
- Direct effect on vascular smooth muscle calcium handling
- Indirect effects through improved insulin sensitivity (hyperinsulinemia is a known driver of sympathetic nervous system activity and sodium retention)
- Anti-inflammatory effects in the vascular wall
Practitioners describe berberine as an add-on rather than a substitute for standard antihypertensive therapy in stage 2 hypertension (systolic >140 or diastolic >90), and as an adjunct for people with stage 1 hypertension (130-139 systolic) and the metabolic syndrome cluster who want a multi-target approach. The modest blood pressure effect adds to the other metabolic benefits.
Inflammation — High-Sensitivity C-Reactive Protein, NF-kappaB, and the Metabolic Inflammasome
Metabolic syndrome is a low-grade chronic inflammatory state. The visceral adipose tissue secretes pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, MCP-1) that elevate circulating C-reactive protein (CRP), drive insulin resistance, and contribute to atherosclerotic plaque formation and progression. The NF-kappaB transcription factor pathway is the central driver of this chronic inflammation, and the NLRP3 inflammasome is the principal sensor that detects metabolic stress (saturated fatty acids, cholesterol crystals, hyperglycemia) and activates the inflammatory cascade.
Berberine has well-documented anti-inflammatory effects through multiple pathways:
- Direct inhibition of NF-kappaB activation, reducing transcription of pro-inflammatory cytokine genes
- Inhibition of the NLRP3 inflammasome, reducing interleukin-1-beta processing and secretion
- Reduction in circulating interleukin-6, tumor necrosis factor-alpha, and high-sensitivity C-reactive protein (hs-CRP) in clinical trials
- AMP-activated protein kinase-mediated suppression of inflammatory signaling (AMP-activated protein kinase and NF-kappaB are reciprocally regulated)
- Reduced metabolic endotoxemia through gut-microbiome modulation (lower circulating lipopolysaccharide, lower TLR4 signaling)
The clinical translation: high-sensitivity C-reactive protein reductions of 20-30% are typical with berberine therapy, which is in the same range as moderate-dose statins. For patients with metabolic syndrome and elevated high-sensitivity C-reactive protein (a marker of residual cardiovascular risk), berberine adds anti-inflammatory benefit on top of its lipid and glycemic effects.
Berberine as a Caloric Restriction Mimetic
Caloric restriction (typically 20-40% reduction in caloric intake without malnutrition) is one of the most reliable interventions for extending lifespan in animal models. The mechanisms include AMP-activated protein kinase activation, mechanistic target of rapamycin (mTOR) inhibition, sirtuin (SIRT1, SIRT3) activation, autophagy induction, mitochondrial biogenesis, and reduced oxidative damage. These pathways converge to produce a phenotype of metabolic flexibility, mitochondrial efficiency, and resistance to age-related decline.
"Caloric restriction mimetics" are interventions that activate the same downstream pathways without requiring actual caloric restriction. The best-studied are:
- Metformin — AMP-activated protein kinase activation, mechanistic target of rapamycin inhibition; the TAME (Targeting Aging with Metformin) trial is testing longevity effects in humans
- Rapamycin — direct mechanistic target of rapamycin inhibition; extends lifespan in multiple animal models
- Resveratrol — SIRT1 activation; effects in humans modest and inconsistent
- Nicotinamide adenine dinucleotide (NAD+) precursors (nicotinamide riboside (NR), nicotinamide mononucleotide (NMN)) — restore declining nicotinamide adenine dinucleotide levels that limit sirtuin activity
- Berberine — AMP-activated protein kinase activation, mechanistic target of rapamycin inhibition, autophagy induction, mitochondrial biogenesis
Berberine arguably has the strongest combined profile of any of these — it activates AMP-activated protein kinase robustly, inhibits mechanistic target of rapamycin indirectly through AMP-activated protein kinase, induces autophagy, drives mitochondrial biogenesis, and has documented effects on the metabolic syndrome cluster that is the proximate clinical manifestation of aging-related metabolic decline. The longevity claim for berberine is not yet supported by direct human evidence (no equivalent of the TAME trial exists for berberine), but the mechanistic case is strong.
Within the "metabolic healthspan" framing, practitioners describe berberine as one component of an anti-aging approach that includes:
- Time-restricted eating or periodic fasting (the actual caloric restriction)
- Regular exercise (the AMP-activated protein kinase and mitochondrial biogenesis inducer)
- Mediterranean or low-carb dietary pattern
- Berberine, usually described at 500 mg three times daily, as a caloric restriction mimetic
- Adjuncts some practitioners add: low-dose metformin, nicotinamide adenine dinucleotide precursor, omega-3 fatty acids, vitamin D, magnesium
This framework is preventive metabolic care rather than evidence-based longevity therapy — the human longevity trials are not yet done.
How Berberine Fits Into Metabolic Syndrome Care
The berberine-based approach to metabolic syndrome that integrative practitioners describe has these parts:
- Diagnostic confirmation — waist circumference, hemoglobin A1c (HbA1c), fasting glucose, fasting insulin, full lipid panel, high-sensitivity C-reactive protein, alanine aminotransferase/aspartate aminotransferase, blood pressure. Metabolic syndrome is diagnosed when 3 of the 5 criteria are met. Vibration-controlled transient elastography (a liver stiffness scan) or MRI-PDFF measures liver fat and scarring when non-alcoholic fatty liver disease is suspected.
- Lifestyle foundation — Mediterranean or low-glycemic diet, 150-300 minutes/week of moderate-intensity activity (mix of aerobic and resistance), 7-9 hours of sleep per night, alcohol limit, smoking cessation. Practitioners treat this as the foundation, with medicines and supplements as add-ons.
- Berberine 500 mg three times daily with meals — the primary supplement in this approach (the Yan 2015 fatty-liver trial used 0.5 g three times daily with lifestyle change for 16 weeks). Practitioners describe raising the dose over 2-3 weeks to reduce gastrointestinal side effects.
- Supplements practitioners add for particular lab results:
- Omega-3 eicosapentaenoic acid (EPA)/docosahexaenoic acid (DHA) 2-4 g/day when triglycerides are elevated
- Magnesium glycinate 400 mg/day — described as broadly supportive of insulin sensitivity
- Vitamin D3 2,000-5,000 international units (IU)/day when serum 25-OH-D is <40 ng/mL
- Inositol (myo + D-chiro combination) when polycystic ovary syndrome or insulin resistance is prominent
- Coenzyme Q10 100-200 mg/day for people taking a statin
- N-acetylcysteine (NAC) 600 mg twice daily when non-alcoholic fatty liver disease is prominent
- Prescription medications used according to which metabolic syndrome features dominate:
- Metformin when hemoglobin A1c is >6.0%, sometimes combined with berberine
- Low-to-moderate dose statin when low-density lipoprotein is >160 or cardiovascular risk is elevated
- Sodium-glucose cotransporter-2 (SGLT2) inhibitor (empagliflozin, dapagliflozin) when hemoglobin A1c remains elevated despite metformin + berberine
- Glucagon-like peptide-1 receptor agonist (semaglutide, tirzepatide) when significant weight loss is the priority
- Angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB) when blood pressure is >130/80 with a concurrent kidney or cardiac concern
- Monitoring schedule — full metabolic syndrome labs rechecked at 3 months, 6 months, then annually if stable, with the regimen adjusted to the response.
- Reassessment at each visit of whether prescription medications can be reduced as metabolic improvement occurs. Practitioners report that berberine + lifestyle sometimes allows one or more prescription drugs to be stopped over 12-24 months.
For more on metabolic syndrome and related conditions, see the Metabolic Syndrome page, the Insulin Resistance page, and the Blood Sugar Remedies page.
Key Research Papers
- Wei W, Zhao H, Wang A, et al. (2012). A clinical study on the short-term effect of berberine in comparison to metformin on the metabolic characteristics of women with polycystic ovary syndrome. European Journal of Endocrinology 166(1):99-105. — PubMed PMID: 22019891
- Lee YS, Kim WS, Kim KH, et al. (2006). Berberine, a natural plant product, activates AMP-activated protein kinase with beneficial metabolic effects in diabetic and insulin-resistant states. Diabetes 55(8):2256-2264. — PubMed PMID: 16873688
- Turner N, Li JY, Gosby A, et al. (2008). Berberine and its more biologically available derivative, dihydroberberine, inhibit mitochondrial respiratory complex I: a mechanism for the action of berberine to activate AMP-activated protein kinase and improve insulin action. Diabetes 57(5):1414-1418. — PubMed PMID: 18285556
- Hardie DG (2014). AMPK — sensing energy while talking to other signaling pathways. Cell Metabolism. — PubMed PMID: 25448702
- Yin J, Gao Z, Liu D, Liu Z, Ye J (2008). Berberine improves glucose metabolism through induction of glycolysis. American Journal of Physiology — Endocrinology and Metabolism 294(1):E148-E156. — PubMed PMID: 17971514
- Yan HM, Xia MF, Wang Y, et al. (2015). Efficacy of berberine in patients with non-alcoholic fatty liver disease. PLoS One. — PubMed PMID: 26252777
- Hu Y, Davies GE (2010). Berberine inhibits adipogenesis in high-fat diet-induced obesity mice. Fitoterapia. — PubMed PMID: 19861153
- An Y, Sun Z, Zhang Y, Liu B, Guan Y, Lu M (2014). The use of berberine for women with polycystic ovary syndrome undergoing IVF treatment. Clinical Endocrinology 80(3):425-431. — PubMed PMID: 23869585
- Cao C, Su M (2019). Effects of berberine on glucose-lipid metabolism, inflammatory factors and insulin resistance in patients with metabolic syndrome. Experimental and Therapeutic Medicine 17(4):3009-3014. (An 80-patient study adding berberine to usual Western treatment, not a placebo-controlled trial.) — PubMed PMID: 30936971
- Brusq JM, Ancellin N, Grondin P, et al. (2006). Inhibition of lipid synthesis through activation of AMP kinase: an additional mechanism for the hypolipidemic effects of berberine. Journal of Lipid Research 47(6):1281-1288. — PubMed PMID: 16508037
- Lan J, Zhao Y, Dong F, Yan Z, Zheng W, Fan J, Sun G (2015). Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension. Journal of Ethnopharmacology 161:69-81. — PubMed PMID: 25498346
- Liu D, Zhao H, Zhang Y, Hu J, Xu H (2025). Efficacy and safety of berberine on the components of metabolic syndrome: a systematic review and meta-analysis of randomized placebo-controlled trials. Frontiers in Pharmacology 16:1572197. — PubMed PMID: 40740996
- Lei L, Wang B, Zhao L, et al.; BRAVO Collaborative Group (2026). Berberine and Adiposity in Diabetes-Free Individuals With Obesity and MASLD: A Randomized Clinical Trial. JAMA Network Open 9(1):e2554152. — PubMed PMID: 41543854
- Nie Q, Li M, Huang C, Yuan Y, Liang Q, Ma X, Qiu T, Li J (2024). The clinical efficacy and safety of berberine in the treatment of non-alcoholic fatty liver disease: a meta-analysis and systematic review. Journal of Translational Medicine 22(1):225. — PubMed PMID: 38429794
- Rinella ME, Lazarus JV, Ratziu V, et al.; NAFLD Nomenclature consensus group (2023). A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology 78(6):1966-1986. — PubMed PMID: 37363821
- Harrison SA, Bedossa P, Guy CD, et al.; MAESTRO-NASH Investigators (2024). A Phase 3, Randomized, Controlled Trial of Resmetirom in NASH with Liver Fibrosis. New England Journal of Medicine 390(6):497-509. — PubMed PMID: 38324483
- Sanyal AJ, Newsome PN, Kliers I, et al.; ESSENCE Study Group (2025). Phase 3 Trial of Semaglutide in Metabolic Dysfunction-Associated Steatohepatitis. New England Journal of Medicine 392(21):2089-2099. — PubMed PMID: 40305708
- Wilding JPH, Batterham RL, Calanna S, et al.; STEP 1 Study Group (2021). Once-Weekly Semaglutide in Adults with Overweight or Obesity. New England Journal of Medicine 384(11):989-1002. — PubMed PMID: 33567185
- Jastreboff AM, Aronne LJ, Ahmad NN, et al.; SURMOUNT-1 Investigators (2022). Tirzepatide Once Weekly for the Treatment of Obesity. New England Journal of Medicine 387(3):205-216. — PubMed PMID: 35658024
PubMed Topic Searches
Connections
- All Herbs
- Berberine Overview
- Berberine Benefits Hub
- Berberine for Blood Sugar
- Berberine for Cholesterol
- Berberine for Gut Health & Small Intestinal Bacterial Overgrowth
- Metabolic Syndrome
- Insulin Resistance
- Polycystic Ovary Syndrome
- Diabetes
- Non-Alcoholic Fatty Liver Disease
- Atherosclerosis
- Inositol
- Hemoglobin A1C
- Fasting Insulin
- Lipid Panel
- Blood Sugar
- Fasting / Time-Restricted Eating
- Omega-3 Fatty Acids
- Metformin — the prescription AMP-activated protein kinase activator berberine was tested head-to-head against in the Wei 2012 polycystic ovary syndrome trial.
- Covered in depth on its own page: Insulin Resistance · Caloric Restriction
- History