Thyme for Respiratory Health and Cough
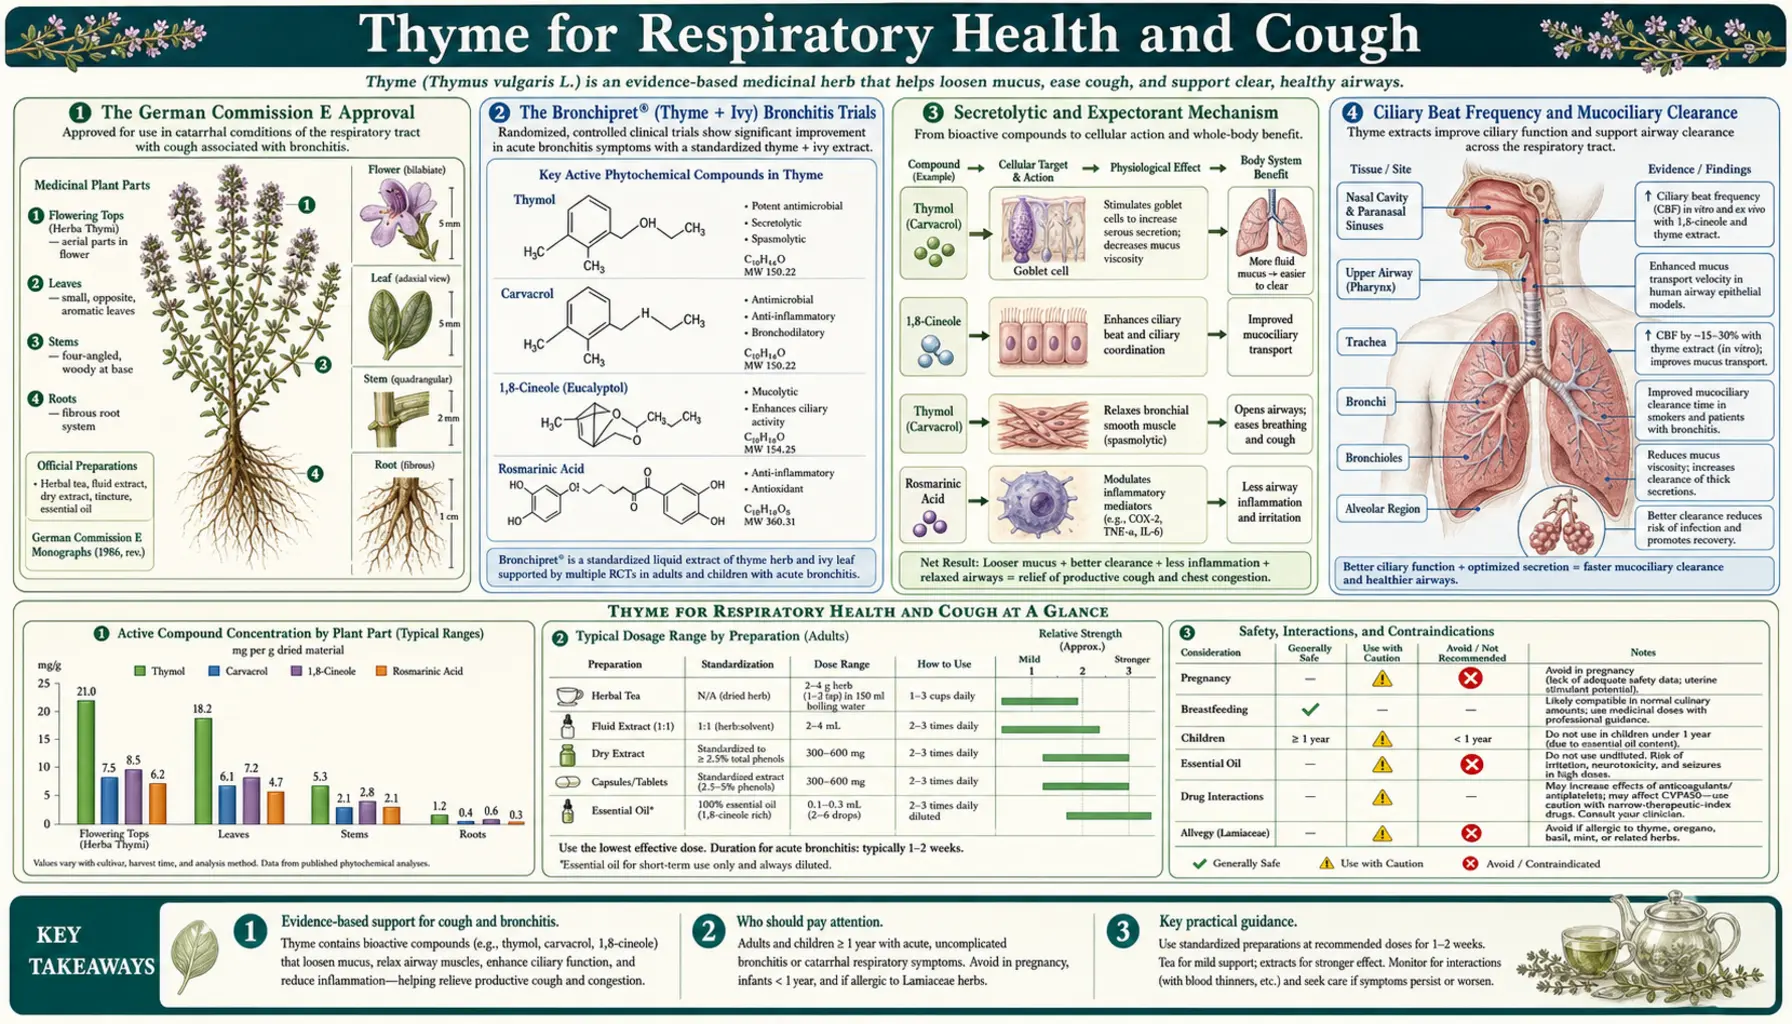
Thyme (Thymus vulgaris) is the most-traditional cough and bronchitis remedy in European folk medicine, and one of the few medicinal herbs to have crossed from folk use into formal regulatory approval. The German Commission E — the expert committee that reviewed herbal drugs for the German regulator — lists thyme as an approved treatment for symptoms of bronchitis, whooping cough, and upper respiratory catarrh, on the strength of pharmacological mechanism and modern clinical trials. Two randomized placebo-controlled trials, each in 361 adults with acute bronchitis — one of a thyme–ivy combination, one of a thyme–primrose combination — reported fewer coughing fits than placebo, and an uncontrolled surveillance study followed 1,234 children and adolescents given a thyme–ivy syrup. The proposed mechanism comes mainly from laboratory and animal work: thyme extract and thymol increase mucociliary transport in mice, are described as reducing the viscosity of bronchial mucus (the secretolytic / expectorant effect), and relax isolated tracheal smooth muscle, while contributing antimicrobial activity against the bacterial superinfection pathogens that complicate viral bronchitis. This deep-dive walks through the Commission E indication, the thyme–ivy combination evidence, the pharmacology, and how thyme tea, syrup, and steam inhalation have been used in adults and children.
Table of Contents
- The German Commission E Approval
- The Thyme–Ivy Combination Bronchitis Trials
- Secretolytic and Expectorant Mechanism
- Ciliary Beat Frequency and Mucociliary Clearance
- Bronchospasmolytic (Antispasmodic) Effect
- The European Cough Syrup Tradition
- Pediatric Use and the Thyme-Primrose Trials
- Preparation Forms: Tea, Tincture, Syrup, Steam, Essential Oil
- Thyme Across the Course of Adult Acute Bronchitis
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
The German Commission E Approval
The German Commission E is the expert committee established in 1978 by the German health authorities (its work now sits with the Federal Institute for Drugs and Medical Devices, BfArM) to evaluate the safety and efficacy of botanical drugs. Its monographs were a reference point for herbal-medicine licensing in Germany. The English edition of its roughly 380 monographs lists about 254 herbal drugs as approved and 126 as unapproved. Thyme is one of the approved.
The Commission E monograph for Thymi herba (the dried aboveground flowering parts of Thymus vulgaris and Thymus zygis) lists the following approved indications:
- Symptoms of bronchitis — both acute and chronic forms, where thyme's secretolytic and antispasmodic action loosens viscous mucus and reduces coughing
- Whooping cough (pertussis) — historically the most-cited indication, although the introduction of pertussis vaccination has reduced clinical relevance in developed countries
- Catarrh of the upper respiratory tract — the productive cough and post-nasal drip of common viral upper respiratory infections
The approved dose range is 1-2 g of dried herb infused in 150 mL of boiling water, taken several times daily as needed. The fluid extract dose is 1-2 g of equivalent extract several times daily. Thyme essential oil is also covered — 1-2 drops on a sugar cube or in honey, up to several times daily, or 2-3 drops in hot water for inhalation. The Commission E found no significant adverse effects at the monograph doses and listed no absolute contraindications other than known thyme allergy.
The European Scientific Cooperative on Phytotherapy (ESCOP) has also published a monograph on thyme herb. The European Medicines Agency Committee on Herbal Medicinal Products (HMPC) adopted an EU monograph on thyme herb in 2007 and later revised it. The HMPC classifies thyme herb preparations as "traditional use" — not "well-established use" — as an expectorant in productive cough associated with colds, meaning the conclusion rests on long-standing use rather than on clinical trials meeting the well-established-use standard. The EMA summary states that most thyme preparations are for adults and adolescents over 12, with a few also for children over 4.
The Thyme–Ivy Combination Bronchitis Trials
The most-studied preparation is a German proprietary phytomedicine, available in tablet, syrup, and drop formulations, that combines a fluid extract of thyme herb (Thymus vulgaris) with a fluid extract of ivy leaf (Hedera helix). The thyme contributes the secretolytic and antimicrobial fractions; the ivy contributes saponins that potentiate the bronchodilator effect through beta-adrenergic activation of bronchial smooth muscle and stimulation of surfactant production. The combination has been tested in placebo-controlled trials. The results come from specific standardized extract combinations and may not transfer to other thyme products.
Kemmerich 2006 thyme–ivy trial. This was a multi-center, randomized, double-blind, placebo-controlled trial of a thyme–ivy fluid-extract syrup in 361 adult outpatients with acute bronchitis and productive cough (182 active, 179 placebo). Participants took 5.4 mL of the syrup or matched placebo three times daily for 11 days. The primary outcome was the change in daytime coughing fits on days 7-9 compared with baseline. Results:
- The active group had a 68.7% mean reduction in coughing fits on days 7-9 vs. 47.6% in the placebo group
- The treatment difference was statistically significant (p < 0.0001)
- A 50% reduction in coughing fits was reached about 2 days earlier on the active combination
- Bronchitis Severity Score responder rates were higher on the active syrup at day 4 (83.0% vs 53.9%) and day 10 (96.2% vs 74.7%)
- There was no difference in the frequency or severity of adverse events between active and placebo; no severe or serious adverse events were reported
Kemmerich 2007 thyme–primrose trial. A second double-blind, placebo-controlled multicentre trial, also in 361 adult outpatients (183 active, 178 placebo), tested tablets combining dry extracts of thyme herb and primrose (Primula veris) root, one tablet three times daily for 11 days. The mean reduction in coughing fits on days 7-9 was 67.1% on the active tablets vs 51.3% on placebo (p < 0.0001), and a 50% reduction was reached about 2 days earlier; tolerability did not differ from placebo. The primrose saponins serve a similar bronchodilator-augmenting role to ivy saponins.
Marzian 2007 surveillance study. A non-interventional postmarketing surveillance study (no control group) followed 1,234 children and adolescents, almost all aged 2-17, with acute bronchitis and productive cough who were given a thyme–ivy syrup at age-appropriate doses for about ten days. The average Bronchitis Severity Score fell from 8.8 to 1.3 points, documented coughing fits fell by an average of 81.3% by day 10, responder rates across age groups were 92.0% to 96.5%, and physicians rated tolerability good or very good in 96.5% of cases. Without a comparison group, the study cannot separate the syrup's effect from natural recovery.
The two Kemmerich trials are notable in the phytomedicine literature because they used a multi-center, double-blind, placebo-controlled design, and they produced effect sizes that were both statistically significant and clinically meaningful. The thyme–ivy and thyme–primrose combinations are the forms these bronchitis trials tested; the saponin-rich ivy or primrose extract is described as augmenting the thyme-alone secretolytic effect.
Secretolytic and Expectorant Mechanism
The single most important pharmacological action of thyme in the respiratory tract is the secretolytic effect — the loosening and thinning of viscous bronchial mucus so that it can be cleared more easily by ciliary action and productive coughing. Several mechanisms contribute:
- Direct dilution effect via increased serous secretion. Thymol absorbed through the gastric mucosa is partly excreted unchanged through the bronchial mucous glands. The thymol itself acts as a mild irritant on the mucous gland secretory epithelium, increasing the watery (serous) fraction of bronchial secretions. The net effect is dilution of the viscous gel-like mucus that characterizes bronchitis.
- Breaking of mucus disulfide bonds. The dominant gel-forming bronchial mucin (MUC5AC) is heavily cross-linked by disulfide bonds between cysteine residues. Thymol, though weaker than the classic mucolytic N-acetylcysteine, has some disulfide-disrupting activity that contributes to the thinning of viscous mucus.
- Volatile oil distribution to airways. When thyme is inhaled (steam inhalation, lozenges, vapor rubs containing thymol) or even when thyme tea is sipped, the volatile thymol and carvacrol reach the upper airway lining directly. This delivers a high local concentration where it matters most, with minimal systemic exposure.
This is why thyme is more useful in productive ("wet") cough than in dry, non-productive cough. In dry cough, there is no viscous mucus to thin and clear — the value of a secretolytic is minimal, and cough suppressants are the drug class usually discussed for that situation. In productive cough with thick, hard-to-clear bronchial secretions, the secretolytic action of thyme can convert a frustrating, exhausting cough into a more efficient, productive cough that resolves the underlying bronchitis faster.
Ciliary Beat Frequency and Mucociliary Clearance
The bronchial epithelium is a ciliated columnar epithelium — each epithelial cell is topped with a brush of motile cilia that beat in coordinated waves to sweep the overlying mucus layer (with trapped particles and pathogens) up and out of the airways toward the throat, where it is swallowed or expectorated. This mucociliary escalator is the single most important non-immune airway defense system. Acute bronchitis, smoke exposure, and viral infection all slow or temporarily paralyze ciliary beating, allowing viscous mucus to pool and providing a stagnant environment in which bacterial superinfection thrives.
In mouse experiments, a thyme extract roughly doubled the rate of mucociliary clearance in the trachea (Wienkötter 2007), and pure thymol and carvacrol increased mucociliary transport in a concentration-dependent way (Begrow 2010). Extracts with very low thymol content were also active, which the authors took to mean that other, unidentified constituents of thyme matter as well. The mechanism of the clearance effect has not been worked out; the 2007 study also found an indirect, modulatory effect of the extract on beta-2 receptors.
How far these animal findings carry over to people has not been measured directly. The proposed link is that faster mucociliary clearance and the secretolytic action discussed above work together — thinner mucus is easier for cilia to move, and faster clearance moves it out sooner — but human studies of thyme have measured cough and symptom scores, not mucociliary clearance or bacterial colonization.
Bronchospasmolytic (Antispasmodic) Effect
In addition to its effect on mucus and cilia, thyme has direct antispasmodic activity on bronchial smooth muscle. The bronchial walls contain a layer of smooth muscle that can contract in response to histamine, leukotrienes, vagal stimulation, or direct irritation. Excessive contraction (bronchospasm) is the hallmark of asthma but also contributes to the wheeze, chest tightness, and paroxysmal coughing of bronchitis.
Thymol, carvacrol, and the flavonoid fraction of thyme (luteolin, apigenin) all relax bronchial smooth muscle in isolated tissue preparations. The dominant mechanism is calcium-channel modulation — thymol blocks both L-type and T-type calcium channels, reducing calcium entry into the smooth muscle cell and thereby reducing contraction. Additional mechanisms include phosphodiesterase inhibition (similar to the methylxanthines like theophylline, though weaker) and possible direct beta-adrenergic activation by some of the flavonoid constituents.
The clinical magnitude of this bronchodilator effect from oral thyme alone is modest — thyme is not a substitute for albuterol in acute bronchospasm. But the effect is real, additive to the secretolytic and ciliary effects, and amplified when thyme is combined with the saponin-rich ivy or primrose extracts in the combination preparations. The combination of "thinner mucus, faster cilia, less smooth-muscle contraction" addresses three of the four key drivers of bronchitis-associated cough simultaneously.
The European Cough Syrup Tradition
Thyme has been the dominant cough-syrup herb in European folk and apothecary medicine for at least four centuries. Recipes for thyme cough syrup — typically thyme infused in honey or simple syrup, sometimes with the addition of lemon, garlic, onion, or ivy — appear in every major European herbal from John Gerard's 1597 Herball through the twentieth-century formularies of Henriette Kress and Christopher Hobbs. The traditional preparation involves making a strong thyme decoction, straining it, combining it with an equal volume of honey or sugar, and dosing 1-2 teaspoons every 2-3 hours during a cough episode.
The honey base is not just a flavoring matter — honey has its own demonstrated cough-suppressant effect, particularly in pediatric upper respiratory infection. In a 2007 trial of 105 children (Paul et al., Archives of Pediatrics & Adolescent Medicine), parents rated a single bedtime dose of buckwheat honey best for nighttime cough and sleep; honey was significantly better than no treatment, dextromethorphan was not better than no treatment, and honey and dextromethorphan did not differ significantly from each other. A 2012 double-blind trial in 300 children aged 1-5 (Cohen et al., Pediatrics) found three honeys rated better than a date-extract placebo. The honey–thyme combination itself has not been compared with either ingredient alone in these trials. The familial transmission of this remedy — grandmother to mother to child — is part of the reason thyme has survived as a respected medicinal in modern European primary care while many older European herbal remedies have faded.
Modern commercial thyme–ivy combination syrups are essentially industrialized, standardized versions of this preparation, with thyme extract combined with ivy or primrose extract in a glycerin-sucrose syrup base. The active pharmacological principle is the same as the traditional remedy; what a commercial product offers over a home-made syrup is dose standardization and convenience.
Pediatric Use and the Thyme-Primrose Trials
Pediatric respiratory infection is one of the most common clinical scenarios in primary care, and the conventional pharmacopeia is conspicuously thin — dextromethorphan has limited evidence and is no longer recommended for children under 4 by the AAP, and codeine-containing cough syrups are contraindicated in children due to ultra-rapid-metabolizer risk. Honey works but is contraindicated in infants under 1 year due to Clostridium botulinum spore risk. This leaves room for well-tolerated phytomedicines, and thyme is one of the most-studied candidates.
Both Kemmerich placebo-controlled trials enrolled adults only. The pediatric data come from the uncontrolled Marzian 2007 surveillance study, in which children and adolescents aged 2-17 received a thyme–ivy syrup at the age-specific doses of its German summary of product characteristics and which reported high responder rates and good tolerability. The EU traditional-use monograph is more restrictive: the EMA summary states that most thyme preparations are for adults and adolescents over 12, with a few also for children over 4.
As a home preparation, thyme tea (1 teaspoon dried thyme per cup of boiling water, steeped 10 minutes, strained, sweetened with honey for children over 1 year) is a traditional first preparation for productive cough in children old enough to drink warm liquids; traditional amounts are 1/4 to 1/2 cup every 2-3 hours. Ingestion of thyme essential oil by young children carries a potential for oral mucosal irritation and a risk of seizure or respiratory depression at large doses; vapor-rub or steam inhalation products containing 1-2% thymol are commonly described as acceptable for children over 2 years.
Pediatric upper respiratory infection is also covered on the Bronchitis and Influenza pages.
Preparation Forms: Tea, Tincture, Syrup, Steam, Essential Oil
Thyme is one of the most preparation-flexible medicinal herbs — the active phenolic monoterpenes are extractable into water (tea), ethanol (tincture), sugar syrup, glycerin, and lipid carriers, and the volatile components are available for steam or vapor inhalation. The form chosen depends on the clinical situation.
- Thyme tea (infusion). The most accessible form. 1-2 teaspoons (about 1-2 g) of dried thyme per 250 mL cup of boiling water, steeped covered for 10 minutes (covered to prevent loss of volatile thymol with the steam), strained. Traditionally sweetened with honey; 3-4 cups per day during an active cough episode is the usual traditional amount. This is the Commission E reference preparation.
- Thyme tincture. A 1:5 ethanol tincture at 45-60% alcohol extracts both the volatile oils and the polyphenolic fraction. Typical adult dose 2-4 mL three times daily, diluted in a small amount of water. Tinctures are convenient for travel and have a multi-year shelf life.
- Thyme syrup. Traditional preparation as described above, or a commercial thyme–ivy combination syrup. Adult dose typically 5-10 mL three to four times daily.
- Thyme steam inhalation. 1-2 teaspoons dried thyme (or 5-6 drops thyme essential oil) added to a large bowl of just-off-the-boil water, with a towel draped over the head while the rising steam is inhaled for 5-10 minutes, 2-3 times daily. This delivers volatile thymol and carvacrol directly to the upper airway with minimal systemic exposure. Traditionally used for sinusitis, laryngitis, and the early stages of bronchitis.
- Thyme essential oil. Traditional internal use is 1-2 drops on a sugar cube or in honey, dissolved in the mouth, two to three times daily — this is high-dose phenolic monoterpene exposure, described for short-term use only (less than 7 days), and the cautions literature raises concerns for young children, pregnancy, and asthma. Topical chest-rub preparations use 1-2% thyme essential oil in a carrier oil (sweet almond, jojoba) applied to the chest and upper back.
A combined regimen described for adult acute bronchitis is thyme tea 3-4 cups daily, plus steam inhalation 2x daily, plus a thyme–ivy combination syrup or a home-made honey-thyme syrup at 1-2 teaspoons every 3 hours for cough, over a course of typically 7-10 days.
Thyme Across the Course of Adult Acute Bronchitis
Acute bronchitis is one of the most common reasons for primary care visits and is mostly viral — antibiotic prescribing is overused, leading to no clinical benefit and substantial contribution to antibiotic resistance and adverse drug reactions. The American College of Physicians and the CDC both recommend against routine antibiotic use for uncomplicated acute bronchitis. Management is therefore largely symptomatic, and thyme-based phytotherapy is one of the more evidence-supported herbal options studied.
The typical course of uncomplicated acute bronchitis in adults (productive cough <3 weeks, no fever >38.5°C, no pleuritic chest pain, no significant dyspnea, no risk factors for bacterial superinfection), and how thyme preparations have been used across it:
- Day 1-2. Onset of productive cough. Herbal regimens described for this stage use thyme tea 3-4 cups daily and steam inhalation 2x daily, with honey-thyme syrup 1-2 teaspoons every 3 hours for cough paroxysms; fluid intake of 2-3 L water daily and a bedroom humidifier are commonly mentioned alongside.
- Day 3-7. The same regimen typically continues, sometimes with a thyme–ivy combination syrup added, alongside reduced physical exertion. Commonly listed "red flag" symptoms: fever >38.5°C lasting >3 days, pleuritic pain, shortness of breath at rest, hemoptysis (coughing blood), confusion in older adults.
- Day 7-14. Cough typically improves and transitions from productive to dry; described regimens reduce thyme tea to 1-2 cups daily and taper inhalation. A cough that is not improving or is worsening at day 7 is usually described as a reason for medical evaluation, to exclude bacterial pneumonia, pertussis (whooping cough in adults presents atypically with a paroxysmal cough lasting 4-8 weeks), or post-infectious bronchospasm.
- Day 14-21. Residual dry cough is common after acute bronchitis and may persist 3-4 weeks. At this point thyme's secretolytic action has little left to act on; honey, lozenges, and time-limited dextromethorphan are the options usually discussed for this stage.
For people with underlying COPD, asthma, immunocompromise, or other respiratory conditions, early medical assessment in any acute bronchitis is the usual clinical guidance; thyme is described as an adjunct in these populations, not a replacement for prescription bronchodilator, inhaled corticosteroid, or antibiotic therapy where indicated. Decisions about medicines and supplements belong with a clinician.
Cautions and Contraindications
- Thyme allergy. Cross-reactive sensitization is possible in patients with allergy to other Lamiaceae (mint family) herbs — oregano, sage, rosemary, basil. Allergic contact dermatitis to thyme, sometimes cross-reacting with rosemary, has been described in case reports. Reported signs of a reaction include rash, hives, or oral mucosal swelling.
- Pregnancy — culinary doses safe, medicinal doses cautious. Culinary use of thyme as a kitchen seasoning is safe in pregnancy. Medicinal doses (tea 3-4 cups/day, tincture, syrup) for short-term acute bronchitis use are likely safe but data are limited; the European Medicines Agency HMPC recommends caution. Internal use of thyme essential oil during pregnancy raises a concern because of the high concentration of phenolic monoterpenes; topical chest-rub at 1-2% dilution is generally described as acceptable.
- Young children and internal essential oil. Oral undiluted thyme essential oil in children under 12 carries a risk of oral mucosal burns, gastric irritation, and (at large doses) seizure. Diluted thyme tea, honey-thyme syrup (over age 1), and steam inhalation are generally described as acceptable for pediatric use.
- Asthma — usually beneficial, with reports of paradoxical bronchospasm. Thyme's antispasmodic action is typically beneficial in mild asthma, but in a small subset of patients aromatic herbal preparations including thyme can trigger bronchospasm; the reaction described is worsening wheeze or chest tightness.
- Bleeding risk — theoretical, low. Thymol has weak antiplatelet activity in vitro; a theoretical concern with high-dose warfarin or other anticoagulants but no clinically significant interactions reported.
- Hypothyroidism. Some sources suggest thyme can suppress thyroid hormone synthesis — this is based on weak animal data and is not clinically relevant at culinary or short-term medicinal doses. The available evidence does not point to a problem for people on thyroid hormone replacement.
- Drug interactions. Few clinically significant interactions. Theoretical additive effect with cholinergic drugs, antiplatelet agents, and other secretolytic / mucolytic drugs (N-acetylcysteine, guaifenesin) — these combinations are generally synergistic and beneficial rather than problematic.
Key Research Papers
- Kemmerich B (2007). Evaluation of efficacy and tolerability of a fixed combination of dry extracts of thyme herb and primrose root in adults suffering from acute bronchitis with productive cough. A prospective, double-blind, placebo-controlled multicentre clinical trial. Arzneimittelforschung. — PubMed PMID: 17966760
- Kemmerich B et al. (2006). Efficacy and tolerability of a fluid extract combination of thyme herb and ivy leaves and matched placebo in adults suffering from acute bronchitis with productive cough. A prospective, double-blind, placebo-controlled clinical trial. Arzneimittelforschung. — PubMed PMID: 17063641
- Marzian O (2007). Treatment of acute bronchitis in children and adolescents: non-interventional postmarketing surveillance study confirms the benefit and safety of a syrup made of extracts from thyme and ivy leaves. MMW Fortschritte der Medizin. — PubMed PMID: 17619603
- Wienkötter N, Begrow F, Kinzinger U, Schierstedt D, Verspohl EJ (2007). The effect of thyme extract on beta2-receptors and mucociliary clearance. Planta Medica 73(7):629-635. — PubMed PMID: 17564943
- Buechi S et al. (2005). Open trial to assess aspects of safety and efficacy of a combined herbal cough syrup with ivy and thyme. Forschende Komplementarmedizin. — PubMed PMID: 16391481
- Blumenthal M et al. (2000). German Commission E Monographs: Thyme herb (Thymi herba). Herbal Medicine: Expanded Commission E Monographs. — PubMed
- European Medicines Agency Committee on Herbal Medicinal Products (2013). Community herbal monograph on Thymus vulgaris. — PubMed
- Begrow F et al. (2010). Impact of thymol in thyme extracts on their antispasmodic action and ciliary clearance. Planta Medica. — PubMed PMID: 19809973
- Meister A et al. (1999). Antispasmodic activity of Thymus vulgaris extract on the isolated guinea-pig trachea: discrimination between drug and ethanol effects. Planta Medica. — PubMed PMID: 10483369
- Salehi B et al. (2018). Thymol, thyme, and other plant sources: Health and potential uses. Phytotherapy Research 32(9):1688-1706. — PubMed PMID: 29785774
- Schulz V, Hansel R, Tyler VE (2001). Rational Phytotherapy: A Reference Guide for Physicians and Pharmacists — thyme chapter. — PubMed
- Cohen HA, Rozen J, Kristal H, et al. (2012). Effect of honey on nocturnal cough and sleep quality: a double-blind, randomized, placebo-controlled study. Pediatrics 130(3):465-471. (relevant context for honey-thyme syrup tradition) — PubMed PMID: 22869830
- Paul IM, Beiler J, McMonagle A, Shaffer ML, Duda L, Berlin CM Jr (2007). Effect of honey, dextromethorphan, and no treatment on nocturnal cough and sleep quality for coughing children and their parents. Archives of Pediatrics & Adolescent Medicine 161(12):1140-1146. — PubMed PMID: 18056558
PubMed Topic Searches
Connections
- All Herbs
- Thyme Overview
- Thyme Benefits Hub
- Thyme Antimicrobial Spectrum
- Thyme Digestive Aid
- Thyme Antioxidant & Acne
- Eucalyptus (Respiratory)
- Ivy Leaf (Respiratory)
- Pelargonium (Respiratory)
- Oregano (Carvacrol Cousin)
- Sage
- Bronchitis
- Asthma
- Influenza
- Sinusitis
- Pulmonology
- Honey (Cough Syrup Base)
- Immune Boosting
- History