⚠ Evidence warning: Clinical trials or other evidence do not support the claims that Maca raises brain BDNF in rodents and protects against Parkinson-type nerve damage in rodent models, or that it helps stress, burnout or non-menopausal anxiety. This page keeps it as a report of what people, websites or other media say.
Maca for Mood and Cognitive Function
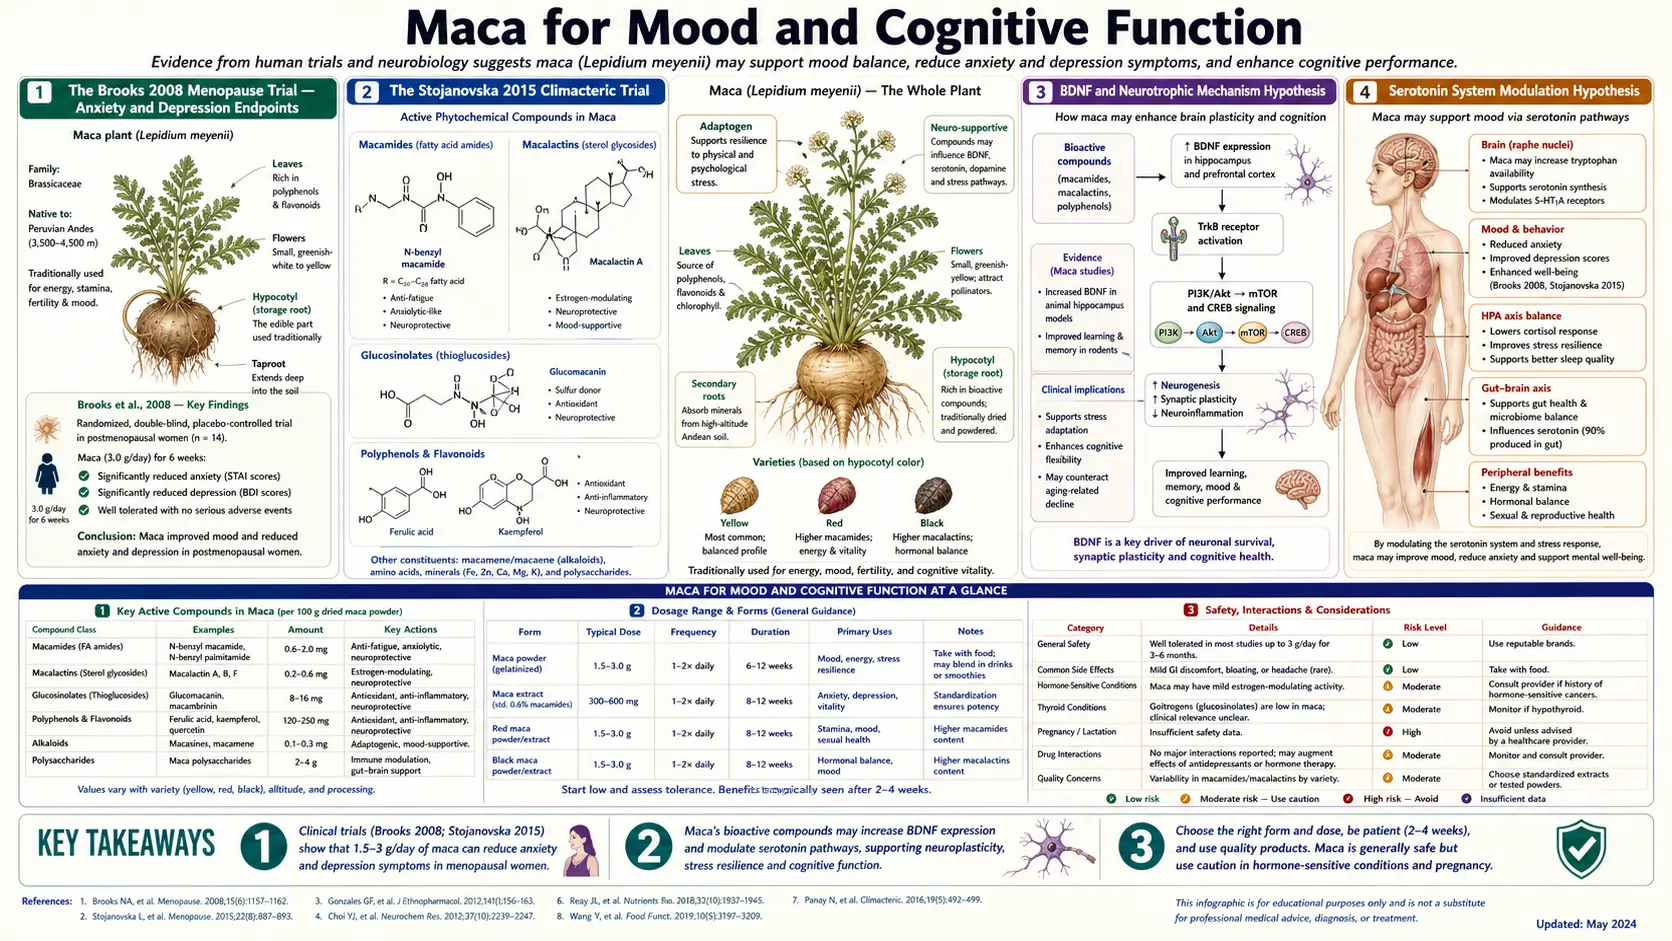
The Maca-and-mood evidence base is anchored by the Brooks et al. 2008 trial in Menopause, in which 14 postmenopausal women took 3.5 g/day Maca and placebo for 6 weeks each, in either order, and showed significant reductions in the psychological-symptom scores of the Greene Climacteric Scale, including its anxiety and depression subscales, and in measures of sexual dysfunction — with the title of the paper explicitly noting that the psychological improvements were "not related to estrogen or androgen content." Subsequent trials have extended this finding to perimenopausal cohorts and to non-menopausal anxiety contexts. The mechanism is hypothesized to involve brain-derived neurotrophic factor (BDNF) upregulation, serotonergic system modulation, and possibly endocannabinoid signaling through the macamide-FAAH pathway shared with the libido benefit. Memory data come almost entirely from rodent models — Rubio et al. 2007 showed that black Maca reversed scopolamine-induced memory impairment in mice, and several other rodent learning-and-memory studies have shown protective effects against various cognitive insults. Human cognitive trials are sparse and have not consistently shown discrete memory or executive-function improvements. The critical context for the mood evidence is the comparison to selective serotonin reuptake inhibitors (SSRIs): the Maca trials studied women with menopausal symptoms, adults in Peru, and people whose depression was already in remission on an antidepressant, so no trial has tested Maca as a replacement for antidepressant drugs in established moderate-to-severe depression, or as the only treatment for major depressive disorder. This page works through the human trial evidence, the brain-derived neurotrophic factor and serotonin hypotheses, the rodent memory data, and how the Maca evidence compares with selective serotonin reuptake inhibitors and other mood interventions.
Table of Contents
- The Brooks 2008 Menopause Trial — Anxiety and Depression Endpoints
- The Stojanovska 2015 Climacteric Trial
- Brain-Derived Neurotrophic Factor and Neurotrophic Mechanism Hypothesis
- Serotonin System Modulation Hypothesis
- Endocannabinoid Overlap with the Libido Mechanism
- The Rubio 2007 Scopolamine-Reversal Mouse Study
- Additional Rodent Memory and Learning Data
- Human Cognitive Trials — What We Have and Don't
- Maca and Selective Serotonin Reuptake Inhibitors — What the Trials Tested
- Mood Uses Studied and Not Studied
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Brooks 2008 Menopause Trial — Anxiety and Depression Endpoints
The single most-cited trial for Maca's mood effects is Nicole A. Brooks et al., "Beneficial effects of Lepidium meyenii (Maca) on psychological symptoms and measures of sexual dysfunction in postmenopausal women are not related to estrogen or androgen content," published in Menopause volume 15 in 2008. The trial was conducted at Victoria University in Australia under blind methodology.
Design: double-blind randomized placebo-controlled crossover trial. 14 postmenopausal women (mean age 56) completed the trial, taking 3.5 g/day Maca powder for 6 weeks and matching placebo for 6 weeks, in either order, over a total of 12 weeks. Symptoms were measured with the Greene Climacteric Scale. Blood levels of estradiol, follicle-stimulating hormone (FSH), luteinizing hormone (LH) and sex hormone-binding globulin (SHBG) were measured at baseline, week 6 and week 12, and Maca extracts were tested in a yeast-based laboratory assay for estrogen-like and androgen-like activity.
Results for the mood endpoints:
- Greene Climacteric Scale psychological sub-scores: significant reduction after Maca compared with both baseline and placebo (P < 0.05), including the anxiety and depression subscales
- Sexual dysfunction: the Greene sexual-dysfunction score also fell significantly after Maca compared with both baseline and placebo
- Serum hormone parameters: no differences in estradiol, FSH, LH or SHBG between baseline, Maca and placebo — the headline negative finding that grounds the title; the yeast assays found no physiologically significant estrogen-like or androgen-like activity in the Maca extracts
The trial is small (n=14) but the crossover design provides each subject as her own control, which substantially increases statistical power per subject. The effect sizes were large enough to reach statistical significance despite the small sample, suggesting that the underlying psychological-symptom signal is robust at least in the postmenopausal subgroup studied.
Critically, the Brooks 2008 trial was independently conducted (no commercial sponsorship from Maca producers), used a generic Maca powder rather than a proprietary standardized extract, and used a validated menopause symptom scale (the Greene Climacteric Scale) — all of which strengthen the credibility of the finding relative to the manufacturer-sponsored Meissner trial series in the same era.
For the broader menopausal context including the vasomotor and sleep endpoints from the same study, see the Hormonal Balance and Menopause deep-dive.
The Stojanovska 2015 Climacteric Trial
Lily Stojanovska and colleagues at Victoria University published a follow-up trial in Climacteric volume 18 in 2015: "Maca reduces blood pressure and depression, in a pilot study in postmenopausal women." Design was a randomized, double-blind, placebo-controlled crossover trial in 29 postmenopausal Hong Kong Chinese women, who took 3.3 g/day Maca or placebo for 6 weeks each, in either order, over 12 weeks.
Measurements included estradiol, follicle-stimulating hormone, sex hormone-binding globulin, thyroid-stimulating hormone, blood fats, glucose, serum cytokines and blood pressure; symptoms and quality of life were assessed with the Greene Climacteric Scale, the SF-36, the Women's Health Questionnaire and the Utian Quality of Life Scale. Results:
- Significant decrease in depression after Maca
- Significant decrease in diastolic blood pressure after Maca (a secondary finding of independent interest)
- No differences in estradiol, follicle-stimulating hormone, thyroid-stimulating hormone, sex hormone-binding globulin, glucose, blood fats or serum cytokines between Maca and placebo
- No significant change in vasomotor symptom sub-scores in this study (small sample limits power for this endpoint)
- Maca was well-tolerated; no significant adverse events
The Stojanovska trial extends the Brooks finding to a different ethnic population (Chinese rather than Australian) and confirms the depression-sub-score signal in an independent cohort. The additional blood pressure observation is interesting and consistent with some cardiovascular benefit, though it has not been the primary focus of most subsequent Maca research.
The combined Brooks 2008 + Stojanovska 2015 evidence is reasonably persuasive that Maca produces measurable mood improvement in postmenopausal women at 3–3.5 g/day, mediated through some mechanism that does not involve sex hormone elevation. The generalization to other clinical populations (premenopausal women, men, and patients with primary depression unrelated to menopausal transition) is less well-supported.
Brain-Derived Neurotrophic Factor and Neurotrophic Mechanism Hypothesis
Brain-derived neurotrophic factor (BDNF) is a small protein that supports neuronal survival, synaptic plasticity, and the growth of new neural connections. Reduced brain-derived neurotrophic factor is implicated in the pathophysiology of major depression, and one of the converging mechanisms of action of selective serotonin reuptake inhibitors, exercise, electroconvulsive therapy, and several other antidepressant interventions is the upregulation of brain-derived neurotrophic factor expression in the hippocampus and prefrontal cortex. Brain-derived neurotrophic factor elevation is now considered one of the most reliable molecular signatures of effective antidepressant action.
Preclinical evidence suggests that Maca extracts upregulate brain-derived neurotrophic factor expression in rodent brain tissue. Rodent studies are reported to show brain-derived neurotrophic factor upregulation in response to chronic Maca supplementation, often coupled with measured improvements in hippocampus-dependent learning tasks.
The hypothesized mechanism for brain-derived neurotrophic factor upregulation by Maca is not yet established at the molecular level. Candidate pathways include:
- Direct CREB / TrkB pathway activation by Maca-derived compounds — the same upstream pathway activated by selective serotonin reuptake inhibitors and exercise. Some macamides have been shown in vitro to interact with elements of this pathway, though the relevance to in vivo brain concentrations is uncertain.
- Indirect activation via reduced cortisol exposure — chronic cortisol elevation suppresses brain-derived neurotrophic factor expression, and any intervention that normalizes hypothalamic-pituitary-adrenal (HPA) axis hyperactivity could secondarily restore brain-derived neurotrophic factor. Maca's modest cortisol-normalizing effects in hypothalamic-pituitary-adrenal-dysregulated subjects (documented in the Meissner trials) would predict this kind of downstream brain-derived neurotrophic factor restoration.
- Antioxidant and anti-inflammatory effects — chronic oxidative stress and neuroinflammation both suppress brain-derived neurotrophic factor expression. Maca's antioxidant capacity (discussed on the Energy and Endurance deep-dive) and possible mild anti-inflammatory effects could contribute indirectly.
- Nutritional repletion — B vitamins, zinc, and magnesium are all required cofactors in brain-derived neurotrophic factor synthesis or signaling, and modest nutritional contributions from Maca may matter in patients with marginal status.
The brain-derived neurotrophic factor hypothesis is plausible and consistent with the rodent neuropharmacology data, but it has not been directly tested in humans on Maca. A trial measuring serum or cerebrospinal fluid brain-derived neurotrophic factor before and after 12 weeks of Maca supplementation would be informative; to our knowledge, no such trial has been published.
Serotonin System Modulation Hypothesis
A parallel hypothesis is that Maca modulates the serotonergic system, with mood-relevant downstream effects. The evidence here is mixed and largely preclinical:
- Some rodent studies have shown changes in brain serotonin metabolite concentrations in Maca-treated animals — typically modest increases in 5-HIAA (the major serotonin metabolite) consistent with increased serotonin turnover
- In vitro studies of Maca extract effects on serotonin receptors have not consistently shown direct binding to 5-HT1A, 5-HT2A, or other major serotonin receptors at physiologic concentrations
- The Dording 2008 trial of Maca in selective serotonin reuptake inhibitor (SSRI)-induced sexual dysfunction enrolled people whose depression was in remission on their SSRI; its abstract reports that Maca was well tolerated alongside the SSRI, but it reports no test of depression scores, so it does not show whether Maca changes the antidepressant effect
- The macamide-FAAH-endocannabinoid pathway discussed for libido may have indirect serotonergic consequences, since endocannabinoid signaling modulates serotonergic neurotransmission in several brain regions
The honest framing is that the serotonin system is plausibly involved in Maca's mood effects but is not the dominant mechanism. The lack of direct receptor binding rules out the simplest serotonergic mechanism (selective serotonin reuptake inhibitor-like reuptake inhibition or direct receptor agonism). More likely, any serotonergic effect is indirect, downstream of hypothalamic-pituitary-adrenal axis modulation, brain-derived neurotrophic factor upregulation, or endocannabinoid signaling changes.
Endocannabinoid Overlap with the Libido Mechanism
One of the most parsimonious mechanistic frameworks for Maca's diverse clinical effects is that a single upstream mechanism — modulation of endocannabinoid tone through macamide-FAAH inhibition — produces effects on libido, mood, anxiety, sleep, and hypothalamic-pituitary-adrenal axis function through the broad role of endocannabinoid signaling in all of these systems.
The hypothesized mechanism is the same as discussed in detail on the Libido and Sexual Function deep-dive: macamides (the N-benzyl fatty acid amides unique to Maca) inhibit fatty acid amide hydrolase (FAAH), the enzyme that degrades anandamide. The result is chronically elevated anandamide tone, which has downstream effects through CB1 receptors expressed densely in:
- The hypothalamus — modulating hypothalamic-pituitary-adrenal stress reactivity, CRH release, sleep-wake cycling, and thermoregulation (relevant to the vasomotor and sleep effects in menopause)
- The limbic system (amygdala, hippocampus, nucleus accumbens) — modulating anxiety, fear extinction, mood, reward processing, and memory consolidation (relevant to the anxiety, depression, and memory effects)
- The hypothalamic-pituitary-gonadal axis at multiple levels — modulating libido and sexual response (relevant to the libido and sexual function effects)
- The basal ganglia and motor cortex — modulating motivation, fatigue perception, and the subjective experience of energy (relevant to the perceived energy and motivation benefits)
A single upstream mechanism producing effects across all these systems would explain why Maca produces such a diverse range of clinical effects without easily mapping to a single conventional drug class. The hypothesis is plausible and consistent with the available data but remains to be directly validated in human trials — specifically, measurement of serum or cerebrospinal anandamide before and after chronic Maca supplementation would be the key first-order test.
The Rubio 2007 Scopolamine-Reversal Mouse Study
The most-cited Maca cognitive-function paper is Julio Rubio et al., "Aqueous and hydroalcoholic extracts of black maca (Lepidium meyenii) improve scopolamine-induced memory impairment in mice," published in Food and Chemical Toxicology volume 45 in 2007. The design used a standard preclinical memory paradigm: male mice received two doses each of an aqueous (0.50 and 2.00 g/kg) and a hydroalcoholic (0.25 and 1.00 g/kg) black Maca extract for 35 days, scopolamine (a muscarinic acetylcholine receptor antagonist) was given to induce a memory impairment, and memory was tested with the Morris water maze (a spatial memory task) and the step-down avoidance test (an associative memory task).
Findings:
- Both aqueous and hydroalcoholic black Maca extracts significantly reduced the scopolamine-induced memory impairment in both behavioral paradigms
- Acetylcholinesterase (AChE) activity in the brain was inhibited by the Maca extracts, while monoamine oxidase activity was not affected, suggesting one possible mechanism (AChE inhibition would preserve synaptic acetylcholine availability against the scopolamine antagonism)
- The treatment was well-tolerated with no acute toxicity at the doses used
The Rubio 2007 study has been the foundation for subsequent claims of Maca as a cognitive or nootropic supplement. The honest interpretation is that the rodent data support a real cognitive-protective effect against a specific acute cholinergic insult (scopolamine), and the modest AChE inhibition mechanism is biologically plausible. The translation to human cognitive enhancement in healthy adults, or to cognitive protection in human Alzheimer's disease, has not been established by human trials — though the Rubio findings have motivated the design of several Alzheimer-model rodent studies that have generally found beneficial effects of Maca on amyloid pathology and behavioral measures of cognition.
Additional Rodent Memory and Learning Data
Beyond Rubio 2007, several other animal and laboratory studies have examined Maca for cognitive endpoints:
- Guo et al. 2016 — middle-aged mice. Fourteen-month-old male mice given Maca powder by mouth for five weeks had better cognitive function, motor coordination and endurance than untreated mice, together with better mitochondrial respiratory function (the cells' energy production) and more autophagy-related proteins (the cells' clean-up machinery) in the brain cortex.
- Pino-Figueroa et al. 2010 — crayfish neurons and rats. Crayfish nerve cells pretreated with a pentane extract of Maca survived hydrogen peroxide damage better, with more protection at higher concentrations. In rats given the extract into a vein before and after a blocked brain artery (a stroke model), the lower dose made the damaged brain area smaller, while higher doses made it larger than in untreated rats.
- Several Parkinson's model studies in rodents have shown protective effects of Maca extract against MPTP-induced dopaminergic neuron loss in the substantia nigra, with consequent improvement in motor and behavioral outcomes. The mechanism appears to involve antioxidant protection of dopaminergic neurons against oxidative insult.
What is not known: the Pino-Figueroa rat result shows that in animals the dose matters — an amount that limited stroke damage at one dose increased it at higher doses — and no human study has worked out which amounts of Maca, if any, protect the brain.
The aggregate preclinical neuroprotection picture is promising but does not yet translate to a clinical recommendation for Maca in Alzheimer's disease, Parkinson's disease, or cognitive decline in humans. Human trials with cognitive endpoints have generally been short and underpowered, and no large randomized trial of Maca for any neurodegenerative condition has been published. In short, Maca has biologically plausible neuroprotective mechanisms supported by rodent evidence, but the human translation remains aspirational rather than evidence-based at this time.
Human Cognitive Trials — What We Have and Don't
The human cognitive-function evidence for Maca is sparse. The relevant data points:
- The Brooks 2008 and Stojanovska 2015 trials measured menopause and quality-of-life scales (the Greene Climacteric Scale, and in 2015 also the SF-36, Women's Health Questionnaire and Utian scales) but did not include discrete cognitive endpoints (working memory, processing speed, executive function tests)
- Several small open-label trials have reported subjective cognitive improvement on Maca, but these are uncontrolled and at high risk of placebo bias
- One small Peruvian study examined Maca in patients with mild cognitive impairment and reported some improvement on a screening cognitive instrument over 12 weeks, but the sample was too small and the methodology too limited for confident interpretation
- The Gonzales-Arimborgo et al. 2016 trial, the largest so far, gave 175 adults living at low and high altitude in Peru 3 g a day of red Maca extract, black Maca extract or placebo for 12 weeks. Both Maca extracts improved mood, energy and health-related quality-of-life scores compared with placebo, the effects on mood and energy were reported as better with red Maca, and both extracts were well tolerated with no serious adverse effects. Its listed outcomes (sexual desire, mood, energy, quality of life, chronic mountain sickness, blood sugar, blood pressure, hemoglobin) did not include formal memory or thinking tests
The absence of large well-designed human cognitive trials means that anyone promoting Maca as a nootropic or cognitive enhancer is extrapolating from rodent data. This extrapolation may turn out to be correct, but for now the evidence supports interest rather than firm conclusions. For memory and thinking, the human evidence on Maca is limited and the rodent data are promising. Human Maca trials have used 1.5–3.5 g a day for 6–12 weeks. The measures with their own research base for thinking skills (regular aerobic exercise, sleep, a Mediterranean-style diet, social engagement, novel learning) are separate from Maca.
Maca and Selective Serotonin Reuptake Inhibitors — What the Trials Tested
The single most important context for the Maca-mood evidence is how it compares with selective serotonin reuptake inhibitors and other antidepressant drugs. No trial has tested Maca as a replacement for antidepressant drugs in people with established moderate-to-severe depression; the human Maca trials studied women with menopausal symptoms, adults in Peru, and people whose depression was already in remission on an antidepressant.
The comparison:
- Effect size: selective serotonin reuptake inhibitors in patients with major depressive disorder produce response rates of roughly 50–70% (defined as 50% reduction in HAM-D or BDI scores) over 8–12 weeks. The Maca mood trials report statistically significant falls in menopause-scale depression and anxiety scores, not response rates on depression scales such as HAM-D or BDI. These are not comparable populations (the Maca trials studied women with menopausal psychological symptoms, not patients with major depressive disorder), and no trial has compared Maca with a selective serotonin reuptake inhibitor head to head.
- Evidence base depth: selective serotonin reuptake inhibitors have been studied in tens of thousands of patients across hundreds of randomized controlled trials, with established efficacy, side effect profile, and dose-response relationships. The Maca mood evidence is a handful of small trials, mostly in menopausal women. The evidence bases are not in the same league.
- Speed of onset: selective serotonin reuptake inhibitors typically produce measurable benefit at 4–6 weeks, with continued improvement through 12 weeks. Maca's mood signal emerged at 6 weeks in the Brooks trial and was maintained at end of treatment. The timelines are comparable, with no obvious advantage to either.
- Side effect profile: selective serotonin reuptake inhibitors have well-known side effects (sexual dysfunction, gastrointestinal (GI) upset, weight gain, sleep disruption, withdrawal phenomena). Maca's side effect profile is much milder (occasional gastrointestinal bloating, primarily). The difference matters most to people who cannot tolerate selective serotonin reuptake inhibitors; the Maca trials did not study that group.
- Use alongside selective serotonin reuptake inhibitors: Maca and selective serotonin reuptake inhibitors are thought to act through different mechanisms. In the Dording 2008 pilot (20 people whose depression was in remission on a selective serotonin reuptake inhibitor, 17 of them women; 10 finished), Maca at 1.5 or 3.0 g a day was taken alongside the antidepressant and was well tolerated; the 3.0 g dose improved sexual-function scores (ASEX from 22.8 to 16.9, MGH-SFQ from 24.1 to 17.0) and the 1.5 g dose did not. The abstract does not report a test of whether depression changed.
A 12-week placebo-controlled trial (Dording 2015) gave Maca 3.0 g a day or placebo to 45 women whose depression had remitted on a selective serotonin reuptake inhibitor or a serotonin-norepinephrine reuptake inhibitor (SNRI) but who had sexual side effects; 42 were analysed. More women reached sexual-function remission on Maca than on placebo (for example, 30.0% vs 20.0% reaching an MGH-SFQ score of 12 or less), the higher remission rates were linked to being postmenopausal, and Maca was well tolerated. A 2025 systematic review and meta-analysis of 11 randomized trials with 859 women covered drug and herbal treatments for antidepressant-induced sexual dysfunction, maca root among them; only two studies could be pooled, bupropion SR 150 mg twice daily improved desire, arousal and orgasm compared with placebo, and the quality of the evidence was rated low.
What the trials tested, by situation:
- Mild depressive symptoms around menopause: the Brooks and Stojanovska trials tested 3.3–3.5 g/day for 6 weeks in postmenopausal women; behavioral measures (exercise, sleep, cognitive-behavioral support) have their own research base
- Moderate-to-severe depression: none of the Maca trials described here studied people with active moderate-to-severe depression, either with Maca alone or with Maca added to a selective serotonin reuptake inhibitor, a serotonin-norepinephrine reuptake inhibitor or another antidepressant
- Selective serotonin reuptake inhibitor-induced sexual dysfunction: the Dording trials added Maca 1.5–3.0 g/day to the existing antidepressant rather than switching antidepressants; the 3.0 g dose improved sexual-function scores in the 2008 pilot, and the 2015 placebo-controlled trial found higher remission rates, mainly in postmenopausal women
- Severe or treatment-refractory depression: no Maca trial has studied this group; severe depression, suicidal thoughts or psychotic features are signs that hospitals and mental-health services treat as urgent
Stopping an antidepressant such as sertraline and taking Maca instead has not been studied. Adding Maca to sertraline or another selective serotonin reuptake inhibitor for low libido is what the Dording trials tested, in people whose depression was in remission.
For more on the mood and depression context, see our Depression page.
Mood Uses Studied and Not Studied
Putting the trial evidence together, the situations studied or proposed for Maca in mood and cognitive support are:
- Perimenopausal and postmenopausal women with mild-to-moderate anxiety and depression symptoms that are part of the menopausal transition rather than primary major depressive disorder. This is the population in which Maca has the strongest evidence base: the mood trials were in postmenopausal women.
- Selective serotonin reuptake inhibitor-induced sexual dysfunction in women on conventional antidepressant therapy. Maca at 3 g/day improved sexual-function scores in the Dording trials, mostly in women whose depression was in remission on the antidepressant; the trial abstracts do not report whether the antidepressant effect changed.
- Adjunctive use in chronic stress and hypothalamic-pituitary-adrenal dysregulation — the same upstream hypothalamic-pituitary-adrenal axis modulation hypothesis that explains the menopausal benefits would predict modest benefit in burnout, chronic stress states, and post-acute-stress recovery contexts. Trial evidence in these contexts is limited but the mechanism is plausible.
- Cognitive support in the elderly as part of a broader lifestyle and nutritional optimization, proposed on the basis of the rodent neuroprotection evidence and the mineral / B-vitamin nutritional contributions; no human trial with memory tests has tested it.
- Anxiety in non-menopausal contexts — mild generalized anxiety, performance anxiety, or context-specific anxiety where conventional anxiolytics are not desired or not indicated. Trial evidence is limited but the menopausal anxiety improvement is plausibly generalizable to a wider population.
Uses that no Maca trial has tested or supported:
- Replacing selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors (SNRIs), or other established antidepressants in moderate-to-severe major depressive disorder
- Use as the only treatment for treatment-refractory depression
- Cognitive enhancement in healthy young adults (insufficient human evidence; the rodent neuroprotection data are in disease and ageing models, not normal cognition)
- Treatment of established Alzheimer's disease or Parkinson's disease (no human trials; preclinical evidence only)
- Use in place of psychiatric care for severe depression, suicidal ideation, or psychotic features
Cautions
- Severe depression and suicidality: Maca has not been tested as a treatment for severe depression. Severe depression, suicidal thoughts, or psychotic features are signs that hospitals and mental-health services treat as urgent.
- Bipolar disorder: the trial evidence in bipolar disorder is essentially nonexistent. The general principle that antidepressant interventions can precipitate manic episodes in unrecognized bipolar disorder applies to any putative mood-elevating intervention, including Maca. In people with bipolar disorder, a mood-lifting treatment can trigger a manic episode (abnormally high or irritable mood, little need for sleep, racing thoughts, risky behaviour).
- Drug interactions with antidepressants: no major interactions documented. In the Dording 2008 and 2015 trials, Maca was taken alongside selective serotonin reuptake inhibitors (and serotonin-norepinephrine reuptake inhibitors in 2015) and was well tolerated. There are no published reports of serotonin syndrome from Maca-SSRI combinations.
- Pregnancy and lactation: there is not enough safety data on Maca during pregnancy or breastfeeding, and none of the mood trials studied depression after childbirth.
- Cognitive endpoint expectations: as discussed above, the human cognitive evidence is limited. No human trial has shown that Maca improves memory or thinking; the rodent data are promising but not yet translated.
- Placebo effect in mood contexts: mood interventions are particularly susceptible to placebo effect, and uncontrolled subjective improvement in users of any new supplement is common. The Brooks and Stojanovska trials used blind methodology specifically to address this, but in clinical practice the boundary between true effect and placebo response is difficult to draw at the individual patient level. This is not a reason to dismiss the benefit; it means one person's experience says little on its own.
- Quality and consistency: as with all Maca uses, sourcing matters. Studies that state where their Maca was grown (often the Junín plateau in Peru) and its color type are easier to compare than those using unspecified commodity Maca. The Brooks trial used generic Maca powder; other positive trials have used standardized extracts. There is no clear consensus on which preparation is optimal for mood endpoints specifically.
Key Research Papers
- Brooks NA et al. (2008). Beneficial effects of Lepidium meyenii (Maca) on psychological symptoms and measures of sexual dysfunction in postmenopausal women are not related to estrogen or androgen content. Menopause, 15(6):1157-1162. — PubMed PMID: 18784609
- Stojanovska L et al. (2015). Maca reduces blood pressure and depression, in a pilot study in postmenopausal women. Climacteric, 18(1):69-78. — PubMed PMID: 24931003
- Rubio J et al. (2007). Aqueous and hydroalcoholic extracts of Black Maca (Lepidium meyenii) improve scopolamine-induced memory impairment in mice. Food and Chemical Toxicology, 45(10):1882-1890. — PubMed PMID: 17543435
- Rubio J et al. (2006). Effect of three different cultivars of Lepidium meyenii (Maca) on learning and depression in ovariectomized mice. BMC Complementary and Alternative Medicine, 6:23. — PubMed PMID: 16796734
- Guo SS et al. (2016). Preservation of cognitive function by Lepidium meyenii (Maca) is associated with improvement of mitochondrial activity and upregulation of autophagy-related proteins in middle-aged mouse cortex. Evidence-Based Complementary and Alternative Medicine, 2016:4394261. — PubMed PMID: 27648102
- Pino-Figueroa A et al. (2010). Neuroprotective effects of Lepidium meyenii (Maca). Annals of the New York Academy of Sciences, 1199:77-85. — PubMed PMID: 20633111
- Dording CM et al. (2008). A double-blind, randomized, pilot dose-finding study of maca root (L. meyenii) for the management of SSRI-induced sexual dysfunction. CNS Neuroscience and Therapeutics, 14(3):182-191. — PubMed PMID: 18801111
- Dording CM et al. (2015). A double-blind placebo-controlled trial of maca root as treatment for antidepressant-induced sexual dysfunction in women. Evidence-Based Complementary and Alternative Medicine, 2015:949036. — PubMed PMID: 25954318
- Pino-Figueroa A et al. (2011). Mechanism of action of Lepidium meyenii (Maca): An explanation for its neuroprotective activity. American Journal of Neuroprotection and Neuroregeneration, 3:87-92. — doi:10.1166/ajnn.2011.1035
- Yang Q et al. (2016). Effects of macamides on endurance capacity and anti-fatigue property in prolonged swimming mice. Pharmaceutical Biology, 54(5):827-834. — PubMed PMID: 26453017
- Hajdu Z et al. (2014). Identification of endocannabinoid system-modulating N-alkylamides from Heliopsis helianthoides var. scabra and Lepidium meyenii. Journal of Natural Products, 77(7):1663-1669. — PubMed PMID: 24972328
- Gonzales-Arimborgo C et al. (2016). Acceptability, safety, and efficacy of oral administration of extracts of black or red Maca (Lepidium meyenii) in adult human subjects: a randomized, double-blind, placebo-controlled study. Pharmaceuticals (Basel), 9(3):49. — PubMed PMID: 27548190
- de Aquino ACQ et al. (2025). Pharmacological treatment of antidepressant-induced sexual dysfunction in women: a systematic review and meta-analysis of randomized clinical trials. Clinics (Sao Paulo), 80:100602. — PubMed PMID: 39985829