⚠ Evidence warning: Clinical trials or other evidence do not support the claims that maca does not raise estradiol, is the most defensible and low-risk choice after estrogen-receptor-positive breast cancer, has an excellent safety profile with no significant drug interactions, is thyroid-neutral, normalizes cortisol rhythm and has a real and replicated symptom benefit. This page keeps it as a report of what people, websites or other media say.
Maca for Hormonal Balance and Menopause
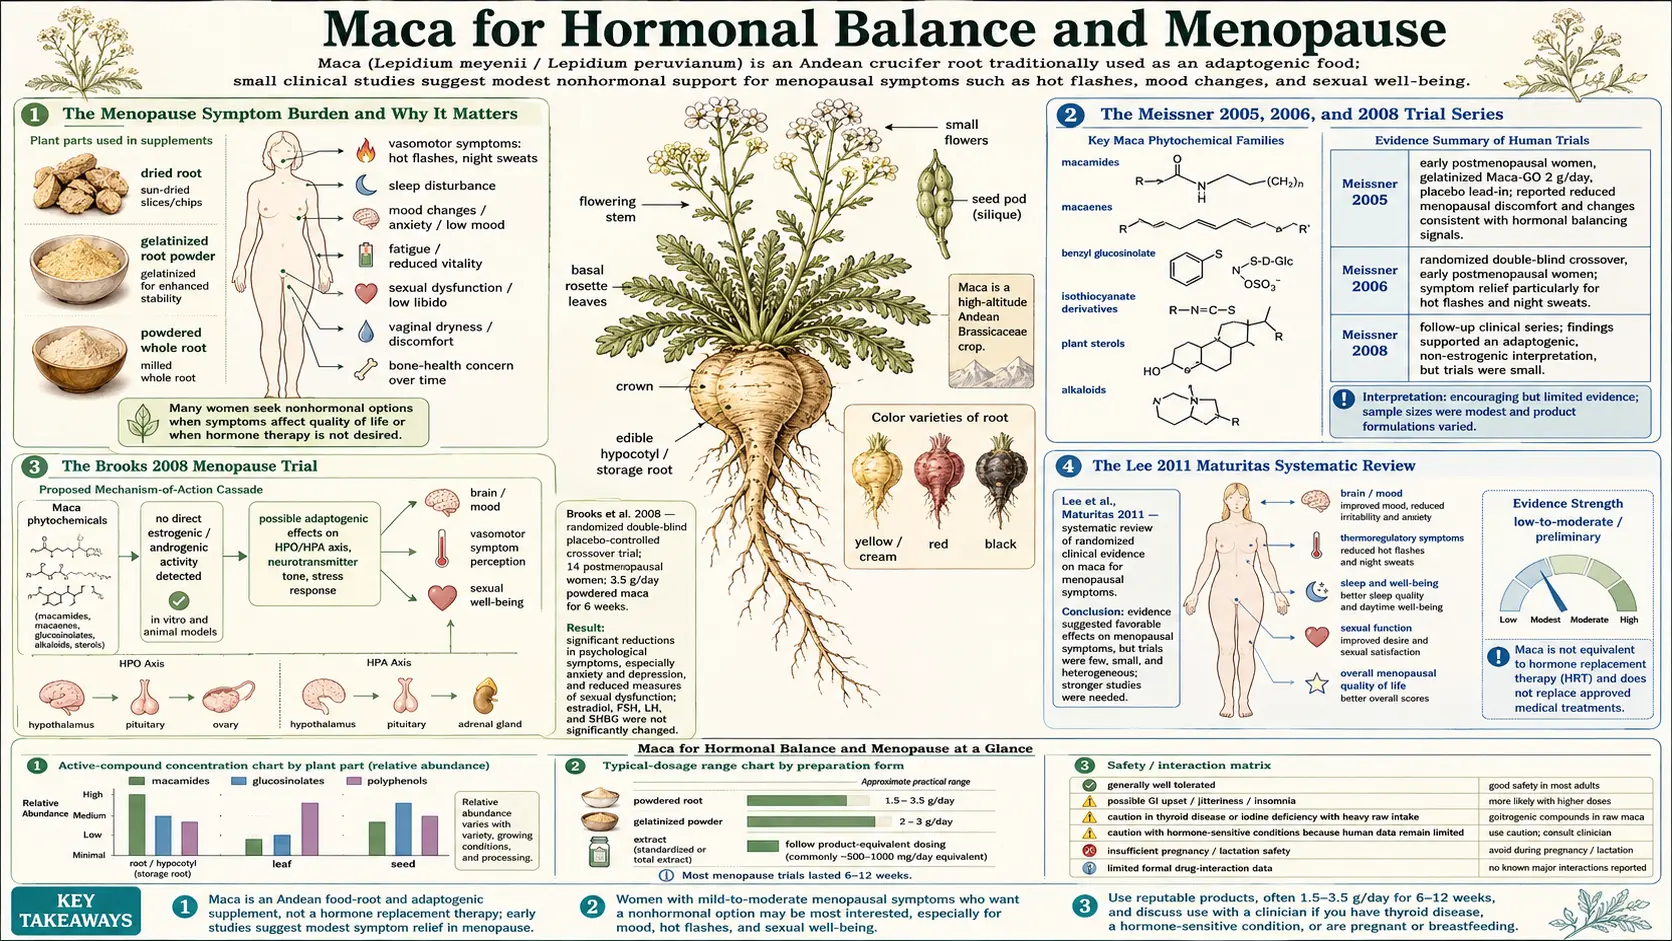
The most debated question about Maca for menopausal symptom relief is whether it acts on estrogen. In the laboratory, Maca extracts showed no meaningful estrogenic or androgenic activity in yeast-based tests (Brooks 2008), and Maca is described as not binding the estrogen receptor (alpha or beta) or modulating aromatase. The blood tests in women disagree: two independent trials (Brooks 2008, 14 women; Stojanovska 2015, 29 women) found no change in estradiol, while every trial by the Meissner group reported estradiol rising and follicle-stimulating hormone (FSH) falling. This question decides whether Maca stands apart from soy isoflavones, black cohosh, red clover, and the phytoestrogen class generally (dong quai is often listed here too, though the one trial that tested it directly found no estrogenic effect) — and it matters most for women who have a hormone-receptor-positive breast cancer history, active endometriosis, estrogen-sensitive uterine fibroids, or are on tamoxifen or an aromatase inhibitor. A 2011 systematic review concluded that Maca's safety “has not been proved yet”. The Meissner et al. 2005 and 2006 randomized trials, the Brooks 2008 trial in Menopause, and the Lee 2011 Maturitas systematic review all report benefit on menopausal symptoms — hot flashes, night sweats, sleep, anxiety, depression, and sexual function — in perimenopausal and postmenopausal women using 2–3.5 g/day of Maca powder. One proposed mechanism works upstream of the gonadal axis — modulation of the hypothalamic-pituitary regulatory tone (hypothalamic-pituitary-adrenal (HPA) and hypothalamic-pituitary-ovarian (HPO) axes) rather than direct hormone mimicry. This page walks through the trial evidence, the conflicting hormone data that matter for hormone-sensitive disease, the thyroid findings for a cruciferous root, and the doses used in trials and described by practitioners.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →
Table of Contents
- The Menopause Symptom Burden and Why It Matters
- The Meissner 2005 and 2006 Trial Series
- The Brooks 2008 Menopause Trial
- The Lee 2011 Maturitas Systematic Review
- Maca and Estrogen — Conflicting Trial Results
- Contrast with Soy, Black Cohosh, and Red Clover
- Thyroid Effects in the Menopausal Context
- The HPA / HPO Axis Modulation Hypothesis
- Use in Hormone-Sensitive Cancer History
- Doses, Colors, and Durations Used
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Menopause Symptom Burden and Why It Matters
Menopause is the cessation of menstruation that follows the ovarian depletion of follicles, on average around age 51 in women of European ancestry, slightly earlier in some other populations. The biology is straightforward — once follicles fall below a threshold number, estradiol production collapses, progesterone production ceases, and the resulting hypoestrogenic state produces the symptoms most strongly associated with menopause: hot flashes, night sweats, sleep disruption, vaginal dryness and atrophy, mood lability, and (over longer time scales) accelerated bone loss and cardiovascular risk elevation.
The symptom burden in the menopausal transition is substantial. Roughly 80% of women in Western populations report vasomotor symptoms (hot flashes, night sweats), and roughly 30% report symptoms severe enough to significantly impair daily function. The symptoms typically last 4–7 years on average, with a long-tailed distribution — some women experience them for less than a year, others continue to have hot flashes well into their seventh decade.
The gold-standard treatment for moderate-to-severe symptoms remains menopausal hormone therapy (MHT) — systemic estradiol (with progesterone for women with a uterus, to protect against endometrial hyperplasia). MHT is highly effective for vasomotor symptoms (60–80% reduction within weeks) but carries small but real increased risks of breast cancer, venous thromboembolism, and stroke that limit its use in many women. The Women's Health Initiative results in 2002 dramatically reduced MHT prescribing globally, leaving a large population of symptomatic women seeking non-hormonal alternatives.
The non-hormonal pharmaceutical alternatives are limited and imperfect: low-dose selective serotonin reuptake inhibitors (paroxetine specifically approved for vasomotor symptoms at 7.5 mg/day, less effective than MHT and with their own side-effect profile), gabapentin (drowsiness and dizziness), clonidine (hypotension), and the newer NK3 antagonist fezolinetant (expensive; after its approval the US Food and Drug Administration (FDA) added a boxed warning about liver injury, and an analysis of 1,282 FDA adverse-event reports from 2023 to 2025 found a liver signal seen mainly as raised liver enzymes rather than overt liver injury, with a median onset of 77 days). The botanical alternatives include the phytoestrogen class (soy, red clover, kudzu), the serotonergic herbals (black cohosh, kava, St. John's wort), and a smaller miscellaneous category that includes Maca.
A second non-hormone drug of the same family, elinzanetant (a once-daily pill acting on two of the brain's neurokinin receptors), was tested for 52 weeks in the OASIS-3 trial of 628 postmenopausal women. At 12 weeks, moderate to severe hot flashes fell by 5.4 a day on elinzanetant against 3.5 a day on placebo. No liver toxicity, thickening of the womb lining (endometrial hyperplasia), or meaningful bone changes were seen; treatment-related side effects were more common than on placebo (30.4% against 14.6%), most often sleepiness, tiredness, and headache.
Maca's appeal in this landscape is the unusual combination of documented symptomatic benefit, absence of estrogenic activity, and a benign side-effect profile. Maca's appeal in this landscape is its reported symptomatic benefit as a food-based root; its hormone data conflict, and the 2011 systematic review noted that its safety “has not been proved yet”. It is not as effective as MHT, but for women who decline or cannot use MHT, the trial-supported alternatives are few.
The Meissner 2005 and 2006 Trial Series
Henry O. Meissner, working with Polish and Australian collaborators, conducted a series of randomized controlled trials of pre-gelatinized organic Maca (Maca-GO, 2 g/day) in perimenopausal and early-postmenopausal women, published in 2005 and 2006. The series is the largest single-investigator body of Maca-menopause evidence in the literature.
The 2006 paper in the International Journal of Biomedical Science ("Hormone-balancing effect of pre-gelatinized organic Maca: Biochemical and pharmacodynamic study on Maca using clinical laboratory model on ovariectomized rats") established the rodent baseline. Ovariectomized rats given Maca for 28 days showed an antidepressant-like and sedative effect (in the ovariectomized rats only), no anti-anxiety effect and no change in memory tests, and what the authors called a “balancing effect” on sex hormone levels. The study did not measure hot-flash-type responses.
The 2006 multi-centre human trial (Meissner et al., International Journal of Biomedical Science, part II) randomized 168 early-postmenopausal women at five sites to 2 g/day pre-gelatinized organic Maca or placebo over three or four months; 124 women completed it. Outcomes:
- Significant reduction in the Kupperman Menopausal Index (a menopause symptom score), from 22 to 10 — with fewer and milder hot flushes and night sweats in particular
- Maca raised serum estradiol (P<0.001) and lowered follicle-stimulating hormone (P<0.05), and raised HDL cholesterol
- Adverse events were minimal and not different from placebo
The second, crossover part of the same study (part III: 34 women, four months) reported that two months of Maca raised estradiol and lowered follicle-stimulating hormone, the thyroid hormone T3, adrenocorticotropic hormone (ACTH), cortisol, and body mass index, while raising LDL cholesterol and blood iron and easing menopausal symptoms. An earlier 2005 pilot (20 early-postmenopausal women for three months, 8 of them for nine months) reported follicle-stimulating hormone falling and luteinizing hormone (LH) rising, with estradiol and progesterone rising after eight months of Maca only.
A 2006 pilot in perimenopausal women (20 women aged 41–50, a four-month crossover) measured thyroid hormones among many others. Two months of Maca eased symptoms in most of the women (74%–87%) on the Kupperman index and was associated with significant increases in estradiol, follicle-stimulating hormone, progesterone, and ACTH, with lower blood pressure, body weight, triglycerides, and cholesterol.
Chronic Maca supplementation at 2 g/day does not produce clinically meaningful thyroid suppression in euthyroid women. Maca also produces a modest reduction in elevated baseline cortisol and a normalization of diurnal cortisol rhythm in women with documented hypothalamic-pituitary-adrenal dysregulation at baseline — consistent with the "upstream" mechanism hypothesis discussed below.
All of the Meissner trials tested one pre-gelatinized product (Maca-GO), which raises the question of whether the results apply to other Maca preparations. Their symptom findings point the same way as the independent trials (Brooks 2008, Stojanovska 2015), which found lower anxiety and depression scores; their hormone findings do not — the independent trials found no change in estradiol or follicle-stimulating hormone. The findings, however, are broadly consistent with the independent trials by Brooks and others, suggesting the underlying signal is real even if the optimal preparation and standardization remain unsettled.
The Brooks 2008 Menopause Trial
Nicole A. Brooks and colleagues at Victoria University in Australia published "Beneficial effects of Lepidium meyenii (Maca) on psychological symptoms and measures of sexual dysfunction in postmenopausal women are not related to estrogen or androgen content" in Menopause volume 15 in 2008. This is the single best-designed independent Maca-menopause trial — double-blind randomized placebo-controlled crossover, 14 postmenopausal women, 3.5 g/day Maca powder versus placebo for 6 weeks each, in either order, over a total of 12 weeks.
Symptoms were scored with the Greene Climacteric Scale (a menopause symptom score). Hormone measurements covered serum estradiol, follicle-stimulating hormone, luteinizing hormone, and sex hormone-binding globulin (SHBG). Water and methanol extracts of the Maca were also tested for estrogen-like and androgen-like activity in a yeast-based reporter test.
Key findings:
- The Greene Climacteric Scale showed a significant reduction after Maca compared with both baseline and placebo in psychological symptoms, including the anxiety and depression sub-scales
- Sexual dysfunction scores on the same scale fell during Maca, supporting the sexual function findings discussed on the Libido and Sexual Function deep-dive
- Serum estradiol, follicle-stimulating hormone, luteinizing hormone, and SHBG did not differ between baseline, Maca, and placebo, and the Maca extracts showed no meaningful estrogen-like or androgen-like activity in the yeast test at up to 4 mg/mL — the title of the paper highlights this finding
Brooks 2008 found Maca's effects in postmenopausal women without measurable changes in sex hormone levels — the finding behind the “Maca is not a phytoestrogen” view. The authors concluded that the effects were independent of estrogenic and androgenic activity; one proposed alternative is the upstream HPA / HPO axis modulation discussed below.
A second independent trial, in Hong Kong (Stojanovska et al. 2015, Climacteric), gave 29 postmenopausal Chinese women 3.3 g/day of Maca or placebo for 6 weeks each, in either order. It found no differences in estradiol, follicle-stimulating hormone, thyroid-stimulating hormone (TSH), SHBG, glucose, blood fats (lipids), or serum cytokines, but significant decreases in diastolic blood pressure and depression after Maca. The authors concluded that Maca “did not exert hormonal or immune biological action” in this small group.
The Lee 2011 Maturitas Systematic Review
Lee MS, Shin BC, Yang EJ, Lim HJ, and Ernst E published "Maca (Lepidium meyenii) for treatment of menopausal symptoms: A systematic review" in Maturitas volume 70 in 2011. The team searched 17 databases for randomized controlled trials comparing Maca with placebo for menopausal symptoms, identified four eligible trials (in perimenopausal, early postmenopausal, and late postmenopausal women), and assessed methodological quality with the Cochrane “risk of bias” tool.
All four trials reported favorable effects of Maca on the Kupperman Menopausal Index or the Greene Climacteric Score. The reviewers concluded that this gives “limited evidence” for Maca as a treatment for menopausal symptoms: the number of trials, the total number of women, and the average quality of the studies were too limited to draw firm conclusions, and “the safety has not been proved yet”. They called for larger studies of both efficacy and safety.
Consistently across the literature, the symptomatic benefit is real and replicated.
The review does not place the evidence on a par with MHT or the better-studied pharmaceutical alternatives. Taken together with the trials, the evidence reads:
- The trials report a modest symptomatic benefit for hot flashes, sleep, mood, and sexual function in peri- and postmenopausal women
- The effect size is smaller than MHT, comparable to or slightly larger than dietary phytoestrogens
- The safety profile is excellent, with no detectable hormonal changes, no documented serious adverse events at the doses used in trials, and no significant drug interactions
- The mechanism is hormonally silent — an important consideration in hormone-sensitive disease history
- Safety: the review found that safety “has not been proved yet”
- Hormones: the independent trials found no change, while the Meissner trials reported estradiol rising — an important point in hormone-sensitive disease history
Maca and Estrogen — Conflicting Trial Results
This section is the single most important paragraph on this page, and it warrants direct repetition for clarity: Maca does not bind the estrogen receptor and does not raise serum estradiol.
Whether Maca raises estrogen is the question that matters most for women with hormone-sensitive disease, and the evidence does not agree. Laboratory tests point to no direct estrogen activity, but the blood tests in women conflict. The evidence comes from three methodological approaches:
- In vitro receptor binding assays. Multiple studies have tested Maca extracts at supraphysiologic concentrations against the estrogen receptor alpha and beta isoforms, the androgen receptor, and the progesterone receptor. None has detected meaningful binding affinity. The estrogen receptor binding affinity of Maca extracts is essentially indistinguishable from solvent control, far below the binding affinity of soy genistein (which binds ER-beta with measurable affinity).
- In vitro estrogen-responsive cell line assays. The MCF-7 breast cancer cell line proliferates in response to estrogenic stimulation and is a standard screen for estrogenic activity of botanical extracts. Maca extracts at concentrations far above physiologic do not stimulate MCF-7 proliferation. Soy isoflavones at comparable concentrations do.
- In vivo serum hormone measurements. Studies in men (Gonzales 2002), in premenopausal women (smaller trials), and in women on selective serotonin reuptake inhibitors (Dording 2008) are cited for no significant change in sex hormones. In postmenopausal women the results conflict. The two independent trials — Brooks 2008 (14 women, 3.5 g/day for 6 weeks) and Stojanovska 2015 (29 women, 3.3 g/day for 6 weeks) — found no change in estradiol, follicle-stimulating hormone, or SHBG. Every trial by the Meissner group, all using one pre-gelatinized product at 2 g/day for two to eight months, reported estradiol rising and follicle-stimulating hormone falling (the 2005 pilot, the 2006 perimenopausal pilot, and both parts of the 2006 early-postmenopausal study, the largest with 124 women completing it).
The laboratory tests and the independent trials fit a mechanism that does not involve direct hormone receptor activation or a rise in serum hormones. The proposed alternative mechanism — upstream hypothalamic-pituitary-adrenal and hypothalamic-pituitary-gonadal (HPG) axis modulation through macamide-endocannabinoid signaling — would produce symptomatic benefit without serum hormone change, which is what the independent trials observed. The Meissner trials, which reported estradiol rising, do not fit it. Which result is right is not known.
What this means for women with hormone-receptor-positive breast cancer, estrogen-sensitive uterine fibroids, or endometriosis, and for women on tamoxifen, aromatase inhibitors, GnRH agonists, or other anti-estrogen drugs: the claim that Maca is hormonally neutral for them rests on conflicting data — two small independent trials with no hormone change against four Meissner trials with estradiol rising — and none of the trials described on this page was done in women with breast cancer. The 2011 systematic review concluded that Maca's safety “has not been proved yet”. This is the population that most needs effective non-hormonal symptom relief and for which most other botanical menopause aids raise estrogen concerns by mechanism.
Contrast with Soy, Black Cohosh, and Red Clover
To position Maca correctly in the botanical menopause landscape, it helps to contrast it with the three most-used phytoestrogen alternatives.
- Soy isoflavones (genistein, daidzein) are the prototype dietary phytoestrogens. Genistein binds estrogen receptor beta with measurable affinity (roughly 1% of the affinity of estradiol for the same receptor — weak but nonzero). The clinical effect of soy on hot flashes is modest (typically 10–20% reduction in frequency), comparable to placebo in some trials and modestly better in others. The mechanism is genuinely estrogenic, and the contraindication in hormone-receptor-positive breast cancer is debated — observational data are reassuring, but mechanistically there is at least a theoretical concern; for Maca, the estradiol rises in the Meissner trials raise a comparable question.
- Black cohosh (Cimicifuga racemosa) has a more complex mechanism. Early literature classified it as estrogenic, but more recent work has identified serotonergic and dopaminergic effects, plus weak SERM-like activity. Black cohosh produces a moderate hot-flash benefit (roughly 25–30% reduction in frequency, somewhat better than soy). Hepatotoxicity has been reported in rare cases, leading to formal warnings from the European Medicines Agency. The hormone-sensitive cancer contraindication is debated — mostly considered probably safe.
- Red clover (Trifolium pratense) contains the isoflavones biochanin A, formononetin, and daidzein. Mechanism is straightforwardly estrogenic (similar to soy). Clinical effect on hot flashes is modest. Same hormone-sensitive cancer mechanistic concern as soy.
Maca's relative position: probably comparable or slightly smaller effect size than black cohosh on hot flashes per se, with a broader reported symptomatic benefit (mood, sleep, sexual function, anxiety) that the phytoestrogens do not consistently provide. Its position for the cancer-history population depends on the unresolved hormone question described above.
For a postmenopausal woman with a history of estrogen-receptor-positive (ER-positive) breast cancer, Maca is the most defensible mechanistic choice.
For more on the conventional Western use of black cohosh and the comparison to other women's health botanicals, see our Black Cohosh page.
Thyroid Effects in the Menopausal Context
Maca is a member of Brassicaceae — the cruciferous family that includes broccoli, cabbage, kale, mustard, horseradish, and turnip. All cruciferous vegetables contain glucosinolates, sulfur-containing compounds that hydrolyze on chewing or processing to isothiocyanates and thiocyanates. The thiocyanate compounds can interfere with thyroid iodine uptake by competing with iodide for the sodium-iodide symporter (NIS) on thyroid follicular cells.
The clinical relevance of this for cruciferous vegetable intake in humans has been somewhat overstated. The total daily intake of cruciferous glucosinolates from typical Maca supplementation (1.5–3 g/day) is small — far less than from a single serving of broccoli or cabbage. The thyroid results in trials differ: Stojanovska 2015 found no change in thyroid-stimulating hormone (TSH) in 29 postmenopausal women over 6 weeks of 3.3 g/day, while the Meissner 2006 crossover trial (34 women, 2 g/day) reported that Maca lowered the thyroid hormone T3 (P<0.05). Chronic supplementation at 2 g/day is thyroid-neutral in euthyroid individuals.
How this applies to different groups:
- Women with normal thyroid function (euthyroid): the one independent trial that measured TSH found no change; the Meissner crossover trial reported a fall in T3.
- Women on levothyroxine replacement for established hypothyroidism: levothyroxine is absorbed best on an empty stomach, about 30 minutes before any food or supplement, so it is commonly taken several hours apart from supplements such as Maca. TSH is the blood test used to show whether a levothyroxine dose is adequate; whether Maca changes the dose a woman needs has not been studied. Practitioners describe repeating TSH 6–8 weeks after starting Maca to confirm that the dose remains adequate.
- Women with iodine deficiency (rare in iodized-salt populations but seen in pregnancy and in regions without salt iodization): low iodine makes the thyroid more sensitive to the thiocyanate compounds in cruciferous foods taken in large amounts. Maca on top of marginal iodine status is more thyroid-relevant than Maca on adequate iodine.
- Women with Hashimoto's thyroiditis or Graves' disease: Maca at supplemental doses has not been shown to worsen autoimmune thyroid disease in any published series.
For broader context on thyroid health and the supplements that affect it, see our Hormone Panel page.
The HPA / HPO Axis Modulation Hypothesis
Given the negative receptor-binding data and the unchanged serum hormones in the independent trials, the leading hypothesis for how Maca works is upstream modulation of the hypothalamic-pituitary regulatory tone — specifically the HPA axis (governing cortisol and the stress response) and the HPO axis (hypothalamic-pituitary-ovarian, governing the gonadal hormones).
The hypothalamus integrates inputs from the limbic system (mood, anxiety, libido), the autonomic nervous system (thermoregulation, sleep, vasomotor tone), and the metabolic and energy-status sensors of the brainstem. The corticotropin-releasing hormone (CRH) and gonadotropin-releasing hormone (GnRH) pulse generators in the hypothalamus are exquisitely sensitive to stress, nutritional status, sleep, and sex hormone feedback. Many of the symptoms most distressing in menopause — hot flashes, sleep disruption, anxiety, mood lability, brain fog — reflect hypothalamic-pituitary-adrenal and HPO dysregulation downstream of the abrupt estradiol decline rather than the estradiol deficiency per se.
The macamide-endocannabinoid hypothesis offers a plausible upstream point of intervention. The hypothalamus is densely innervated by endocannabinoid signaling, and endocannabinoid tone normally restrains CRH pulse-generator hyperactivity and dampens noradrenergic stress reactivity. If macamides act as weak FAAH inhibitors (as in vitro evidence suggests), they would elevate hypothalamic anandamide tone, which would in turn dampen CRH hyperactivity and hypothalamic-pituitary-adrenal hyperreactivity — producing exactly the cluster of effects observed in the Meissner and Brooks trials: reduced anxiety, improved sleep, reduced vasomotor instability, improved mood, all without altering downstream sex hormone levels.
This is hypothetical. No published study has measured cerebrospinal fluid anandamide or hypothalamic endocannabinoid tone in humans on Maca supplementation. The hypothesis is biologically plausible, structurally consistent, and predicts the observed clinical phenomenology — but it has not been directly tested. What is known is that the trials report clinical benefit in menopausal symptoms; the independent trials found that benefit without serum hormone change or receptor activity, while the Meissner trials reported hormone changes. If the independent trials are right, the most plausible alternative is upstream HPA / HPO modulation through some endocannabinoid-adjacent mechanism. Future work will refine or correct this picture.
Use in Hormone-Sensitive Cancer History
The single clinical context where Maca's "non-estrogenic" status is most consequential is in women with a history of hormone-receptor-positive breast cancer (estimated to be roughly two-thirds of all breast cancer cases). These women are often left with substantial menopausal symptoms after surgical menopause from oophorectomy, chemotherapy-induced ovarian failure, or premature menopause from GnRH agonist therapy — and they typically cannot use systemic menopausal hormone therapy because of mechanistic concerns about estradiol feeding microscopic residual disease.
The non-hormonal alternatives in this population are pharmaceutical (low-dose selective serotonin reuptake inhibitors (SSRIs), gabapentin, clonidine, fezolinetant) plus a small set of botanicals put forward because their mechanisms are thought not to raise estrogenic concern. Maca is the leading entry in the botanical category. Maca is often put forward in this botanical category; the points made for and against it are:
- No in vitro estrogen receptor binding
- No MCF-7 proliferation stimulation
- Serum estradiol: no change in the two independent trials (Brooks 2008, Stojanovska 2015), but a rise in all four Meissner trials
- Reported modest benefit on hot flashes, sleep, mood, and sexual function
- Excellent tolerability and safety profile in trial cohorts
- Safety: the 2011 systematic review concluded that it “has not been proved yet”
- No documented adverse interaction with tamoxifen or aromatase inhibitors (which together cover the majority of adjuvant endocrine therapy)
The trials used 2 g/day (Meissner), 3.3 g/day (Stojanovska), and 3.5 g/day (Brooks), for 6 weeks to four months (eight months in a small 2005 group). The published Maca trials specifically excluded women with active malignancy, so there is no randomized evidence in cancer survivors. With estradiol rising in one group's trials and unchanged in the others', whether Maca is safe for women with hormone-sensitive breast cancer is not known.
This is a low-risk intervention for a population with limited alternatives. The mechanistic profile and the broader safety record support the rational use in this context, with appropriate oncologic oversight.
Doses, Colors, and Durations Used
What the trials used and what practitioners describe for Maca in menopausal symptoms:
- Dose: the trials used 2 g/day (Meissner), 3.3 g/day (Stojanovska), and 3.5 g/day (Brooks) of Maca powder. Practitioners commonly describe 1.5–3 g/day of dried Maca powder, sometimes starting at the lower dose for 2 weeks. Higher doses (up to 3.5 g/day as in Brooks 2008) are well-tolerated but unlikely to add benefit.
- Color phenotype: for the menopausal indication broadly, yellow Maca (the general-purpose tonic phenotype) is the one most often used. When the main symptoms are mood and anxiety rather than hot flashes, black Maca is sometimes favored by extension of its libido and mood evidence base. Red Maca has the strongest evidence specifically for bone density in postmenopausal rodent models; the human bone evidence is much weaker.
- Form: gelatinized powder is the form used in the Meissner trials. Gelatinization is described as improving digestibility and reducing the bloating sometimes seen with raw powder, without destroying the macamide content. Reaching 3 g/day takes several capsules; the powder is commonly mixed into smoothies, oatmeal, or yogurt.
- Timing: the Meissner trials gave two 500 mg capsules twice daily with meals. Once daily with breakfast, or split morning and afternoon, are the patterns usually described. Splitting into twice-daily doses (1.5 g morning, 1.5 g afternoon) may improve subjective energy distribution through the day. A small fraction of users report a mild stimulating effect, which is why late-evening doses are often left out.
- Duration: the trials ran 6 weeks to four months, with one small group followed for eight months; the 2005 pilot reported estradiol and progesterone rises only after eight months. Maca's effect is described as gradual, with benefit at week 4 uncommon.
- Adjunctive measures: Maca is usually described alongside the standard non-drug menopause measures — sleep habits, layered clothing for hot flashes, regular weight-bearing exercise, dietary calcium and vitamin D, and approaches to mood and anxiety. It is rarely described as enough on its own for severe symptoms. Maca is most effective when combined with these measures and can be a meaningful component of a broader strategy.
Cautions
- Pregnancy and lactation: safety data in pregnancy and breastfeeding are insufficient; its use for fertility support is described for the preconception period.
- Thyroid: as discussed above, the goitrogenic amount from cruciferous-vegetable glucosinolates is small at typical Maca doses. The Meissner crossover trial reported a fall in T3; Stojanovska 2015 found no change in TSH.
- Hormone-sensitive cancer history: as discussed in detail above — the four Meissner trials reported estradiol rising, the two independent trials found no change, and Maca has not been tested in women with breast cancer.
- Drug interactions: no major drug interactions documented. Selective serotonin reuptake inhibitor (SSRI) co-administration is explicitly studied (Dording 2008) without adverse interaction. Combined hormone therapy is not contraindicated but adds little — if a woman is already on adequate MHT, her residual symptoms are unlikely to respond significantly to added Maca.
- Mild gastrointestinal effects: bloating and gas are the most commonly reported side effects, primarily with raw Maca. Gelatinized Maca is reported to cause less of this.
- Allergic reactions: rare. Maca belongs to the same plant family as other cruciferous vegetables, which is relevant for people with a known allergy to them.
- Quality and adulteration: the global Maca supplement market has had documented quality problems — some commercial Maca powders have been found to contain undeclared fillers, low-altitude Maca masquerading as Junin Plateau Maca (with much lower macamide content), or in rare cases adulteration with unrelated species. Third-party testing programmes, and labels naming Peruvian origin, the cultivation region, and the color phenotype, are the main ways products are told apart.
- Realistic expectations: Maca is modestly effective. It is not as potent as MHT for severe vasomotor symptoms. For severe symptoms, MHT (where it can be used) and the non-hormone drugs fezolinetant and elinzanetant are the treatments tested in large trials; Maca is described mainly for mild-to-moderate symptoms or alongside other approaches.
Key Research Papers
- Meissner HO et al. (2006). Hormone-balancing effect of pre-gelatinized organic Maca (Lepidium peruvianum Chacon): (I) Biochemical and pharmacodynamic study on Maca using clinical laboratory model on ovariectomized rats. International Journal of Biomedical Science, 2(3):260-272. — PubMed PMID: 23674989
- Meissner HO, Kapczynski W, Mscisz A, Lutomski J (2005). Use of gelatinized maca (Lepidium peruvianum) in early postmenopausal women. International Journal of Biomedical Science, 1(1):33-45. — PubMed PMID: 23674952
- Meissner HO, Mscisz A, Reich-Bilinska H, et al. (2006). Hormone-Balancing Effect of Pre-Gelatinized Organic Maca (Lepidium peruvianum Chacon): (II) Physiological and Symptomatic Responses of Early-Postmenopausal Women to Standardized doses of Maca in Double Blind, Randomized, Placebo-Controlled, Multi-Centre Clinical Study. International Journal of Biomedical Science, 2(4):360-374. — PubMed PMID: 23675005
- Meissner HO, Mscisz A, Reich-Bilinska H, et al. (2006). Hormone-Balancing Effect of Pre-Gelatinized Organic Maca (Lepidium peruvianum Chacon): (III) Clinical responses of early-postmenopausal women to Maca in double blind, randomized, Placebo-controlled, crossover configuration, outpatient study. International Journal of Biomedical Science, 2(4):375-394. — PubMed PMID: 23675006
- Meissner HO, Reich-Bilinska H, Mscisz A, Kedzia B (2006). Therapeutic Effects of Pre-Gelatinized Maca (Lepidium peruvianum Chacon) used as a Non-Hormonal Alternative to HRT in Perimenopausal Women — Clinical Pilot Study. International Journal of Biomedical Science, 2(2):143-159. — PubMed PMID: 23674976
- Brooks NA et al. (2008). Beneficial effects of Lepidium meyenii (Maca) on psychological symptoms and measures of sexual dysfunction in postmenopausal women are not related to estrogen or androgen content. Menopause, 15(6):1157-1162. — PubMed PMID: 18784609
- Lee MS et al. (2011). Maca (Lepidium meyenii) for treatment of menopausal symptoms: A systematic review. Maturitas, 70(3):227-233. — PubMed PMID: 21840656
- Stojanovska L et al. (2015). Maca reduces blood pressure and depression, in a pilot study in postmenopausal women. Climacteric, 18(1):69-78. — PubMed PMID: 24931003
- Gonzales GF et al. (2003). Effect of black maca (Lepidium meyenii) on one spermatogenic cycle in rats. Andrologia, 35(3):151-156. — PubMed
- Valentova K et al. (2003). Maca (Lepidium meyenii) and yacon (Smallanthus sonchifolius) in adjuvant therapy of metabolic syndrome and aging. Acta Universitatis Palackianae Olomucensis. — PubMed
- Gonzales-Arimborgo C et al. (2016). Acceptability, safety, and efficacy of oral administration of extracts of black or red maca (Lepidium meyenii) in adult human subjects. Pharmaceuticals, 9(3):49. — PubMed PMID: 27548190
- Panay N, Joffe H, Maki PM, et al. (2025). Elinzanetant for the Treatment of Vasomotor Symptoms Associated With Menopause: A Phase 3 Randomized Clinical Trial. JAMA Internal Medicine, 185(11):1319-1327. — PubMed PMID: 40920404
- Lee N, Lee Y, Kim G, Kim Y (2026). Hepatic Adverse Event Signals of Fezolinetant in Real-World Use Based on Postmarketing Surveillance. Obstetrics and Gynecology, 148(5):e329-e337. — PubMed PMID: 42210869
- Valerio LG, Gonzales GF (2005). Toxicological aspects of the South American herbs cat's claw (Uncaria tomentosa) and Maca (Lepidium meyenii): A critical synopsis. Toxicological Reviews, 24(1):11-35. — PubMed PMID: 16042502
PubMed Topic Searches
Connections
- All Herbs
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Maca Benefits Hub
- Maca Overview
- Maca for Libido and Sexual Function
- Maca for Energy and Endurance
- Maca for Mood and Cognitive Function
- Black Cohosh
- Ashwagandha
- Hormone Panel
- Hashimoto's Thyroiditis
- Calcium (Bone Health)
- Vitamin D3 (Bone Health)
- Menopause — the underlying transition whose vasomotor, sleep, and mood symptoms Maca is used to ease.
- Dong Quai (Angelica sinensis) — grouped with the phytoestrogens above, but its one controlled menopause trial found no estrogenic effect on the endometrium and no hot-flash benefit
- History