He Shou Wu Liver Health and Hepatotoxicity Warning
CRITICAL SAFETY NOTICE
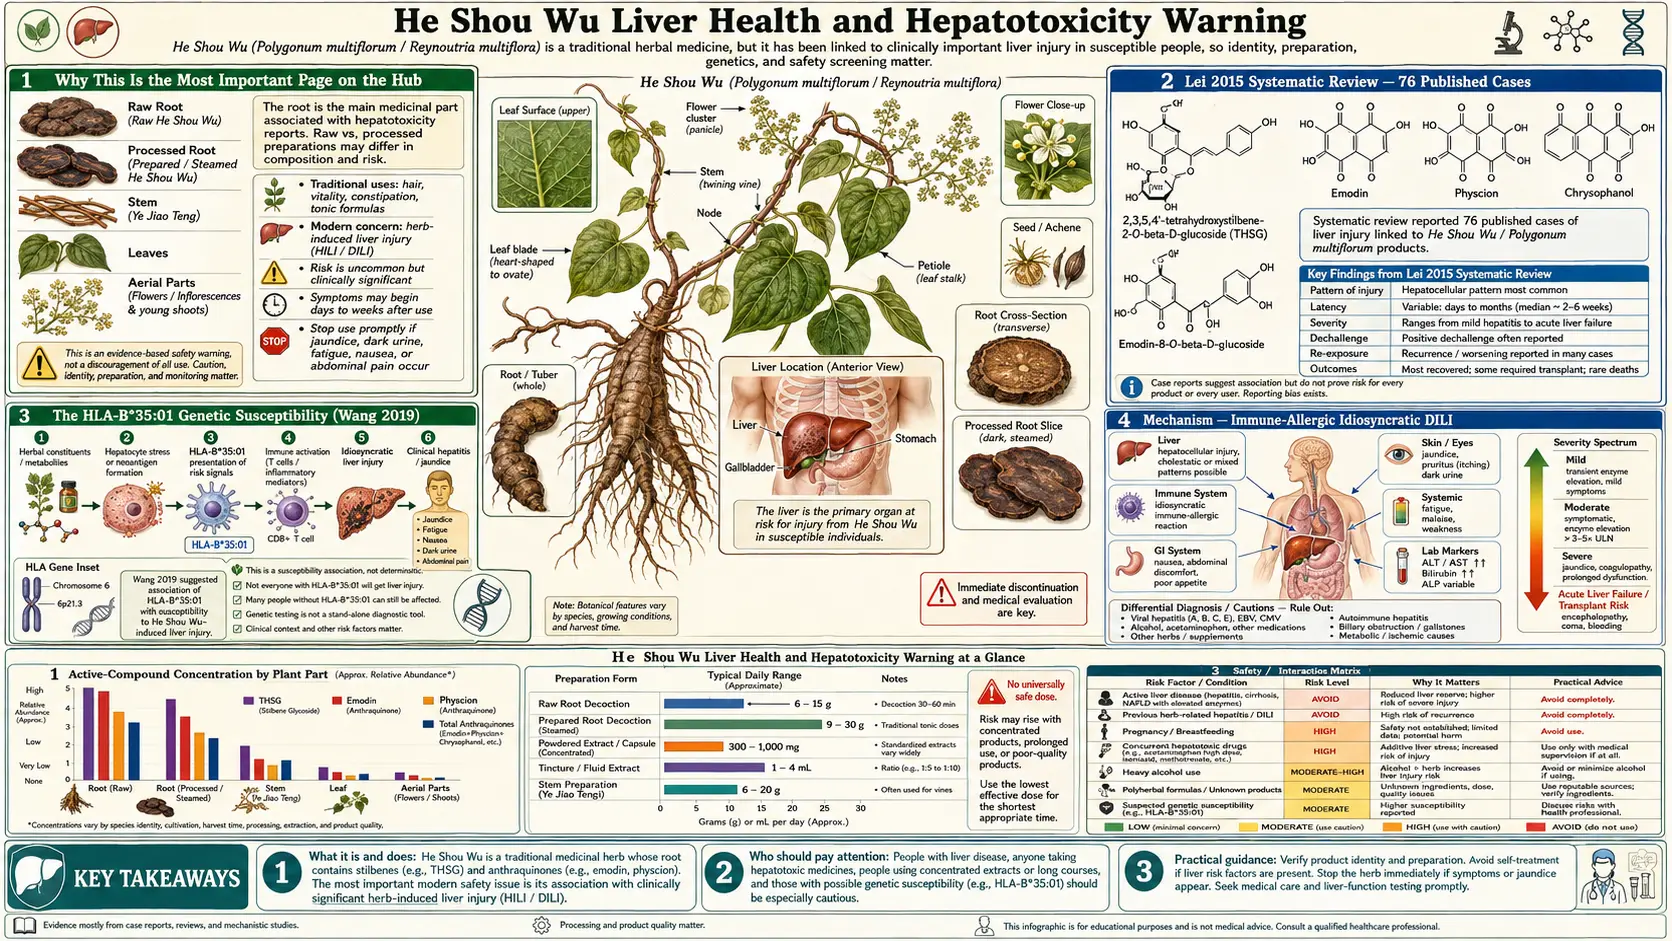
He Shou Wu is one of the most-reported single herbs in the global drug-induced liver injury (DILI) literature. This page is the most important page on the entire He Shou Wu hub. Liver injury from the herb can be silent for weeks, and liver blood tests (liver function tests) are the only way to see it before symptoms appear. In someone taking He Shou Wu, new jaundice (yellow eyes or skin), dark urine, light stool, pain under the right ribs (right upper quadrant, RUQ, pain), unexplained fatigue, nausea, or itching are signs of liver injury that hospitals treat as urgent.
He Shou Wu's modern reputation is dominated by two competing narratives. The traditional Chinese medicine (TCM) tradition: 800 years of use as a longevity, hair, and kidney-essence tonic with relative safety when properly processed. The modern hepatology literature: dozens of well-documented cases of severe drug-induced liver injury (DILI), some progressing to acute liver failure requiring transplantation, and an internationally recognized human leukocyte antigen-B*35:01 genetic susceptibility allele (Li et al. 2019, Hepatology). Both narratives are true. The reconciliation is that the hepatotoxicity appears largely idiosyncratic and immune-mediated — although the largest case review also linked most cases to long-term use and overdose — and probably occurs in only a small minority of users — but in those susceptible individuals it can be severe, unpredictable, and lethal. The processing distinction (raw sheng shou wu vs. processed zhi shou wu) matters for safety but does not eliminate the risk. This page covers the mechanism, the case literature, the regulatory landscape, the human leukocyte antigen-B*35:01 finding, the situations in which the research raises the greatest concern, the liver-test schedule described for herb users, and the warning signs of liver injury.
Table of Contents
- Why This Is the Most Important Page on the Hub
- Lei 2015 Systematic Review — 450 Cases in 76 Articles
- The Human Leukocyte Antigen-B*35:01 Genetic Susceptibility (Li 2019)
- Mechanism — Immune-Allergic Idiosyncratic DILI
- Processed (Zhi Shou Wu) vs Raw (Sheng Shou Wu)
- International Regulatory Actions
- Situations of Greatest Concern in the Research
- Situations That Add to the Risk
- How Liver Tests Track He Shou Wu Injury
- Warning Signs of Liver Injury
- What Happens When Liver Injury Is Suspected
- Key Research Papers
- Connections
- Featured Videos
Why This Is the Most Important Page on the Hub
Of the dozens of herbs in the TCM materia medica that have entered the Western herbal supplement market, He Shou Wu (Polygonum multiflorum, sold widely as Fo-Ti) has accumulated the most extensive and most concerning hepatotoxicity literature. The U.S. National Institutes of Health / National Institute of Diabetes and Digestive and Kidney Diseases (NIH/NIDDK) LiverTox database lists Polygonum multiflorum with a Category B (highly likely) causality designation for hepatocellular and cholestatic injury. The published case literature includes:
- Acute hepatocellular injury (the most common pattern, with alanine aminotransferase (ALT) typically 10 to 50× upper limit of normal)
- Cholestatic injury with prolonged jaundice and pruritus
- Mixed hepatocellular-cholestatic pattern
- Several cases of acute liver failure requiring transplantation or progressing to death
- Re-challenge cases in which a hypersensitivity pattern recurred faster and more severely on second exposure
This is not a "theoretical" or "weak signal" safety concern. It is a well-documented, internationally recognized, mechanistically explained adverse-event profile that has generated regulatory actions in multiple jurisdictions. The injury cannot be predicted in advance for any one person, which is why the case literature puts so much weight on liver testing and on recognizing the warning signs.
The counterargument that He Shou Wu has been used safely for centuries in TCM is partially valid but does not eliminate the modern concern. Traditional use was typically within an integrated TCM diagnostic framework, with experienced practitioner oversight, time-limited courses, the processed root preparation, and combination with other herbs that may have modulated toxicity. Modern over-the-counter Western use is often standalone, indefinite, with poorly characterized raw-root preparations, and without liver function test (LFT) monitoring — precisely the conditions that maximize the chance of an unrecognized adverse event progressing to a serious outcome.
Lei 2015 Systematic Review — 450 Cases in 76 Articles
The most comprehensive single source on He Shou Wu hepatotoxicity is Lei et al. (2015) in Evidence-Based Complementary and Alternative Medicine. The systematic review searched six medical databases up to June 2014, identified 923 database records, and included 76 articles (59 case reports and 17 case series) from the Chinese-language and English-language literature, covering a total of 450 cases of Polygonum multiflorum-associated liver damage. Key findings:
- Age distribution: in the 72 single-patient case reports, ages ranged from 5 to 78, median 36.5; 6 of the 72 (8.3%) were under 18
- Sex distribution: of the 450 cases, 224 (49.8%) were male and 226 (50.2%) female — the authors found no sex pattern. Graying hair and hair loss were the most common reason for taking the herb (43 of the 72 case reports, 59.7%)
- Time to onset: in the case reports, 1 to 240 days from starting the herb, median 30 days — symptoms mostly appeared “a month or so” after starting
- Clinical pattern: in the 221 case-series patients whose injury type was reported, 59.7% had hepatocellular injury (predominant alanine aminotransferase/aspartate aminotransferase (AST) elevation), 15.4% cholestatic (predominant alkaline phosphatase / bilirubin elevation), and 24.9% mixed
- Peak alanine aminotransferase: commonly 10 to 50× the upper limit of normal (ULN), with extreme values above 100× ULN in the most severe cases
- Outcomes: 441 of the 450 patients (98%) recovered or had improved liver function after stopping He Shou Wu products and receiving supportive care; 2 received liver transplants and 7 died
- Preparation type: cases involved raw and processed He Shou Wu decoction pieces and many Chinese patent medicines containing the herb; in two case series the ratio of processed to raw He Shou Wu was 5:13 and 25:11. The authors wrote that all He Shou Wu products may lead to liver damage regardless of processing
- Dose: only 25 case reports gave a daily dose (1 to 100 g, median 15 g); 14 of them exceeded the Chinese Pharmacopoeia (2010) maximum of 12 g a day (3–6 g for raw root, 6–12 g for processed root). The authors concluded that the liver damage shows a “dose-time-toxicity” relationship and that most cases were “much related to long-term and overdose of drugs”
- Repeated episodes: 23 of the 72 case reports (31.9%) described liver damage with He Shou Wu more than once, and 3 (4.2%) had a family history of He Shou Wu-related hepatitis
- Concomitant medications: often present but the causal pattern (improvement on herb discontinuation, recurrence on re-challenge in several cases) implicated He Shou Wu as the primary agent in most cases
Subsequent post-2015 publications have continued to add cases and case series, including a 2017 Korean case series, a 2019 European reporting database review, and several Chinese tertiary-hospital DILI registry analyses. Lei's 2015 count alone reached 450 published cases, and the true incidence in unselected populations is unknown but presumably higher (most adverse events are not published).
The Human Leukocyte Antigen-B*35:01 Genetic Susceptibility (Li 2019)
The most important advance in understanding He Shou Wu hepatotoxicity was the 2019 Hepatology paper by Li et al. titled "HLA-B*35:01 Allele Is a Potential Biomarker for Predicting Polygonum multiflorum-Induced Liver Injury in Humans." The study sequenced the human leukocyte antigen (HLA) region of 11 Chinese patients with Polygonum multiflorum DILI and compared them with a Han Chinese reference database, then checked the result in a separate group of 15 patients with Polygonum multiflorum DILI, 33 patients with liver injury from other drugs and 99 population controls, and finally followed 72 outpatients taking the herb for 4 weeks.
Key findings:
- The human leukocyte antigen-B*35:01 allele was found in 45.4% of the 11 first patients, compared with 2.7% of the Han Chinese population (odds ratio 30.4); in the replication and combined analyses the odds ratios were 86.5 compared with other DILI and 143.9 compared with population controls
- In the prospective arm, 6 of the 72 outpatients developed a symptom-free rise in liver enzymes (transaminases) within the 4 weeks: 37.5% of HLA-B*35:01 carriers compared with 4.7% of non-carriers (relative risk 8.0)
- The population frequency of human leukocyte antigen-B*35:01 was 2.7% in the Han Chinese reference data; in the US Drug-Induced Liver Injury Network it was found in 11% of population controls (Hoofnagle 2021)
- The human leukocyte antigen-B*35:01 association implicates a human leukocyte antigen class I-restricted CD8+ T-cell response — an immune-allergic / hypersensitivity mechanism rather than a direct dose-dependent metabolic toxicity
- This is mechanistically analogous to other well-characterized human leukocyte antigen-mediated DILI: abacavir / human leukocyte antigen-B*57:01, flucloxacillin / human leukocyte antigen-B*57:01, ximelagatran / DRB1*0701, amoxicillin-clavulanate / DRB1*15:01, several Chinese herb DILI associations
- The Li finding has been replicated in subsequent Chinese cohorts and extended to investigations of other allele associations
The clinical implication is profound: Polygonum multiflorum hepatotoxicity is a pharmacogenetic adverse drug reaction. It is, in principle, partially predictable through pre-prescription human leukocyte antigen typing — the same approach that has dramatically reduced abacavir hypersensitivity through mandatory human leukocyte antigen-B*57:01 screening. As of 2026, pre-treatment human leukocyte antigen-B*35:01 typing is not routinely available or routinely recommended for He Shou Wu in any jurisdiction, but it is a plausible future direction for risk stratification in integrative medicine practice, particularly in Han Chinese populations.
Without routine human leukocyte antigen typing, nobody can know in advance whether they carry the susceptibility allele. A negative family history of herb-induced injury does not eliminate the risk because most individuals with the susceptibility allele have never been challenged with the herb.
Mechanism — Immune-Allergic Idiosyncratic DILI
The current best-characterized mechanism for He Shou Wu hepatotoxicity is an immune-allergic, human leukocyte antigen-class I-restricted, CD8+ T-cell-mediated attack on hepatocytes. One proposed sequence, modeled on other immune-mediated drug injuries and not yet shown in people:
- Hepatic metabolism of a parent compound — an anthraquinone (most likely emodin or a closely related oxidized metabolite, or possibly an oxidized stilbene) is processed by hepatic CYP450 enzymes (CYP3A4, CYP1A2) to a reactive intermediate.
- Hapten formation — the reactive intermediate covalently binds to hepatocyte proteins, forming a neo-antigen (hapten-protein conjugate).
- Human leukocyte antigen presentation — in human leukocyte antigen-B*35:01 carriers, the haptenated peptide is presented by the human leukocyte antigen-B*35:01 molecule on hepatocyte and antigen-presenting cell surfaces.
- T-cell activation — CD8+ cytotoxic T cells recognize the haptenated peptide as foreign and mount an immune response.
- Hepatocyte killing — CD8+ T cells release perforin and granzymes, inducing hepatocyte apoptosis. The resulting hepatocellular injury releases more haptenated antigen and amplifies the response.
- Clinical presentation — alanine aminotransferase and aspartate aminotransferase rise (hepatocellular pattern), often with eosinophilia (a hallmark of immune-allergic DILI), and progression depends on the magnitude of the immune response and the timeliness of herb discontinuation.
A 2024 study in mice (Zeng et al.) points to a different first step. It found that emodin, the main component of the herb, binds to HLA-B*35:01–peptide complexes non-covalently — directly, without first being turned into a reactive metabolite that sticks to proteins (the “pharmacological interaction,” or p-i, mechanism). Mice carrying the human HLA-B*35:01 gene developed immune liver injury from emodin, with raised liver enzymes, inflammatory cells and more CD8+ T cells in the liver, while ordinary mice did not. This is animal evidence; whether the same happens in people is not yet known.
This mechanism explains several otherwise puzzling features of He Shou Wu DILI:
- Idiosyncratic onset: the time to clinically apparent injury (median 30 days, range 1 to 240 days in Lei 2015) is consistent with the time required for clonal expansion of antigen-specific T cells
- Non-linear dose relationship: immune activation is largely binary; once a sufficient threshold of haptenated antigen accumulates to activate a clonally expanded T-cell population, the injury occurs regardless of further dose — although the Lei 2015 review also found a “dose-time-toxicity” pattern in the case reports that gave doses
- Re-challenge faster and more severe: memory T cells respond more rapidly on re-exposure — this is a hallmark of immune-allergic DILI and a feature documented in several He Shou Wu re-challenge cases
- Eosinophilia, rash, fever (the hypersensitivity triad): documented in a subset of He Shou Wu DILI cases, consistent with an immune-allergic mechanism rather than direct toxicity
- Human leukocyte antigen association: a defining feature of immune-mediated DILI
The alternative mechanism — direct dose-dependent anthraquinone hepatotoxicity — almost certainly also contributes some component of injury risk, particularly with raw root and very large or prolonged doses. Emodin has been shown in cell culture and animal models to induce hepatocyte mitochondrial dysfunction and oxidative damage. But the predominant clinical pattern in humans appears to be the idiosyncratic immune mechanism.
Processed (Zhi Shou Wu) vs Raw (Sheng Shou Wu)
The distinction between processed (zhi shou wu, 制首乌) and raw (sheng shou wu, 生首乌) is the main quality difference between He Shou Wu products. The two preparations have meaningfully different anthraquinone content, different traditional indications, and different reported hepatotoxicity rates.
Traditional processing (jiu zhi, 酒制): Raw root is sliced and repeatedly steamed and sun-dried with black soybean (hei dou) broth, in the classical method over nine cycles ("jiu zheng jiu shai" — "nine steamings and nine sun-dryings"). The black bean broth provides both heat-transfer medium and chemical interaction; the prolonged elevated-temperature exposure (typically 100°C for hours per cycle) hydrolyzes and partially destroys the free anthraquinones, conjugates some to glycosides and other less-bioavailable forms, and substantially reduces the laxative and (presumably) hepatotoxic profile.
Comparative analytical chemistry from Wang et al. (2018) and other studies:
- Free emodin in raw root: typically 0.05 to 0.3% by dry weight
- Free emodin in properly processed root: typically 0.01 to 0.08% (roughly 60 to 80% reduction)
- Combined emodin (glycoside + free): less dramatically reduced — processing converts forms more than it destroys the underlying anthraquinone backbone
- Tetrahydroxystilbene glucoside (TSG) content: relatively preserved or modestly reduced by processing
- Tannin content: increased in processing through condensation and polymerization — gives processed root its characteristic darker color
Processing is described as lowering the free-anthraquinone content, but the case data show it does not remove the liver risk. In two case series gathered by Lei 2015, the ratio of processed to raw He Shou Wu among the patients was 5:13 in one and 25:11 in the other — processed root accounted for most cases in the second series. A 2014 series of 18 otherwise healthy Chinese patients with liver injury from Polygonum multiflorum alone (Dong et al.; median age 42, onset 1 to 120 days, median 27) concluded that the products can be associated with liver injury “regardless of herbal processing.”
The traditional and modern clinical observations:
- Raw root is indicated traditionally for constipation, parasites, malaria, and as an external poultice. The laxative effect is significant at therapeutic doses. Internal use over weeks to months is generally not what classical TCM prescribes.
- Processed root is indicated for the hair, kidney essence, longevity, and tonifying applications that have made the herb famous in the West. The laxative effect is much reduced.
- Hepatotoxicity case literature includes both raw and processed root, with processed root the majority in at least one case series. The human leukocyte antigen-B*35:01 mechanism is allele-driven, so even reduced-anthraquinone preparations can trigger injury in susceptible individuals.
For buyers, the difference shows up in the label: processed (zhi shou wu) root carries a lower free-anthraquinone load than raw root, while bulk powders, unlabeled capsules, and "raw He Shou Wu" products from unregulated suppliers add the unpredictable risks of quality variation and adulteration. Even with properly processed root, the idiosyncratic risk remains.
International Regulatory Actions
Multiple national regulatory bodies have issued safety advisories or restrictions on Polygonum multiflorum:
- UK MHRA (Medicines and Healthcare products Regulatory Agency): issued multiple Drug Safety Updates on Polygonum multiflorum / Fo-Ti hepatotoxicity. The agency has received Yellow Card reports of serious liver injury and recommends consumers avoid products containing the herb unless under specialist supervision.
- Australian TGA (Therapeutic Goods Administration): classified Polygonum multiflorum as a substance requiring liver-injury warning labeling on listed therapeutic products and has issued safety alerts. Products must carry warnings about hepatotoxicity and the need to seek medical attention for symptoms.
- Health Canada: issued advisories on products containing Polygonum multiflorum and required hepatotoxicity warnings on Natural Health Product licenses.
- European Medicines Agency (EMA) and individual European national agencies: several countries (notably France, Germany, the Netherlands) have issued pharmacovigilance reports on Polygonum multiflorum DILI through national reporting systems and EudraVigilance.
- China NMPA (National Medical Products Administration): the Chinese regulator — the country of origin of the herb — has issued multiple safety circulars and updated the Chinese Pharmacopoeia entry for Polygonum multiflorum with hepatotoxicity warnings and dose restrictions. This is notable: the Chinese regulator, with the deepest cultural and clinical experience with the herb, considers the modern hepatotoxicity signal serious enough to warrant warnings.
- US FDA: has not issued a specific safety alert on Polygonum multiflorum in the dietary supplement category but has communicated concerns through MedWatch reports and adverse event databases. The herb is legal to sell as a dietary supplement in the US without specific warning requirements.
- WHO: the WHO monograph on Polygonum multiflorum includes hepatotoxicity in the safety profile.
The pattern across these regulatory actions: the more aggressively the agency reviews post-market pharmacovigilance, the more concern it has expressed about Polygonum multiflorum. The relative permissiveness of the US dietary supplement regulatory framework is not evidence that the herb is safe.
Situations of Greatest Concern in the Research
The case literature and the herb's safety profile raise the greatest concern in the following situations, whatever the indication or processing form:
- Pre-existing chronic liver disease — chronic hepatitis B or C, non-alcoholic fatty liver disease (NAFLD), non-alcoholic steatohepatitis (NASH), alcoholic liver disease, autoimmune hepatitis, primary biliary cholangitis, primary sclerosing cholangitis, cirrhosis of any etiology
- Elevated baseline liver enzymes — alanine aminotransferase, aspartate aminotransferase, or alkaline phosphatase above the upper limit of normal at baseline
- Active alcohol use disorder — alcohol potentiates the hepatotoxic injury and complicates diagnosis
- Recent prior He Shou Wu injury — after an alanine aminotransferase/aspartate aminotransferase elevation, jaundice, or hypersensitivity reaction to He Shou Wu, re-exposure carries the risk of a faster, more severe immune (memory) response; Lei 2015 found repeated episodes in 31.9% of case reports.
- Pregnancy and lactation — the safety profile in pregnancy is undefined; anthraquinones cross placenta; insufficient evidence of safety
- Children under 18 — insufficient safety data; the case literature includes pediatric DILI
- Known human leukocyte antigen-B*35:01 carriers — where this information is available (e.g., from prior pharmacogenomic testing for other indications); in the 2019 prospective study, carriers had a liver-enzyme rise eight times as often as non-carriers (37.5% vs 4.7%)
- Acute hepatitis or any acute liver injury — including the recovery phase from any other liver injury
- Liver transplant recipients — immunosuppression and graft sensitivity make any liver-toxic exposure a particular danger to the transplanted liver
Situations That Add to the Risk
Other situations add to the risk or make an injury harder to recognize early:
- Concomitant hepatotoxic medications — particularly methotrexate, isoniazid, valproate, ketoconazole, amiodarone, statins, acetaminophen at >3 g/day. Each of these carries its own liver-injury warning, so combined use adds to the load on the liver.
- Concomitant other herbal hepatotoxins — kava (especially the European banned-and-reinstated controversy), comfrey (pyrrolizidine alkaloids), greater celandine, pennyroyal, chaparral, germander, mistletoe (oral), green tea extract at supraphysiologic doses. Green tea extract injury is tied to the same gene variant: in the US Drug-Induced Liver Injury Network, HLA-B*35:01 was found in 72% of 40 green-tea liver-injury cases, compared with 12% of drug cases and 11% of population controls, and 3 of the 40 (8%) needed a liver transplant (Hoofnagle 2021)
- Hereditary or acquired CYP450 polymorphisms — particularly CYP3A4 and CYP1A2 ultra-rapid or poor metabolizer status may affect risk; not routinely tested. A 2014 study of 43 Chinese patients with Polygonum multiflorum liver injury (Ma et al.) found the CYP1A2*1C variant in 46.5% of patients compared with 27.9% of healthy controls
- Inflammatory bowel disease with active flare — intestinal absorption may be altered; baseline liver function is more variable; many inflammatory bowel disease (IBD) medications are themselves hepatotoxic
- Chronic kidney disease stage 4 or 5 — altered drug clearance affects all herbal interventions
- Recent gastric bypass or other malabsorption — altered absorption may produce unpredictable systemic exposure
- Elderly >75 years — reduced hepatic reserve, polypharmacy, and reduced ability to tolerate any DILI event
- Diabetes with poor glycemic control — non-alcoholic fatty liver disease is highly prevalent in this population, often subclinical
- Frequent nonsteroidal anti-inflammatory drug (NSAID) use — baseline hepatic stress is elevated
In all of the above circumstances the safety margin is narrower and an injury is harder to recognize early. Other herbs traditionally used for similar purposes have their own pages: Astragalus for general tonification, Schisandra, traditionally used for the liver, and Ginseng for energy and stress.
How Liver Tests Track He Shou Wu Injury
Because the injury is often silent at first, liver blood tests are the only way to catch it early. A testing schedule built around the published onset times looks like this:
- Baseline (before starting): alanine aminotransferase, aspartate aminotransferase, alkaline phosphatase (ALP), gamma-glutamyl transferase (GGT), total bilirubin, direct bilirubin, albumin, prothrombin time / international normalized ratio (INR), complete blood count with eosinophil percentage. Hepatitis B surface antigen and hepatitis C antibody if not previously screened. Abdominal ultrasound shows underlying liver disease, non-alcoholic fatty liver disease, or fatty infiltration. Without a starting value, a later rise cannot be dated to the herb.
- Week 4 follow-up: alanine aminotransferase, aspartate aminotransferase, alkaline phosphatase, total bilirubin. Earlier injury is documented — onset ranged from 1 day in Lei 2015 and from 1 to 120 days (median 27) in Dong 2014.
- Week 12 follow-up: Same panel. The median time-to-onset was about 30 days in Lei 2015, with cases up to 240 days, so a week-12 test catches much of the later onset.
- Every 3 months thereafter while in use: Same panel. Some authors describe monthly tests during the first 6 months, given the time-to-onset distribution.
- At any new symptom: a reason for LFTs regardless of schedule
- After discontinuation: LFTs 4 weeks after stopping show whether values have returned to normal (or document a subclinical injury that improves with discontinuation)
Interpretation thresholds (Hy's Law and the Council for International Organizations of Medical Sciences (CIOMS) criteria for DILI):
- Alanine aminotransferase or aspartate aminotransferase >3× ULN: an early injury signal; many DILI cases first manifest with alanine aminotransferase in this range, and a repeat test about a week later shows whether it is rising.
- Alanine aminotransferase or aspartate aminotransferase >5× ULN: a marked injury signal.
- Alanine aminotransferase or aspartate aminotransferase >10× ULN: serious DILI is presumed at this level.
- Total bilirubin >2× ULN with concurrent alanine aminotransferase/aspartate aminotransferase elevation: "Hy's Law" criterion — predicts approximately 10% case fatality from hepatocellular DILI; hospitals treat this pattern as urgent.
- Eosinophilia >500/µL with LFT abnormality: supports the immune-allergic mechanism, reinforces the He Shou Wu causality, and predicts response to discontinuation
- Coagulopathy (international normalized ratio >1.5): a sign of acute liver failure, which hospitals treat as urgent
This schedule is more intensive than what most users currently do. It reflects the documented severity of the injury when it occurs and the lack of warning symptoms before LFT abnormality.
Warning Signs of Liver Injury
Any of the following during use is a sign of liver injury that hospitals treat as urgent. In the Lei 2015 review, 98% of patients recovered or improved after the herb was stopped:
- Jaundice — yellow discoloration of the sclera (whites of the eyes), skin, or mucous membranes. The sclera shows it earlier than skin in light-skinned individuals; the soft palate is a useful examination site in darker-skinned individuals.
- Dark urine — the color of strong tea or cola, due to conjugated bilirubin excretion
- Light or clay-colored stool — reflects reduced bilirubin excretion into bile (cholestatic pattern)
- Right upper quadrant pain or tenderness — under the right rib cage, often dull and persistent
- Unexplained fatigue or malaise — particularly when persistent and out of proportion to other circumstances
- Nausea or loss of appetite — new-onset, particularly with any of the above
- Pruritus (itching) — particularly generalized itching without rash, often the earliest symptom of cholestatic injury
- Rash with fever — the immune-allergic hypersensitivity triad
- Easy bruising or unusual bleeding — reflects coagulopathy, a sign of advanced injury
- Confusion, somnolence, asterixis (flapping tremor) — signs of hepatic encephalopathy, a sign of acute liver failure; this is a medical emergency
The asymptomatic phase of significant liver injury can last weeks — in the 2019 prospective study, every liver-enzyme rise found was without symptoms — so waiting for symptoms misses this phase. By the time jaundice appears, alanine aminotransferase is often already in the hundreds and meaningful injury has occurred. In the case literature, stopping the herb is what was followed by recovery, and stopping at the symptom-free alanine aminotransferase-elevation phase comes before any progression to acute liver failure.
What Happens When Liver Injury Is Suspected
- Stopping the herb. Stopping is the main treatment for herb-induced liver injury; in the published cases recovery followed discontinuation, and herb-induced liver injury care involves no tapering or "finishing the bottle."
- Other medicines and supplements. Acetaminophen, nonsteroidal anti-inflammatory drugs (NSAIDs) at high dose, and other herbal supplements add to the load on an injured liver; stopping a prescribed medicine suddenly carries its own risks, which is why the prescribing clinician is part of that decision.
- Fluids and alcohol. Alcohol adds its own liver injury and makes liver-test results harder to read.
- Urgent liver tests. Same-day or next-day labs. The panel used for suspected herb-induced liver injury includes alanine aminotransferase, aspartate aminotransferase, alkaline phosphatase, gamma-glutamyl transferase, total bilirubin, direct bilirubin, international normalized ratio, and complete blood count with eosinophil percentage.
- The supplement bottle. The bottle itself (not just the name) lets the manufacturer, batch, and ingredient list be documented, along with a list of all other medications and supplements.
- Naming the herb. He Shou Wu is also sold as Polygonum multiflorum or Fo-Ti. Many primary care clinicians are not familiar with its liver-injury literature or its human leukocyte antigen-B*35:01 link, so the herb's names, the weeks of use, and the dose help them place the injury.
- Reporting the adverse event. In the US, reports go to U.S. Food and Drug Administration (FDA) MedWatch; in the UK, to the Yellow Card system; in Australia, to the Therapeutic Goods Administration (TGA). These reports accumulate the pharmacovigilance data that drives future safety actions.
- Severe injury (severe RUQ pain, deepening jaundice, vomiting, confusion, bleeding, signs of encephalopathy) is a medical emergency that hospitals treat as urgent. Acute liver failure progresses over hours to days and may require transfer to a liver transplant center.
- Re-exposure. After a He Shou Wu injury, re-exposure is more dangerous than the first exposure because of immune memory; Lei 2015 found repeated episodes in 31.9% of case reports.
- Follow-up monitoring. LFTs are repeated until values return to normal, then again at 6 months to check for chronic injury. Severe cases may be followed yearly.
The good news in the case literature: the great majority of individuals who stop He Shou Wu at the first sign of injury recover fully over weeks to months, often with no residual liver disease. Early recognition is everything. The cases that progress to acute liver failure are predominantly those who continued the herb despite developing symptoms, often because they did not connect their symptoms to the supplement they were taking.
Key Research Papers
- Lei X et al. (2015). Liver Damage Associated with Polygonum multiflorum Thunb.: A Systematic Review of Case Reports and Case Series. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 25648693
- Li C, Rao T, Chen X, et al. (2019). HLA-B*35:01 Allele Is a Potential Biomarker for Predicting Polygonum multiflorum-Induced Liver Injury in Humans. Hepatology 70(1):346-357. — PubMed PMID: 30985007
- Lin L et al. (2015). Traditional usages, botany, phytochemistry, pharmacology and toxicology of Polygonum multiflorum: A review. Journal of Ethnopharmacology. — PubMed PMID: 25449462
- Jung KA et al. (2011). Drug-induced liver injury: twenty-five cases of acute hepatitis following ingestion of Polygonum multiflorum Thunb. Gut and Liver. — PubMed PMID: 22195249
- Dong H, Slain D, Cheng J, Ma W, Liang W (2014). Eighteen cases of liver injury following ingestion of Polygonum multiflorum. Complementary Therapies in Medicine 22(1):70-4. — PubMed PMID: 24559819
- Ma KF, Zhang XG, Jia HY (2014). CYP1A2 polymorphism in Chinese patients with acute liver injury induced by Polygonum multiflorum. Genetics and Molecular Research 13(3):5637-43. — PubMed PMID: 25117321
- Park GJ, Mann SP, Ngu MC (2001). Acute hepatitis induced by Shou-Wu-Pian, a herbal product derived from Polygonum multiflorum. Journal of Gastroenterology and Hepatology 16(1):115-7. — PubMed PMID: 11206309
- Navarro VJ, Barnhart H, Bonkovsky HL, et al. (2014). Liver injury from herbals and dietary supplements in the U.S. Drug-Induced Liver Injury Network. Hepatology 60(4):1399-408. — PubMed PMID: 25043597
- Björnsson ES (2015). Drug-induced liver injury: an overview over the most critical compounds. Archives of Toxicology 89(3):327-34. — PubMed PMID: 25618544
- Hoofnagle JH, Bonkovsky HL, Phillips EJ, et al. (2021). HLA-B*35:01 and Green Tea-Induced Liver Injury. Hepatology 73(6):2484-2493. — PubMed PMID: 32892374
- Zeng X, Li C, Liu Y, et al. (2024). HLA-B*35:01-mediated activation of emodin-specific T cells contributes to Polygonum multiflorum thunb. -induced liver injury in mice. Journal of Ethnopharmacology 334:118523. — PubMed PMID: 38969149
PubMed Topic Searches
Connections
- All Herbs
- He Shou Wu Overview
- He Shou Wu Benefits Hub
- Hair and Anti-Aging
- Cognitive Function
- Longevity and Cardiovascular
- Hepatitis
- Schisandra (Hepatoprotective)
- Milk Thistle (Silymarin)
- Astragalus (Safer Tonic Alternative)
- Ginseng (Safer Tonic Alternative)
- Rhubarb (Related Anthraquinone)
- Liver Detox
- Liver Function Tests
- Pharmaceutical Toxicity
- History