Lentils for Soluble Fiber and Cholesterol
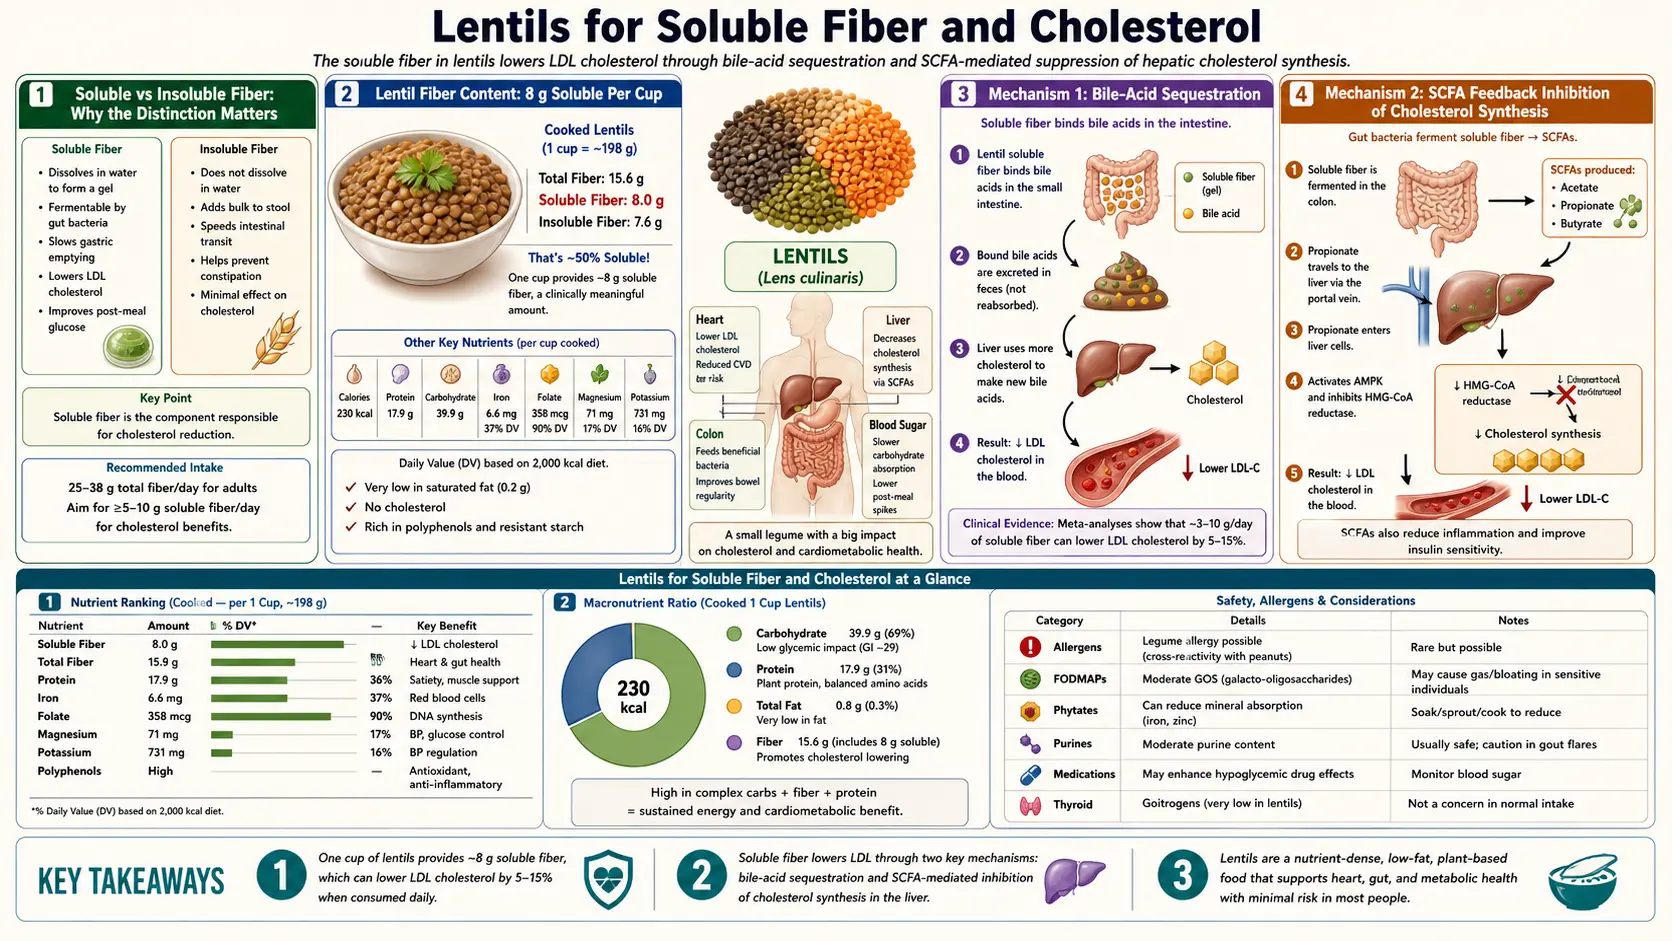
In 1984, James Anderson and colleagues at the University of Kentucky published a landmark trial in the American Journal of Clinical Nutrition showing that hypercholesterolemic men eating one cup of beans or oat bran daily for three weeks experienced approximately 19% reductions in total cholesterol and 24% reductions in low-density lipoprotein (LDL) cholesterol. The Anderson data, replicated across dozens of subsequent trials, established legume soluble fiber as a legitimate, evidence-based dietary intervention for elevated low-density lipoprotein — producing effect sizes that approach the lower end of low-intensity statin therapy without the side-effect profile. A single cup of cooked lentils delivers about 8 grams of soluble fiber, the dose at which the proposed low-density lipoprotein-lowering mechanisms (bile-acid binding and short-chain fatty acid feedback inhibition of hepatic cholesterol synthesis) are thought to engage. This page walks through the mechanism, the major trial data including the 2014 CMAJ meta-analysis by Ha et al. that established a 5% low-density lipoprotein reduction per daily 130 g pulse serving, and the Portfolio Diet framework that stacks lentils with nuts, plant sterols, and viscous fibers for additive effect.
Table of Contents
- Soluble vs Insoluble Fiber: Why the Distinction Matters
- Lentil Fiber Content: 8 g Soluble Per Cup
- Mechanism 1: Bile-Acid Sequestration
- Mechanism 2: Short-Chain Fatty Acid Feedback Inhibition of Cholesterol Synthesis
- The 1984 Anderson Trial and Its Successors
- The 2014 Ha Meta-Analysis: 5% Low-Density Lipoprotein Per Cup
- The Portfolio Diet — Stacking Interventions
- Lentils and Statins Across Cardiovascular Risk Levels
- Secondary Benefits: Blood Pressure and Glycemic Control
- One Cup Per Day in Practice
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Soluble vs Insoluble Fiber: Why the Distinction Matters
Dietary fiber is the umbrella term for plant-derived carbohydrate that resists digestion by human pancreatic and small-intestinal enzymes. It splits into two functionally distinct subcategories with different physiologic effects:
- Soluble fiber dissolves in water to form a viscous gel inside the gut lumen. The viscosity slows gastric emptying, delays glucose absorption (the basis for the low glycemic index of lentils), traps bile acids and dietary cholesterol (the basis for low-density lipoprotein reduction), and provides fermentable substrate for colonic bacteria. Major dietary sources: oat beta-glucan, psyllium husk, legume gum (the major form in lentils, chickpeas, and beans), apple and citrus pectin.
- Insoluble fiber does not dissolve. It acts as bulk-forming, transit-accelerating material that increases stool weight and reduces colonic transit time. It is the dominant fiber type in wheat bran, vegetable cell walls, and the seed coats of grains and legumes. It does not engage the bile-acid sequestration pathway and does not measurably affect low-density lipoprotein cholesterol.
This distinction is why "high-fiber" foods are not all equivalent for cholesterol-lowering. A bowl of wheat-bran cereal (high in insoluble wheat-bran fiber) does not have the low-density lipoprotein effect of a bowl of oatmeal (high in soluble beta-glucan). Lentils sit toward the soluble-fiber-rich end of the spectrum — roughly half of their 16 g total fiber per cup is soluble, making them comparable to oats and rolled barley on a per-serving basis.
The size of the soluble-fiber effect is modest. A 1999 meta-analysis of 67 controlled trials found that each gram of soluble fiber (in the range of 2-10 g/day) lowered low-density lipoprotein by only about 0.057 mmol/L. Its example: 3 g of soluble fiber from oats (3 servings of oatmeal, 28 g each) lowered total and low-density lipoprotein cholesterol by about 0.13 mmol/L, an effect the authors called small within the practical range of intake. Fiber from oats, psyllium and pectin worked about equally, and triglycerides and high-density lipoprotein did not change. For legumes as whole foods, a 2011 meta-analysis of 10 trials (268 people) found that diets rich in non-soy legumes lowered total cholesterol by 11.8 mg/dL and low-density lipoprotein by 8.0 mg/dL compared with control diets.
Lentil Fiber Content: 8 g Soluble Per Cup
U.S. Department of Agriculture (USDA) FoodData Central lists 15.6 g total dietary fiber per 198 g cooked cup of lentils. Detailed compositional studies (Tosh et al. and Quinones et al.) place the soluble fraction at approximately 50% of total fiber, or about 7.5-8 g of soluble fiber per cup. The dominant soluble fibers in lentils are:
- Legume gum / galactomannans — storage polysaccharides in the endosperm of legume seeds, accounting for most of the viscosity-forming behavior
- Pectin — concentrated in the seed coat and cotyledon cell walls
- Beta-glucans — present in smaller quantities than in oats but still meaningful
- Resistant starch (Type 2 and Type 3) — not technically classified as fiber by all definitions but functionally fermentable and behaving similarly to soluble fiber
For comparison, the soluble fiber content per typical serving of common foods:
- Lentils, 1 cup cooked: ~8 g soluble fiber
- Black beans, 1 cup cooked: ~5 g
- Chickpeas, 1 cup cooked: ~5 g
- Oatmeal, 1 cup cooked: ~2 g (beta-glucan)
- Psyllium husk, 1 tbsp: ~4 g
- Apple with skin, 1 medium: ~1 g
- Brussels sprouts, 1 cup cooked: ~2 g
- Avocado, 1 medium: ~2 g
The US Institute of Medicine adequate intake recommendation is 14 g of total fiber per 1,000 kcal consumed — approximately 25 g/day for women and 38 g/day for men. The average American consumes only 15-17 g/day. A single cup of lentils closes about 50% of the average American fiber deficit and supplies roughly the entire daily soluble fiber target.
Mechanism 1: Bile-Acid Sequestration
The liver synthesizes approximately 400-800 mg of new bile acids per day from cholesterol, conjugates them with glycine or taurine, and secretes them via the bile duct into the small intestine where they emulsify dietary fats for absorption. Under normal circumstances, the body recycles bile acids efficiently — approximately 95% are reabsorbed in the terminal ileum and returned to the liver via the portal circulation (the enterohepatic circulation), and only about 5% are lost in feces each day.
Soluble fiber is proposed to bind bile acids in the small intestine and keep them from being reabsorbed in the ileum. The 1984 Anderson trial (below) found this for oat bran, which raised the amount of bile acids lost in stool — but the bean diet had the opposite effect and lowered stool bile-acid loss, even though it lowered cholesterol just as much. Where binding does happen, the bile-acid-fiber complex passes into the colon and is excreted. The liver then has to draw down its cholesterol pool to synthesize replacement bile acids — and a substantial fraction of that drawdown comes from low-density lipoprotein particles, which the liver removes from circulation via low-density lipoprotein receptor upregulation. The end result is measurable reductions in plasma low-density lipoprotein cholesterol.
This is the same mechanism used by pharmaceutical bile-acid sequestrants like cholestyramine, colestipol, and colesevelam — first-generation cholesterol-lowering drugs that bind bile acids in the gut. Oat fiber appears to work along the same lines at a lower magnitude (drugs are dose-titrated to bind nearly all luminal bile acids; food fiber binds only a fraction). For beans, the Anderson stool data did not show this effect, so the bile-acid route has not been demonstrated for legumes.
The downstream effects:
- Hepatic CYP7A1 (cholesterol-7-alpha-hydroxylase, the rate-limiting enzyme for bile acid synthesis) is upregulated
- Hepatic HMG-CoA reductase (the rate-limiting enzyme for cholesterol synthesis, also the statin target) is partially upregulated to replenish cholesterol used for new bile acids
- Hepatic low-density lipoprotein receptor expression increases to capture circulating low-density lipoprotein for cholesterol input
- Plasma low-density lipoprotein cholesterol decreases as a net result
Mechanism 2: Short-Chain Fatty Acid Feedback Inhibition of Cholesterol Synthesis
The second mechanism operates downstream in the colon. Soluble fiber that escapes binding to bile acids passes into the colon where it is fermented by anaerobic bacteria, producing short-chain fatty acids (SCFAs) — primarily acetate, propionate, and butyrate, in a typical ratio of roughly 60:20:20.
Propionate, in particular, is absorbed across the colonic epithelium, enters the portal circulation, and reaches the liver where it inhibits cholesterol synthesis at the HMG-CoA reductase step — the same enzyme targeted by statin drugs. Animal models and some human metabolic studies suggest that hepatic propionate exposure can reduce de novo cholesterol synthesis by 10-30%.
Butyrate, while a less effective cholesterol-synthesis inhibitor, is the dominant energy substrate for colonocytes (the cells lining the colon) and the molecular signal maintaining tight junction integrity in the colonic epithelium. Butyrate signaling through GPR43 and HDAC inhibition has anti-inflammatory effects on the gut-immune axis that may indirectly affect cardiovascular risk through reduced systemic inflammation.
Acetate, the most abundant short-chain fatty acid (SCFA) produced, is largely used for de novo lipogenesis in adipose tissue and as an energy substrate in muscle, with smaller effects on hepatic lipid metabolism.
The two proposed mechanisms — bile-acid binding (shown for oat bran, not for beans) plus short-chain fatty acid-mediated cholesterol synthesis inhibition — are offered as explanations for the low-density lipoprotein reductions seen in fiber and legume trials. The two mechanisms are partially independent, which is why combining lentils with oats (different short-chain fatty acid profile, different bile-acid binding affinity) produces incrementally additive rather than redundant effects.
The 1984 Anderson Trial and Its Successors
James Anderson's 1984 paper in the American Journal of Clinical Nutrition (Hypocholesterolemic effects of oat-bran or bean intake for hypercholesterolemic men) was the landmark demonstration that food-level legume intake produced cholesterol-lowering effects comparable to early-generation drugs. The design:
- 20 hypercholesterolemic men (mean baseline low-density lipoprotein 240 mg/dL)
- Randomized to receive 100 g/day of oat bran (about 1 cup cooked) or 100 g/day of pinto/navy beans (about 1.2 cups cooked) for 21 days
- A control diet first, then random allocation to either the oat-bran or the bean diet (parallel groups, not a crossover), all on a metabolic ward
- Outcomes: total cholesterol, low-density lipoprotein, high-density lipoprotein (HDL), triglycerides at baseline and 21 days
Results: total cholesterol fell by approximately 19% in the bean group and 19% in the oat-bran group. Low-density lipoprotein fell by 24% in the bean group and 23% in the oat-bran group. High-density lipoprotein was preserved. Triglycerides did not change significantly. Oat bran raised stool weight by 43% and raised the bile acids lost in stool; beans did not raise stool weight and lowered stool bile-acid loss. The effect sizes were comparable to early statin trials of the era (lovastatin 20 mg produced approximately 25-30% low-density lipoprotein reduction).
Subsequent trials with lentils specifically (rather than the mixed-bean Anderson protocol) have produced effect sizes typically in the 5-15% low-density lipoprotein reduction range, smaller than the original Anderson numbers because:
- The Anderson population had higher baseline cholesterol (greater reduction potential)
- Modern populations have already incorporated more fiber and unsaturated fat into their backgrounds, leaving less room for additional effect
- Lentils have somewhat lower soluble fiber per gram than pinto beans (about 8 g vs 11 g per cup)
The robust modern estimate from the 2014 Ha meta-analysis in CMAJ is approximately 5% low-density lipoprotein reduction from one daily 130 g serving of pulses (lentils, beans, chickpeas, dry peas) over 6 weeks. This is a clinically meaningful, evidence-grade effect.
The 2014 Ha Meta-Analysis: 5% Low-Density Lipoprotein Per Cup
The Ha et al. 2014 meta-analysis published in the Canadian Medical Association Journal (Effect of dietary pulse intake on established therapeutic lipid targets for cardiovascular risk reduction) pooled 26 randomized controlled trials enrolling 1,037 participants. Key findings:
- Median pulse dose was 130 g/day (about 1 cup cooked)
- Median trial duration was 6 weeks
- Pulse consumption reduced low-density lipoprotein cholesterol by approximately 0.17 mmol/L (6.6 mg/dL), corresponding to about a 5% reduction from baseline low-density lipoprotein of approximately 130 mg/dL
- Effects on high-density lipoprotein and triglycerides were small and not statistically significant
- The meta-analysis found no effect on its other two lipid targets, apolipoprotein B and non-high-density-lipoprotein cholesterol; the authors called for longer, higher-quality trials
- Effect was consistent across lentils, beans, chickpeas, and dry peas, with no significant heterogeneity by pulse type
The 5% low-density lipoprotein reduction may sound modest, but applied at the population level it corresponds to a meaningful cardiovascular event reduction. The 2010 Cholesterol Treatment Trialists' Collaboration meta-analysis of 26 statin trials established that each 1.0 mmol/L (38.7 mg/dL) reduction in low-density lipoprotein produced approximately a 22% reduction in major vascular events (rate ratio 0.78), "just over a fifth". A 5% low-density lipoprotein reduction from baseline 130 mg/dL corresponds to about 6.5 mg/dL absolute reduction, equating to roughly a 3.5% relative reduction in major vascular events over 5 years — not by itself transformative, but cumulative when stacked with other dietary changes.
The Portfolio Diet — Stacking Interventions
David Jenkins and colleagues at the University of Toronto developed the Portfolio Diet in the early 2000s as a deliberately stacked dietary protocol combining multiple individually-modest low-density lipoprotein-lowering interventions to produce additively large effects. The four pillars:
- Plant sterols / stanols — about 2 g/day; the Portfolio trials supplied them as plant sterols added to the diet (1.0 g per 1,000 kcal in the 2003 trial). Reduces cholesterol absorption from the gut. Approximately 10% low-density lipoprotein reduction at this dose.
- Soluble fiber — 10 g/day, from oats, barley, psyllium, eggplant, okra, and legumes including lentils. Bile-acid sequestration + short-chain fatty acid feedback. Approximately 5-7% low-density lipoprotein reduction.
- Soy protein — 50 g/day, from soy foods such as fermented tempeh and natto, tofu, soy milk, or soy meat substitutes. Approximately 5% low-density lipoprotein reduction.
- Nuts — 30 g/day (about a small handful), particularly almonds and walnuts. Provides monounsaturated fats, plant sterols, and arginine. Approximately 5% low-density lipoprotein reduction.
In the pivotal 2003 Jenkins JAMA trial, 46 adults with high cholesterol were randomly assigned for 1 month to a diet very low in saturated fat (control), the same diet plus lovastatin 20 mg/day, or the Portfolio diet. Low-density lipoprotein fell 8.0% on the control diet, 30.9% with lovastatin and 28.6% on the Portfolio diet, and the statin and Portfolio results did not differ significantly — comparable to a low-intensity statin. In the longer 2011 JAMA trial, 351 people with high cholesterol received dietary advice for 6 months while choosing their own food (rather than eating supplied meals). Low-density lipoprotein fell 13.8% with intensive Portfolio advice (7 clinic visits) and 13.1% with routine Portfolio advice (2 visits), versus 3.0% on a low-saturated-fat control diet, and the size of the fall tracked how closely people kept to the diet.
Lentils are an attractive addition to the soluble-fiber pillar because they simultaneously provide the soy protein equivalent for those who don't tolerate soy — in effect collapsing two pillars into one food. A typical "lentil-stacked" Portfolio Diet substitution might be a daily cup of lentil soup or lentil-based dal instead of separate tofu and oatmeal courses.
Lentils and Statins Across Cardiovascular Risk Levels
The comparison is not lentils-versus-statins but rather a question of which combination of interventions makes sense at a given baseline cardiovascular risk:
- Low cardiovascular risk (10-year atherosclerotic cardiovascular disease (ASCVD) risk <5%) — lifestyle is generally the main approach at this level. A daily cup of lentils contributes to a Portfolio-style dietary pattern that addresses low-density lipoprotein without medication.
- Borderline risk (5-7.5%) — lifestyle intensification is generally the first step. A daily lentil serving combined with weight loss, exercise, smoking cessation, and stress management can shift this category back below the lifestyle threshold for many patients.
- Intermediate risk (7.5-20%) — the ACC/AHA guidelines recommend considering statin therapy at this level, with shared decision-making between patient and clinician. Lifestyle including lentils remains foundational; statins add an independent 25-50% low-density lipoprotein reduction on top.
- High risk (>20% 10-year risk, or established ASCVD) — high-intensity statin (atorvastatin 40-80 mg or rosuvastatin 20-40 mg) is the standard of care. Lentils remain part of the dietary backbone but are not a statin substitute at this risk level.
- Familial hypercholesterolemia (FH) — baseline low-density lipoprotein above 190 mg/dL even in young patients — lifestyle including lentils is inadequate. Maximum-intensity statins, ezetimibe, and PCSK9 inhibitors are typically required.
For patients who cannot tolerate statins due to myalgia (3-10% of statin users), the food-based portfolio approach including lentils becomes more important by default. For those who tolerate statins, the dietary and pharmacologic approaches are additive rather than competitive.
Secondary Benefits: Blood Pressure and Glycemic Control
Beyond low-density lipoprotein cholesterol, regular lentil intake produces measurable benefits in two adjacent cardiovascular risk factors:
Blood pressure. The 2014 Jayalath et al. meta-analysis of 8 randomized controlled trials (RCTs) (n=554) examining pulse intake and blood pressure found systolic blood pressure reductions of approximately 2.25 mmHg and diastolic reductions of approximately 0.71 mmHg, statistically significant for systolic. The proposed mechanisms: high potassium content (731 mg per cup, more than a banana), magnesium content (71 mg per cup), and fiber-mediated effects on endothelial function. A 2 mmHg systolic reduction is modest individually but at the population level corresponds to about a 6% reduction in stroke mortality and a 4% reduction in coronary heart disease mortality.
Glycemic control. Lentils have a glycemic index of approximately 30 (low; for comparison, white rice is 73, white bread is 75, watermelon is 76). The Jenkins 2012 Archives of Internal Medicine trial randomized 121 type 2 diabetic patients to either a low-glycemic-index diet emphasizing pulses (about 1 cup/day) or a control diet high in wheat fiber from whole-wheat products for 3 months. Hemoglobin A1c (HbA1c) fell by 0.5 percentage points on the legume diet and by 0.3 on the whole-wheat diet, so the legume diet's extra effect was 0.2 points. The legume diet also lowered systolic blood pressure by 4.5 mmHg more than the whole-wheat diet and lowered the calculated coronary heart disease risk score (by 0.8%). The Sievenpiper 2009 Diabetologia meta-analysis of 41 pulse-intake trials confirmed consistent effects on fasting glucose and hemoglobin A1c in both diabetic and non-diabetic populations.
In line with these lipid, blood pressure, and glycemic effects, the 2001 Bazzano analysis of the NHANES I Epidemiologic Follow-up Study (9,632 US adults followed for an average of 19 years) found that eating legumes 4 or more times a week, compared with less than once a week, was linked to a 22% lower risk of coronary heart disease and an 11% lower risk of cardiovascular disease overall.
One Cup Per Day in Practice
The dose at which lentils produce measurable cardiovascular benefit is approximately 1 cup cooked daily (or 130 g, equivalent to about 1/2 cup dry weight). Operationally:
- Daily lentil soup — the simplest implementation. Red lentils + onion + carrot + celery + canned tomato + cumin + lemon juice, simmered 25 minutes. One large bowl meets the daily target.
- Daily dal-and-rice or mujadara at one meal — the traditional Indian / Middle Eastern implementations, well-documented for compliance and acceptability.
- Lentil salad at lunch — cooked French green lentils with olive oil, mustard, parsley, and shallot, kept refrigerated for 3-4 days of grab-and-go lunches.
- Sprouted lentil garnish — raw sprouted lentils added to salads, sandwiches, or stir-fries provides higher mineral bioavailability (see Soaking and Phytates) and approximately equivalent fiber to cooked lentils.
- Lentils in place of red meat at 2-3 dinners per week — lentil bolognese, lentil tacos, lentil shepherd's pie. Each substitution adds about 8 g soluble fiber and removes about 3 g saturated fat, compounding the low-density lipoprotein benefit.
Expected response: 4-8 weeks of a daily cup of lentils in a previously lentil-free diet is expected to lower low-density lipoprotein by roughly 5-10%. A fasting lipid panel at baseline and after about 8 weeks shows the change. When no change appears, the usual explanations are a lower real intake than planned (most non-responders are sub-dose; in the 2011 Portfolio trial the fall tracked adherence) and other dietary components offsetting the gains (saturated fat from cheese, butter, fatty meat blunts the response).
Cautions
- Gas and bloating during adaptation — the raffinose and stachyose oligosaccharides in lentils ferment in the colon and produce gas. People commonly start at 1/4 to 1/3 cup daily and increase over 2-4 weeks. The gut microbiome adapts — populations that habitually eat legumes do not experience the same effect. An alpha-galactosidase enzyme supplement can ease the transition.
- Drug interactions — high fiber intake can reduce absorption of certain medications. Notable: levothyroxine, digoxin, certain antibiotics. Taking these medicines at least 2 hours apart from a high-fiber meal is the spacing commonly used to limit this effect.
- Mineral binding (phytates) — at very high legume intakes (multiple cups per day for extended periods) the phytic acid load can measurably reduce zinc, iron, and calcium absorption. Mitigated by soaking and sprouting; see Soaking and Phytates.
- Vitamin K interaction with warfarin — lentils contain modest vitamin K (~3 mcg per cup, low compared to leafy greens at 500+). Sudden large increases in lentil intake are unlikely to destabilize warfarin international normalized ratio (INR), but consistency is the operative principle — warfarin dosing is set around a steady vitamin K intake.
- Acute kidney injury / advanced chronic kidney disease (CKD) — lentils are moderately high in potassium and phosphorus. One cooked cup carries about 731 mg of potassium (see above). Angiotensin-converting enzyme inhibitors (ACE inhibitors), angiotensin receptor blockers (ARBs) and spironolactone all raise blood potassium, and failing kidneys clear less of it, so in chronic kidney disease stage 4-5 or existing high blood potassium (hyperkalemia) the potassium from lentils adds to a level that is already high.
- Histamine intolerance / mast cell activation syndrome — canned and aged lentil products may contain elevated histamine. Lentils freshly cooked from dry are the lower-histamine form.
Key Research Papers
- Anderson JW, Story L, Sieling B, Chen WJ, Petro MS, Story J (1984). Hypocholesterolemic effects of oat-bran or bean intake for hypercholesterolemic men. American Journal of Clinical Nutrition, 40(6):1146-1155. — PubMed PMID: 6095635
- Ha V et al. (2014). Effect of dietary pulse intake on established therapeutic lipid targets for cardiovascular risk reduction: a systematic review and meta-analysis of randomized controlled trials. CMAJ, 186(8):E252-262. — PubMed PMID: 24710915
- Bazzano LA et al. (2011). Non-soy legume consumption lowers cholesterol levels: a meta-analysis of randomized controlled trials. Nutrition, Metabolism & Cardiovascular Diseases, 21(2):94-103. — PubMed PMID: 19939654
- Jenkins DJ et al. (2003). Effects of a dietary portfolio of cholesterol-lowering foods vs lovastatin on serum lipids and C-reactive protein. JAMA, 290(4):502-510. — PubMed PMID: 12876093
- Jenkins DJ et al. (2011). Effect of a dietary portfolio of cholesterol-lowering foods given at 2 levels of intensity of dietary advice on serum lipids in hyperlipidemia. JAMA, 306(8):831-839. — PubMed PMID: 21862744
- Brown L et al. (1999). Cholesterol-lowering effects of dietary fiber: a meta-analysis. American Journal of Clinical Nutrition, 69(1):30-42. — PubMed PMID: 9925120
- Jayalath VH et al. (2014). Effect of dietary pulses on blood pressure: a systematic review and meta-analysis of controlled feeding trials. American Journal of Hypertension, 27(1):56-64. — PubMed PMID: 24014659
- Sievenpiper JL et al. (2009). Effect of non-oil-seed pulses on glycaemic control: a systematic review and meta-analysis of randomised controlled experimental trials in people with and without diabetes. Diabetologia, 52(8):1479-1495. — PubMed PMID: 19526214
- Jenkins DJ et al. (2012). Effect of legumes as part of a low glycemic index diet on glycemic control and cardiovascular risk factors in type 2 diabetes. Archives of Internal Medicine, 172(21):1653-1660. — PubMed PMID: 23089999
- Bazzano LA et al. (2001). Legume consumption and risk of coronary heart disease in US men and women: NHANES I Epidemiologic Follow-up Study. Archives of Internal Medicine, 161(21):2573-2578. — PubMed PMID: 11718588
- Cholesterol Treatment Trialists' (CTT) Collaboration (2010). Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. Lancet, 376(9753):1670-1681. — PubMed PMID: 21067804
- Hartley L et al. (2016). Dietary fibre for the primary prevention of cardiovascular disease. Cochrane Database of Systematic Reviews. — PubMed PMID: 26758499
PubMed Topic Searches
Connections
- All Food
- Lentils (Main Page)
- Lentils Benefits Hub
- Lentils for Plant Protein and Iron
- Lentils for Folate
- Soaking and Phytates
- Oats (Beta-Glucan)
- Beans
- Chickpeas
- Hypercholesterolemia
- Atherosclerosis
- Hypertension
- Type 2 Diabetes
- Lipid Panel
- Heart Health (Cardiology)
- Magnesium
- Potassium
- History
- Nutrients