Honey as a Cough Suppressant — The Pediatric and Adult Evidence
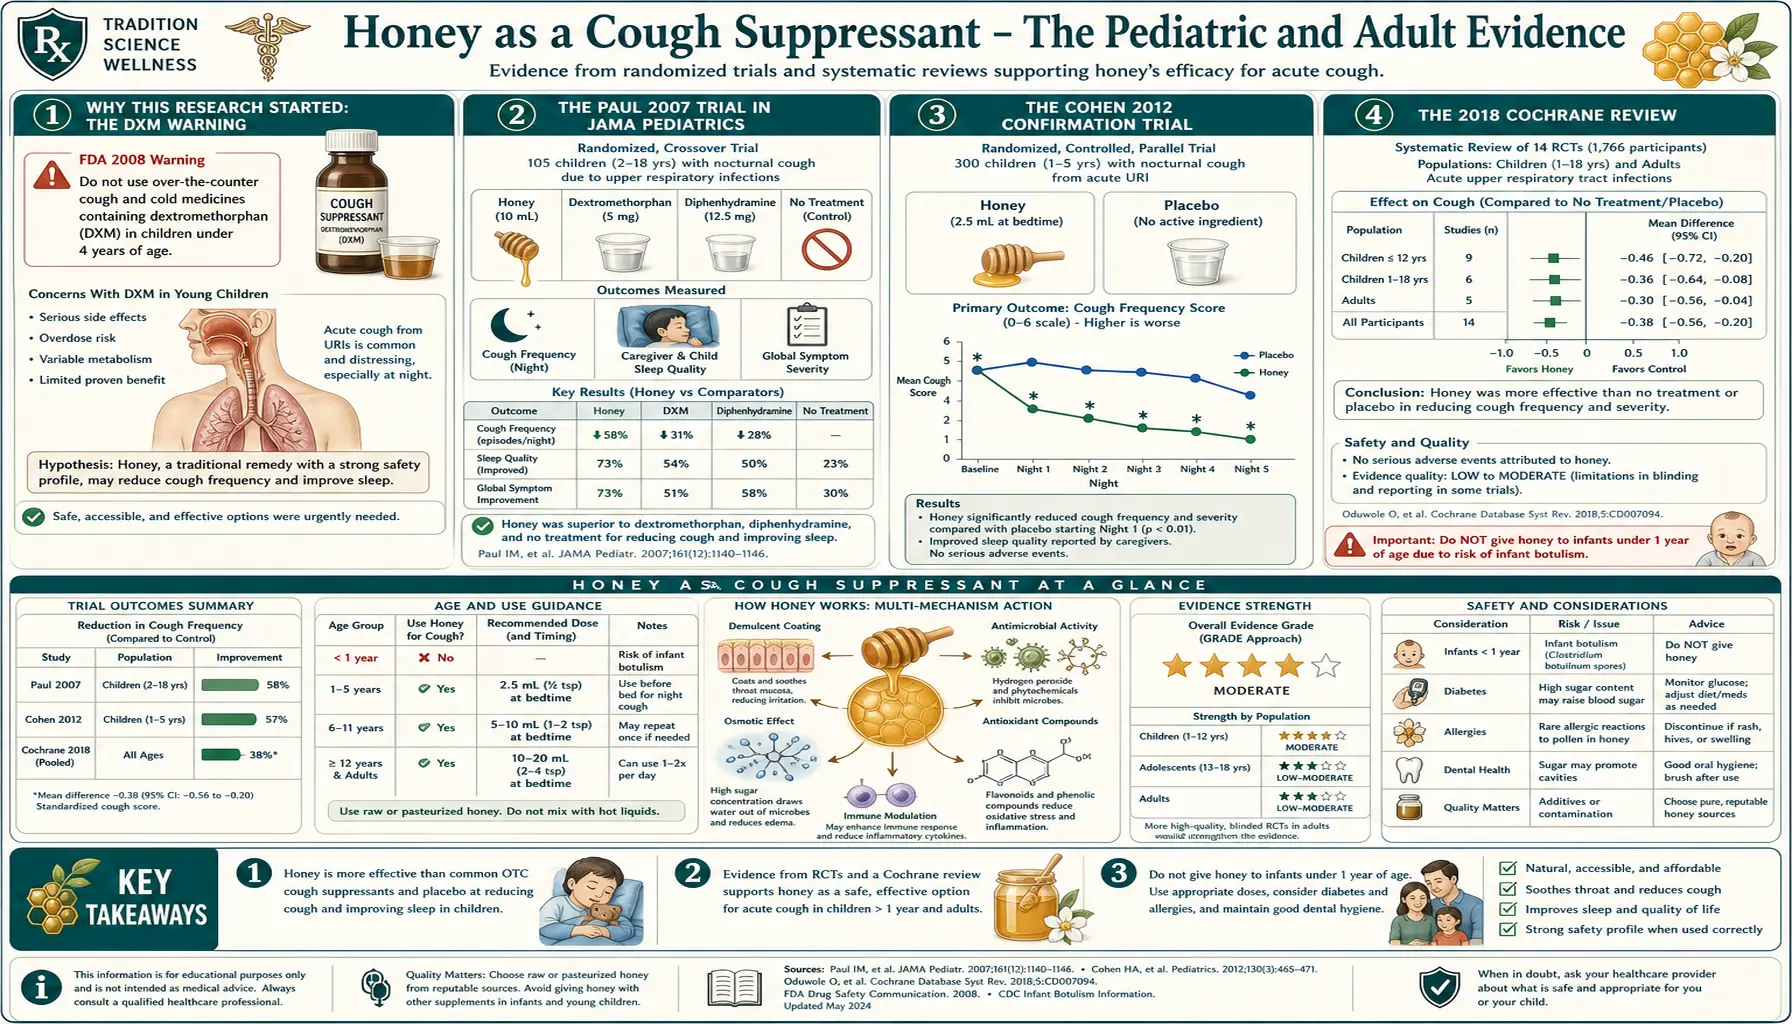
In 2007, Ian Paul and colleagues at Penn State College of Medicine published an unusual trial in JAMA Pediatrics. They randomized 105 children aged 2-18 with upper respiratory infection and nocturnal cough to one of three treatments: a single bedtime dose of buckwheat honey, an age-appropriate dose of dextromethorphan (the active ingredient in most over-the-counter cough syrups), or no treatment. Parents rated honey best of the three. In paired comparisons honey did significantly better than no treatment for cough frequency and the combined symptom score, while honey and dextromethorphan did not differ significantly. The paper appeared two months after a U.S. Food and Drug Administration (FDA) advisory committee recommended against over-the-counter cough and cold medicines for children under six; the World Health Organization had already noted honey as a possible cough treatment in a 2001 report. A 2018 Cochrane review of six pediatric trials confirmed the effect. The evidence in adults is less robust but generally supportive. This page walks through the trial evidence, the proposed mechanisms (demulcent coating, sweet-taste mediated mucus production, mild antimicrobial effect), the buckwheat-honey angle, practical dosing, and the categorical infant contraindication that applies regardless of cough severity.
Table of Contents
- Why This Research Started: The DXM Warning
- The Paul 2007 Trial in JAMA Pediatrics
- The Cohen 2012 Confirmation Trial
- The 2018 Cochrane Review
- Proposed Mechanisms
- Why Buckwheat Honey Specifically
- Practical Dosing
- Adult Cough Evidence
- The Infant Contraindication
- Cautions
- Key Research Papers
- Connections
- Featured Videos
Why This Research Started: The DXM Warning
To understand why a JAMA Pediatrics paper on honey for cough became influential, it helps to know what was happening in pediatric cough-and-cold medicine in the years leading up to it.
For decades, over-the-counter cough and cold medicines for children — combining antitussives (dextromethorphan or DXM), antihistamines (diphenhydramine, brompheniramine), decongestants (pseudoephedrine, phenylephrine), and expectorants (guaifenesin) — were standard pediatric pharmacy products, frequently used by parents and recommended by pediatricians. The accumulated trial evidence for efficacy in children was thin, however, and safety concerns mounted through the 1990s and early 2000s as case reports accumulated of dose-related toxicity (sedation, respiratory depression, cardiac events, and rare fatal overdoses) particularly in infants and toddlers.
In October 2007, the U.S. Food and Drug Administration convened a Nonprescription Drugs Advisory Committee that recommended against the use of over-the-counter cough and cold medicines in children under six years of age. In January 2008 the FDA issued a nationwide Public Health Advisory recommending that over-the-counter cough and cold medicines not be used to treat infants and children under two years of age, because serious and potentially life-threatening side effects can occur. In October 2008 the manufacturers' trade association announced that these products should not be used in children under 4, and manufacturers voluntarily relabeled them: "do not use in children under 4 years of age." The American Academy of Pediatrics went further, recommending against use under 6 years.
This created a clinical vacuum. Parents and pediatricians faced sick children with miserable nighttime cough and no recommended pharmacy intervention. Into this gap, the Paul 2007 trial — published just two months after the FDA advisory committee's recommendation — offered a credible, evidence-based, low-cost alternative. The timing was a major factor in its rapid adoption.
The Paul 2007 Trial in JAMA Pediatrics
The Paul trial (Archives of Pediatrics and Adolescent Medicine, 2007; the journal was later renamed JAMA Pediatrics) was a three-arm randomized controlled trial. Participants were 105 children aged 2-18 with upper respiratory infection, cough symptoms for less than 7 days, and no underlying chronic respiratory disease. They were randomized at the bedtime appointment to one of:
- Buckwheat honey — age-based dose (half-teaspoon for ages 2-5, one teaspoon for ages 6-11, two teaspoons for ages 12+), given 30 minutes before bedtime
- Dextromethorphan — honey-flavored dextromethorphan in age-appropriate dose
- No treatment — control arm received no intervention
The next morning, parents completed a 5-question survey scoring (on 0-6 Likert scales) the previous night's cough frequency, cough severity, bothersome cough impact on the child, impact on parent sleep, and impact on child sleep. Results:
- Honey scored significantly better than no treatment in paired comparisons for cough frequency and the combined symptom score; overall, honey consistently scored best and no treatment worst
- Honey and dextromethorphan did not differ significantly on any measure
- Dextromethorphan vs no treatment showed no statistically significant difference, consistent with the broader literature questioning over-the-counter (OTC) cough syrup efficacy in children
- Honey was well tolerated; mild hyperactivity was reported in 5 honey-treated children (likely sugar-related), no other adverse effects
The trial was funded in part by the National Honey Board, an industry trade group — an important caveat that the authors disclosed. However, the methodology (single-night three-arm randomized comparison) was sound, and the result has been independently replicated.
The Cohen 2012 Confirmation Trial
The most important methodological criticism of the Paul 2007 trial was the lack of placebo. The no-treatment group could not be blinded; parents who got honey for their child knew they were getting active treatment. The Cohen 2012 trial in Pediatrics addressed this by using a syrup-textured placebo (silan date extract) that matched honey for sweetness and viscosity.
Cohen et al. randomized 300 Israeli children aged 1-5 with upper respiratory infection and nocturnal cough to one of four arms:
- Eucalyptus honey
- Citrus honey
- Labiatae (lip-family) honey
- Placebo (silan date extract, matched for sweetness and viscosity)
All four arms received a 10 g (about 2 teaspoon) dose 30 minutes before bedtime. The cough scoring system was the same Likert-scale parent-completed survey from the Paul protocol.
Results: All three honey varieties produced significantly larger improvements than placebo for cough frequency, cough severity, bothersome impact, and child sleep. The three honey varieties did not differ significantly from each other.
Together, the Paul 2007 and Cohen 2012 trials established that:
- Honey is superior to placebo for nocturnal cough in children — ruling out the "sweetness alone" or "viscosity alone" explanation
- Honey and dextromethorphan did not differ significantly in the Paul trial — and dextromethorphan was not better than no treatment on any outcome
- The effect generalizes across multiple honey types (buckwheat, eucalyptus, citrus, labiatae)
The 2018 Cochrane Review
The Oduwole 2018 Cochrane review (PubMed PMID: 29633783) pooled six trials with 899 children with acute cough due to upper respiratory infection. The pooled effect:
- Honey vs no treatment for cough frequency: mean difference -1.05 points on a 7-point scale, favoring honey (moderate-certainty evidence)
- Honey vs diphenhydramine: honey may be better for cough frequency (mean difference -0.57; 1 study, 80 children; low-certainty evidence)
- Honey vs dextromethorphan: may have a similar effect (mean difference -0.07, not statistically significant; low-certainty evidence)
- Honey vs salbutamol: honey probably better for up to three days, with no advantage beyond three days; honey vs bromelin (a pineapple enzyme) mixed with honey: probably little or no difference
- Honey vs placebo: significantly favoring honey (mean difference -1.62 for cough frequency; moderate-certainty evidence)
The Cochrane review concluded that honey probably reduces cough symptoms more than no treatment, diphenhydramine, and placebo, but may make little or no difference compared with dextromethorphan. The certainty of evidence was rated moderate for the honey-vs-no-treatment and honey-vs-placebo comparisons, and low for the comparisons with dextromethorphan and diphenhydramine.
Based on this evidence, the American Academy of Pediatrics, the UK National Institute for Health and Care Excellence (NICE), and equivalent agencies in most developed countries now recommend honey as a first-line treatment for symptomatic relief of acute cough in children over 12 months old. The World Health Organization had noted honey as a possible treatment for cough and cold symptoms earlier, in a 2001 report.
Proposed Mechanisms
No single mechanism fully explains honey's antitussive effect. The proposed contributing mechanisms include:
- Demulcent coating effect — honey is viscous and adheres to the pharyngeal mucosa, providing a physical coating that may reduce irritation of cough-trigger receptors in the upper airway. This is the same proposed mechanism for the older "honey-and-lemon" home remedy.
- Sweet-taste reflex — the strong sweet taste of honey triggers salivation and increased mucus production in the upper airway. The increased airway secretions may dilute irritants and reduce cough sensitivity. There is also some evidence that sweet taste produces a centrally-mediated cough-reflex modulation via the medullary cough center, though this is less well established.
- Mild antimicrobial activity — the four mechanisms of honey antibacterial activity (osmotic, peroxide, low pH, and MGO in Manuka) discussed in the Wound Healing page may reduce bacterial colonization on the pharyngeal mucosa, though most upper-respiratory cough is viral rather than bacterial.
- Anti-inflammatory and antioxidant phenolics — honey's polyphenols, particularly in dark honeys like buckwheat, may produce local mucosal anti-inflammatory effects. Raw honey retains more of these than pasteurized.
- Sleep-quality effect — both Paul and Cohen reported parent-rated sleep improvement, which may be partly independent of objective cough frequency. A demulcent that interrupts even a few coughs in the early sleep period may produce disproportionate benefit for sleep continuity.
Importantly, the mechanism is local and short-lasting. Honey does not provide a systemic antitussive effect like dextromethorphan or codeine. The benefit window is approximately the first 30-60 minutes after dosing — which is why the trials specifically dosed 30 minutes before bedtime to align peak effect with the period of greatest sleep-onset disruption.
Why Buckwheat Honey Specifically
Paul 2007 specifically used buckwheat honey, and it has become the default recommendation in many US pediatric circles. The reasons:
- High phenolic content — buckwheat honey is one of the darkest commercially available honeys (along with manuka, heather, and chestnut). Color in honey roughly tracks total phenolic content; darker honeys have more antioxidant and anti-inflammatory polyphenols. Buckwheat honey's oxygen radical absorbance capacity (ORAC) is typically 5-10 times that of clover honey.
- Strong characteristic taste — buckwheat honey has a robust, molasses-like flavor that produces a strong sweet-taste reflex. Children sometimes don't love the flavor, but it triggers the salivation and mucus-production response well.
- Availability — buckwheat honey is widely available from US producers in Pennsylvania, New York, and the upper Midwest. Cohen 2012 confirmed that other dark honey varieties (eucalyptus, citrus, labiatae) work comparably.
For practical purposes, any dark, unprocessed, raw or minimally-processed honey appears equivalent. Manuka honey works for cough but costs far more, and the MGO content that distinguishes Manuka is mostly irrelevant to the cough mechanism. More on Manuka and its MGO rating.
Practical Dosing
The doses used in the two pediatric trials:
- Ages 2-5 (Paul 2007) — half teaspoon (2.5 mL, approximately 3.5 g) 30 minutes before bedtime
- Ages 1-5 (Cohen 2012) — a single 10 g dose 30 minutes before bedtime
- Ages 6-11 (Paul 2007) — one teaspoon (5 mL, approximately 7 g) 30 minutes before bedtime
- Ages 12-18 (Paul 2007) — two teaspoons (10 mL, approximately 14 g) 30 minutes before bedtime
Neither trial enrolled adults.
The dose can be taken straight from a spoon, in a small amount of warm (not hot) water or chamomile tea, or used to coat the throat directly; stirred into a large cup of very hot tea it is diluted, which weakens the demulcent coating effect.
Most trials studied only a single bedtime dose, so a repeat dose during the night (for example if cough recurs and disrupts sleep at 2 AM) is outside what the trials tested.
Duration of use: the cough of a typical upper respiratory infection lasts about 3-7 days. A cough that persists more than 2 weeks usually has another cause (see Cautions below); honey is not a treatment for chronic cough, post-viral bronchial hyperreactivity, asthma, or any non-self-limiting cough syndrome. See the Cough page for a broader discussion of cough etiologies.
Adult Cough Evidence
The evidence base in adults is much smaller than in children, primarily because the major trials have focused on the pediatric population (where DXM is not recommended and the clinical need for an alternative is greatest). The Abuelgasim 2021 systematic review (PubMed PMID: 32817011) pooled 14 studies of honey for upper respiratory tract infections and found:
- Honey was associated with greater improvement in cough symptoms than usual care in upper respiratory tract infections
- The effect size was smaller than seen in pediatric trials
- Heterogeneity between trials was low for the comparisons with usual care (I² 0% for the combined symptom score and cough frequency, 20% for cough severity); the two-study comparison with placebo was highly heterogeneous (I² 91%) and not statistically significant
The mechanistic plausibility of benefit in adults is the same as in children (demulcent, sweet-taste, mild antimicrobial). The review's authors concluded that honey was superior to usual care for the symptoms of upper respiratory tract infections and “provides a widely available and cheap alternative to antibiotics,” while calling for further high-quality, placebo-controlled trials. Honey does not treat the conditions behind a cough that is severe, lasts beyond 2 weeks, brings up pus-coloured or bloody sputum, comes with fever, or occurs in someone with underlying lung disease; those are covered on the Bronchitis page and the Pneumonia page.
The Infant Contraindication
The single most important caveat for honey-for-cough: the CDC states: “Do not feed honey to a child who is younger than 1 year old” — however severe the cough. The risk of infant botulism (discussed in detail on the Raw vs Pasteurized page) outweighs any potential benefit. This contraindication applies to:
- All honey varieties — clover, buckwheat, wildflower, orange blossom, Manuka, any other
- Both raw and pasteurized honey (pasteurization does not eliminate Clostridium botulinum spores)
- Honey in any preparation — on a spoon, in tea, in cereal, on a pacifier, in baby food
- Comb honey, honey-containing products, and granola, breads, or baked goods sweetened with honey if the infant might mouth a portion
For a cold at any age, the CDC lists these warning signs for medical care: trouble breathing or fast breathing, dehydration, a fever that lasts longer than 4 days, symptoms that last more than 10 days without getting better, and symptoms such as fever or cough that improve and then return or worsen. The signs of infant botulism the CDC lists are constipation, poor feeding, drooping eyelids, pupils that are slow to react to light, a face showing less expression than usual, and a weak cry that sounds different than usual; the CDC calls botulism a medical emergency. Relief measures for an infant's cold include saline nasal drops, humidified air (a humidifier or cool-mist vaporizer), fever relief with acetaminophen (the U.S. infant acetaminophen label gives no dose for babies under 2 years or under 24 lb and says “ask a doctor”; for older children it allows no more than 5 doses in 24 hours), and the patience to wait out the typical 7-10 day course of a viral upper respiratory infection. Honey is ruled out at this age, and the CDC states that over-the-counter cough and cold medicines are not recommended for children younger than 6 years because they can cause serious and sometimes life-threatening side effects.
Cautions
- Under 12 months — absolute contraindication — see above
- Diabetes — honey contains approximately 80% sugar. The single-dose (1-2 teaspoon = 7-14 g) load is small and unlikely to cause significant glycemic issues in well-controlled diabetes, but it counts as carbohydrate, which matters most for people using insulin or sulfonylureas.
- Tooth decay — honey is cariogenic. The bedtime dosing pattern places sugar on tooth surfaces during the sleeping hours, when salivary clearance is minimal. Rinsing the mouth with water after the dose clears some of the sugar, and brushing 20-30 minutes later (after tooth enamel has had time to re-mineralize from the acid exposure) removes the rest.
- Honey allergy — rare but possible. Anaphylaxis to honey has been reported, particularly in individuals with severe bee-venom allergy or with allergy to specific pollens (composite-family pollens in particular). A reaction after a dose points to the honey as the cause; anaphylaxis is a medical emergency.
- Pollen-allergic individuals — raw honey contains pollen and may transiently worsen seasonal allergy symptoms in highly sensitized individuals. Pasteurized or ultra-filtered honey has lower pollen content. The "local honey desensitizes you to local allergens" claim is not well supported; honey contains primarily entomophilous (insect-pollinated) pollens, while seasonal allergic rhinitis is caused primarily by anemophilous (wind-pollinated) pollens that bees do not collect.
- Cough that lasts more than 2 weeks — usually has a cause other than a cold: post-infectious cough, pertussis (whooping cough), asthma, gastroesophageal reflux disease (GERD), ACE-inhibitor cough, post-nasal drip syndrome, or other causes.
- Productive cough with discolored sputum, fever, or shortness of breath — suggests bacterial bronchitis or pneumonia, which honey does not treat; trouble breathing or fast breathing is on the CDC's list of warning signs for medical care.
- Mad honey poisoning — honey from Rhododendron-rich regions of Turkey, Nepal, and certain other areas can contain grayanotoxin. Rare in commercial honey but a real consideration for tourist purchases.
- Drug interactions — no documented oral-honey drug interactions at the small doses used for cough.
Key Research Papers
- Paul IM, Beiler J, McMonagle A, Shaffer ML, Duda L, Berlin CM Jr (2007). Effect of honey, dextromethorphan, and no treatment on nocturnal cough and sleep quality for coughing children and their parents. Archives of Pediatrics & Adolescent Medicine — PubMed PMID: 18056558
- Cohen HA, Rozen J, Kristal H, Laks Y, Berkovitch M, Uziel Y, Kozer E, Pomeranz A, Efrat H (2012). Effect of honey on nocturnal cough and sleep quality: a double-blind, randomized, placebo-controlled study. Pediatrics — PubMed PMID: 22869830
- Oduwole O, Udoh EE, Oyo-Ita A, Meremikwu MM (2018). Honey for acute cough in children. Cochrane Database of Systematic Reviews — PubMed PMID: 29633783
- Shadkam MN, Mozaffari-Khosravi H, Mozayan MR (2010). A comparison of the effect of honey, dextromethorphan, and diphenhydramine on nightly cough and sleep quality in children and their parents. Journal of Alternative and Complementary Medicine — PubMed PMID: 20618098
- Abuelgasim H, Albury C, Lee J (2021). Effectiveness of honey for symptomatic relief in upper respiratory tract infections: a systematic review and meta-analysis. BMJ Evidence-Based Medicine — PubMed PMID: 32817011
- Paul IM (2012). Therapeutic options for acute cough due to upper respiratory infections in children. Lung. PubMed PMID: 21892785
- Goldman RD (2014). Honey for treatment of cough in children. Canadian Family Physician — PubMed PMID: 25642485
- Eccles R (2006). Mechanisms of the placebo effect of sweet cough syrups. Respiratory Physiology & Neurobiology — PubMed PMID: 16326149
- Smith SM, Schroeder K, Fahey T (2014). Over-the-counter (OTC) medications for acute cough in children and adults in community settings. Cochrane Database — PubMed PMID: 25420096
- WHO (2001). Cough and cold remedies for the treatment of acute respiratory infections in young children. PubMed: WHO cough and cold
- Schroeder K, Fahey T (2002). Systematic review of randomised controlled trials of over the counter cough medicines for acute cough in adults. BMJ — Search PubMed
- Ayazi P, Mahyar A, Yousef-Zanjani M, Allami A, Esmailzadehha N, Beyhaghi T (2017). Comparison of the effect of two kinds of Iranian honey and diphenhydramine on nocturnal cough and the sleep quality in coughing children and their parents. PLOS ONE — PubMed PMID: 28103276