⚠ Evidence warning: Clinical trials or other evidence do not support the claim that sustained manuka honey can turn around chronic wounds that antibiotics failed to heal. This page keeps it as a report of what people, websites or other media say.
Honey for Wound Healing — Topical Use, Burns, and Chronic Ulcers
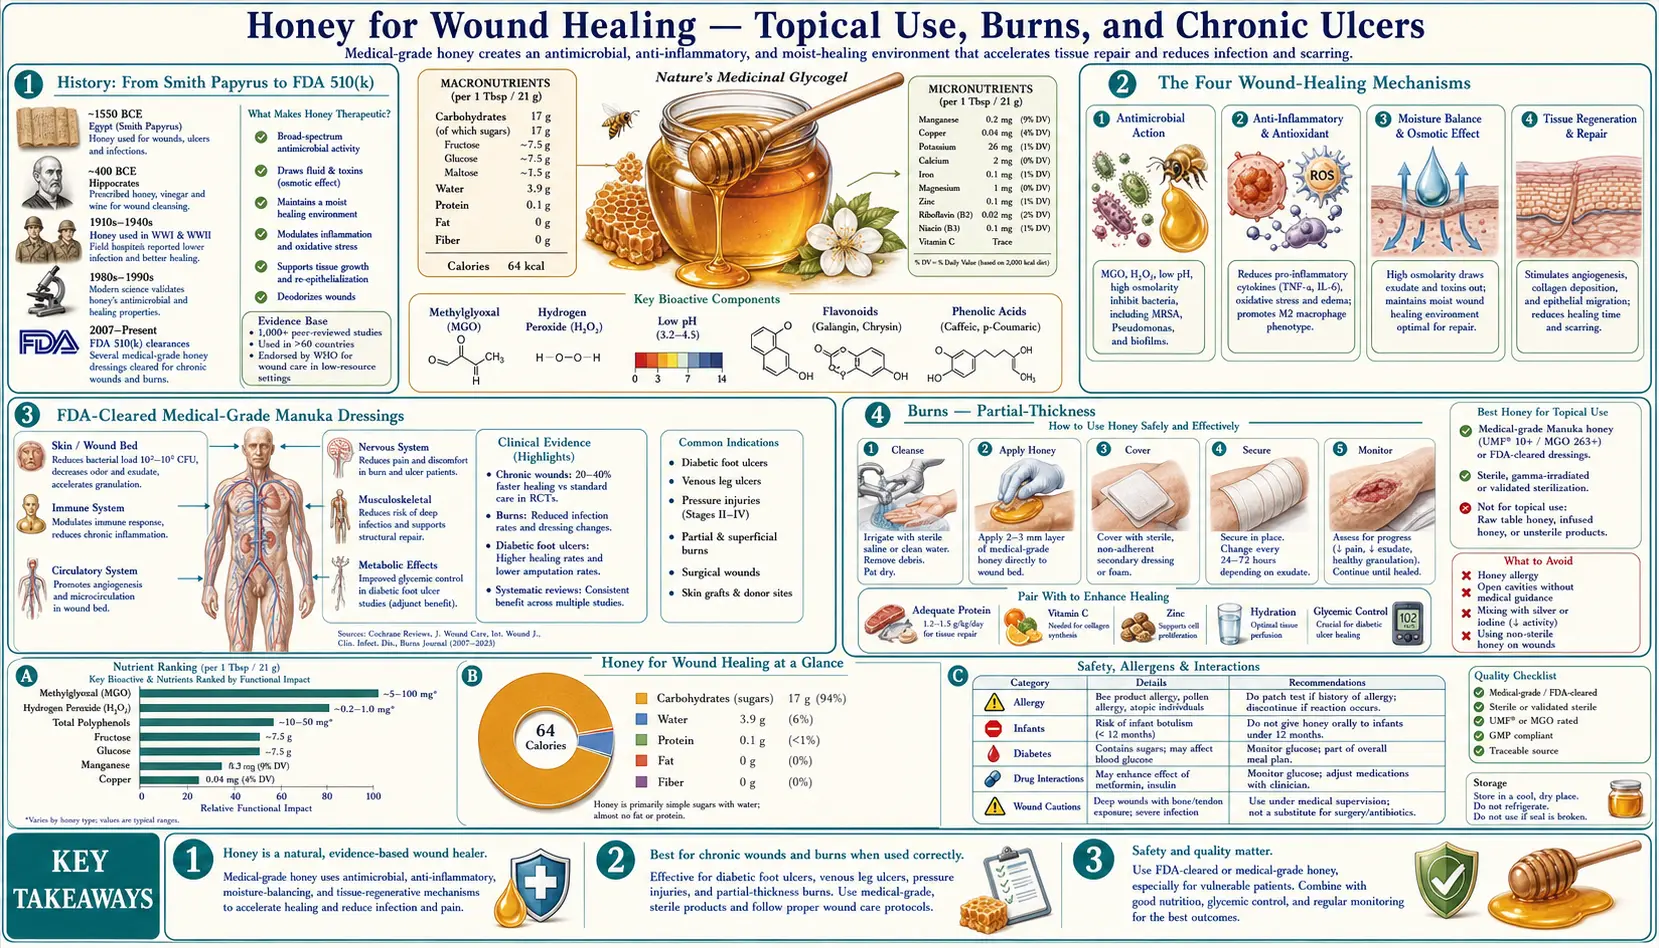
Honey is one of the oldest wound dressings on the planet — the Smith Papyrus (circa 1600 BCE Egypt) describes its use, as do early Greek, Roman, and Arabic medical texts. Modern medicine abandoned honey in the 1940s with the arrival of antibiotics, then rediscovered it in the 1990s and 2000s as antibiotic resistance accelerated and chronic wound rates climbed with diabetes prevalence. Today, U.S. Food and Drug Administration-cleared 510(k) medical-grade Manuka honey dressings are used in hospital wound care in the US, UK, Australia, and across the EU. The Cochrane Collaboration's 2015 systematic review of 26 randomized trials (3,011 participants) found that honey dressings healed partial-thickness burns faster than conventional dressings, and called the effects on chronic wounds unclear. Four mechanisms work together — osmotic dehydration, hydrogen peroxide release, low pH, and (in Manuka) direct methylglyoxal bactericidal kill — and the combination has documented efficacy against methicillin-resistant Staphylococcus aureus (MRSA), Pseudomonas aeruginosa, and other multidrug-resistant pathogens that increasingly defeat conventional antibiotic therapy.
Table of Contents
- History: From Smith Papyrus to U.S. Food and Drug Administration 510(k)
- The Four Wound-Healing Mechanisms
- U.S. Food and Drug Administration-Cleared Medical-Grade Manuka Dressings
- Burns — Partial-Thickness
- Chronic Ulcers (Diabetic Foot, Venous Leg, Pressure)
- Methicillin-Resistant Staphylococcus Aureus, Pseudomonas, and Antibiotic-Resistant Pathogens
- Why Honey Disrupts Biofilms (and Why That Matters)
- Practical Application: Home Use vs Hospital Use
- Where Honey Is Not Used
- How Manuka and Ordinary Honey Compare in the Lab
- Cautions
- Key Research Papers
- Connections
- Featured Videos
History: From Smith Papyrus to U.S. Food and Drug Administration 510(k)
The Edwin Smith Papyrus, an Egyptian surgical text dated to approximately 1600 BCE and itself a copy of an older work, describes 48 cases of traumatic injury and includes detailed instructions for the application of honey to wounds. Honey, lint, and grease are the recurring topical agents. Hippocrates, Aristotle, Galen, and Dioscorides all wrote on the wound-healing properties of honey. Through the medieval period and into the early 20th century, honey-based dressings (often combined with cod liver oil or wax) were standard surgical practice across European, Arabic, Indian, and Chinese medical traditions.
The arrival of penicillin in the 1940s and the broader antibiotic revolution that followed displaced honey almost entirely. By the 1960s, mainstream Western medicine viewed honey-on-wounds as a discredited folk remedy. The exception was Russian and Eastern European surgical practice, where honey continued to see use, and parts of the developing world where antibiotic access was limited.
The modern rediscovery began in New Zealand in the 1980s and 1990s. Peter Molan at the University of Waikato published a long series of papers characterizing the antibacterial activity of New Zealand honeys, leading to the identification of methylglyoxal as the dominant non-peroxide active in Manuka (Mavric et al. 2008) and the development of the UMF rating system. See the Manuka rating page for the chemistry.
The first medical-grade Manuka honey dressing, developed in Australia, was U.S. Food and Drug Administration-cleared as a 510(k) medical device in the United States in 2007 for the management of moderately to heavily exuding wounds including diabetic foot ulcers, leg ulcers, pressure ulcers, and partial-thickness burns. Other products followed in the UK, the Netherlands and elsewhere. By the late 2010s, Manuka honey dressings were in use in chronic wound clinics across the developed world.
The Four Wound-Healing Mechanisms
The therapeutic effect of honey on wounds emerges from four overlapping mechanisms that act simultaneously. Understanding all four explains why different honeys produce different effects, why pasteurized honey is partly inactive, and why the medical-grade products work even after gamma irradiation.
- Osmotic dehydration of bacteria — honey has water activity (aw) below 0.6, well under the 0.85 threshold most bacteria require for growth. When honey is applied to a wound, the steep osmotic gradient draws water out of bacterial cells and out of the wound bed, simultaneously dehydrating contaminating bacteria and producing the moist (but not wet) environment that supports keratinocyte migration and tissue healing. This mechanism is present in any unadulterated honey, raw or pasteurized.
- Hydrogen peroxide generation — bee-derived glucose oxidase (GOx), suspended inactive in concentrated honey, becomes active when honey is diluted by wound exudate. GOx oxidizes glucose to gluconic acid and hydrogen peroxide. The peroxide is generated slowly, at low concentration (around 1 mmol/L), and continuously — achieving sustained bactericidal activity without the tissue toxicity of pharmacy-grade 3% (~880 mmol/L) hydrogen peroxide. This mechanism is destroyed by pasteurization: GOx is heat-labile. It is also the reason Manuka medical-grade products do not rely on this mechanism — gamma irradiation used to sterilize hospital product also reduces GOx activity, but Manuka's heat- and irradiation-stable MGO carries the load.
- Low pH — honey is acidic (pH 3.2-4.5). Applied to a wound, it acidifies the wound bed. This inhibits bacterial protease activity, releases oxygen from hemoglobin (improving local tissue oxygenation), and shifts the wound milieu toward conditions favorable to fibroblast and keratinocyte function. The pH effect is heat-stable and present in pasteurized honey.
- Methylglyoxal (MGO) direct kill — Manuka only — the methylglyoxal that distinguishes Manuka from other honeys produces a fourth mechanism: direct alkylation of bacterial proteins and DNA. At Manuka concentrations of 100+ mg/kg MGO and above, this mechanism is bactericidal against essentially all clinically important wound pathogens, including those resistant to most antibiotics. MGO is heat-stable and gamma-irradiation-stable, which is what enables manufacture of sterile medical-grade Manuka dressings.
Beyond the four direct antimicrobial mechanisms, honey also produces secondary wound-healing effects that are increasingly well-documented: stimulation of keratinocyte and fibroblast proliferation, autolytic debridement (the osmotic gradient pulls necrotic tissue away from the wound bed), reduction of wound odor (by reducing the bacterial production of ammonia and short-chain fatty acids), and reduction of edema and inflammation.
U.S. Food and Drug Administration-Cleared Medical-Grade Manuka Dressings
Medical-grade Manuka honey differs from food-grade Manuka in three important ways:
- Gamma irradiation — food-grade honey can contain Clostridium botulinum spores (the infant-botulism risk). Medical-grade Manuka for wound application is gamma-irradiated (typically 25 kGy) to eliminate spores. This is critical for application to deep wounds or wounds in patients with compromised gut motility.
- Standardized MGO concentration — medical-grade product is tested and labeled to a specific MGO level, typically equivalent to UMF 18+ or MGO 700+ for premium hospital products.
- Pharmaceutical packaging — sterile single-use packets, impregnated dressings (gauze, alginate, hydrogel matrix), gels in sterile tubes. The presentation matches existing wound-care workflow.
The main kinds of commercially available products:
- US-cleared dressing lines — the original U.S. Food and Drug Administration-cleared product type. Available as paste, gel, alginate dressing, calcium alginate, hydrocolloid, and impregnated foam, and used in US hospital chronic-wound clinics.
- UK products — 100% sterile Manuka honey in a tube and as an impregnated tulle dressing, used in UK National Health Service (NHS) wound care.
- European products — distributed across the EU.
- Various national-formulary products — Australia, New Zealand, and several other countries have domestic Manuka medical-device products.
All of these products are intended for use under standard wound-care protocols, typically by a wound-care nurse or wound-care physician, applied at dressing changes every 1-3 days depending on exudate volume.
Burns — Partial-Thickness
Burns are the application with the most consistent clinical evidence for honey. The 2015 Cochrane review (Jull et al.) covered 26 trials with 3,011 participants across all wound types. For partial-thickness burns, high-quality evidence from 2 trials (992 people) found honey dressings healed burns an average of 4.68 days faster than conventional treatment (polyurethane film, paraffin gauze, soframycin gauze, sterile linen, or leaving the burn exposed). Compared with silver sulfadiazine, very low-quality evidence from 4 trials (332 people) favored honey by 5.12 days, while high-quality evidence from 6 trials (462 people) found no difference in healing within 6 weeks (risk ratio 1.00), with fewer side effects on honey. In one trial of 50 people, early excision and grafting healed burns 13.6 days faster than honey followed by grafting as needed. A separate 2017 review of 9 randomized trials against silver sulfadiazine found honey about 5.76 days faster (95% confidence interval −8.14 to −3.39) on moderate-quality evidence. The classic Indian study by Subrahmanyam (1991) compared honey with silver sulfadiazine gauze in 104 people with superficial burns: 91% vs 7% of wounds were sterile within 7 days, healthy new tissue appeared at 7.4 vs 13.4 days, and 87% vs 10% healed within 15 days, with less scarring reported on honey.
The mechanism explanation is straightforward: partial-thickness burns expose a large surface area, are heavily exudative, and are at high risk of bacterial colonization that delays healing or progresses to deep infection. Honey's broad-spectrum antimicrobial activity prevents the colonization, the osmotic effect absorbs exudate without sticking to the wound bed, and the moist environment supports keratinocyte migration from the wound edges and from preserved epidermal islands in the burn bed.
Practical considerations for partial-thickness burns:
- First-degree burns (sunburn, erythema only) do not need honey or any other dressing
- Superficial partial-thickness burns (blistering, painful, blanching) are where honey is most used — medical-grade Manuka with a non-adherent dressing, changed every 2-3 days
- Deep partial-thickness and full-thickness burns require surgical evaluation and are typically managed with skin grafts; honey may be used as an adjunct but not as monotherapy
- Any burn larger than the patient's palm, on the face/hands/genitals, or with signs of infection is the kind of burn hospitals treat as needing a clinician's evaluation
For more on burns generally, see the Burns page.
Chronic Ulcers (Diabetic Foot, Venous Leg, Pressure)
Chronic ulcers are the largest market for medical-grade Manuka. They share three problematic features: they are colonized or infected with biofilm-forming bacteria, they fail to progress through normal wound-healing phases, and they often co-occur in patients with diabetes, peripheral vascular disease, or immobility. Conventional treatments (silver dressings, antimicrobial alginates, negative-pressure wound therapy) are effective but expensive and do not always work.
What the trials show, by type of wound:
- Diabetic foot ulcers — the Cochrane review calls the effect unclear (2 trials, 93 people, low-quality evidence). In one randomized trial of 63 patients, ulcers healed in 31 vs 43 days on Manuka dressings and 78% vs 35.5% became sterile in the first week, while the share of ulcers healed did not differ significantly (97% vs 90%). Infection matters here because diabetic foot infections are the leading cause of non-traumatic lower-extremity amputation. See the Diabetes page for context.
- Venous leg ulcers — the HALT (Honey as Adjuvant Leg Ulcer Therapy) trial in New Zealand was the largest randomized controlled trial (n=368) of Manuka for venous leg ulcers. Healing at 12 weeks did not differ significantly: 55.6% with Manuka and 49.7% with usual care (P=0.258). Manuka dressings came with more adverse events and probably higher cost, and other outcomes did not differ. In a separate small trial of venous leg ulcers, MRSA (methicillin-resistant Staphylococcus aureus) was cleared from 70% of affected wounds (7 of 10) with manuka honey and 16% (1 of 6) with hydrogel at 4 weeks; the numbers are very small and this was a lab outcome, not healing. The evidence summary in the UK guideline on leg ulcer infection (NICE NG152) reports a Manuka dressing as not significantly different from standard care for healing and infection, and its recommendations do not mention honey.
- Pressure ulcers (bedsores) — smaller trials suggest faster healing with Manuka than with hydrocolloid or saline-soaked gauze. The one the Cochrane review counts is a trial of 40 people, honey against saline soaks (risk ratio 1.41, 95% confidence interval 1.05 to 1.90), rated very low quality. The osmotic debridement effect is particularly valuable for stage 2-3 pressure ulcers with necrotic slough.
- Post-surgical wound dehiscence — case series support Manuka for surgical wounds that have re-opened, particularly when contaminated.
What is not known: the Cochrane review found it difficult to draw overall conclusions because patients and comparisons varied and most evidence was low quality. Outside partial-thickness burns and infected post-operative wounds, it says the evidence does not form a robust basis for decision making.
The typical regimen: Manuka dressing applied at every standard dressing change (1-3 days), continued until the wound has filled with granulation tissue and shrunk to closure. Cost per dressing is several US dollars — expensive compared to saline gauze but cheaper than long courses of systemic antibiotics or hospital admission for infection.
Methicillin-Resistant Staphylococcus Aureus, Pseudomonas, and Antibiotic-Resistant Pathogens
One of the strongest arguments for honey in modern wound care is its activity against pathogens that defeat most conventional antibiotics:
- Methicillin-resistant Staphylococcus aureus — in the Cooper et al. 2002 lab paper, 18 strains from infected wounds were stopped from growing at concentrations below 10% (v/v) of both manuka honey and ordinary pasture honey. That test measures growth inhibition, not complete kill. In a 2008 lab study, 6 community-acquired strains were cleared to none detectable within 24 hours by Northern Irish and French honeys, none of them manuka. Later papers report that clinical isolates tested remain susceptible to Manuka honey. See the methicillin-resistant Staphylococcus aureus page.
- Pseudomonas aeruginosa — one of the most problematic gram-negative wound pathogens, especially in burns and chronic ulcers. The Cooper 2002 paper tested 17 burn-derived Pseudomonas strains: manuka and pasture honey both stopped growth at under 10%. The Roberts 2015 paper showed Manuka reduces Pseudomonas motility, an important virulence factor. See the Pseudomonas page.
- Vancomycin-resistant enterococci — in-vitro activity demonstrated.
- Extended-spectrum beta-lactamase-producing Escherichia coli — in-vitro activity demonstrated, including against carbapenem-resistant strains.
- Acinetobacter baumannii — an emerging burn/intensive care unit (ICU) pathogen with frequent multidrug resistance. Manuka shows in-vitro activity, with limited clinical data so far.
- Mycobacteria — in-vitro activity against M. tuberculosis, M. abscessus, and atypical mycobacteria has been demonstrated, but clinical use is exploratory.
The key feature is that extensive in-vitro work has failed to produce stable Manuka-resistant mutants of clinically important pathogens. The proposed reason: MGO acts through multiple non-specific protein and DNA targets simultaneously, leaving no single target for resistance mutations to address. This is unlike most antibiotics, which target a single enzyme or pathway and accumulate resistance with use.
Why Honey Disrupts Biofilms (and Why That Matters)
Biofilms are bacterial communities encased in a self-produced extracellular polymeric matrix. Within a biofilm, bacterial metabolic activity is reduced, antibiotic penetration is poor, and the community as a whole is up to 1,000-fold less susceptible to antibiotics than the same bacteria in planktonic (free-swimming) form. Biofilms are the primary reason chronic wounds become and stay chronic — ordinary antibiotic courses do not penetrate the matrix to kill the embedded bacteria, and as soon as the antibiotic is withdrawn, the biofilm regrows.
Honey, and especially Manuka honey, has documented biofilm-disrupting activity in the lab. The Maddocks 2012 lab paper showed manuka honey permeating 24-hour-old Streptococcus pyogenes biofilms, causing significant cell death and breaking cells away from the biofilm, though biofilms needed higher concentrations than free-floating bacteria. The proposed mechanisms include osmotic disruption of the matrix, direct MGO penetration through the matrix, and methylglyoxal-induced downregulation of biofilm-formation gene expression.
Practitioners report that a chronic wound managed for months with systemic antibiotics with no resolution can sometimes be turned around by sustained Manuka honey topical application, on the idea that it addresses the biofilm component that the systemic antibiotics could not reach. The biofilm papers above are lab studies.
Practical Application: Home Use vs Hospital Use
The home routine people describe for minor wounds, abrasions, small superficial burns, and skin irritations:
- The wound is cleaned with saline or clean water
- A thin layer of MGO 400+ Manuka honey (between UMF 10+ and UMF 15+ on the UMF table) goes on the wound surface
- A non-adherent dressing (non-stick gauze pad, hydrocolloid, or similar) covers it
- The dressing is changed every 24-48 hours, with honey reapplied as needed
- This continues until the wound is closed and healed
- Expanding redness, warmth, increasing pain, fever, or purulent discharge are signs of infection that hospitals treat as urgent; a wound that does not progress within 1-2 weeks is also outside what home care handles
Wounds usually managed by professionals (chronic ulcers, deep wounds, burns larger than a palm, infected wounds, wounds in patients with diabetes or compromised immunity):
- Wound-care clinics evaluate these
- Medical-grade Manuka products are used in clinics and are gamma-irradiated to eliminate C. botulinum spore risk
- Application is by a wound-care nurse following an individualized care plan
- Insurance coverage is generally available for medical-grade honey dressings under wound-care benefits
For minor wounds, people use food-grade Manuka. Wounds in immunocompromised patients, deep wounds, and any wound that breaches the skin into deeper tissue are where medical-grade (gamma-irradiated, sterile) honey is the form used, because food-grade honey can carry Clostridium botulinum spores. See the Dermatology section for related skin conditions.
Where Honey Is Not Used
- Deep penetrating wounds — honey is not packed into deep cavity wounds that communicate with body cavities (e.g. abdominal, thoracic) without surgical evaluation
- Internal application — honey's uses are topical and oral; injecting it, instilling it into the bladder or peritoneum, or using it as eye drops requires specific medical-device clearance for that application
- Patients with documented honey allergy or bee-venom anaphylaxis
- Infants and toddlers under 12 months — honey on skin abrasions raises a concern in this age group; food-grade honey can release spores into the environment, and infants can ingest topical honey through hand-mouth contact
- Wounds with active heavy bleeding — honey is not a hemostatic agent; bleeding is controlled first by standard means
- Necrotic eschar — honey can soften and debride eschar over time, but it is not a substitute for sharp surgical debridement when that is indicated
How Manuka and Ordinary Honey Compare in the Lab
Studies testing both side by side found manuka and ordinary pasture honey stopped the growth of MRSA (18 strains) and Pseudomonas aeruginosa (17 strains) at similar strengths, under 10%. In the MRSA study, artificial honey, a plain sugar solution, needed at least three times the strength to do the same, so sugar alone does not explain the effect. These are lab results and do not show which honey heals wounds better in people. A 2016 review of manuka research notes that therapeutic honey commands a premium price and that the honey industry is actively promoting research on it; one of that review's authors works for a honey company.
Cautions
- Infant botulism — topical application — food-grade honey applied to the skin of an infant under 12 months poses risk because the infant can ingest honey through hand-mouth contact or mouthing of the dressing. Medical-grade gamma-irradiated Manuka under clinician direction is the only form described for this age group.
- Transient burning or stinging — some patients report a brief stinging sensation at application, lasting 5-30 minutes. This is attributed to the osmotic effect on exposed nerve endings and the low pH. It resolves with continued use and is not a sign of harm.
- Increased exudate volume initially — the osmotic effect can transiently increase wound exudate as fluid is drawn from the wound bed. Dressing absorbency is matched to this, and dressings are checked and changed more often in the first 24-48 hours of honey therapy.
- Honey allergy — rare. Contact dermatitis from topical honey has been reported, including in patients with no oral honey allergy. A rash at the dressing site is the sign of this reaction.
- Glycemic effect from absorption — topically applied honey on small wounds does not produce systemic glycemic effects. Large-area application (e.g. extensive burns) in diabetic patients may produce measurable glucose absorption, and blood sugar is monitored in that setting.
- Adverse events in the largest trial — in the HALT trial of 368 people with venous leg ulcers, adverse events were more common with honey dressings than usual care (relative risk 1.3, 95% confidence interval 1.1 to 1.6).
- Drug interactions — no documented topical honey drug interactions. Concurrent systemic antibiotic therapy is not contraindicated and may be synergistic.
- Cost — medical-grade Manuka dressings are expensive. They are most cost-effective for chronic wounds where the alternative is months of failed conventional therapy or progression to amputation.
Key Research Papers
- Jull AB, Cullum N, Dumville JC, Westby MJ, Deshpande S, Walker N (2015). Honey as a topical treatment for wounds. Cochrane Database of Systematic Reviews — PubMed PMID: 25742878
- Subrahmanyam M (1991). Topical application of honey in treatment of burns. British Journal of Surgery — PubMed PMID: 2032114
- Molan P, Rhodes T (2015). Honey: A Biologic Wound Dressing. Wounds — PubMed PMID: 26061489
- Cooper RA, Halas E, Molan PC (2002). The efficacy of honey in inhibiting strains of Pseudomonas aeruginosa from infected burns. Journal of Burn Care & Rehabilitation. PubMed PMID: 12432313
- Cooper RA, Molan PC, Harding KG (2002). The sensitivity to honey of Gram-positive cocci of clinical significance isolated from wounds. Journal of Applied Microbiology — PubMed PMID: 12392533
- Maeda Y, Loughrey A, Earle JA et al. (2008). Antibacterial activity of honey against community-associated methicillin-resistant Staphylococcus aureus. Complementary Therapies in Clinical Practice. PubMed PMID: 18396250
- Maddocks SE, Lopez MS, Rowlands RS, Cooper RA (2012). Manuka honey inhibits the development of Streptococcus pyogenes biofilms and causes reduced expression of two fibronectin binding proteins. Microbiology — PubMed PMID: 22294681
- Carter DA, Blair SE, Cokcetin NN et al. (2016). Therapeutic Manuka Honey: No Longer So Alternative. Frontiers in Microbiology — PubMed PMID: 27148246
- Roberts AEL, Maddocks SE, Cooper RA (2015). Manuka honey reduces the motility of Pseudomonas aeruginosa by suppression of flagella-associated genes. Journal of Antimicrobial Chemotherapy. PubMed PMID: 25404649
- Jull A, Walker N, Parag V, Molan P, Rodgers A (2008). Randomized clinical trial of honey-impregnated dressings for venous leg ulcers (HALT trial). British Journal of Surgery — PubMed PMID: 18161896
- Kamaratos AV, Tzirogiannis KN, Iraklianou SA, et al. (2014). Manuka honey-impregnated dressings in the treatment of neuropathic diabetic foot ulcers. International Wound Journal — PubMed PMID: 22985336
- Gethin G, Cowman S (2008). Bacteriological changes in sloughy venous leg ulcers treated with manuka honey or hydrogel: an RCT. Journal of Wound Care — PubMed PMID: 18666717
- Aziz Z, Abdul Rasool Hassan B (2017). The effects of honey compared to silver sulfadiazine for the treatment of burns: A systematic review of randomized controlled trials. Burns — PubMed PMID: 27576926
- Yaghoobi R, Kazerouni A, Kazerouni O (2013). Evidence for clinical use of honey in wound healing as an anti-bacterial, anti-inflammatory anti-oxidant and anti-viral agent: A review. Jundishapur Journal of Natural Pharmaceutical Products — PubMed PMID: 24624197
PubMed Topic Searches
Connections
- All Food
- Wound Healing — the full repair guide: phases, first aid, nutrition, dressings
- Honey Main Page
- Honey Benefits Hub
- Manuka and MGO Rating
- Raw vs Pasteurized
- Cough Suppressant Evidence
- Wound Care
- Burns
- Methicillin-Resistant Staphylococcus Aureus
- Pseudomonas aeruginosa
- Diabetes Foot Ulcer
- Eczema
- Remedies
- Immune Boosting
- History
- Nutrients