Quinoa Glycemic Index
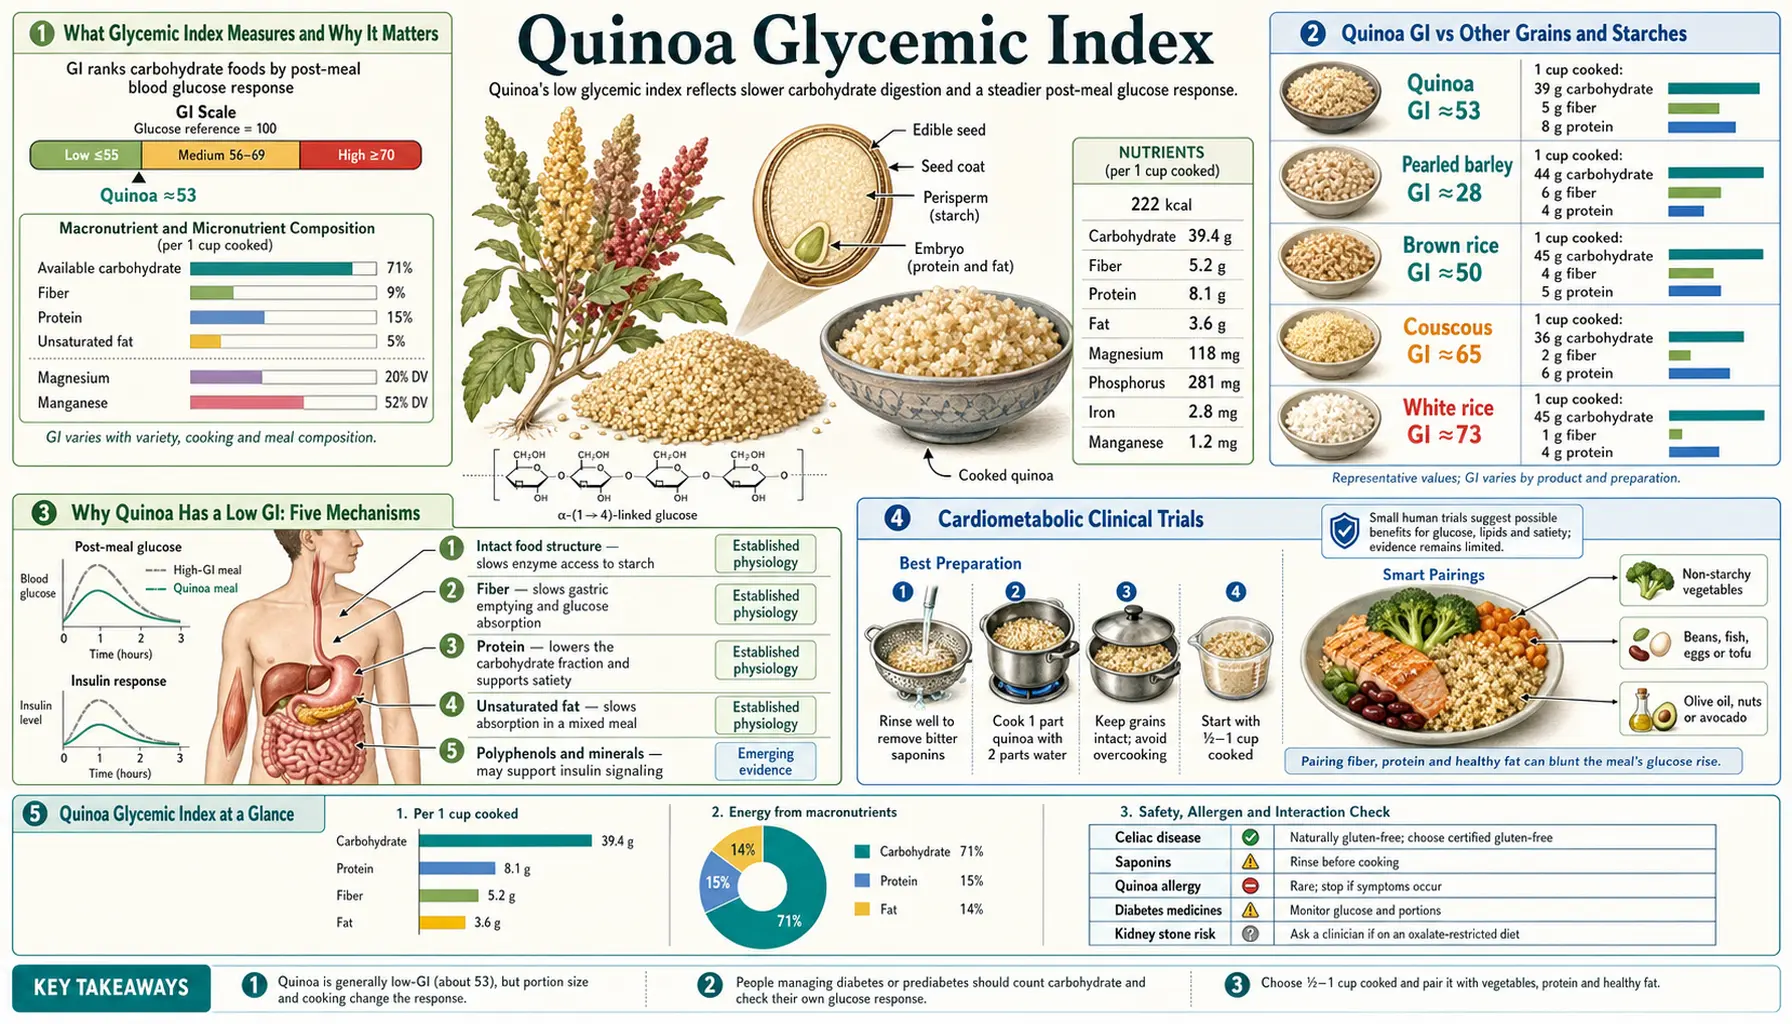
Quinoa has a glycemic index (GI) of approximately 53, placing it just below the 55-threshold that separates "low GI" foods from "moderate GI" foods, and well below the major refined-grain alternatives: white rice (GI ~73), brown rice (~68), couscous (~65), bulgur (~46-55), white potato (~78), and white bread (~75). The glycemic load of a typical 150 g cooked serving is about 13, which is modest. Randomized controlled trials of quinoa lasting 4-12 weeks have given mixed, mostly small results: in some, triglycerides, low-density lipoprotein (LDL) cholesterol, body weight or hemoglobin A1c (HbA1c) fell with quinoa, while in others, including a 2026 trial of 148 adults, the changes did not differ from those with the comparison grains. This page covers the chemistry that explains the low GI (resistant starch, high amylose ratio, fiber, protein, polyphenols), the relevant cardiometabolic clinical trials, and the practical implications for type 2 diabetes prevention and management, dyslipidemia, and metabolic syndrome.
Table of Contents
- What Glycemic Index Measures and Why It Matters
- Quinoa GI vs Other Grains and Starches
- Why Quinoa Has a Low GI: Five Mechanisms
- Cardiometabolic Clinical Trials
- Lipid Effects: Low-Density Lipoprotein, Triglycerides, High-Density Lipoprotein
- Weight and Satiety Effects
- Quinoa in Metabolic Syndrome
- How Quinoa Fits Type 2 Diabetes Meal Plans
- Quinoa Polyphenols and Insulin Sensitivity
- Cooking, Cooling, and Resistant Starch
- Cautions
- Key Research Papers
- Connections
- Featured Videos
What Glycemic Index Measures and Why It Matters
The glycemic index (GI) is a ranking of carbohydrate-containing foods on a 0-100 scale based on how much they raise blood glucose in the two hours after eating, compared with a reference food (typically glucose itself, assigned GI 100). The standard test involves giving subjects a portion of test food containing 50 g of available carbohydrate, drawing capillary glucose at intervals over 2 hours, calculating the area under the curve, and comparing it to the area under the curve from 50 g pure glucose.
Foods are categorized as:
- Low GI — 55 or below (most legumes, most fruits, dairy, quinoa, steel-cut oats, sweet potatoes)
- Moderate GI — 56 to 69 (whole wheat bread, brown rice, white potato when cooked-and-cooled, sucrose itself at GI 65)
- High GI — 70 and above (white rice, white bread, instant oatmeal, hot white potato, glucose at 100)
The clinical relevance: high-GI foods produce rapid blood glucose spikes that trigger correspondingly large insulin releases. Chronic exposure to high postprandial glucose and insulin contributes to insulin resistance, beta-cell stress, dyslipidemia, and weight gain. Multiple long-term cohort studies (Nurses' Health Study, Health Professionals Follow-up Study, EPIC-Norfolk) have linked high dietary glycemic load to increased risk of type 2 diabetes and cardiovascular disease, independent of total carbohydrate intake.
The glycemic load (GL) refines GI by accounting for portion size. GL is calculated as (GI × grams of available carbohydrate in the portion) ÷ 100. A typical 150 g cooked-quinoa serving contains about 25 g available carbohydrate, giving a GL of (53 × 25) ÷ 100 = 13, classified as moderate. The same weight of white rice contains about 40 g available carbohydrate at GI 73, giving GL = (73 × 40) ÷ 100 = 29, more than double.
For diabetes management, both the GI of individual foods and the cumulative daily GL matter. The American Diabetes Association notes that low-GI diets produce modest but consistent improvements in hemoglobin A1c (about 0.4 percentage points) and that this contribution accumulates with other interventions (medication, weight loss, physical activity).
Quinoa GI vs Other Grains and Starches
The International Tables of Glycemic Index (Atkinson, Foster-Powell, Brand-Miller, updated periodically) provide the standard reference values. For grains and starches in their typical cooked forms:
- Quinoa, cooked — GI ~53 (low)
- Bulgur, cooked — GI ~46-55 (low to borderline)
- Pearl barley, cooked — GI ~28 (low)
- Steel-cut oats — GI ~52 (low)
- Brown rice, cooked — GI ~68 (moderate)
- Couscous, cooked — GI ~65 (moderate)
- Whole wheat pasta — GI ~48 (low)
- White rice, cooked — GI ~73 (high)
- Jasmine rice — GI ~89 (very high)
- White bread — GI ~75 (high)
- Instant oatmeal — GI ~79 (high)
- Cornflakes — GI ~81 (very high)
- Boiled white potato (hot) — GI ~78 (high)
- Cooked-and-cooled white potato — GI ~58 (moderate, due to resistant starch)
- Sweet potato — GI ~63 (moderate)
Quinoa is competitive with the lowest-GI common grains (steel-cut oats, pearl barley, bulgur, whole wheat pasta) and substantially lower than the most-consumed staples in many cultures (white rice in Asia, white bread in Europe and North America, instant breakfast cereals globally). The substitution opportunity is meaningful — replacing one daily white-rice meal with a quinoa-based meal produces a measurable reduction in daily glycemic load and, over weeks to months, measurable improvements in metabolic markers.
Why Quinoa Has a Low GI: Five Mechanisms
Several quinoa-specific properties combine to slow glucose absorption and lower the postprandial spike.
1. High amylose-to-amylopectin ratio. Starch consists of two polymers of glucose: linear amylose and highly branched amylopectin. The branching pattern of amylopectin presents more enzyme-accessible chain ends to alpha-amylase and is rapidly digested. Linear amylose forms tighter helical structures that resist enzymatic attack. Quinoa starch is about 11% amylose vs roughly 18-25% in conventional rice; however, quinoa starch granules are exceptionally small (1-2 micrometers vs 5-10 for rice and 10-30 for wheat), and the small granule size combined with the protein-encapsulated granule architecture actually slows digestion despite the lower amylose percentage.
2. Resistant starch content. A fraction of quinoa starch (about 2-3% of dry weight in freshly cooked quinoa, rising to 5-6% when cooked and cooled) resists digestion in the small intestine and reaches the colon, where it is fermented by gut bacteria to short-chain fatty acids (butyrate, propionate, acetate). Resistant starch is functionally similar to dietary fiber for glycemic effect: it contributes no glucose to the bloodstream and triggers glucagon-like peptide-1 (GLP-1) release that further reduces postprandial glucose.
3. Soluble and insoluble fiber. Cooked quinoa supplies about 2.8 g fiber per 100 g (compared with 0.4 g in white rice). The fiber slows gastric emptying and physically traps starch granules in a gel-like matrix that delays alpha-amylase access.
4. Protein content. Quinoa is roughly 14% protein on a dry basis (vs 7-8% for rice), and the protein matrix physically embeds starch granules within the cooked grain. Concurrent dietary protein also stimulates glucagon-like peptide-1 and CCK release and slows gastric emptying, both of which blunt the postprandial glucose response.
5. Polyphenols (quercetin, kaempferol, ferulic acid). Quinoa is unusually rich in flavonoid polyphenols, particularly quercetin and kaempferol, which inhibit alpha-amylase and alpha-glucosidase activity at physiologically relevant concentrations — the same mechanism as the prescription antidiabetic drugs acarbose and miglitol, though much weaker. Quercetin in particular also has documented direct effects on insulin sensitivity and on intestinal SGLT-1 glucose transport.
The combination of all five mechanisms accounts for the observed low GI. No single mechanism dominates, and the effect is reduced if quinoa is overcooked into a mush (which disrupts granule architecture and protein matrix) or if it is consumed alone without complementary protein or fat.
Cardiometabolic Clinical Trials
Several controlled trials have tested quinoa in place of other grains or a placebo over 4-12 week intervention periods, with mixed results. Key examples:
- Navarro-Perez et al. 2017 — 50 adults with overweight or obesity, randomized to no quinoa, 25 g or 50 g of quinoa a day for 12 weeks. Body composition and total, LDL and HDL cholesterol did not change significantly; serum triglycerides fell from 1.14 to 0.72 mmol/L in the 50 g group only.
- De Carvalho et al. 2014 — 35 postmenopausal women with excess weight ate 25 g of quinoa flakes or corn flakes daily for 4 weeks (double-blind). Triglycerides fell in both groups; total cholesterol (191 to 181 mg/dL) and LDL cholesterol (129 to 121 mg/dL) fell only in the quinoa group.
- Abellán Ruiz et al. 2017 — a Spanish double-blind trial in 30 adults with prediabetes, randomized 2:1 to a processed quinoa product or a placebo powder (maltodextrin) for 28 days. In the quinoa group, body mass index and HbA1c fell and fullness ratings rose; fasting glucose did not change.
- Pourshahidi et al. 2020 — a randomized double-blind crossover trial in 40 healthy adults aged 50-75 (most with high cholesterol), who ate 15 g of quinoa biscuits or wheat biscuits daily for 4 weeks each. Compared with the wheat biscuits, the quinoa biscuits lowered total cholesterol by 0.30 mmol/L, LDL cholesterol by 0.25 mmol/L and weight by 0.61 kg; triglycerides, HDL cholesterol and C-reactive protein (CRP) did not differ.
- Li et al. 2018 — 37 healthy men with overweight ate bread providing 20 g of quinoa flour a day or refined wheat bread, 4 weeks each (crossover). Blood glucose and LDL cholesterol fell in both periods with no difference between quinoa and control; the only difference was a lower glucose area under the curve on continuous monitoring during the last 4 days of the quinoa period.
- Berti et al. 2004 (early study) — glucose and insulin responses to three gluten-free foods and ordinary bread in healthy volunteers, with an exploratory comparison with people with celiac disease. The glycemic index of quinoa was slightly lower than that of gluten-free pasta and bread; insulin responses did not differ; the authors wrote that further and larger studies are required.
- Oztekin et al. 2026 — a randomized trial in Turkey in 148 adults aged 25-45 with overweight or obesity, who ate 40 g a day of quinoa, buckwheat, bulgur or rice for 4 weeks. Changes in blood tests and body measurements did not differ between the four groups. Within the quinoa group, fat mass fell, fasting glucose fell in men only, and total cholesterol fell in men but rose in women.
The collective pattern: these are small, short trials (29-148 people, 4-12 weeks) with mixed results. Where effects appeared they were modest — for example an LDL drop of 0.25 mmol/L (about 10 mg/dL) in older adults eating quinoa biscuits — and two trials found no difference from the comparison grain. None of these trials lasted longer than 12 weeks.
Lipid Effects: Low-Density Lipoprotein, Triglycerides, High-Density Lipoprotein
Lipid changes are the effect reported most often in quinoa trials, although results differ between trials. Several mechanisms are proposed:
- Soluble fiber binding bile acids — the soluble fiber in quinoa binds bile acids in the small intestine, increasing fecal bile acid excretion. The liver compensates by upregulating bile acid synthesis from cholesterol, drawing down hepatic and plasma cholesterol pools. This is the same mechanism as the bile acid sequestrant drug class (cholestyramine, colesevelam).
- Residual saponins binding cholesterol — saponins (even in trace residual amounts after washing) bind dietary and biliary cholesterol in the gut lumen, reducing absorption. See the Saponin Removal page.
- Substitution effect — replacing a serving of refined grain with quinoa replaces a high-glycemic, low-fiber, low-protein food with a low-glycemic, moderate-fiber, complete-protein food. Even at constant total calories, the substitution favorably shifts hepatic de novo lipogenesis (which is driven by postprandial glucose and insulin spikes) toward lower triglyceride production.
- Plant sterols and squalene — quinoa contains plant sterols and is unusually rich in squalene (a cholesterol biosynthesis intermediate). Plant sterols compete with dietary cholesterol for micelle space in the intestinal lumen, reducing cholesterol absorption.
- Polyunsaturated fatty acid contribution — quinoa contains about 6% fat by dry weight, with a favorable PUFA profile dominated by alpha-linolenic acid (ALA, omega-3) and linoleic acid (omega-6).
The measured lipid results of the trials above:
- Navarro-Perez 2017 (50 g a day, 12 weeks): triglycerides 1.14 to 0.72 mmol/L; LDL, total and high-density lipoprotein (HDL) cholesterol unchanged; no change at 25 g a day
- De Carvalho 2014 (25 g quinoa flakes, 4 weeks): LDL cholesterol 129 to 121 mg/dL and total cholesterol 191 to 181 mg/dL in the quinoa group only; triglycerides fell in both groups
- Pourshahidi 2020 (15 g quinoa biscuits, 4 weeks): LDL cholesterol 0.25 mmol/L lower and total cholesterol 0.30 mmol/L lower than with wheat biscuits; triglycerides and HDL not different
- Li 2018 (20 g quinoa flour in bread, 4 weeks): LDL fell in both the quinoa and wheat periods, with no difference between them
What is not known: no trial cited here has tested quinoa for longer than 12 weeks, and none was run in people with diagnosed diabetes, so the long-term effect on cholesterol, blood sugar or heart disease is not established.
Weight and Satiety Effects
Quinoa's combination of protein, fiber, and slow-digesting carbohydrate produces a strong satiety signal. Subjects given quinoa-based test meals report higher fullness ratings and lower hunger ratings over the following 3-4 hours compared with isocaloric refined-grain test meals. Mechanisms include slower gastric emptying, sustained glucagon-like peptide-1 release, sustained CCK release, and reduced post-meal glucose volatility that prevents the rebound-hypoglycemia hunger seen with high-GI meals.
Translating satiety into measurable weight change has produced mixed results. In ad-libitum substitution trials where subjects can adjust other intake freely, modest weight reductions (1-3 kg over 6-12 weeks) have been reported. In strict isocaloric substitution trials, weight change is minimal but body composition shifts modestly favorable (small increases in lean mass, small reductions in visceral fat). The quinoa-driven weight effect is real but small; quinoa is not a weight-loss intervention on its own but contributes to a broader dietary pattern that supports gradual weight stability or modest loss.
Quinoa in Metabolic Syndrome
Metabolic syndrome (the cluster of central obesity, elevated triglycerides, low high-density lipoprotein, elevated blood pressure, and elevated fasting glucose) is the dominant cardiovascular and diabetes risk pattern in modern Western populations. Quinoa substitution affects all five components of the syndrome to some degree:
- Central obesity — modest reductions in waist circumference (1-3 cm) in some trials, driven by satiety and improved insulin sensitivity
- Elevated triglycerides — 10-25% reduction in fasting and postprandial triglycerides (the most robust quinoa effect)
- Low high-density lipoprotein — minimal change or modest increase; the high-density lipoprotein effect is the smallest and least consistent
- Elevated blood pressure — modest reductions (2-4 mmHg systolic), likely combining ACE-inhibitor bioactive peptide effects, magnesium contribution, and low-GI / weight-related improvements
- Elevated fasting glucose — reductions of 5-15 mg/dL in pre-diabetic populations, smaller reductions in established T2D
For prevention-focused dietary patterns (Mediterranean, DASH, MIND), quinoa fits naturally as a grain substitute. The combination with leafy greens, legumes, olive oil, fatty fish, and nuts produces an additive cardiometabolic benefit greater than any single component alone. For more on metabolic syndrome, see the Type 2 Diabetes page.
How Quinoa Fits Type 2 Diabetes Meal Plans
For people with established type 2 diabetes, these points follow from the glycemic data above.
- Substitution, not addition — quinoa replacing a comparable portion of refined grain (white rice, couscous, pasta, bread) is the format that produces glycemic improvement. Adding quinoa on top of existing carbohydrate intake adds calories without the substitution benefit.
- Standard portion is 1/2 to 3/4 cup cooked — about 90-130 g, providing 15-23 g available carbohydrate (1-1.5 "carb exchanges" in diabetic education terms). This pairs well with a protein source and a non-starchy vegetable.
- Protein and fat at the same meal — adding a chicken breast, salmon fillet, lentil dal, or a generous drizzle of olive oil further reduces the postprandial glucose response by slowing gastric emptying.
- Cooling and reheating for additional resistant starch — cooked quinoa stored in the refrigerator overnight develops additional retrograded starch, increasing the resistant starch content from ~3% to ~5-6%. Reheated quinoa retains most of this benefit. Quinoa salads (cooked, cooled, dressed) are particularly favorable from a glycemic perspective.
- Individual glucose response varies — glycemic response varies meaningfully between individuals based on gut microbiome, insulin sensitivity, prior meal composition, and physical activity. Self-monitoring after quinoa-based meals can confirm the expected benefit and guide portion adjustments.
- Insulin dosing — quinoa is not low-carb. A 1/2-cup serving still contains about 17 g carbohydrate, which counts toward insulin coverage in carbohydrate counting; the GI benefit is in glucose stability rather than total carb load.
Quinoa Polyphenols and Insulin Sensitivity
Beyond the macronutrient and fiber effects, quinoa supplies substantial flavonoid polyphenols, including quercetin, kaempferol, ferulic acid, and several glycoside derivatives. The polyphenol content is concentrated in the seed coat and bran fraction; whole-grain quinoa retains substantially more than processed quinoa flour.
Quercetin in particular has documented direct effects on glucose metabolism:
- Inhibition of alpha-amylase and alpha-glucosidase (delays starch digestion)
- Inhibition of intestinal SGLT-1 glucose transport (delays glucose absorption)
- Improved insulin sensitivity in muscle and adipose tissue (in cell culture and animal studies)
- Anti-inflammatory effects that may reduce chronic low-grade inflammation contributing to insulin resistance
- Antioxidant activity that may protect pancreatic beta cells from oxidative damage
The polyphenol contribution from a typical serving of quinoa is modest in absolute terms (about 15-30 mg total flavonoids per 100 g cooked) but adds to the overall favorable metabolic profile. In combination with other polyphenol sources (berries, dark leafy greens, tea, dark chocolate, extra-virgin olive oil), the cumulative polyphenol intake from a quinoa-inclusive diet pattern is substantial.
Cooking, Cooling, and Resistant Starch
The glycemic properties of quinoa can be enhanced through controlled cooking and storage:
- Standard cooking — 1 cup quinoa + 2 cups water/broth, bring to boil, reduce to simmer, cover, cook 15-20 minutes until water absorbed and germ has spiraled away from seed.
- Overnight refrigeration — the gelatinized starch retrogrades into more ordered crystalline structures resistant to enzymatic digestion. This roughly doubles resistant starch content.
- Cold or briefly reheated — cold quinoa salad retains the maximum resistant starch. Brief microwave reheating (under 1 minute) preserves most of the retrograded starch. Long reheating or repeated cooking-cooling cycles can re-gelatinize and reduce the benefit.
- Overcooking — overcooked mushy quinoa has higher GI than al-dente quinoa because the starch granules have been more completely gelatinized and the protein-starch matrix is disrupted.
- Vinegar or lemon — acetic acid further slows starch digestion by inhibiting amylase activity. Dressing quinoa salads with vinegar-based dressings produces an additional small GI reduction.
The "cooked and cooled" trick works for any starchy food (rice, potatoes, pasta, oats) but is particularly easy to exploit with quinoa because cold quinoa is a culturally accepted format (quinoa salad) and stores well.
Cautions
- Carbohydrate is still carbohydrate — quinoa is not "low carb." A typical 150 g cooked serving still provides about 25 g available carbohydrate. For people on strict low-carb or ketogenic diets, one serving uses up a large share of the day's carbohydrate allowance.
- Oxalate content — quinoa is moderately oxalate-rich (about 21 mg per 100 g cooked). This matters for people with calcium oxalate kidney stones; calcium-rich foods eaten at the same meal (yogurt, cheese, leafy greens) bind oxalate in the gut lumen before absorption.
- Phytate effect on minerals — quinoa phytate reduces iron and zinc absorption modestly. Soaking, sprouting, or pairing with vitamin C-rich foods (citrus, peppers, tomatoes) mitigates this effect.
- Portion control still applies — the glycemic load of a 1-cup quinoa serving is about 26, which is moderate but adds up across multiple servings. Diabetic and pre-diabetic meal plans commonly use a 1/2 to 3/4 cup portion.
- Cooking method matters — overcooked or pressure-cooked quinoa loses some of its GI advantage. Standard stovetop cooking to al-dente texture preserves the benefit.
- Quinoa flour is higher GI — finely ground quinoa flour digests faster than intact cooked grains. Baked goods made with quinoa flour are still better than refined wheat flour baked goods but do not match the GI of whole-grain quinoa.
Key Research Papers
- Atkinson FS, Foster-Powell K, Brand-Miller JC (2008). International tables of glycemic index and glycemic load values. Diabetes Care. — PubMed PMID: 18835944
- Navarro-Perez D, Radcliffe J, Tierney A, Jois M (2017). Quinoa seed lowers serum triglycerides in overweight and obese subjects: a dose-response randomized controlled clinical trial. Current Developments in Nutrition. — PubMed PMID: 29955719
- Abellán Ruiz MS, Barnuevo Espinosa MD, García Santamaría C et al. (2017). [Effect of quinua (Chenopodium quinoa) consumption as a coadjuvant in nutritional intervention in prediabetic subjects]. Nutrición Hospitalaria. 2017;34(5):1163-1169. — PubMed PMID: 29130716
- Pourshahidi LK, Caballero E, Osses A, Hyland BW, Ternan NG, Gill CIR (2020). Modest improvement in CVD risk markers in older adults following quinoa (Chenopodium quinoa Willd.) consumption: a randomized-controlled crossover study with a novel food product. European Journal of Nutrition. 2020;59(7):3313-3323. — PubMed PMID: 31919583
- Li L, Lietz G, Bal W, Watson A, Morfey B, Seal C (2018). Effects of quinoa (Chenopodium quinoa Willd.) consumption on markers of CVD risk. Nutrients. 2018;10(6):777. — PubMed PMID: 29914146
- Berti C, Riso P, Monti LD, Porrini M (2004). In vitro starch digestibility and in vivo glucose response of gluten-free foods and their gluten counterparts. European Journal of Nutrition. — PubMed PMID: 15309439
- Foucault AS et al. (2012). Quinoa extract enriched in 20-hydroxyecdysone protects mice from diet-induced obesity and modulates adipokines expression. Obesity (Silver Spring). 2012;20(2):270-7 (animal study). — PubMed PMID: 21869758
- Tang Y, Tsao R (2017). Phytochemicals in quinoa and amaranth grains and their antioxidant, anti-inflammatory, and potential health-beneficial effects: a review. Molecular Nutrition and Food Research. 2017;61(7). — PubMed PMID: 28239982
- Graf BL et al. (2015). Innovations in health value and functional food development of quinoa (Chenopodium quinoa Willd.) Comprehensive Reviews in Food Science and Food Safety. — PubMed PMID: 27453695
- Brand-Miller JC, Stockmann K, Atkinson F et al. (2009). Glycemic index, postprandial glycemia, and the shape of the curve in healthy subjects. American Journal of Clinical Nutrition. — PubMed PMID: 19056599
- Livesey G, Taylor R, Livesey HF et al. (2019). Dietary glycemic index and load and the risk of type 2 diabetes: a systematic review and updated meta-analyses. Nutrients. — PubMed PMID: 31195724
- Tang Y et al. (2015). Characterization of phenolics, betanins and antioxidant activities in seeds of three Chenopodium quinoa Willd. genotypes. Food Chemistry. — PubMed PMID: 25053071
- De Carvalho FG, Ovídio PP, Padovan GJ, Jordão Junior AA, Marchini JS, Navarro AM (2014). Metabolic parameters of postmenopausal women after quinoa or corn flakes intake — a prospective and double-blind study. International Journal of Food Sciences and Nutrition. 2014;65(3):380-5. — PubMed PMID: 24344670
- Oztekin Y, Gonen-Colak B, Tekin S, Lay I, Erbas T, Dagdelen S, Buyuktuncer Z (2026). Comparative effects of quinoa, buckwheat, bulgur, and rice on cardiometabolic health in adults with overweight or obesity: a randomized controlled study. Metabolites. 2026;16(9):628. — PubMed PMID: 42783753