⚠ Evidence warning: Clinical trials or other evidence do not support the claims that urolithin metabotype A producers have the strongest responses to pomegranate while metabotype 0 subjects respond weakly or not at all, that direct urolithin A is safe and gives consistent mitochondrial changes across all metabotype groups and is the more reliable choice for targeted mitophagy, and that dietary pomegranate is adequate for routine cardiovascular and anti-inflammatory effects. This page keeps it as a report of what people, websites or other media say.
Pomegranate Punicalagins and Antioxidants
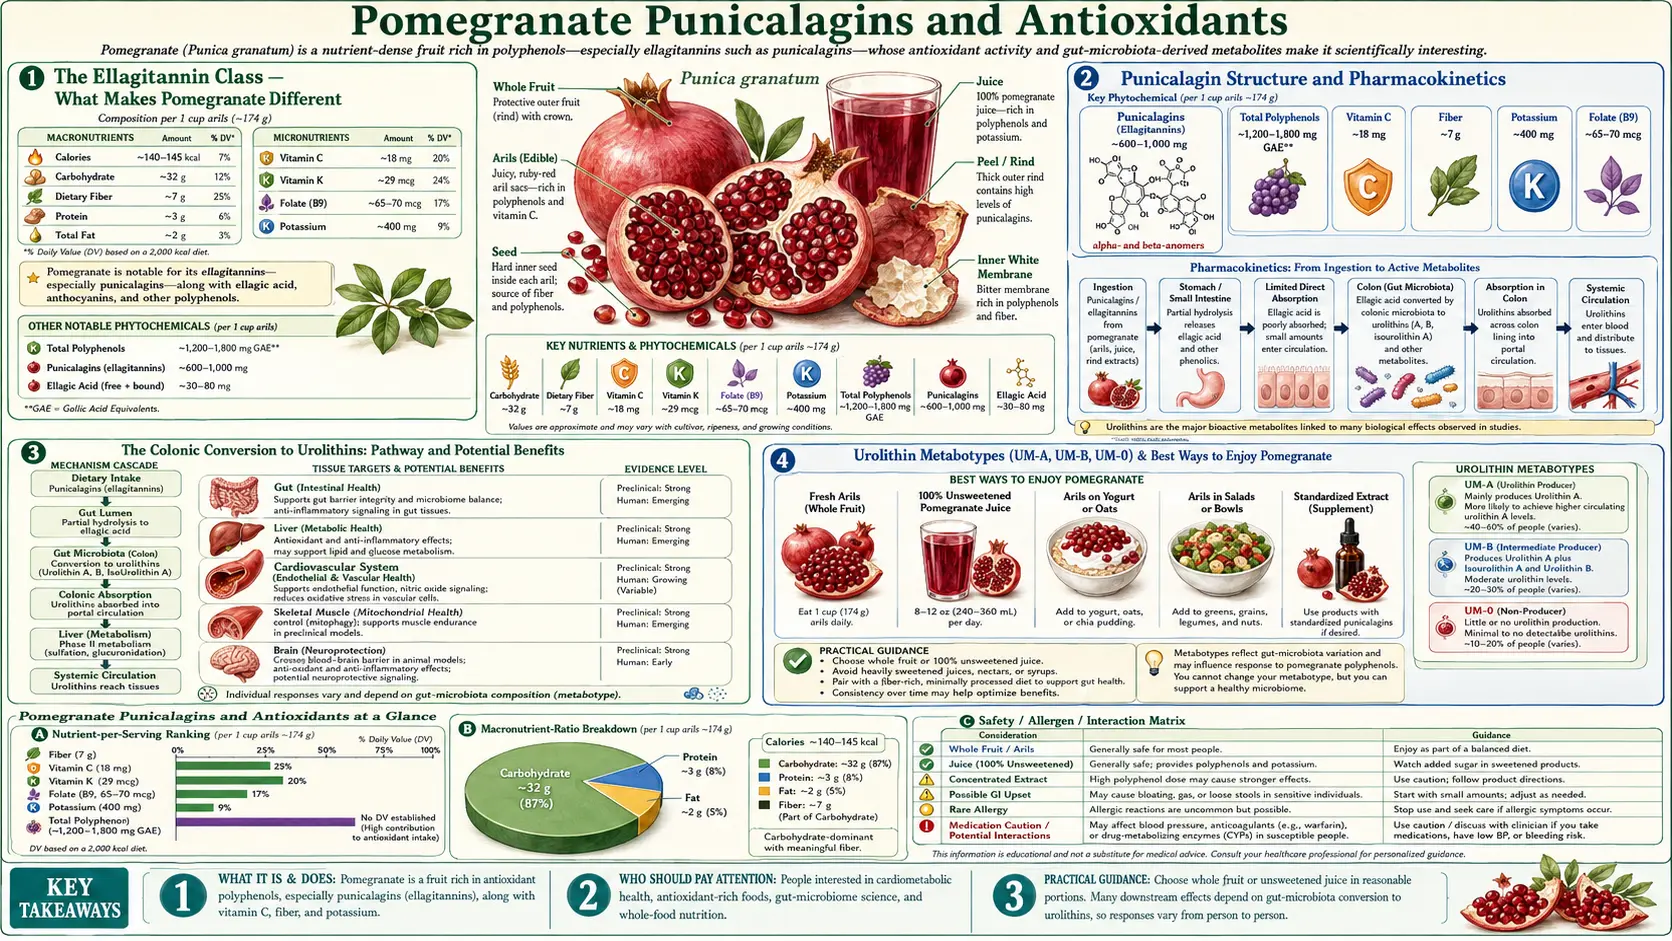
Pomegranate's pharmacology is built around one molecular family that is largely unique to the fruit: the punicalagins, a pair of giant ellagitannins (molecular weight roughly 1,084 Da) that account for over half of the antioxidant activity of pomegranate juice. These molecules are too large to be absorbed intact — instead, they are hydrolyzed in the upper gut to release free ellagic acid, and the bulk of the dose is then metabolized by specific colonic bacteria into a series of smaller bioactive metabolites called urolithins. Urolithin A is the principal circulating bioactive in humans and the molecule behind most of the cardiovascular, prostate, and mitochondrial effects that show up in clinical trials. This deep dive walks through the chemistry, the metabotype concept that may help explain why pomegranate seems to work well for some people and barely at all for others, and the forms and amounts that studies have used.
Table of Contents
- The Ellagitannin Class — What Makes Pomegranate Different
- Punicalagin Structure and Pharmacokinetics
- The Colonic Conversion to Urolithins
- Urolithin Metabotypes (UM-A, UM-B, UM-0)
- ORAC, FRAP, and the Antioxidant-Activity Question
- NF-kB Inhibition and Anti-Inflammatory Effects
- Urolithin A and Mitophagy (Mitochondrial Quality Control)
- Other Pomegranate Polyphenols (Anthocyanins, Punicic Acid)
- Practical Dose, Form, and Microbiome Considerations
- Key Research Papers
- Connections
- Featured Videos
The Ellagitannin Class — What Makes Pomegranate Different
Plants produce thousands of polyphenols, which are loosely grouped into a few major families: flavonoids (catechins of green tea, anthocyanins of berries, isoflavones of soy), phenolic acids (chlorogenic acid in coffee, hydroxycinnamic acids in many fruits), stilbenes (resveratrol in grape skins and red wine), and tannins. The tannins themselves split into condensed tannins (proanthocyanidins of grape seed, cocoa, apple skin) and hydrolyzable tannins (gallotannins and ellagitannins).
The ellagitannins are a relatively narrow class: walnuts, certain berries (raspberry, strawberry, cloudberry, blackberry), oak-aged spirits, and pomegranate. Of these, pomegranate delivers the largest and most concentrated ellagitannin dose in the human diet. A single 240 mL serving of pomegranate juice typically contains 700-1,800 mg of total polyphenols, of which roughly half are punicalagins. A cup of raspberries delivers maybe 100-300 mg of ellagitannins. A handful of walnuts delivers perhaps 100-200 mg. No other common food comes close to pomegranate on a per-serving basis.
What makes the ellagitannins pharmacologically interesting is that they are not the actual bioactives. They are essentially prodrugs — large molecules that get broken down in the gut to release free ellagic acid, and the ellagic acid then gets metabolized by the colonic microbiome to produce the urolithins, which are the molecules that actually circulate and reach target tissues. The whole point of consuming pomegranate is to deliver the substrate (punicalagins) that the microbiome converts to the active urolithins.
Punicalagin Structure and Pharmacokinetics
Punicalagin exists as two anomers, alpha and beta, that interconvert in solution. Both have the same molecular formula (C48 H28 O30) and the same molecular weight (1,084 Da). The molecule consists of a glucose core esterified with gallagic acid and hexahydroxydiphenic acid (HHDP) residues — essentially a glucose decorated with multiple aromatic ester groups whose phenolic hydroxyls are responsible for the antioxidant activity.
At 1,084 Da, punicalagin is roughly twice the size of an average drug molecule and far above the practical threshold for passive intestinal absorption. Studies measuring plasma punicalagin after ingestion of pomegranate juice find essentially no intact punicalagin in circulation — the parent compound does not survive the gut.
What happens instead is a series of step-wise hydrolysis reactions. In the acidic stomach and the upper small intestine, the ester bonds are partially cleaved, releasing free ellagic acid (molecular weight 302 Da) and intermediate breakdown products. A small fraction of free ellagic acid is absorbed in the small intestine and conjugated by phase-II enzymes in the liver, producing ellagic acid glucuronide and sulfate conjugates that briefly appear in plasma and urine.
The bulk of the dose, however, reaches the colon largely intact, where it encounters the microbiome. This is where the real bioactivation occurs.
The Colonic Conversion to Urolithins
In the colon, specific bacterial species progressively dehydroxylate ellagic acid through a series of enzymatic steps to produce a family of smaller dibenzopyranone molecules called urolithins. The principal pathway proceeds:
- Ellagic acid → urolithin M5 (four hydroxyls)
- Urolithin M5 → urolithin C (three hydroxyls)
- Urolithin C → urolithin A (two hydroxyls, the principal circulating metabolite)
- Urolithin A → urolithin B (one hydroxyl)
- Side branch: urolithin C → isourolithin A (different hydroxyl positions)
The bacteria principally responsible have been identified through both metagenomic and culture-based work. They belong primarily to the genera Gordonibacter (in particular Gordonibacter pamelaeae and Gordonibacter urolithinfaciens) and Ellagibacter (Ellagibacter isourolithinifaciens), both in the family Eggerthellaceae of the phylum Actinobacteria. These are minor members of a typical adult gut microbiome — usually well under 1% of total bacteria — but their presence or absence determines whether a given individual can convert pomegranate ellagitannins to urolithins at all.
Urolithin A is much smaller than punicalagin (molecular weight 228 Da, similar to a typical drug molecule), lipophilic enough to cross cell membranes, and well absorbed from the colon into the portal circulation. After phase-II conjugation in the liver, urolithin A glucuronide is the dominant form in plasma. Peak plasma concentrations of urolithin A glucuronide after a substantial pomegranate dose typically reach 0.5-2 micromolar and persist for 24-48 hours — long enough to produce meaningful pharmacologic effects with daily intake.
Urolithin Metabotypes (UM-A, UM-B, UM-0)
The discovery that not everyone can convert pomegranate ellagitannins to urolithins is one of the most important developments in pomegranate pharmacology. Francisco Tomas-Barberan's group in Spain described three urolithin-producing groups (metabotypes, also called phenotypes) based on the urinary urolithin profile after eating ellagitannin or ellagic acid foods. Their 2014 summary of several human intervention trials gave these definitions and ranges:
- Metabotype A (UM-A) — produces only urolithin A (as its conjugates). Between 25 and 80% of the volunteers in the different trials. Generally associated with the strongest clinical responses to pomegranate.
- Metabotype B (UM-B) — produces isourolithin A and/or urolithin B in addition to urolithin A. The second relevant group, 10-50% of volunteers. A higher share of metabotype B was seen in volunteers with chronic illness linked to gut microbial imbalance (metabolic syndrome or colorectal cancer).
- Metabotype 0 (UM-0) — none of these urolithins detected; 5-25% of volunteers. These individuals get essentially no urolithin from pomegranate.
The same three groups appeared whatever the ellagitannin food (walnuts and other nuts, strawberries, raspberries and other berries, or pomegranates). A later Spanish cohort of 839 people aged 5 to 90 found that aging is the main factor that determines which metabotype a person has.
The largest individual responses to pomegranate cluster in subjects who turn out to be UM-A producers. UM-0 subjects show much weaker or absent responses to the same dose. Whether metabotype explains why pomegranate trials disagree is still a hypothesis. The Tomas-Barberan group wrote that these phenotypes should be considered in intervention trials of ellagitannins and that whether they relate to different health benefits deserves further research; the early Aviram cardiovascular and Pantuck prostate trials did not report participants' metabotypes. The idea is that if a meaningful fraction of enrolled patients are UM-0, the average response is diluted toward null even though UM-A subgroup responses may still be substantial. In the placebo-controlled phase III prostate trial, pomegranate extract did not significantly lengthen the prostate-specific antigen (PSA) doubling time in men with rising PSA after treatment; the subgroup that did show greater lengthening was defined by a gene variant, the manganese superoxide dismutase (MnSOD) AA genotype, not by urolithin metabotype (Paller, Pantuck and Carducci 2017 review).
The workaround studied so far is direct urolithin A supplementation, sold as commercial urolithin A supplements. Direct urolithin A bypasses the microbiome conversion step. In a 100-person study by the manufacturer's scientists (Singh et al., 2022), only 12% of people had detectable urolithin A at the start and about 40% converted a glass of pomegranate juice into urolithin A, while 500 mg of urolithin A gave more than 6-fold higher urolithin A exposure than the juice. In the first human trial, also by the manufacturer's scientists (Andreux et al., 2019), urolithin A had a favourable safety profile in healthy, sedentary elderly people. Direct urolithin A is safe, well-tolerated, and produces consistent mitochondrial-health biomarker changes across all metabotype groups. The trade-off is cost — direct urolithin A is expensive compared to pomegranate juice.
ORAC, FRAP, and the Antioxidant-Activity Question
Pomegranate juice routinely scores among the highest of any food on the laboratory antioxidant-capacity assays. Seeram's 2008 comparison of commonly consumed polyphenol-rich beverages found pomegranate juice ranked #1 by total polyphenol content, oxygen radical absorbance capacity (ORAC), TEAC (trolox-equivalent antioxidant capacity), and TPC (total polyphenol content), beating red wine, green tea, blueberry juice, acai juice, cranberry juice, and orange juice.
However, the relevance of in-vitro antioxidant assays to in-vivo human health has been seriously questioned. The original oxygen radical absorbance capacity database that the U.S. Department of Agriculture (USDA) maintained for years was withdrawn in 2012 because the agency concluded that food oxygen radical absorbance capacity values do not predict in-vivo antioxidant effects. The reasons are several:
- Most polyphenols are poorly absorbed intact — what reaches plasma is often a heavily metabolized form with much lower antioxidant activity than the parent compound
- The systemic antioxidant system (glutathione, catalase, superoxide dismutase, uric acid) is far more important than any dietary contribution
- In-vitro free-radical scavenging activity does not translate to in-vivo benefit in any reliable way
The pomegranate-specific point is that punicalagin's in-vitro antioxidant activity is largely irrelevant to its in-vivo effect, because punicalagin itself does not reach circulation. What matters in vivo is the urolithin A formed by colonic conversion, and urolithin A is a much weaker direct free-radical scavenger than its parent ellagitannins. The clinical effects of pomegranate are not driven by simple free-radical scavenging — they are driven by specific receptor and signaling effects of the urolithins, particularly mitophagy induction, androgen receptor inhibition, NF-kB inhibition, and ACE inhibition. The oxygen radical absorbance capacity ranking is a marketing tool, not a mechanism of action.
NF-kB Inhibition and Anti-Inflammatory Effects
One of the better-characterized effects of urolithin A and the parent ellagic acid is inhibition of the NF-kB (nuclear factor kappa-light-chain-enhancer of activated B cells) transcription factor pathway. NF-kB is the master regulator of inflammatory gene expression — activated by tumor necrosis factor-alpha, interleukin-1 (IL-1), lipopolysaccharide (LPS), oxidative stress, and many other stimuli, it translocates to the nucleus and induces expression of inflammatory cytokines (interleukin-6, IL-8, tumor necrosis factor, TNF), adhesion molecules (VCAM-1, ICAM-1), and cyclooxygenase-2 (COX-2).
Adams et al. (2006) showed that pomegranate juice, total pomegranate ellagitannins, and isolated punicalagin all suppressed NF-kB activation in cultured colon cancer cells, with parallel reductions in cyclooxygenase-2 expression. The downstream effect is suppression of the chronic low-grade inflammation that drives the cardiovascular, oncogenic, and metabolic complications of aging.
Larrosa et al. (2010) extended this to an animal model of colitis, showing that pomegranate extract and isolated urolithin A both reduced colonic inflammation, MPO activity, cyclooxygenase-2 expression, and inflammatory cytokine production in a rat DSS-colitis model. The urolithin A arm performed as well as the parent extract, supporting the conclusion that urolithin A is the principal in-vivo bioactive.
For human patients, the practical implication is that any condition characterized by chronic inflammation — cardiovascular disease, metabolic syndrome, inflammatory bowel disease, autoimmune conditions — is a proposed target for daily pomegranate or urolithin A, with the caveat that the effect is modest and has not been shown to substitute for primary treatment.
Urolithin A and Mitophagy (Mitochondrial Quality Control)
The most exciting recent finding about urolithin A is its ability to induce mitophagy — the selective autophagy of damaged mitochondria. Mitophagy is the cellular quality-control mechanism that identifies dysfunctional mitochondria (typically marked by collapse of the inner membrane potential and accumulation of PINK1 on the outer membrane), tags them with ubiquitin via Parkin, and routes them to the autophagosome for lysosomal degradation. The cell then replaces them with new mitochondria through PGC-1alpha-driven biogenesis.
Mitophagy declines with age and is impaired in a number of chronic conditions including sarcopenia, neurodegeneration, and cardiometabolic disease. Pharmacologic mitophagy induction has been a major target of geroscience research.
Ryu et al. (2016) in Nature Medicine showed that urolithin A induced mitophagy in C. elegans, prolonged lifespan by 45%, and improved muscle function in older rodents. Andreux et al. (2019) followed up in humans with direct urolithin A supplementation from a commercial urolithin A supplement: in healthy, sedentary elderly people it had a favourable safety profile, and 4 weeks at 500 mg and 1,000 mg changed (the authors write “modulated”) plasma acylcarnitines and skeletal-muscle mitochondrial gene expression — a molecular signature of improved mitochondrial health, not a measured gain in strength or endurance.
What is not known. A 2026 systematic review found only five randomized human trials of urolithin A supplements, with 236 people in total — small, short-term trials in very different groups of people. Only one outcome could be pooled, the 6-minute walk test (two trials): it improved by about 17 m, but the result was not statistically significant and the certainty of evidence was rated low. Results for muscle strength, endurance, aerobic capacity and mitochondrial markers were described as exploratory signals, not reproducible evidence that urolithin A works.
The pomegranate-versus-direct-supplement question matters here. A typical 8 oz pomegranate juice serving delivers enough punicalagin substrate to produce meaningful urolithin A in a UM-A subject, but the achieved plasma concentrations of urolithin A glucuronide from dietary pomegranate are lower and more variable than those from direct supplementation. For routine cardiovascular and anti-inflammatory effects, dietary pomegranate is adequate. For targeted mitophagy induction (e.g. sarcopenia in older adults), direct urolithin A is probably the more reliable choice. The cardiovascular and anti-inflammatory studies used dietary pomegranate, while the human mitophagy trials (for example, in older adults with age-related muscle loss) used direct urolithin A.
Other Pomegranate Polyphenols (Anthocyanins, Punicic Acid)
Punicalagins are the dominant story but not the only one. Pomegranate also contains:
- Anthocyanins (delphinidin, cyanidin, and pelargonidin glycosides) — the red pigments responsible for the color of the juice and arils. These are the same class of pigments found in blueberries and red cabbage. They contribute to the antioxidant activity but are not particularly distinctive of pomegranate.
- Punicic acid (a conjugated linolenic acid, 9Z,11E,13Z-octadeca-9,11,13-trienoic acid) — found in pomegranate seed oil at roughly 65-80% of total fatty acids. Studied in animal models for anti-inflammatory and metabolic effects. Cold-pressed pomegranate seed oil is sold as a separate supplement for these effects.
- Smaller-molecule ellagitannins and gallotannins — punicalin, pedunculagin, and various gallotannins contribute to the total polyphenol pool but follow the same gut-conversion pattern as punicalagins.
- Free ellagic acid — some unbound ellagic acid is present in the juice and is more directly absorbable than the conjugated ellagitannins.
- Vitamin C, potassium, and small amounts of B vitamins — the basic micronutrient content of any fresh fruit. Not the reason to drink pomegranate juice.
The whole-fruit synergy argument — that the various polyphenols work together better than any single isolated compound — is plausible but not well demonstrated. The bulk of the in-vitro and in-vivo bioactivity tracks the urolithin formation, which tracks the ellagitannin load, which is dominated by punicalagins.
Practical Dose, Form, and Microbiome Considerations
What studies have used, and what is known about the microbiome side, for someone interested in the urolithin pharmacology:
- Amounts in use — 8 oz (240 mL) of pure pomegranate juice, or 1 medium pomegranate's arils, or roughly 500-1,000 mg of standardized pomegranate extract (typically standardized to 30-40% punicalagins). The dose used in most positive cardiovascular and prostate trials is 8-16 oz of juice per day.
- Timing — with or without food. The conversion to urolithins is microbiome-driven and not affected by meal timing in any clinically meaningful way.
- Sugar load consideration — 8 oz pomegranate juice contains roughly 30-32 g of sugar (similar to a soft drink). This matters for diabetic and metabolic-syndrome patients. Whole arils provide fiber that buffers the glycemic response. See the Juice vs Whole deep dive for the trade-offs.
- The microbiome — Gordonibacter abundance is described as supported by overall fiber intake and microbial diversity. A diverse plant-rich diet, prebiotic fiber, and fewer unnecessary antibiotic courses are described as supporting the conversion machinery; in the Singh study, people who made urolithin A had a significantly more diverse gut microbiome.
- Direct urolithin A — age is the main factor deciding metabotype in the 839-person cohort, and metabotype B was more common with metabolic syndrome or colorectal cancer. Commercial urolithin A supplements give a urolithin A dose that does not depend on gut bacteria.
- Drug interactions — pomegranate juice is a modest cytochrome P450 3A4 (CYP3A4) inhibitor and may interact with warfarin, statins, and calcineurin inhibitors. In human liver enzyme preparations in the lab, pomegranate juice inhibited the drug-processing enzyme cytochrome P450 3A (CYP3A) about as strongly as grapefruit juice. In people, it did not: in 13 healthy volunteers, 8 oz of pomegranate juice did not change the blood levels or clearance of oral or intravenous midazolam (the standard test drug for this enzyme), while 8 oz of grapefruit juice raised oral midazolam levels about 1.5-fold. See the cautions on the Pomegranate main page.
Key Research Papers
- Cerda B et al. (2004). The potent in vitro antioxidant ellagitannins from pomegranate juice are metabolised into bioavailable but poor antioxidant hydroxy-6H-dibenzopyran-6-one derivatives by the colonic microflora. European Journal of Nutrition — PubMed PMID: 15309440
- Seeram NP et al. (2005). Pomegranate juice ellagitannin metabolites are present in human plasma and some persist in urine for up to 48 hours. Journal of Nutrition — Search PubMed
- Tomas-Barberan FA et al. (2017). Urolithins, the rescue of "old" metabolites to understand a "new" concept: metabotypes as a nexus between phenolic metabolism, microbiota dysbiosis, and host health status. Molecular Nutrition & Food Research — PubMed PMID: 27158799
- Espin JC et al. (2013). Biological significance of urolithins, the gut microbial ellagic acid-derived metabolites: the evidence so far. Evidence-Based Complementary and Alternative Medicine — PubMed PMID: 23781257
- Larrosa M et al. (2010). Anti-inflammatory properties of a pomegranate extract and its metabolite urolithin-A in a colitis rat model. Journal of Nutritional Biochemistry — Search PubMed
- Ryu D et al. (2016). Urolithin A induces mitophagy and prolongs lifespan in C. elegans and increases muscle function in rodents. Nature Medicine — PubMed PMID: 27400265
- Andreux PA et al. (2019). The mitophagy activator urolithin A is safe and induces a molecular signature of improved mitochondrial and cellular health in humans. Nature Metabolism — PubMed PMID: 32694802
- D'Amico D et al. (2021). Impact of the natural compound urolithin A on health, disease, and aging. Trends in Molecular Medicine — PubMed PMID: 34030963
- Seeram NP et al. (2008). Comparison of antioxidant potency of commonly consumed polyphenol-rich beverages in the United States. Journal of Agricultural and Food Chemistry — PubMed PMID: 18220345
- Mertens-Talcott SU et al. (2006). Absorption, metabolism, and antioxidant effects of pomegranate (Punica granatum L.) polyphenols after ingestion of a standardized extract in healthy human volunteers. Journal of Agricultural and Food Chemistry — PubMed PMID: 17090147
- Adams LS et al. (2006). Pomegranate juice, total pomegranate ellagitannins, and punicalagin suppress inflammatory cell signaling in colon cancer cells. Journal of Agricultural and Food Chemistry — Search PubMed
- Heber D (2008). Multitargeted therapy of cancer by ellagitannins. Cancer Letters — PubMed PMID: 18468784
- Tomás-Barberán FA, García-Villalba R, González-Sarriás A, Selma MV, Espín JC (2014). Ellagic acid metabolism by human gut microbiota: consistent observation of three urolithin phenotypes in intervention trials, independent of food source, age, and health status. Journal of Agricultural and Food Chemistry — PubMed PMID: 24976365
- Cortés-Martín A, García-Villalba R, González-Sarriás A, et al. (2018). The gut microbiota urolithin metabotypes revisited: the human metabolism of ellagic acid is mainly determined by aging. Food & Function — PubMed PMID: 30004553
- Paller CJ, Pantuck A, Carducci MA (2017). A review of pomegranate in prostate cancer. Prostate Cancer and Prostatic Diseases — PubMed PMID: 28440320
- Singh A, D'Amico D, Andreux PA, et al. (2022). Direct supplementation with Urolithin A overcomes limitations of dietary exposure and gut microbiome variability in healthy adults to achieve consistent levels across the population. European Journal of Clinical Nutrition — PubMed PMID: 34117375
- Dao T, Nguyen TT, Gariani K, Kim HJ, Ryu D (2026). Effects of Urolithin A supplementation on muscle health outcomes in humans from randomized controlled trials. Frontiers in Nutrition — PubMed PMID: 42559151
- Farkas D, Oleson LE, Zhao Y, et al. (2007). Pomegranate juice does not impair clearance of oral or intravenous midazolam, a probe for cytochrome P450-3A activity: comparison with grapefruit juice. Journal of Clinical Pharmacology — PubMed PMID: 17322140
PubMed Topic Searches
Connections
- All Food
- Pomegranate (Main Page)
- Pomegranate Benefits Hub
- Pomegranate for Prostate & Prostate-Specific Antigen
- Pomegranate for Cardiovascular Health
- Juice vs Whole Arils
- Walnuts (Other Ellagitannin Source)
- Raspberries (Ellagitannin Source)
- Resveratrol
- Green Tea (Epigallocatechin Gallate)
- Vitamin C
- Antioxidant Therapy
- Mitochondrial Support
- Atherosclerosis
- History
- Nutrients