⚠ Evidence warning: Clinical trials or other evidence do not support the claims that pomegranate forms extend prostate-specific antigen doubling time, shrink carotid artery thickening and treat age-related muscle loss. This page keeps it as a report of what people, websites or other media say.
Pomegranate Juice vs Whole Arils — Which Form Delivers the Benefits
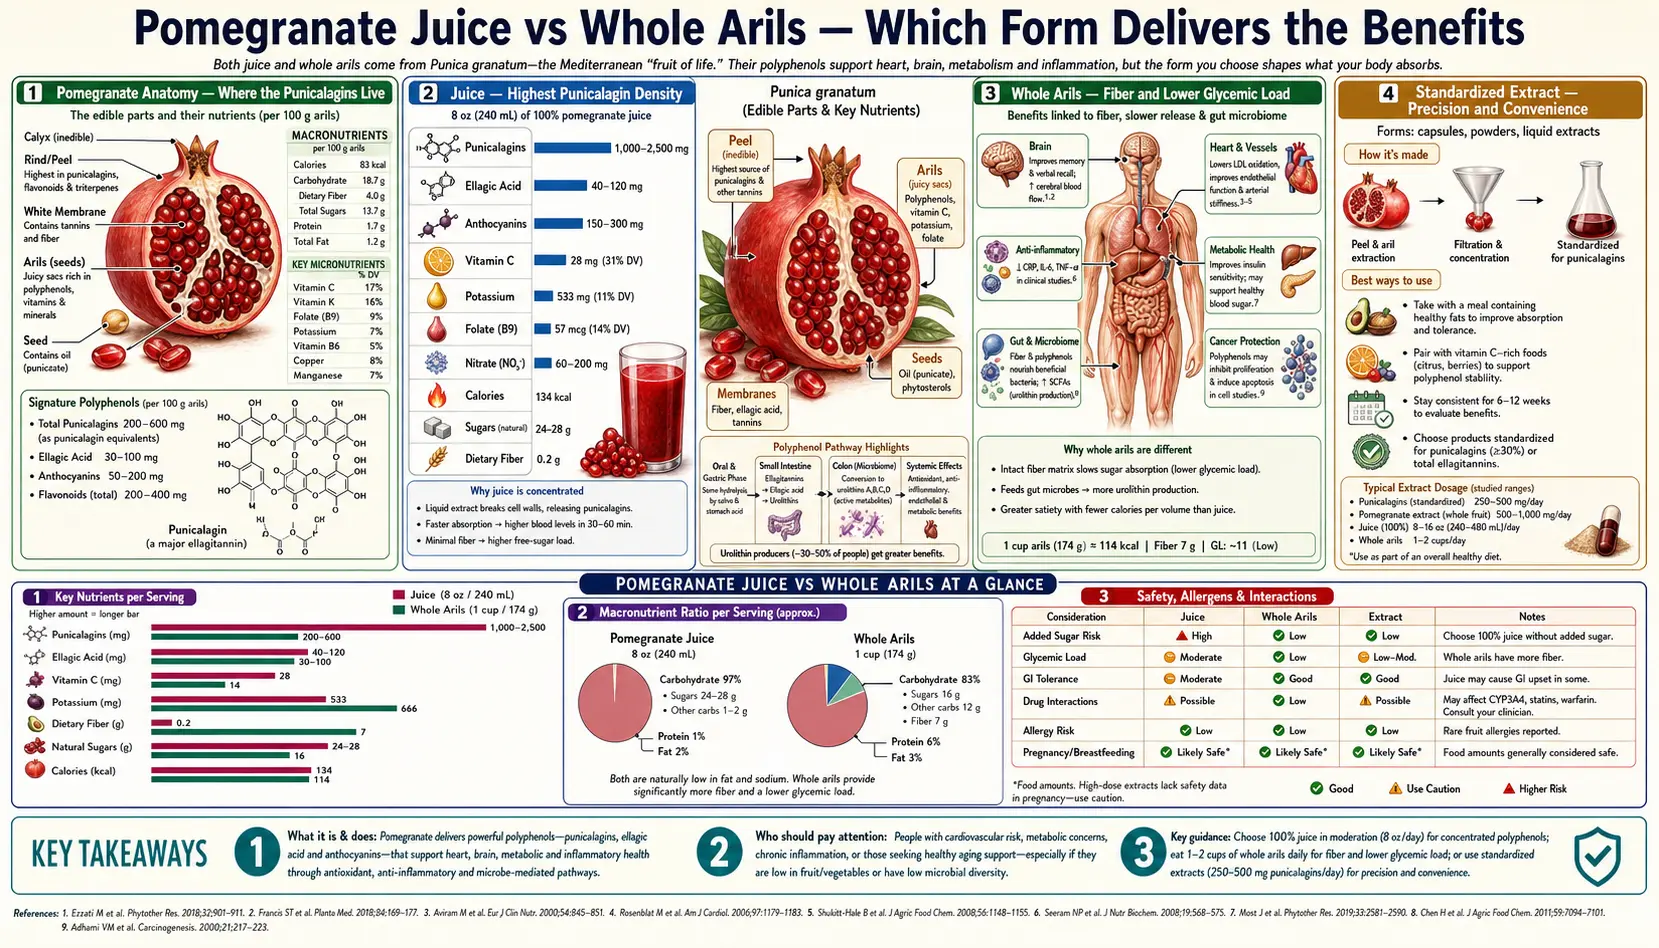
A common practical question about pomegranate is whether to eat the arils (the juicy seed sacs), drink the juice, or take a standardized extract capsule. Each form has trade-offs in punicalagin content, sugar load, fiber, cost, convenience, and seasonal availability. The juice often contains more punicalagins per serving than the arils alone because commercial juicing presses also extract tannins from the rind and the pith (the white spongy material between arils), the tissues reported to hold the highest punicalagin concentrations in the whole fruit. The whole arils win on fiber, sugar regulation, and food-matrix synergy. Concentrated extract wins on dose precision and avoidance of sugar. This deep-dive walks through the differences in punicalagin and ellagic acid content, the glycemic implications, the practical scenarios in which each form is used, and the view often given for healthy adults (whole arils daily, with juice or extract as occasional dose boosts for specific therapeutic targets).
Table of Contents
- Pomegranate Anatomy — Where the Punicalagins Live
- Juice — Highest Punicalagin Density
- Whole Arils — Fiber and Lower Glycemic Load
- Standardized Extract — Precision and Convenience
- Direct Urolithin A Supplements
- Sugar Content and Glycemic Impact
- Cost and Practical Considerations
- Seasonal Availability and Storage
- How Each Form Is Used by Clinical Goal
- Key Research Papers
- Connections
- Featured Videos
Pomegranate Anatomy — Where the Punicalagins Live
A whole pomegranate has four distinct tissue compartments, each with very different polyphenol composition:
- Outer leathery rind (pericarp) — the reddish-tan tough outer skin. Inedible. Very high punicalagin content (5-10% by dry weight in some varieties), but not consumed.
- Inner pith / mesocarp — the white spongy material that divides the fruit into compartments and holds the arils. Inedible in the raw fruit but contributes substantially to commercial juice production. Very high punicalagin content (3-7% by dry weight).
- Arils (the juicy seed sacs) — the red gel-like sacs that contain the juice and seed. The edible portion. Only traces of punicalagin were detected in juice pressed from arils alone in the laboratory (Gil 2000); high anthocyanin content (the red pigments), high vitamin C.
- Seeds (within the arils) — the woody seed at the center of each aril. Contains punicic acid (a conjugated linolenic acid) and is the source of pomegranate seed oil. Most people swallow the seeds with the aril juice; some spit them out.
The highest punicalagin concentration is reported to be in the rind and pith, with the seeds containing relatively little punicalagin but the bulk of the punicic acid. This anatomy explains why commercial juicing — which crushes the whole fruit including the pith and partially the rind — produces juice with higher punicalagin content than the arils alone would suggest. Manual extraction of just the arils (without pith pressing) yields a beverage with less punicalagin per ounce than commercial juice.
Gil et al. (2000) show plainly why home-squeezed and factory juice differ. They compared commercial juices pressed from whole pomegranates with juice made in the laboratory from arils only. The commercial juices held 1,500-1,900 mg of punicalagin per litre, while the aril-only juice held only traces. Antioxidant activity, on a lab scale called Trolox equivalent antioxidant capacity (TEAC), was 18-20 TEAC in commercial juice and 12-14 TEAC in aril-only juice. The authors concluded that factory pressing pulls some of the hydrolyzable tannins out of the fruit rind.
Juice — Highest Punicalagin Density
Commercial 100% pomegranate juice is produced by pressing the entire fruit including the pith. The resulting juice is reported to contain 1,500-2,500 mg of total polyphenols per 240 mL serving. Gil et al. (2000) measured punicalagin at 1,500-1,900 mg per litre of commercial juice, which works out to about 360-456 mg per 240 mL serving. This is far higher than the traces they found in juice from arils alone, because the pressing extracts tannins from the rind, and the pith is also reported to contribute to the punicalagin load.
Tezcan et al. (2009) compared commercial pomegranate juices for total phenolic, organic acid and sugar content, and punicalagin content is reported to vary substantially with processing method, variety, and fruit ripeness. The dark color and the characteristic tannic astringency of pure pomegranate juice both correlate with punicalagin content. Heavily diluted juices, juices with added apple or grape juice, and "from concentrate" reconstituted products typically have lower active punicalagin content than freshly pressed 100% juice.
Advantages of juice:
- Highest punicalagin dose per serving of any commonly available form
- Used as the intervention in most positive clinical trials (Pantuck, Aviram, Sumner)
- Convenient daily dosing — 4-8 oz poured from the bottle
- Year-round availability (commercial juice has a long shelf life)
- Easily incorporated into smoothies, sparkling water, or as a salad-dressing ingredient
Disadvantages of juice:
- High sugar load: 8 oz contains roughly 30-32 g of sugar (similar to a 12 oz cola)
- Expensive: $5-8 per 16 oz bottle in most US grocery stores
- No fiber (extraction process discards the aril skin and pith)
- Some commercial juices include preservatives or are blended with other juices
- Once opened, refrigerated shelf life is typically 5-7 days
Whole Arils — Fiber and Lower Glycemic Load
Eating whole pomegranate arils is the most traditional form of consumption and the form most aligned with the broader principles of whole-food nutrition. A typical medium pomegranate yields about 1 cup of arils (approximately 175 g), containing roughly 24 g of sugar and 7 g of dietary fiber.
The fiber matters for two reasons. First, it slows the absorption of the sugar, producing a much smaller glycemic excursion than the equivalent amount of juice. Second, fiber feeds the colonic microbiome — including Gordonibacter and Ellagibacter species that perform the punicalagin-to-urolithin conversion. A higher-fiber baseline diet supports the microbial conversion machinery that determines whether you get the urolithin payoff from any pomegranate intake.
The aril punicalagin content is often described as moderate — per gram, roughly 30-50% of what commercial juice delivers, because the pith contribution is absent. Gil et al. (2000) measured much less in laboratory juice from arils: only traces, against 1,500-1,900 mg per litre in commercial juices. The calorie- and sugar-adjusted comparison is often said to favor arils, on the idea that per gram of sugar consumed arils deliver more punicalagin than juice does; the Gil measurements point the other way, with far more punicalagin in commercial juice.
Advantages of whole arils:
- Fiber benefit — both glycemic and microbiome-supporting
- Lower glycemic load per serving than juice
- Whole-food matrix synergy (vitamin C, anthocyanins, fiber, polyphenols together)
- Satiety — arils require chewing and produce more meaningful satiety than juice
- Often less expensive per gram of polyphenol than premium juices
Disadvantages of whole arils:
- Lower absolute punicalagin dose than juice (so for therapeutic protocols requiring large punicalagin loads, juice or extract may be more practical)
- Seasonal availability — fresh whole pomegranates are widely available October through January in the northern hemisphere; spring and summer availability is limited and prices rise
- Aril extraction is messy and time-consuming if not buying pre-extracted
- Pre-extracted refrigerated arils have a short shelf life (3-5 days)
- Frozen arils are a year-round alternative but texture is slightly altered
Standardized Extract — Precision and Convenience
Pomegranate extract supplements are concentrated polyphenol preparations, typically standardized to 30-40% punicalagins by weight. A 500 mg capsule of 40%-punicalagin extract delivers approximately 200 mg of punicalagins — a substantial fraction of the punicalagin dose of an 8 oz juice serving but with zero sugar.
The Paller 2013 randomized trial gave 104 men with a rising prostate-specific antigen (PSA) 1 g/day or 3 g/day of a commercial pomegranate extract for up to 18 months, with no juice arm, and its PSA effects were similar to those reported in the original Pantuck juice trial. Median prostate-specific antigen doubling time lengthened from 11.9 to 18.8 months on 1 g and from 12.2 to 17.5 months on 3 g, with no significant difference between the two doses. Diarrhea occurred in 1.9% of men on 1 g and 13.5% of men on 3 g. The authors wrote that the significance of this slowing "remains unclear" and called for placebo-controlled studies.
The Pantuck 2015 placebo-controlled trial (183 men) also used extract, with a small juice group of 17 men. Median prostate-specific antigen doubling time rose from 12.9 to 14.5 months with extract (P = 0.13), from 11.1 to 15.6 months with placebo, and from 12.7 to 20.3 months with juice; none of these changes were statistically significant between the three groups. The authors concluded that, compared with placebo, pomegranate extract "did not significantly prolong" the doubling time.
Advantages of standardized extract:
- Zero sugar — a draw for people with diabetes, ketogenic dieters and calorie-restricted protocols
- Precise dosing — you know exactly how many milligrams of punicalagins per capsule
- Long shelf life (1-2 years in the closed bottle)
- Compact and travel-friendly
- Less expensive per unit polyphenol than premium juice
Disadvantages of standardized extract:
- Lacks the whole-food matrix — no fiber, no vitamin C, no anthocyanins (depending on the specific product formulation)
- Quality variation between brands — some products carry testing by independent third-party organizations
- Less psychologically satisfying than whole food for many people
- Most clinical trials of pomegranate used juice, not extract; the extract evidence base is smaller
People seeking the cardiovascular or prostate benefits of pomegranate without the sugar load often describe a 500-1,000 mg/day standardized extract as the most practical choice. Products differ in whether they specify punicalagin content (not just generic "pomegranate extract") and in whether they carry third-party certification.
Direct Urolithin A Supplements
The newest option is direct urolithin A supplementation, bypassing the pomegranate-to-microbiome conversion step entirely. The leading branded product, from a Swiss company, provides 500 mg of urolithin A per daily dose. Several generic urolithin A products have followed.
The rationale for direct urolithin A supplementation:
- Bypasses urolithin metabotype variability — UM-0 individuals (usually put at about 5-10% of adults) who cannot convert ellagitannins to urolithins are said to get no benefit from dietary pomegranate but full benefit from direct urolithin A. In Singh 2022 (European Journal of Clinical Nutrition, 100 people, sponsored by the maker), only 12% had detectable urolithin A at baseline, about 40% converted significantly after a glass of pomegranate juice, and a food product with 500 mg of urolithin A gave more than 6-fold the exposure of the juice; that study measured blood levels, not health benefit. UM-B individuals (about 20-25%) get intermediate conversion and may benefit from supplementation.
- Consistent plasma concentrations — direct urolithin A produces predictable, reproducible pharmacokinetics, whereas dietary pomegranate produces highly variable urolithin A levels depending on the day's microbiome state, recent antibiotic use, and substrate-loading history.
- Higher achievable plasma concentrations — direct supplementation can reach plasma urolithin A levels several-fold higher than dietary intake, which may be necessary for some therapeutic effects (particularly mitophagy induction in muscle).
The trade-off is cost. Branded urolithin A is substantially more expensive than pomegranate juice or extract on a per-day basis. For mitophagy-targeted indications (sarcopenia, age-related muscle decline, mitochondrial dysfunction), the direct urolithin A approach is often described as having the cleanest clinical evidence, at a premium price. Andreux 2019 tested safety and blood and muscle biomarkers over 4 weeks in healthy, sedentary elderly people, and Singh 2022 (European Journal of Clinical Nutrition) tested blood levels; neither tested sarcopenia or muscle outcomes, and both list authors employed by the maker. For general cardiovascular and prostate support in a person with a normal microbiome, dietary pomegranate is often considered adequate at much lower cost.
Two 2022 muscle trials, both with authors linked to the maker, came later. In 66 adults aged 65-90, 1,000 mg/day for 4 months improved muscle endurance in a hand muscle and a leg muscle and lowered some blood markers, but its primary endpoints, walk distance and muscle ATP (cell energy) production in the hand, showed no significant improvement over placebo (Liu 2022). In middle-aged adults given two doses for 4 months, muscle strength rose about 12%, but peak power output, the primary endpoint, did not significantly improve (Singh 2022, Cell Reports Medicine).
Sugar Content and Glycemic Impact
The sugar content of pomegranate forms:
- 8 oz commercial pomegranate juice: roughly 30-32 g sugar (mostly fructose and glucose). Glycemic index 53 (moderate). Glycemic load roughly 18 per serving (high).
- 1 cup arils (1 medium pomegranate): roughly 24 g sugar with 7 g fiber. Glycemic load roughly 14 per serving (moderate; fiber moderates the load).
- 1/2 cup arils: roughly 12 g sugar with 3.5 g fiber. Glycemic load roughly 7 per serving (low).
- 500 mg pomegranate extract capsule: less than 1 g carbohydrate. Glycemic load essentially zero.
- Direct urolithin A 500 mg capsule: less than 1 g carbohydrate. Glycemic load essentially zero.
For comparison: 12 oz of regular cola contains 39 g sugar; 8 oz orange juice contains 22 g; 1 medium apple contains 19 g sugar plus 4 g fiber.
For a person with diabetes or anyone monitoring glycemic load, the forms compare this way:
- 8 oz of pomegranate juice as a routine daily intake carries the 30-32 g sugar load listed above
- Whole arils (1/2 to 1 cup) add the fiber benefit
- Standardized extract or direct urolithin A bypass the sugar issue entirely
- Juice taken occasionally as part of a meal that includes protein, fat, and fiber is described as absorbing more slowly
One small study measured juice in diabetes directly, at a much smaller amount than 8 oz. In 10 people with non-insulin-dependent diabetes, 50 mL (1.7 oz) of pomegranate juice a day for 3 months "did not affect serum glucose, cholesterol and triglyceride levels" (Rosenblat 2006).
Cost and Practical Considerations
Approximate cost comparison for a daily dose delivering roughly 200-400 mg of punicalagins (US grocery store and supplement retailer pricing, 2026):
- 8 oz 100% pomegranate juice : $2-3 per serving. Roughly $60-90 per month for daily intake.
- 1 medium fresh pomegranate (in season): $2-4 per fruit, roughly 1 cup of arils. Comparable cost to juice when in season; significantly more expensive out of season.
- Frozen arils (1 cup serving): roughly $3-4 per serving from frozen-fruit bags. Year-round availability at predictable cost.
- Standardized pomegranate extract (500 mg/day): $15-25 per month from reputable brands. Most cost-effective per milligram of punicalagin.
- Direct urolithin A (branded, 500 mg/day): $60-100 per month at retail. Most expensive option.
A combination is a common practice: whole arils when in season for the fiber and food-matrix benefit, frozen arils or juice during off-season months, and standardized extract as a backup or for people with diabetes limiting the sugar load.
Seasonal Availability and Storage
Fresh pomegranates are a fall-and-early-winter fruit in the northern hemisphere — widely available October through January, with peak quality and lowest pricing in November and December. Imported southern-hemisphere fruit extends availability into spring at higher cost. By summer, fresh whole pomegranates are typically unavailable or of poor quality at extreme prices.
Storage:
- Whole intact pomegranates store well at room temperature for 1-2 weeks, or refrigerated for 2-3 months without significant polyphenol loss
- Pre-extracted fresh arils (refrigerated tubs from grocery stores) keep 3-5 days refrigerated
- Frozen arils keep 12 months in a household freezer with minimal polyphenol loss; texture softens slightly on thawing
- Commercial pomegranate juice (sealed) has a 9-12 month shelf life; once opened, refrigerated shelf life is 5-7 days
- Standardized extract capsules have 1-2 year shelf life if stored at room temperature in a closed bottle
The frozen arils option is particularly useful for year-round access at predictable cost — most US grocery stores carry frozen pomegranate arils (name brands or store brands) at around $5-6 per 12 oz bag.
How Each Form Is Used by Clinical Goal
Different goals are linked with different forms in the research and in common practice:
- General cardiovascular and antioxidant support — commonly described as whole arils 1/2 to 1 cup per day when in season; standardized extract 500 mg/day during off-season; or 4-8 oz juice with a meal.
- Targeted prostate-specific antigen-doubling-time extension in biochemical recurrence — the Pantuck 2006 protocol used 8 oz juice daily; Paller 2013 used 1 g/day or 3 g/day pomegranate extract. Practitioners describe at least 6 months with serial prostate-specific antigen monitoring. In the Pantuck 2015 placebo-controlled trial, none of the changes were statistically significant between groups.
- Carotid intima-media thickness regression in atherosclerosis — the Aviram 2004 protocol used 50 mL (1.7 oz) juice daily in 10 patients, 5 of whom continued for up to 3 years; the maximal effects came after 1 year, and further use "had no additional beneficial effects" on intima-media thickness (IMT). A proportional extract dose is sometimes suggested but was not tested. The largest artery trial (Davidson 2009) gave 240 mL/day of juice or a control drink to 289 people at moderate heart risk for up to 18 months and found no significant difference in overall carotid thickening; exploratory analyses suggested less progression in people with the worst blood-fat and oxidation markers.
- Blood pressure reduction — described as 4-8 oz juice daily, or 500-1,000 mg/day extract, with an effect reported within 2-4 weeks.
- People with diabetes seeking cardiovascular benefit — commonly described as standardized extract 500-1,000 mg/day in place of juice, or whole arils 1/2 cup with a mixed meal.
- Mitophagy and sarcopenia (older adults) — direct urolithin A 500 mg/day is often described as the most evidence-supported option, though the muscle trials missed their primary endpoints (see the urolithin A section). Dietary pomegranate is described as less reliable given metabotype variability with age.
- Anti-inflammatory or general healthspan — commonly described as whole arils when available, frozen arils otherwise. The fiber and microbiome benefits add value beyond pure punicalagin delivery.
- Limited budget — standardized extract 500 mg/day at roughly $15-20/month is the most cost-effective entry point.
Key Research Papers
- Tezcan F et al. (2009). Antioxidant activity and total phenolic, organic acid and sugar content in commercial pomegranate juices. Food Chemistry 115:873-877 — doi:10.1016/j.foodchem.2008.12.103
- Gil MI et al. (2000). Antioxidant activity of pomegranate juice and its relationship with phenolic composition and processing. Journal of Agricultural and Food Chemistry — PubMed PMID: 11052704
- Seeram NP et al. (2008). Comparison of antioxidant potency of commonly consumed polyphenol-rich beverages in the United States. Journal of Agricultural and Food Chemistry — PubMed PMID: 18220345
- Paller CJ et al. (2013). A randomized phase II study of pomegranate extract for men with rising PSA following initial therapy for localized prostate cancer (1 g vs 3 g of extract). Prostate Cancer and Prostatic Diseases — PubMed PMID: 22689129
- Pantuck AJ et al. (2015). A randomized, double-blind, placebo-controlled study of the effects of pomegranate extract on rising PSA levels in men following primary therapy for prostate cancer. Prostate Cancer and Prostatic Diseases — PubMed PMID: 26169045
- Mertens-Talcott SU et al. (2006). Absorption, metabolism, and antioxidant effects of pomegranate (Punica granatum L.) polyphenols after ingestion of a standardized extract in healthy human volunteers. Journal of Agricultural and Food Chemistry — PubMed PMID: 17090147
- Andreux PA et al. (2019). The mitophagy activator urolithin A is safe and induces a molecular signature of improved mitochondrial and cellular health in humans (direct urolithin A vs dietary). Nature Metabolism — PubMed PMID: 32694802
- Singh A et al. (2022). Direct supplementation with Urolithin A overcomes limitations of dietary exposure and gut microbiome variability in healthy adults to achieve consistent levels across the population. European Journal of Clinical Nutrition. PubMed PMID: 34117375
- Singh A et al. (2022). Urolithin A improves muscle strength, exercise performance, and biomarkers of mitochondrial health in a randomized trial in middle-aged adults. Cell Reports Medicine — PubMed PMID: 35584623
- Liu S et al. (2022). Effect of Urolithin A Supplementation on Muscle Endurance and Mitochondrial Health in Older Adults: A Randomized Clinical Trial. JAMA Network Open — PubMed PMID: 35050355
- Heber D et al. (2007). Safety and antioxidant activity of a pomegranate ellagitannin-enriched polyphenol dietary supplement in overweight individuals with increased waist size. Journal of Agricultural and Food Chemistry. PubMed PMID: 17966977
- Tomas-Barberan FA et al. (2017). Urolithins, the rescue of "old" metabolites to understand a "new" concept: metabotypes as a nexus among phenolic metabolism, microbiota dysbiosis, and host health status. Molecular Nutrition & Food Research — PubMed PMID: 27158799
- Rosenblat M et al. (2006). Anti-oxidative effects of pomegranate juice consumption by diabetic patients on serum and on macrophages. Atherosclerosis. PubMed PMID: 16226266
- Aviram M et al. (2004). Pomegranate juice consumption for 3 years by patients with carotid artery stenosis (50 mL/day dose). Clinical Nutrition — PubMed PMID: 15158307
- Davidson MH et al. (2009). Effects of consumption of pomegranate juice on carotid intima-media thickness in men and women at moderate risk for coronary heart disease. American Journal of Cardiology — PubMed PMID: 19766760
PubMed Topic Searches
Connections
- All Food
- Pomegranate (Main Page)
- Pomegranate Benefits Hub
- Punicalagins & Antioxidants
- Pomegranate for Prostate & Prostate-Specific Antigen
- Pomegranate for Cardiovascular Health
- Type 2 Diabetes
- Metabolic Syndrome
- Mitochondrial Support
- Antioxidant Therapy
- Walnuts (Ellagitannin Source)
- Raspberries (Ellagitannin Source)
- Vitamin C
- Hemoglobin A1c
- History
- Nutrients