Peripheral Neuropathy: Symptoms, Red Flags and What Helps
This page is written for the person living with it — what it feels like, what is known to help, and which signs are urgent. For the clinical reference on the same condition — epidemiology, pathophysiology, staging and treatment — see Peripheral Neuropathy in Neurology.
Table of Contents
- Overview: The Damage Behind the Symptom
- What It Actually Feels Like
- The Stocking-Glove Pattern
- The Common Causes
- Serious and Less Common Causes
- Red Flags: Signs Treated as Urgent
- How It Is Evaluated
- What Helps: Self-Care and Physical Measures
- What to Expect Over Time
- Connections
- Key Research Papers
- Featured Videos
Overview: The Damage Behind the Symptom
Peripheral neuropathy means the nerves outside your brain and spinal cord — the long cables running to your hands, feet, skin, and internal organs — are injured or dying back. It is not one disease; more than a hundred conditions can start the process.
Here is the distinction worth keeping. Our Numbness and Tingling page is about the sensation — pins and needles, the arm that went dead because you slept on it, which has causes with nothing to do with nerve damage: a pinched nerve root, poor circulation, hyperventilation, low calcium. Peripheral neuropathy is what you have when the numbness comes from real injury to the fibres themselves — the wiring is degenerating, not temporarily squashed.
It is common and under-recognised: roughly 2–3% of adults, about 8% over age 55. Half of people with diabetes develop it, and many already have measurable damage on the day they are diagnosed. Three facts shape the rest of this page:
- Nerves die back from the far end first. That is why it starts in the toes and why it is symmetrical.
- Some causes are fully reversible and some are not. A B12 deficiency caught at six months is a different story from one caught at three years, which is why early recognition changes the outcome.
- Even an irreversible cause can be slowed and its symptoms treated. "Nothing can be done" is almost never true.
What It Actually Feels Like
The words people use tell a doctor which kind of nerve fibre is failing. Nerves are a bundle of different-sized fibres with different jobs, and they do not fail in lockstep.
Small-Fibre Symptoms (Pain and Temperature)
The thinnest fibres carry pain, heat, cold, and itch, and also run sweating and blood-vessel tone. When they go first, the experience is loud:
- Burning in the soles, worst at night — like standing on hot sand or walking on gravel.
- Allodynia — the bedsheet hurts; light touch is read as pain. Real, well documented, and often disbelieved by others.
- Lost temperature sense, so scalding bathwater goes unnoticed, plus dry, cracked, hairless skin, because the same fibres run the sweat glands.
Large-Fibre Symptoms (Touch, Vibration, Position)
The thick fibres carry vibration, light touch, and proprioception — your unconscious sense of where your limbs are. When these fail the experience is quiet, which is exactly why it is dangerous:
- Numbness like thick socks, a rubber glove, or felt between foot and floor.
- Balance trouble in the dark, because vision had been quietly compensating for the lost position sense.
- Not feeling an injury: a blister, a tack in the shoe, a pebble worn all day. This is the road to a diabetic foot ulcer.
Motor and Autonomic Symptoms
Later, motor fibres join in: toes that will not lift, tripping on carpet edges, unsteady wide-based walking, and thinning of the muscle between thumb and index finger. Autonomic fibres cause lightheadedness on standing, early fullness after small meals, diarrhoea alternating with constipation, and either absent sweating or drenching sweats in odd places.
The Stocking-Glove Pattern
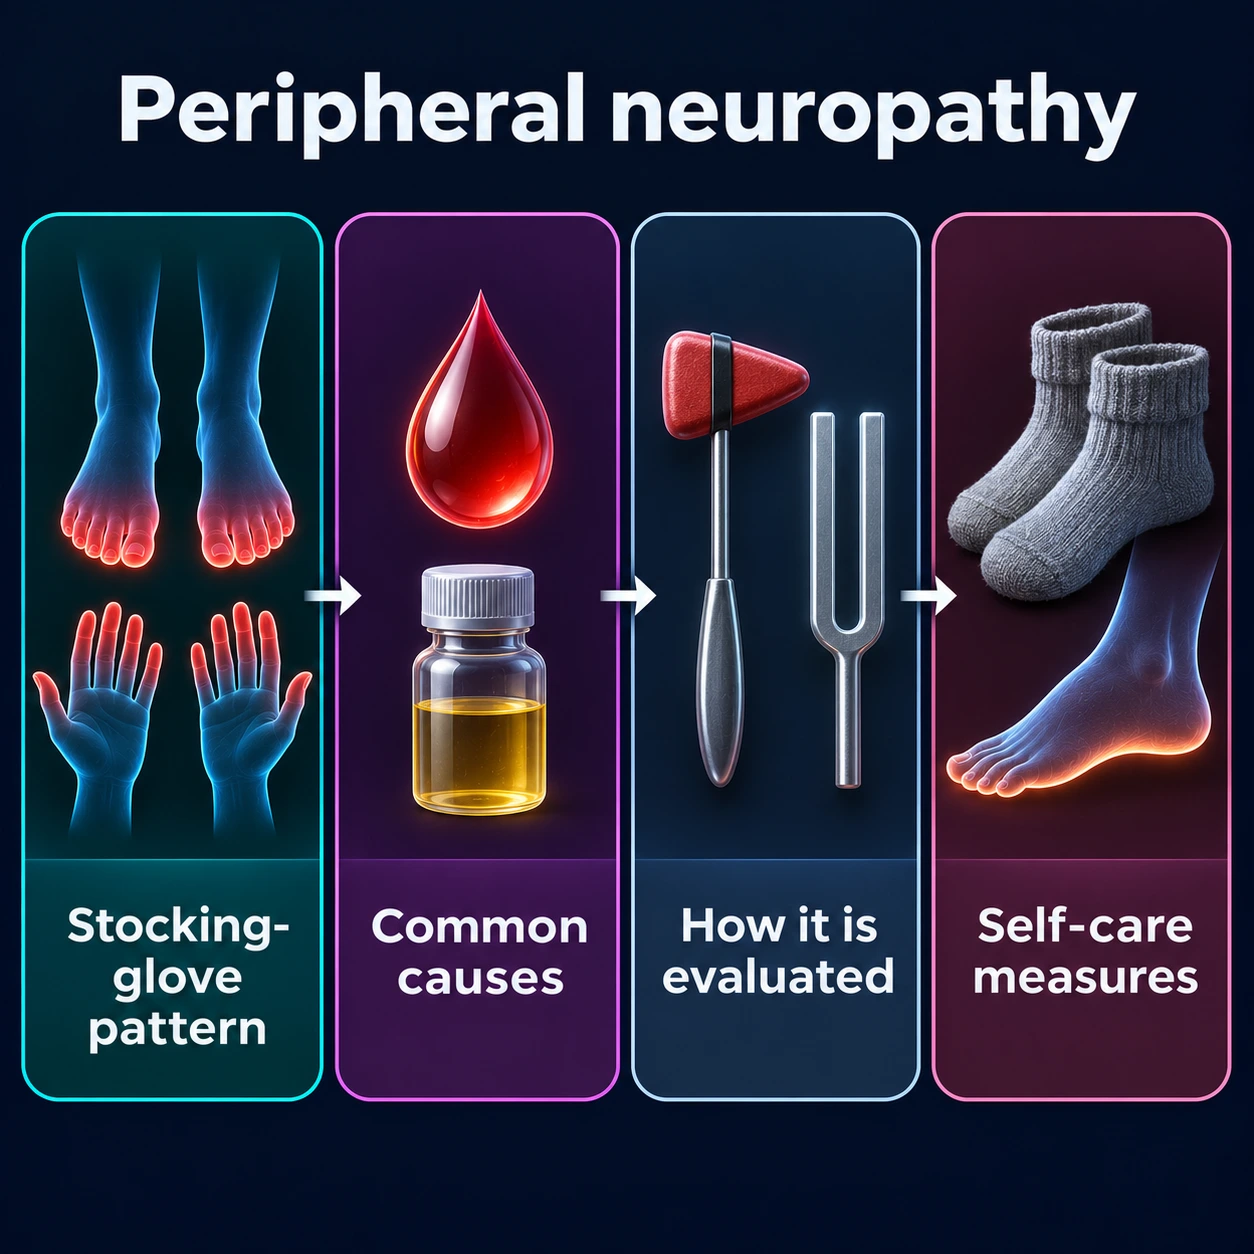
The most useful clue in neuropathy is where it is. Most metabolic and toxic neuropathies produce a distal symmetric polyneuropathy, called the stocking-glove pattern because the affected area looks like an invisible sock, and later an invisible glove, drawn onto the body. Departures from it — asymmetry, a band of numbness around the trunk, hands before feet — point elsewhere, and are listed under Red Flags.
The reason is mechanical. One sensory nerve cell in your lower back must maintain a metre of axon reaching your big toe, supplied from a cell body the size of a speck of dust. That is expensive to run, so when anything degrades the cell's energy supply, transport machinery, or blood supply, the far end is abandoned first — length-dependent, or dying-back, degeneration. So it begins in both feet at once, in the toes, equally on each side; it ascends slowly over months to years, often with a clear border at a sock line; and the hands join later, once the legs are affected to roughly the knee, because arm nerves are shorter.
The Common Causes
Roughly half of all polyneuropathy is diabetic or prediabetic. Most of the rest comes from a short list: nutritional deficiency, alcohol, medications and chemotherapy, thyroid disease, kidney failure, and the genuinely idiopathic group.
Diabetic and Prediabetic Neuropathy
The largest single cause worldwide. High glucose damages nerves several ways at once — oxidative stress overwhelming the axon's mitochondria, advanced glycation end-products stiffening proteins, and injury to the tiny vasa nervorum capillaries that feed the nerve, which is therefore starved and poisoned at the same time.
It starts before the diagnosis. Impaired glucose tolerance alone is associated with small-fibre neuropathy, and many people labelled "idiopathic" turn out to have an abnormal 2-hour glucose tolerance test. And tight glucose control helps type 1 more than type 2: a Cochrane review found new neuropathy down by 1.84% a year in type 1 (1,228 people), against 0.58% a year in type 2 (6,669 people), which was not formally significant (P = 0.06). Severe low blood sugar episodes increased in both types. Triglycerides, obesity, hypertension, and smoking carry independent weight in type 2, so glucose is not the only target. Screening is described as annual, starting at diagnosis in type 2.
Chemotherapy-Induced Peripheral Neuropathy (CIPN)
Several chemotherapy classes are directly neurotoxic, and this is a leading reason treatment gets dose-reduced or stopped. In a large meta-analysis, about 68% of patients had neuropathy within the first month and around 30% still had it at six months.
- Platinum drugs (cisplatin, oxaliplatin) accumulate in the dorsal root ganglia, which sit outside the blood–nerve barrier and are unprotected. Oxaliplatin also causes an acute cold-triggered dysesthesia — a cold drink brings immediate electric throat tightening and hand cramping — and platinum neuropathy is notorious for coasting, worsening for weeks to months after the last dose.
- Taxanes (paclitaxel, docetaxel) disrupt the microtubule railway carrying supplies down the axon; vincristine can abolish ankle reflexes early; bortezomib and thalidomide cause a painful small-fibre neuropathy, often dose-limiting in myeloma.
New numbness, burning, or buttoning difficulty matters most when it is reported at the visit it starts, not at the end of the cycle. Early dose modification is the only intervention with strong evidence for preventing permanent damage — the 2020 American Society of Clinical Oncology (ASCO) guideline update found no agent recommended for preventing this neuropathy, which makes early reporting the whole strategy.
Vitamin B12 Deficiency
B12 builds and maintains myelin, and its deficiency causes a neuropathy that is often fully reversible if caught early and permanent if not — the most important treatable cause to look for. Advanced deficiency also involves the spinal cord (subacute combined degeneration), adding severe balance loss and brisk rather than absent reflexes.
The risk list is longer than most people expect: metformin, whose long-term use lowers B12 in the very patients already at risk of diabetic neuropathy, so the two get conflated; years of acid suppression; pernicious anaemia; gastric bypass and celiac disease; unsupplemented vegan diets; and nitrous oxide, which inactivates B12 directly and can cause a devastating neuropathy in weeks. Critically, a "normal" serum B12 does not rule this out — damage occurs in the 200–350 pg/mL grey zone, so when the level is borderline and the picture fits, the follow-up tests are methylmalonic acid and homocysteine, which rise before B12 falls. See Vitamin B12.
Alcohol-Related Neuropathy
Heavy drinking damages nerves twice over: ethanol and acetaldehyde are directly toxic to axons, and heavy drinkers are frequently short of thiamine (vitamin B1) and folate because alcohol displaces food and impairs absorption. The result is a painful, burning, small-fibre-predominant neuropathy of the feet. Abstinence plus repletion — thiamine first, before any glucose-containing intravenous (IV) fluid, to avoid precipitating Wernicke encephalopathy — halts progression, and partial recovery over months is common. See Alcohol Use Disorder and Vitamin B1.
Other Metabolic and Drug Causes
Hypothyroidism causes a generalised neuropathy and predisposes to compression neuropathies such as carpal tunnel syndrome, so a thyroid-stimulating hormone (TSH) test is part of the standard workup, and chronic kidney disease produces a uraemic neuropathy that improves with adequate dialysis. Vitamin B6 cuts both ways: deficiency causes neuropathy, but chronic pyridoxine above roughly 50–100 mg daily causes a severe sensory neuronopathy, which happens to people taking well-meant high-dose B-complex supplements (see Vitamin B6). A 2026 census of US supplement labels found 5.1% of adult products directing 100 mg/day or more and 9.1% above 50 mg/day; 56.2% of those at 100 mg or more were not sold as B6 or B-complex products. The US upper limit is 100 mg/day, and other jurisdictions use lower limits such as 12 mg/day. Copper deficiency mimics B12 deficiency after bariatric surgery. Prolonged metronidazole, nitrofurantoin, isoniazid, and amiodarone are reported drug causes, and testing for environmental toxins is generally reserved for a real exposure history.
Idiopathic (Cryptogenic) Sensory Polyneuropathy
After a thorough workup, a quarter to a third of cases have no identified cause. This group is the one most often dismissed, and the dismissal is not warranted: it is a real diagnosis with a known behaviour — onset usually after 55, sensory-predominant, very slowly progressive, rarely causing significant weakness, not shortening life. It is usually revisited periodically, because some cases later prove to have impaired glucose tolerance or a monoclonal protein.
Serious and Less Common Causes
Individually uncommon, but not to be missed: most are treatable and several are time-critical.
Guillain-Barré Syndrome and Chronic Inflammatory Demyelinating Polyneuropathy
Guillain-Barré syndrome is an acute autoimmune attack on nerve myelin, often two to four weeks after a diarrhoeal or respiratory infection. It presents as rapidly ascending weakness and numbness over hours to days with lost reflexes, and can progress to paralysis of the breathing muscles. It is an emergency — immunoglobulin or plasma exchange works, and works better early. Chronic inflammatory demyelinating polyneuropathy (CIDP) is its chronic cousin, evolving over more than eight weeks with weakness in the proximal muscles as well as the distal ones, absent reflexes, and little pain. Immunotherapy can restore function, yet it is regularly misdiagnosed for years as "just diabetic neuropathy." Weakness out of proportion to numbness is the tell.
Subcutaneous efgartigimod is a newer treatment studied for chronic inflammatory demyelinating polyneuropathy. In the ADHERE trial, 214 of 322 people (66%) improved on open-label treatment; among responders, relapse occurred in 27.9% of those staying on it and 53.6% of those switched to placebo (hazard ratio 0.39). The authors state that longer-term data and comparison with currently available treatments still need further study.
Vasculitis, Monoclonal Proteins, and Amyloid
Inflammation of the small arteries feeding nerves makes individual nerves infarct one at a time, producing mononeuritis multiplex — a stepwise, asymmetric, painful pattern, such as a wrist drop this week and a foot drop next month. It occurs in systemic vasculitis and Sjögren's syndrome, and is treated with urgent immunosuppression. Separately, an abnormal antibody protein from a clone of plasma cells turns up in roughly one in ten otherwise unexplained neuropathies, which is why protein electrophoresis and free light chains belong in the workup. AL amyloidosis is the one to catch: painful small-fibre neuropathy plus autonomic failure plus weight loss, bilateral carpal tunnel, or heart failure is the pattern that leads to urgent haematology referral.
Inherited transthyretin amyloidosis also causes polyneuropathy and now has drug treatments. A 2026 network analysis of 6 trials (989 people) found improvement over placebo on a nerve score with each drug assessed on it. Gene-silencing drugs looked strongest, though the authors call this hypothesis-generating, with few data and no head-to-head trials.
Infections and Inherited Disease
Human immunodeficiency virus (HIV), Lyme disease, leprosy (still the leading infectious cause worldwide), and shingles with its postherpetic neuralgia all belong on the list. Charcot-Marie-Tooth disease is the commonest inherited neuropathy, around 1 in 2,500; the clues are onset in childhood or the teens, very high arches or hammer toes, and little pain for the amount of deformity.
Red Flags: Signs Treated as Urgent
Most neuropathy develops over years and is worked up in clinic. The features below change that: they mean the process is fast, asymmetric, or compressing something, and the window for preventing permanent damage is measured in hours to days.
Signs Hospitals Treat as Emergencies
- Weakness or numbness climbing your legs over hours to days, especially with lost reflexes — possible Guillain-Barré syndrome, which hospitals do not treat as a routine-appointment problem.
- Difficulty breathing, a weak cough, or trouble swallowing with new weakness — the breathing and swallowing muscles may be failing.
- Numbness in the saddle area (inner thighs, genitals, buttocks) with new loss of bladder or bowel control, plus back pain — this is cauda equina syndrome, a surgical emergency, not a neuropathy.
- A band of numbness around the chest or abdomen, or a clear horizontal cut-off on the trunk — that level points to the spinal cord.
- Sudden foot drop or wrist drop, particularly with fever, rash, or joint pain — possible vasculitic nerve infarction.
- A hot, red, swollen or deformed foot in someone with diabetes — possible Charcot foot or deep infection. A numb foot can be badly infected and barely hurt.
- Severe new numbness after nitrous oxide use — acute B12 inactivation moves that fast.
Signs Usually Checked Within Days, Not Months
- Marked asymmetry — one foot or hand clearly worse, named nerves failing in sequence, symptoms starting in the hands, or rapid progression that is noticeably worse this month than last.
- Weakness out of proportion to numbness, or weakness in thighs and shoulders rather than only feet — a pattern that points to chronic inflammatory demyelinating polyneuropathy, which is treatable.
- Unexplained weight loss, night sweats, or fever alongside the neuropathy — see Unexplained Weight Loss and Night Sweats.
- Fainting on standing, inability to sweat, severe constipation or diarrhoea, or early fullness after eating — autonomic involvement narrows the differential considerably. See Lightheadedness on Standing.
- Any new foot ulcer, blister, dark callus, or wound that is not healing. In a numb foot this is urgent regardless of how it looks or feels.
How It Is Evaluated
A good workup answers three questions in order: Is this really neuropathy? What pattern is it? What is causing it? Skipping to the third is how people end up with expensive scans and no answer.
The Bedside Examination
Most of the diagnosis is made here, with a few dollars of equipment: the 10-gram monofilament pressed on the sole until it buckles, where failure to feel it marks a foot at risk of ulceration; a 128 Hz tuning fork on the big toe joint, since vibration loss is often the earliest large-fibre finding; pinprick and cold mapped upward to find the top of the "stocking"; ankle reflexes, where absent ankle jerks with intact knee jerks is the signature of a length-dependent process; the Romberg test, in which swaying with eyes closed means proprioception rather than the inner ear is failing; and foot inspection of skin, nails, calluses, and pulses.
Blood Tests
- Fasting glucose and hemoglobin A1c (HbA1c), and if both are normal a 2-hour oral glucose tolerance test, which catches impaired glucose tolerance that hemoglobin A1c misses.
- Vitamin B12, with methylmalonic acid and homocysteine if borderline.
- Serum protein electrophoresis with immunofixation and free light chains — the test most often left out, and the one that finds amyloidosis.
- Thyroid-stimulating hormone, a blood count, a metabolic panel, and erythrocyte sedimentation rate (ESR) or C-reactive protein (CRP).
Nerve Testing
Nerve conduction studies and electromyography (EMG) confirm neuropathy, separate axonal from demyelinating damage (a critical fork — demyelinating patterns raise treatable chronic inflammatory demyelinating polyneuropathy or a hereditary neuropathy), and show whether motor fibres are involved. One caveat matters enormously: they assess only large fibres, so a normal electromyography study does not rule out small-fibre neuropathy, and many patients are wrongly told their symptoms are not real on the strength of a normal study. Skin punch biopsy for intraepidermal nerve fibre density is the reference test for small fibres; spine magnetic resonance imaging (MRI) and lumbar puncture are added when the pattern suggests cord disease, Guillain-Barré syndrome, or chronic inflammatory demyelinating polyneuropathy.
What the doctor is ruling out, in plain terms: an inflammatory neuropathy needing immunotherapy this week, a treatable deficiency that becomes permanent if missed, a plasma-cell disorder or cancer signalling itself through the nerves, a cauda equina problem masquerading as neuropathy, and a drug or supplement quietly causing all of it that could simply be stopped.
What Helps: Self-Care and Physical Measures
Two goals run in parallel: stop the damage progressing, and make daily life liveable. Treating the cause means glucose control, B12 or thiamine repletion, stopping alcohol or the offending drug, thyroid replacement, adequate dialysis, or immunotherapy for chronic inflammatory demyelinating polyneuropathy. In type 2 diabetes especially, glucose is not the only target: triglycerides, blood pressure, weight, and smoking are independently linked to progression, and addressing them is part of the nerve treatment.
Exercise — The Most Underrated Intervention
This is the measure patients most often dismiss. Supervised aerobic plus resistance exercise reduces neuropathic symptoms and pain. In a 2012 pilot study of 17 people with diabetic peripheral neuropathy, a 10-week supervised programme was followed by less pain and more nerve fibre branching in a skin biopsy taken from the upper part of the leg, which hints at structural change as well as symptom relief. It had no control group, and the authors state the findings need validating against one. The routine usually described is 30 minutes of moderate activity most days, strength work twice weekly, and deliberate balance training such as tandem stance or tai chi.
Foot Protection
A numb foot cannot report injury, and roughly 15% of people with diabetes develop a foot ulcer, almost always with neuropathy as the precursor. A 2023 review estimates that healed diabetic foot ulcers come back in 42% of people at 1 year and 65% at 5 years, and that pressure-relieving footwear lowered ulcer risk (13.3% against 25.4% with usual care). The routine described to prevent amputations:
- Both feet inspected every day, soles and between the toes included — a mirror on the floor or a phone camera shows the soles.
- Shoes worn at all times, indoors and out, and shaken out every time. Pebbles, tacks, and coins cause a startling number of ulcers.
- Bathwater tested with an elbow or thermometer, not the foot, because a numb foot does not register scalding; heating pads on numb feet carry the same risk.
- Well-fitted shoes with a wide, deep toe box, custom insoles for people with deformity or a previous ulcer, and calluses trimmed by a podiatrist rather than at home, where a numb foot cannot feel a cut.
Falls, Night Pain, and Therapy
Neuropathy roughly doubles fall risk, mostly through lost position sense. The usual measures are removing throw rugs, night-lights on the route to the bathroom, shower grab bars, and a cane or walking poles on uneven ground — a pole restores some of the ground information your feet have stopped sending. Pain reliably worsens at night, and many people describe relief from keeping feet cool — a fan or a bed cradle holding the sheets off the toes. Insomnia covers sleep loss that has become its own problem. Physiotherapy offers gait retraining, balance work, and an ankle-foot orthosis for foot drop.
Supplements: What the Evidence Shows
Replacing documented deficiencies — B12, thiamine, folate, copper — at proper therapeutic doses is the only supplement intervention with strong evidence. Alpha-lipoic acid at 600 mg daily has the best data among the optional supplements, with modest symptom improvement in trials such as SYDNEY 2. That trial gave 181 people treatment for only 5 weeks: the symptom score fell 51% at 600 mg against 32% on placebo, and nausea, vomiting and vertigo rose with the dose. High-dose vitamin B6 is a known hazard here — above roughly 50–100 mg daily long term it can cause neuropathy. It turns up beyond B6 products, including "nerve support" formulas, which often pair a hazardous dose of B6 with a sensible dose of B12.
When Medication Is Warranted
Medication is for pain and sleep disruption. No current drug reverses nerve damage or restores numb sensation, which is worth being clear-eyed about, because a treatment aimed at the wrong target will always feel like a failure. When pain interferes with sleep, walking, work, or mood, that is the point at which medication is generally offered. The number needed to treat is how many people take a drug for one extra person to get relief. A 2015 meta-analysis gave 6.4 for serotonin-norepinephrine reuptake inhibitors, 7.7 for pregabalin and 7.2 for gabapentin for a 50% reduction in neuropathic pain, lower for tricyclics, with treatment effects overstated by about 10% through publication bias. Its 2025 update, counting responders at 50% or 30% reduction or moderate relief, gave 4.6 for tricyclics, 7.4 for serotonin-norepinephrine reuptake inhibitors and 8.9 for the gabapentin-pregabalin class. Most people get partial relief, a minority get substantial relief, some get none. A 30–50% reduction with better sleep is a genuine success; expecting zero pain sets up an endless drug rotation.
The largest head-to-head trial, OPTION-DM (130 people with diabetic nerve pain analysed), compared amitriptyline, duloxetine and pregabalin pathways. Pain fell from 6.6 to 3.3 out of 10 in all three, with no significant difference between them. People with poor relief on one drug who added a second improved by 1.0 point, against 0.2 for those staying on one.
- Duloxetine (a serotonin-norepinephrine reuptake inhibitor), 30 mg daily for a week then 60 mg. Strong evidence in diabetic neuropathy, and notably the one agent with positive randomised-trial evidence in chemotherapy-induced neuropathic pain. The size of that effect is small: in the 231-person trial the mean difference from placebo was 0.73 points out of 10 over 5 weeks, and the same 2020 oncology guideline states that the amount of benefit from duloxetine is limited. Also treats coexisting depression; first-week nausea usually settles.
- Gabapentin, titrated over weeks toward 1,800–3,600 mg daily in divided doses. Cheap and widely used, but frequently prescribed at ineffective doses and then written off — 300 mg at night is a starting dose, not a treatment dose. Sedation and ankle swelling are the usual limits.
- Tricyclics — amitriptyline, or better tolerated in older adults nortriptyline, 10–25 mg at bedtime titrating toward 75 mg. Effective, inexpensive, and usefully sedating at night, but anticholinergic effects and cardiac conduction risk limit use over about 65.
- Topicals are underused: 5% lidocaine patches have almost no systemic absorption and suit frail or heavily medicated people, and the capsaicin 8% patch is a single clinic-applied treatment lasting up to three months. Their measured effect is smaller than the oral drugs': the 2025 Neuropathic Pain Special Interest Group (NeuPSIG) analysis gives a number needed to treat of 14.5 for lidocaine 5% plasters (very low certainty) and 13.2 for capsaicin 8% patches, both second-line with a weak recommendation.
Opioids sit at the bottom of the published ladder for chronic neuropathic pain: the same 2025 analysis lists them as third-line with a weak recommendation (number needed to treat 5.9, number needed to harm 15.4, low certainty), and reviews show at best modest short-term benefit, no long-term function gain, and substantial harms — tolerance, dependence, hyperalgesia, falls. For people already on long-term opioids, the approach described is slow, supported tapering with a better regimen in place, not an abrupt stop. Pain-focused cognitive behavioural therapy meaningfully improves function and distress, and spinal cord stimulation has randomised evidence in refractory painful diabetic neuropathy. See Neuropathic Pain.
What to Expect Over Time
A damaged axon with an intact cell body can regrow, but at roughly 1 millimetre per day — about an inch a month, so regrowing from ankle to toes takes months and from the knee down closer to a year. Demyelinating injury, where the insulation rather than the wire is damaged, recovers much faster once the cause is removed; if the nerve cell body itself has died, that fibre does not come back. The practical consequence: improvement is invisible week to week. Progress shows across three-to-six-month intervals, and a monthly log of pain score, walking distance, and stumbles makes it visible.
- B12, thiamine, and copper deficiency — often substantial or complete recovery if treated within months, partial at a year, and frequently permanent after prolonged deficiency, especially where the spinal cord was involved.
- Drug-, toxin-, and chemotherapy-induced — usually stabilises and improves after withdrawal, with most recovery in the first six to twelve months, though platinum drugs coast for a few weeks first and fine fingertip sensation recovers less completely than pain does.
- Diabetic — slowly progressive, but the rate is modifiable. Sensation already lost is rarely regained; further loss usually can be prevented. Pain may subside as numbness deepens, which is not improvement.
- Idiopathic sensory polyneuropathy — the most reassuring natural history: very slow progression, weakness uncommon, disability driven by pain and balance rather than paralysis, no effect on life expectancy.
Two closing points. Chronic neuropathic pain carries a high rate of coexisting depression and anxiety, and treating those improves pain scores too. And "it's just neuropathy, nothing can be done" is rarely the whole story, and neuromuscular specialists are the clinicians who focus on this — the list of treatable causes above is long, the workup that finds most of them is a single blood draw, and a normal nerve conduction study does not mean your small fibres are healthy.
Connections
Key Research Papers
Key Research Papers
- Pop-Busui R, Boulton AJM, Feldman EL, et al. Diabetic Neuropathy: A Position Statement by the American Diabetes Association. Diabetes Care. 2017;40(1):136-154. — PubMed PMID: 27999003
- Seretny M, Currie GL, Sena ES, et al. Incidence, prevalence, and predictors of chemotherapy-induced peripheral neuropathy: a systematic review and meta-analysis. Pain. 2014;155(12):2461-2470. — PubMed PMID: 25261162
- Smith EML, Pang H, Cirrincione C, et al. Effect of duloxetine on pain, function, and quality of life among patients with chemotherapy-induced painful peripheral neuropathy: a randomized clinical trial. JAMA. 2013;309(13):1359-1367. — PubMed PMID: 23549581
- Loprinzi CL, Lacchetti C, Bleeker J, et al. Prevention and Management of Chemotherapy-Induced Peripheral Neuropathy in Survivors of Adult Cancers: ASCO Guideline Update. J Clin Oncol. 2020;38(28):3325-3348. — PubMed PMID: 32663120
- Finnerup NB, Attal N, Haroutounian S, et al. Pharmacotherapy for neuropathic pain in adults: a systematic review and meta-analysis. Lancet Neurol. 2015;14(2):162-173. — PubMed PMID: 25575710
- Callaghan BC, Little AA, Feldman EL, Hughes RAC. Enhanced glucose control for preventing and treating diabetic neuropathy. Cochrane Database of Systematic Reviews. 2012;(6):CD007543. — PubMed PMID: 22696371
- Ziegler D, Ametov A, Barinov A, et al. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Care. 2006;29(11):2365-2370. — PubMed PMID: 17065669
- Kluding PM, Pasnoor M, Singh R, et al. The effect of exercise on neuropathic symptoms, nerve function, and cutaneous innervation in people with diabetic peripheral neuropathy. J Diabetes Complications. 2012;26(5):424-429. — PubMed PMID: 22717465
- Soliman N, Moisset X, Ferraro MC, et al. Pharmacotherapy and non-invasive neuromodulation for neuropathic pain: a systematic review and meta-analysis. Lancet Neurol. 2025;24(5):413-428. — PubMed PMID: 40252663
- Tesfaye S, Sloan G, Petrie J, et al. Comparison of amitriptyline supplemented with pregabalin, pregabalin supplemented with amitriptyline, and duloxetine supplemented with pregabalin for the treatment of diabetic peripheral neuropathic pain (OPTION-DM): a multicentre, double-blind, randomised crossover trial. Lancet. 2022;400(10353):680-690. — PubMed PMID: 36007534
- Allen JA, Lin J, Basta I, et al. Safety, tolerability, and efficacy of subcutaneous efgartigimod in patients with chronic inflammatory demyelinating polyradiculoneuropathy (ADHERE): a multicentre, randomised-withdrawal, double-blind, placebo-controlled, phase 2 trial. Lancet Neurol. 2024;23(10):1013-1024. — PubMed PMID: 39304241
- Duarte GS, Machado TLGN, Rodrigues FB, et al. Pharmacological Interventions for Hereditary Transthyretin-Related Amyloidosis With Polyneuropathy: Systematic Review and Network Meta-Analysis. Eur J Neurol. 2026;33(6):e70627. — PubMed PMID: 42266139
- Staiger B. Vitamin B6 Doses on United States Dietary Supplement Labels Relative to the Tolerable Upper Intake Level: A Census of the National Institutes of Health Dietary Supplement Label Database. Cureus. 2026;18(10):e118244. — PubMed PMID: 42903915
- Armstrong DG, Tan TW, Boulton AJM, Bus SA. Diabetic Foot Ulcers: A Review. JAMA. 2023;330(1):62-75. — PubMed PMID: 37395769